





Introduction
Shortly after the arrival of powerful, publicly available generative artificial intelligence (AI) tools such as OpenAI’s ChatGPT, they were quickly deployed by many researchers to assist in their research and manuscript preparation. This quickly led to questions about the role of these technologies as authors or tools (Armitage, Reference Armitage2024). ChatGPT was credited as an author on at least four research papers (Stokel-Walker, Reference Stokel-Walker2023), which was swiftly condemned by the research community (one preprint on medRxiv listed ChatGPT as a co-author (Kung et al., Reference Kung, Cheatham, Sillos, De Leon, Elepaño, Madriaga, Aggabao, Diaz-Candido, Maningo and Tseng2022) yet its subsequent publication in PLOS Digital Health did not credit the large language model with authorship) (Kung et al., Reference Kung, Cheatham, Medenilla, Sillos, De Leon, Elepaño, Madriaga, Aggabao, Diaz-Candido, Maningo, Tseng and Dagan2023). While the status of AI tools as non-authors has been clarified, the broader question of how AI tools should be appropriately used in academic research remains inconsistently answered across publishers and journals, even as scholars increasingly integrate these technologies into their research and writing processes.
In primary health care, the implications of AI tool adoption require particular attention. Primary health care researchers work across diverse settings with varying technological resources, which makes clear and accessible guidance essential for maintaining research integrity while enabling legitimate use of these powerful tools. While some professional organizations including the International Committee of Medical Journal Editors (ICMJE) and the Committee on Publication Ethics (COPE) have developed guidance for AI use in manuscript preparation, the adoption of these recommendations varies across journals, creating a patchwork of policies that can confuse authors and compromise editorial consistency.
To the best of our knowledge, AI policies among primary health care journals have not been reviewed. This review addresses this gap by assessing the availability and content of AI policies across primary health care journals and their publishers. By examining both journal-level and publisher-level AI policies, this review characterizes the current state of AI use governance in primary health care publishing and explores the implications of policy variations.
Methods
Journal selection
We conducted searches for primary health care journals across three databases on 16 July 2025: SCImago Journal & Country Rank (SJR), Google Scholar, and a Google search.
SJR is a publicly available portal that includes the journals and country-specific indicators developed from the information contained in the Scopus database (SCImago Journal and Country Rank, 2025) (Scopus is an abstract and citation database of peer-reviewed literature including scientific journals, books, and conference proceedings) (Scopus, 2025). SJR was searched for primary health care journals listed under Subject area ‘Medicine’ > Subject category ‘Family Practice’ (SCImago Journal & Country Rank, 2025). 40 journals were identified in this search.
The search was supplemented with Google Scholar’s publicly available list of top 20 primary health care journals (Categories > Health & Medical Sciences > Primary Health Care) according to their h5-index (Google Scholar, 2025). After removing duplicates, seven additional journals were identified.
Finally, a Google search of ‘primary health care journal‘ was carried out and the primary health care journals from the first 20 results were collected. Nine such journals were collected. After removing duplicates, three additional journals were identified.
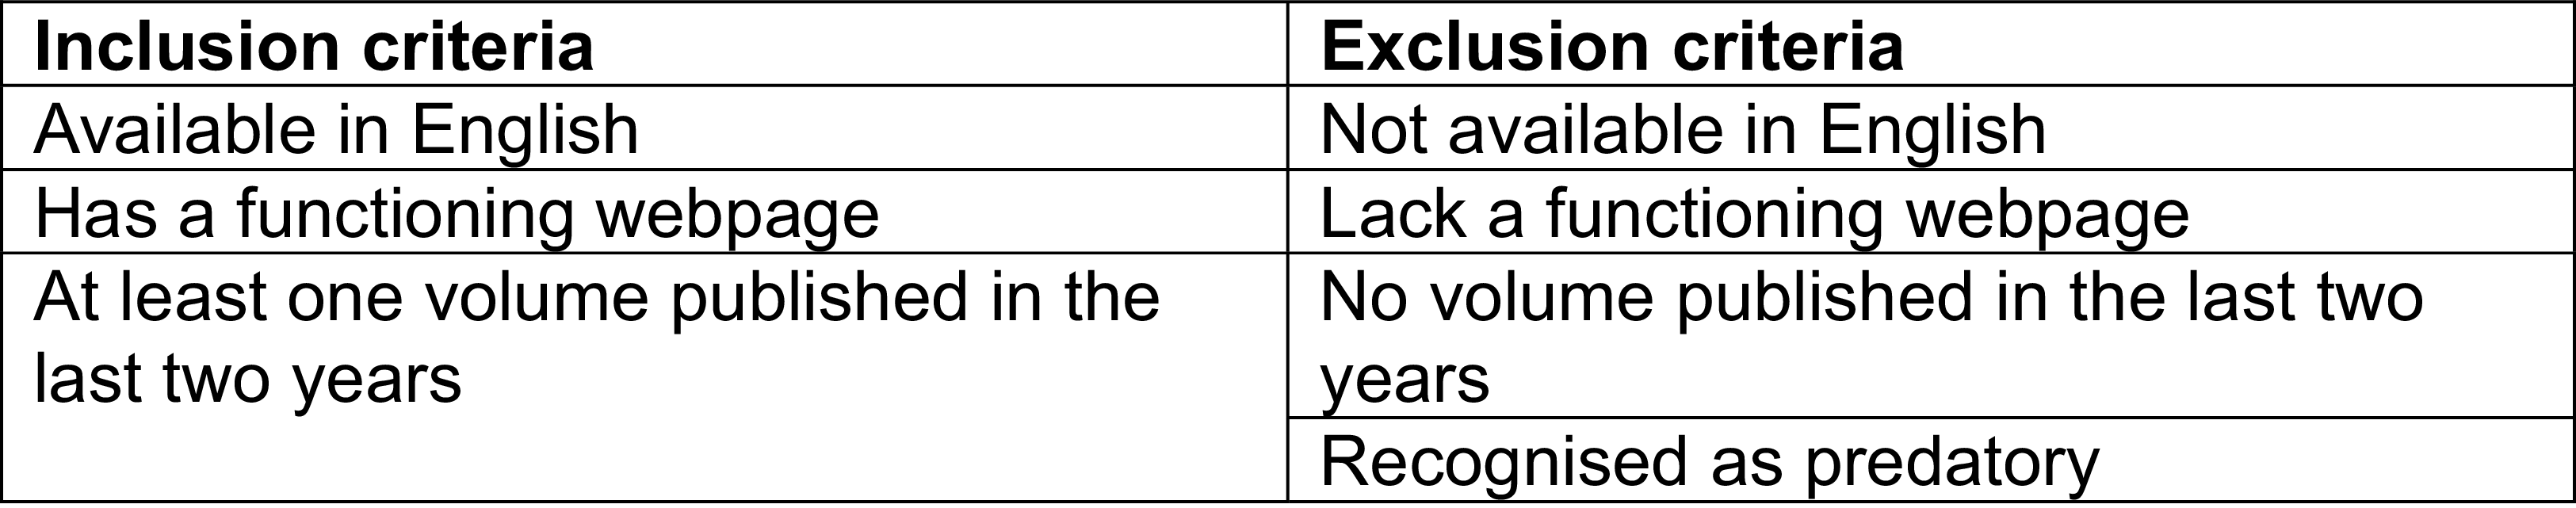
After removing duplicates, 50 unique journals were identified and screened (see inclusion and exclusion criteria in Figure 1).
Inclusion and exclusion criteria.

Figure 1. Long description
A table with two columns and three rows, detailing inclusion and exclusion criteria. The first column is labeled ‘Inclusion criteria’ and the second column is labeled ‘Exclusion criteria’. Row 1: Available in English, Not available in English. Row 2: Has a functioning webpage, Lack a functioning webpage. Row 3: At least one volume published in the last two years, No volume published in the last two years, Recognised as predatory.
Journals that were not in English, that lacked a functioning webpage, or that did not have a volume published within the last two years were excluded. All journals and publishers were checked against recognized criteria for predatory status (Nishikawa-Pacher, Reference Nishikawa-Pacher2022) (predatory journals claim to be legitimate scholarly publications but misrepresent their publishing practices such as by falsely claiming to provide peer review, hiding information about article processing charges, and misrepresenting members of the journal’s editorial board) (Elmore and Weston, Reference Elmore and Weston2020). Those recognized as predatory journals or publishers were excluded. This resulted in a final sample of 41 journals. The Preferred Reporting Items for Systematic Reviews and Meta-Analyses flow diagram (Page et al., 2020) for this review can be found in Figure 2 (Haddaway et al., Reference Haddaway, Page, Pritchard and McGuinness2022).
Preferred Reporting Items for Systematic Reviews and Meta-Analyses flow diagram.

The final sample of journals and their publishers included in the review can be found in Figure 3.
Final sample of journals and their publishers included in the study.

Figure 3. Long description
A table listing journals and their publishers in the field of family medicine and general practice. The table has 41 rows and 3 columns. The columns are labeled ‘Journal (alphabetical order)’, ‘Publisher’, and an index number. The table lists various journals focused on family medicine and general practice along with their respective publishers. The journals are listed in alphabetical order. The publishers include a variety of academic and professional organizations. The table provides a comprehensive overview of the journals and publishers in this specific field.
Search strategy
The thorough identification of AI policies within primary health care journals required examination of both journal-specific and publisher-level policy frameworks. Contemporary academic publishing operates within a hierarchical structure in which individual journals function under parent publishers who oversee editorial production, distribution, and financial operations. While journals maintain editorial independence, their policies are often constrained by broader publisher guidelines. Accordingly, journals might operate under publisher-mandated AI policies that are not explicitly stated at the journal level. Consequently, comprehensive AI policy identification required examination of both journal-level statements and publisher-level frameworks to ensure complete coverage of applicable AI guidelines.
One reviewer (RA) reviewed each journal’s homepage, author guidelines, submission policies, and editorial policies for references to the use of AI. Each journal was categorized as No for Journal AI Policy in a MS Excel document (henceforth: spreadsheet) if no statement relating to AI was found at the journal level. If such a statement was found, the journal was categorized as Yes for Journal AI Policy in the spreadsheet and select relevant language from the policy was copied into it under Journal AI Policy: Language.
If the journal was categorized as No for Journal AI Policy, the reviewer then searched for a statement from the publisher relating to AI. The publisher was categorized as No for Publisher AI Policy in the spreadsheet if no AI statement was found at the publisher level. If such a statement was found, the publisher was categorized as Yes for Publisher AI Policy in the spreadsheet and select relevant language from the policy was copied into it under Publisher AI Policy: Language.
In cases where no AI statement was found at both the journal level and publisher level, one reviewer (RA) emailed the journal or the journal editor to ascertain whether an AI policy is available.
If a journal was found to have a journal-level or publisher-level AI policy, the policy was summarized by the reviewer as either permissive or non-permissive. A policy was deemed non-permissive if it does not accept manuscripts that have received any form of AI assistance to any degree, and permissive if it is favourable to considering manuscripts that have received AI assistance.
To enhance the credibility of the search, a second reviewer (AAO) independently assessed the final sample of journals and, when relevant, their publishers for statements relating to AI. Any conflicts between the reviewers were resolved by discussion. There were no cases in which consensus could not be achieved, representing complete inter-rater agreement across all assessments. Formal inter-rater reliability statistics were not calculated, as the binary categorization of policy presence and permissiveness involved minimal interpretive ambiguity. This study is best characterized as a structured policy audit rather than a qualitative content analysis, reflecting its focus on systematic identification and description of existing policy frameworks.
Online assessments took place between 18 July 2025 and 21 July 2025, inclusive. The acceptance of email responses was available until 05 March 2026.
Results
Of the 41 journals assessed, 33 (80.5%) were found to have a publicly available AI policy – 21 (51.2%) at the level of the journal level and 12 (29.3%) at the level of the publisher. Eight (19.5%) journals – Anatolian Journal of Family Medicine, Canadian Family Physician, Chinese Journal of General Practitioners, Eurasian Journal of Family Medicine, Hong Kong Practitioner, Malaysian Family Physician, Primary Health Care Practice Journal, and Russian Family Doctor – had no identifiable publicly available AI policy at the journal level or at the publisher level (see Figure 4).
Pie chart of identifiable AI policies at journal level and publisher level.

All 33 publicly available AI policies were summarized as permissive – none completely prohibited the use of AI assistance in manuscript preparation, and all indicated willingness to consider manuscripts that had received AI assistance (see Figure 5).
AI policy or absence by journal/publisher, and whether AI policy is permissive or non-permissive.

Figure 5. Long description
The table lists 33 journals and publishers, detailing their AI policies. It includes columns for the journal’s name, publisher, identifiable AI policy, whether the policy is permissive or non-permissive, and relevant policy language. Each row provides specific information about the AI policy of the respective journal or publisher. For example, the African Journal of Primary Health Care and Family Medicine has a permissive policy requiring disclosure of AI use. The American Family Physician also has a permissive policy, mandating disclosure of AI use. The Anatolian Journal of Family Medicine has no identifiable policy. The table continues with similar details for each listed journal and publisher, summarizing their stance on AI assistance in manuscript preparation.
In all of the eight cases where no AI statement was found at either the journal level or publisher level, only one journal – Canadian Family Physician – replied to the reviewer’s email to ascertain whether an AI policy is available. The response explained that the journal’s AI policy is not listed on the website of the journal or the publisher, but is included in the journal’s submission and peer review platform, ScholarOne. Because the policy is not available on the journal’s homepage, author guidelines, submission policies, or editorial policies, and similarly unavailable at the publisher level, the journal was recorded as having no identifiable policy.
Discussion
This study finds that while a majority (80.5%) of primary health care journals have established publicly available AI policies, significant challenges remain in policy accessibility and implementation. For authors in primary health care who might use AI to assist in manuscript preparation, the absence of universal and accessible AI policies creates uncertainty and potential threats to compliance.
The finding that one in five primary health care journals lacks any identifiable public AI policy reveals a substantial gap in guidance for primary health care researchers. Even among journals with such policies, their inconsistent location at the journal level (51.2%) and publisher level (29.3%) generates potential confusion among authors. Authors might be uncertain whether a publisher’s AI policy applies to their target journal, particularly when the journal does not explicitly reference the publisher’s policy on its webpages. The example of Canadian Family Physician, which located its AI policy within its submission platform but not in publicly accessible locations, exemplifies how hidden policies can generate confusion and create compliance challenges. This inconsistent transparency might cause hesitancy among authors: those who disclose AI assistance in manuscript preparation might worry that editors will reject their work based on undeclared standards, while those who do not disclose AI assistance due to unclear guidelines face potential ethical concerns if AI involvement is later discovered. Furthermore, the absence of transparent AI policies could lead to inconsistent editorial decision-making because editors on the same journal’s editorial board might regard the permissibility of AI assistance differently.
While all the publicly available AI policies identified were permissive to the submission of manuscripts that have received AI assistance, they each contained all or a combination of the following five conditions for the use of AI to be considered acceptable: disclosure of AI use, the tasks that AI tools can be used for, AI tools not constituting authorship, author responsibility for submitted work, and AI usage by peer reviewers.
Disclosure of AI use
All AI policies required authors to disclose if AI tools have been used to assist the production of the manuscript. This disclosure might be within the manuscript itself (such as in the Methods section), in the submission portal, in the cover letter to the editor, or in all or a combination of these locations. For example, the British Journal of General Practice’s AI policy states that ‘authors can use generative AI and AI-assisted technologies for writing manuscripts or language editing, and these should be declared and clearly described at submission in the cover letter to the editor and in the Methods (or Acknowledgements, where appropriate) section of the article, stating why and how the tool was used‘. Some policies require disclosure of the exact AI model(s) used and the tasks with which they assisted. The AI policies of some journals, such as the Korean Journal of Family Medicine, adhere to ICMJE guidelines regarding the use of AI in manuscript preparation, which states that ‘authors who used AI technology to conduct the study should describe its use in the methods section in sufficient detail to enable replication of the approach including the tool used, version, and prompts where applicable‘ (International Committee of Medical Journal Editors, 2025). Others, such as the Australian Journal of General Practice, adopt the COPE position statement, which includes that ‘authors who use AI tools in the writing of a manuscript… must be transparent in disclosing in the Materials and Methods (or similar section) of the paper how the AI tool was used and which tool was used’ (Committee on Publication Ethics, 2023).
Tasks that AI tools can be used for
Some AI policies state which tasks can and cannot be completed with the assistance of AI tools in the process of manuscript preparation, such as for idea generation, literature summarization, study design, language translation, data analysis, content writing, copy editing, and image production. For example, the AI policy of Family Practice states that ‘the use of AI, for example, to help generate content or images, write code, process data, or for translation) should be disclosed both in cover letters to editors and in the Methods or Acknowledgements section of manuscripts‘. The AI policy of BMC Primary Care’s publisher permits AI-assisted copy editing, which it considers to constitute ‘AI-assisted improvements to human-generated texts for readability and style, and to ensure that the texts are free of errors in grammar, spelling, punctuation and tone‘, but does not permit AI-assisted ‘generative editorial work and autonomous content creation‘.
AI and authorship
No AI policy recognizes AI tools as satisfying their criteria for authorship, and none permit AI tools to be listed as authors in submitted manuscripts. For example, Family Medicine and Community Health’s AI policy stated that ‘AI technologies will not be accepted as an author(s) of any content submitted to BMJ for publication. BMJ only recognizes humans as being capable of authorship since they must be accountable for the work‘. Others, such as The Lancet Primary Care, adopt the COPE position statement, which includes that ‘AI tools cannot meet the requirements for authorship as they cannot take responsibility for the submitted work. As non-legal entities, they cannot assert the presence or absence of conflicts of interest nor manage copyright and license agreements’ (Committee on Publication Ethics, 2023).
Author responsibility for submitted AI-assisted work
Some AI policies explicitly state that authors who use AI tools in the production of their manuscript remain entirely responsible for any submitted work that has received assistance from AI tools. For example, the AI policy of the Journal of General and Family Medicine states that ‘the author is fully responsible for the accuracy of any information provided by the [AI] tool and for correctly referencing any supporting work on which that information depends‘, while that of the Journal of Primary Care & Community Health’s publisher states that ‘authors are responsible for ensuring their submission is accurate and meets the standards for rigorous scholarship‘. Others, such as BJGP Open, adopt the COPE position statement, which includes that ‘authors are fully responsible for the content of their manuscript, even those parts produced by an AI tool, and are thus liable for any breach of publication ethics‘ (Committee on Publication Ethics, 2023).
AI usage by peer reviewers
Some AI policies discuss the use of AI in the peer review process. Many AI policies explain that manuscripts submitted to journals for consideration are confidential and copyrighted by their respective authors, meaning there is a risk associated with inputting any section or all of the submitted manuscript to an AI tool to assist with the peer review process. While some policies prohibit entirely the use of AI tools for the peer review process, others recommend against it but request transparent declaration if they are used. For example, the AI policy of the publisher of BMC Primary Care states that ‘if any part of the evaluation of the claims made in the manuscript was in any way supported by an AI tool, we ask peer reviewers to declare the use of such tools transparently in the peer review report‘, while the AI policy of Family Medicine states that ‘the editorial team prefers that reviewers do NOT use AI in their peer review… If peer reviewers do elect to use an AI tool the editors ask that reviewers disclose to the editors how the tool was used in the review‘.
While all AI policies were summarized as permissive, the variety in the conditions under which AI assistance is considered acceptable across journals and publishers deepens the potential confusion among authors who submit manuscripts to primary health care journals. This highlights the importance for authors to pay close attention to the requirements of the AI policy of the specific journal (or its publisher) to which they are submitting manuscripts. Notably, several journals explicitly aligned their AI policies with established frameworks from the ICMJE or COPE, suggesting that these bodies are emerging as de facto standard-setters in this space. However, adoption of these frameworks remained partial and inconsistent across the sample, indicating that even where authoritative guidance exists, its uptake is not universal. Future research might also examine whether AI policy adoption clusters among major publishers, varies by geography or journal impact factor, or tracks temporal trends in AI governance more broadly.
Limitations
This study has limitations. First, data were collected over a brief period. Given the rapidly evolving nature of AI technology and its adoption, AI policies are likely to change frequently, potentially limiting the long-term validity of these findings. Future research incorporating version tracking of AI policies over time would enable longitudinal analysis of policy evolution and adoption trends. Second, the study was limited to English-language journals, potentially overlooking AI policies in non-English primary health care publications and limiting the generalisability of findings to global publishing practices. This Anglophone bias is particularly notable given that primary health care has strong global coverage, with significant research published in non-English journals that may operate under distinct governance norms. Third, the study relied on searches of SJR, Google Scholar, and Google and therefore might not have captured all relevant primary health care journals, particularly newer or specialized publications. Fourth, while the study excluded recognized predatory journals, the criteria for identifying such publications might not be comprehensive or universally agreed upon. Fifth, where no journal-level AI policy was identified, the study assumed that the publisher-level AI policy applies to all journals under that publisher, yet individual journals might have established their own AI policy that was not publicly available. Sixth, as demonstrated by Canadian Family Physician, some journals might have AI policies embedded in their submission platforms that were not captured in this study. Seventh, only one of the eight journals without identifiable journal-level or publisher-level AI policies responded to the reviewer’s email, which limits understanding of whether such policies exist but are not publicly accessible. Eighth, no formal quality scoring instrument was applied to the identified policies, as no validated tool currently exists for assessing the quality, clarity, enforceability, or comprehensiveness of AI publishing policies. The permissive/non-permissive dichotomy employed here, while appropriate as a high-level summary, does not fully capture degrees of conditionality in policy requirements; future work might develop a more granular classification framework.
Recommendations
The study’s findings lead to the following five recommendations: first, all primary health care journals that currently lack an AI policy should establish one. Second, all AI policies should be publicly available and easily located on the journal’s website (or at least on the publisher’s website). No AI policy should be exclusively located within the journal’s submission platform such that authors can be aware of the policy’s requirements before preparing their manuscripts. Third, all AI policies should address the five core elements revealed in this study: AI use disclosure requirements, acceptable AI tasks, AI authorship considerations, author responsibility, and peer review guidelines. Fourth, AI policies should evolve as the abilities of these tools increase to adapt to their consequences in academic research and publishing. Fifth, future research should complement policy audits with stakeholder analysis, incorporating editorial perspectives, author compliance experiences, and comparisons between society-owned and commercially published journals, to better understand the practical implementation and impact of AI policies.
Conclusion
This study reveals that significant gaps remain in accessibility and standardization of AI policies in primary health care journals. This fragmented governance landscape, characterized by inconsistent policy locations and varying requirements, might create confusion for authors and compromise research integrity.
Although all identified policies were permissive toward AI use, the heterogeneous requirements across journals undermine effective governance. This is particularly concerning in primary health care journals, where research directly informs clinical practice. The findings highlight an urgent need for easily accessible, standardized AI policies. Such improvements would enable researchers to harness AI’s potential while maintaining the transparency and scientific rigour essential to primary health care research.
Data availability statement
All data are available in the submitted documents.
Acknowledgements
Not applicable.
Author contributions
Richard Armitage: conceived the idea, collected, reviewed, and analyzed the data, and wrote the first draft of the manuscript.
Amani Al-Oraibi: independently reviewed the data and reviewed the manuscript.
Funding statement
The authors received no funding for this work.
Competing interests
The authors declare no competing interests.
Ethical standards
No ethical approval required as this was a review of existing policies.
Consent for publication
All authors consent to this manuscript being published.


 Open access

