





Our brains have an incredible capacity for learning, but even more impressive, perhaps, is our ability to identify when to learn versus when to rely on pre-existing knowledge. One way we do this is by keeping track of the statistics of our environment to determine how likely things are to change from moment to moment (Mathys, Daunizeau, Friston, & Stephan, Reference Mathys, Daunizeau, Friston and Stephan2011; Soltani & Izquierdo, Reference Soltani and Izquierdo2019; Yu & Dayan, Reference Yu and Dayan2005). In stable environments, we can ignore random events that deviate from our expectations and instead rely on long-run averages to guide our decision-making (Behrens, Woolrich, Walton, & Matthew, Reference Behrens, Woolrich, Walton and Rushworth2007). In volatile environments, where the state of the world is known to change, we should learn from our prediction errors in order to adapt our decision-making to the new conditions. Computational models of decision-making characterize this by estimating an individual’s ‘learning rate’, which determines the balance between new and old information when updating a belief (Sutton & Barto, Reference Sutton and Barto1998). Using these methods, healthy individuals have been shown to increase their learning rate in response to greater environmental volatility (Behrens et al., Reference Behrens, Woolrich, Walton and Rushworth2007; Blain & Rutledge, Reference Blain and Rutledge2020) when learning from both positive and negative events (Browning et al., Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015; Gagne, Zika, Dayan, & Bishop, Reference Gagne, Zika, Dayan and Bishop2020).
Outside of normative models, there is considerable interest in the computations that fuel decision-making from a clinical perspective. For example, it is well established that individuals suffering from internalizing disorders experience intolerance of uncertainty (Boswell, Thompson-Hollands, Farchione, & Barlow, Reference Boswell, Thompson-Hollands, Farchione and Barlow2013; Dugas, Gagnon, Ladouceur, & Freeston, Reference Dugas, Gagnon, Ladouceur and Freeston1998; Saulnier, Allan, Raines, & Schmidt, Reference Saulnier, Allan, Raines and Schmidt2019). Such intolerance is often associated with the feeling that the world is unpredictable, leading to avoidance, indecision, and distress (Dugas et al., Reference Dugas, Sexton, Hebert, Bouchard, Gouin and Shafran2022). One possibility is that these adverse reactions to uncertainty stem from difficulties detecting and adjusting to changes in the state of the world (Bishop & Gagne, Reference Bishop and Gagne2018). Indeed, it has been shown that individuals with high levels of trait anxiety (n = 30) are less able to adjust their learning rate in response to environmental volatility during threat avoidance learning (Browning et al., Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015). Gagne et al. (Reference Gagne, Zika, Dayan and Bishop2020) extended this work showing that impaired learning rate adaptation was related to a general factor of anxious-depression in a mixed sample of healthy controls and people with major depressive disorder or generalized anxiety disorder (n = 86) and an online crowdsourced sample using both reward pursuit and loss avoidance paradigms (n = 147).
These cross-sectional findings suggest that impaired learning rate adaptation is a possible mechanism underlying anxious-depression. This opens several interesting avenues for research, including leveraging individual differences to understand why certain treatments are effective for some, but not others, or laying the foundation for novel and targeted interventions. To progress these aims, however, longitudinal designs are necessary to understand cause and effect. For example, it is not clear if impaired learning rate adaptation is a consequence of experiencing high levels of anxious-depression, a ‘tax’ on the brain’s attention system, or a predisposing trait that tends not to fluctuate. Likewise, it is unclear if impairments in learning rate adaptation are improved by interventions that alleviate anxiety and depression. A recent study of eating disorders suggested this could be the case, where there were differences in learning rate adaptation between those who had recovered versus those with persistent symptoms (Pike et al., Reference Pike, Sharpley, Park, Cowen, Browning and Pulcu2023).
However, there are inconsistencies in the published record that require consideration. Hammond, Xu, Ai, and Van Dam (Reference Hammond, Xu, Ai and Van Dam2023) did not find a significant relationship between general distress and learning rate adaptation in two samples (n = 100; n = 88), and in the punishment condition in this task, the direction of effects was actually reversed. Pulcu and Browning (Reference Pulcu and Browning2017) found the opposite, a marginally significant association between anxiety and learning rate adaptation in a loss avoidance context (n = 30), but there were no significant effects in the reward condition, and no associations with depressive symptoms in either context. More recently, a series of five studies (total n = 550) failed to replicate the association with anxiety using a variety of tasks (Satti et al., Reference Satti, Wille, Nassar, Cichy, Schuck, Dayan and Bruckner2025). This aligns with similar challenges replicating this effect in other studies (Blain & Rutledge, Reference Blain and Rutledge2020; Jassim et al., Reference Jassim, Waade, Parsons, Petzschner, Rua, Rodgers, Baron-Cohen, Suckling, Mathys and Lawson2025). One explanation for these mixed findings is that a true effect, if present, is small and considerably larger samples are required to estimate it.
The present study aimed to address these issues by examining whether learning rate adaptation is associated with individual differences in anxious-depression in a large treatment-seeking sample. Specifically, the Precision in Psychiatry (PIP) study (Lee et al., Reference Lee, Palacios, Richards, Hanlon, Lynch, Harty, Claus, Swords, O’Keane, Stephan and Gillan2023, Reference Lee, Richards, Heinzle, Hanlon, Lynch, Harty, Claus, O’Keane, Stephan, Whelan and Gillan2025) followed two transdiagnostic patient cohorts as they initiated a course of either internet-based cognitive behavioral therapy (iCBT) (n = 677) or antidepressant therapy (n = 95), over a four-week period. An additional group of healthy participants (n = 95) were also followed for four weeks without intervention. We aimed to establish the continuous relationship between learning rate adaptation and anxious-depression in each sample and test whether learning rate adaptation changes following iCBT or antidepressant therapy, and if any such changes relate to symptom improvements.
Methods
Participants
iCBT group
Participants receiving iCBT via the SilverCloud Health platform were recruited from two sites: the Berkshire Healthcare NHS Foundation Trust (UK) and Aware Ireland, a mental health charity that provides free services to individuals suffering from mood disorders. Participants were 18–70 years old, fluent in English, and had access to a computer. They also had to score ≥ 10 on the Work and Social Adjustment Scale (WSAS: Mundt, Marks, Shear, & Greist, Reference Mundt, Marks, Shear and Greist2002) and be within 2 days of starting treatment. A total of 2404 participants were screened for the iCBT group, of which 1496 were deemed eligible, and 836 provided baseline data. For the present study, we included only those who provided complete baseline and follow-up data on the aversive learning task and mental health measures (n = 677).
Antidepressant group
Participants initiating a course of antidepressant medication were recruited through online (Google Ads, social media platforms, charity websites) and in-print (pharmacies, GP surgeries, counselling clinics, newsletters) advertisements. Like the iCBT arm, participants were between 18 and 70 years old, fluent in English, had access to a computer, scored ≥10 on the WSAS (Mundt et al., Reference Mundt, Marks, Shear and Greist2002), and were within 2 days of starting their treatment. They were required to upload a photograph of their antidepressant prescription for verification. There was no requirement for participants to be medication-free prior to the study; participants could be either initiating or changing their antidepressant medication. A total of 270 participants were screened, of which 174 were deemed eligible, and 102 provided baseline data. After exclusion for missing follow-up data (n = 7), the sample consisted of 95 participants.
Healthy participant group
Participants who self-reported no mental health disorders were recruited through advertisements posted online, mailing lists, and around the Trinity College Dublin campus. To be eligible, participants had to score < 10 on the WSAS (Mundt et al., Reference Mundt, Marks, Shear and Greist2002) and not be receiving any treatment for their mental health. These participants were matched for sociodemographic characteristics with the antidepressant group. A total of 444 participants were screened for the healthy participant group, of which 245 were deemed eligible, and 113 provided baseline data. After exclusion for missing follow-up data (n = 18), 95 participants were analyzed.
Mental health measures
Participants completed an assessment of three transdiagnostic factor scores of ‘anxious-depression’ (AD), ‘social withdrawal’ (SW), and ‘compulsivity and intrusive thought’ (CIT) at baseline and follow-up. These scores are derived from nine self-report questionnaires detailed in the supplement. Responses on these measures are transformed into transdiagnostic dimensions by multiplying each item score by a corresponding beta weight (derived from a previous factor analysis: Gillan et al., Reference Gillan, Kosinski, Whelan, Phelps and Daw2016). We also performed a new factor analysis in the iCBT group to check if the factor structure was consistent with a previously gathered crowdsourced sample and found high consistency (Supplementary Figure S8), with correlation of weights ranging from r = .87 to r = .96.
Aversive learning task
At both baseline and follow-up, participants completed a gamified version of an aversive learning task (Behrens et al., Reference Behrens, Woolrich, Walton and Rushworth2007; Browning et al., Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015). This task is designed to capture the degree to which participants adapt their learning rate in response to environmental volatility (Figure 1). A full description of the task is available in the Supplement. In brief, the task consisted of two blocks of 70 trials, which differed in the volatility of response-outcome contingencies (Figure 1). Participants were informed that they should choose the urchin that was less likely to steal but that this could change throughout the game. They were also asked to consider the magnitude of loss on each trial, as at times it may be strategic to risk choosing the stealing urchin if the potential loss was comparatively small. In the stable block, one of two sea urchins consistently stole from the participant in 75% of trials. In the volatile block, the underlying choice-outcome contingencies switched approximately every 20 trials, meaning the other urchin became aversive (i.e. the urchin switched between stealing on 80% of trials to 20% of trials). Participants completed both blocks in one run (140 trials total) and were not notified of any changes of block or task contingencies. At each session, participants were randomly allocated to receive one of two task schedules: stable first or volatile first, denoting the order in which they received the stable and volatile blocks.
(a) Example trial of the Deep Sea Task, an aversive learning task in which participants had to avoid losing points (‘pearls’) by keeping track of the changing response-outcome contingencies of two sea urchins. On each trial, participants were presented with a choice between a blue and orange urchin that differed in the number of points they could potentially steal (displayed on the urchin). Participants selected their choice via keypress, which either led to a loss (left choice) of the corresponding number of points, or a safe trial (right choice), where no points (pearls) were deducted. The running total of points was on display throughout at the top of the screen. (b) Outcome probabilities throughout the task, indicating the likelihood of the urchin stealing across the stable and volatile blocks. At each session, participants were randomly allocated to complete one of two schedules: stable first (top) or volatile first (bottom; adapted from Browning et al. (Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015)).

Figure 1. Long description
Panel A, titled Example Choice Trial, depicts a flowchart of the Deep Sea Task. At the top, a central diver icon faces a blue urchin labeled 53 and an orange urchin labeled 76. A treasure chest at the top center shows a score of 5000. Two arrows point downward to the next stage.
On the left path, labeled Left Choice, a green glow surrounds the blue urchin. Below this, the Stealing Urchin outcome shows the blue urchin with a mean face, the diver recoiling, and the treasure chest score reduced to 4947 with a minus 53 label.
On the right path, labeled Right Choice, a green glow surrounds the orange urchin. Below this, the Safe Urchin outcome shows the blue urchin with a mean face but the diver remains safe, and the treasure chest score stays at 5000.
Panel B contains two line graphs showing percent Urchin Steals on the y-axis from 0 to 100 against Trial Number on the x-axis from 0 to 140.
The top graph shows a stable first schedule. A gray shaded area from trial 0 to 70 indicates a stable block where the probability is constant at 75 percent. From trial 70 to 140, the white area indicates a volatile block where the probability square-waves between 20 percent and 80 percent every 20 trials.
The bottom graph shows a volatile first schedule. The gray shaded area from trial 0 to 70 shows the volatile square-wave pattern between 20 percent and 80 percent. From trial 70 to 140, the white area indicates a stable block where the probability remains constant at 75 percent.
Modelling of choice behavior
To capture behavior on the aversive learning task, we fit an extended Rescorla–Wagner model (previously described in Behrens et al., Reference Behrens, Woolrich, Walton and Rushworth2007; Browning et al., Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015) to participant choice data. The basic model has three free parameters: learning rate (α), an inverse temperature or choice stochasticity parameter (β), and a risk preference parameter (λ). The primary parameter of interest was learning rate, which captures the degree to which participants update their estimates about the urchins based on recent information versus longer-run averages. In this model, the probability that the blue urchin will steal pearls on the present trial (
$ {p}_t $
 ) is calculated based on the previous trial’s outcome (
$ {o}_{t-1} $
 ), using a Rescorla–Wagner learning rule:

Here the learning rate (
$ \alpha $
 ) determines the degree to which the participant relies on the prediction error (
$ {o}_{t-1}-{p}_{t-1} $
 ) to update their estimated probability of the urchin stealing on the next trial. This outcome probability is then additively combined with the difference in outcome magnitudes (
$ {m}_{blue},{m}_{orange} $
 ; i.e. the number of pearls to be stolen) between the two urchins (
$ {v}_t $
 ). This additive mixture is adjusted by a risk parameter (λ), which determines the relative importance of magnitude and probability in guiding participants’ choices:

Finally, a softmax action selector is used to generate action probabilities stochastically, incorporating an inverse temperature parameter (β) that captures the degree to which participants use the trial-by-trial additive mixture of probability and magnitude to guide their choices (
$ c $
 ):

This model was fit to each participant individually, separately for their stable and volatile blocks. Parameters were estimated using a Bayesian grid-search where individual parameter estimates were taken as the expected value of the marginal probability density function over that parameter, obtained by direct integration. The standard deviation of parameter estimates was computed in the same way. Further details on the specification of the model, including parameter recovery, model comparison to a version with an alternative specification of the risk parameter (where probabilities and magnitudes are multiplied, not added) are available in the supplement. We also describe a Hierarchical Bayesian Estimation (HBE) sensitivity analysis in the supplement. Briefly, the key difference is that in the HBE analysis, (1) we analyse stable and volatile blocks together and directly estimate learning rate adaptation within the model, and (2) models are fit to data from each group of participants (iCBT, control, antidepressant), rather than person-by-person. None of these alternative analyses changes the conclusions of the paper.
Statistical analyses
We analyzed the parameter estimates generated by the reinforcement learning model in linear models to assess the effect of volatility on learning rate (α), the relationship between learning rate adaptation (Δα) and anxious-depression scores and how this relationship changes following treatment. For completeness, the same analyses were repeated for the two remaining parameters: inverse temperature (β) and risk preference (λ). All models were adjusted for age and sex, and conducted in R version 4.1.1 (R Core Team, 2021). To quantify the continuous relationship between learning rate adaptation (Δα) and mental health factors, we performed separate linear regression analyses for each participant group. In these models, we regressed baseline (week 0) learning rate adaptation (Δα: αvolatile - αstable) onto AD, CIT, and SW. We examined if changes in symptoms from baseline to follow-up were related to changes in learning rate adaptation using Pearson correlation. We estimated test–retest reliability of the main model parameters in the control group, who underwent no intervention. We calculated the intra-class correlation (ICC2,1) from their baseline to week 4 scores on learning rate and learning rate adaptation. We did not perform any correction for multiple comparisons. Data quality was assessed using catch questions and behavioral performance criteria detailed in the supplement and used for sensitivity analyses.
Results
Sample characteristics
At baseline, the three participant groups had no differences in their level of education (X 2(4,867) = 7.02, p = .135) or sex (X 2(2,867) = 1.39, p = .499). However, iCBT participants were older than the control group (M diff = 3.47 years, t (126) = 2.72, p = .007) (Supplementary Table S2), the latter of whom were recruited to match the similarly sized antidepressant arm.
As expected, at baseline, the three groups differed in terms of their AD scores (F (2,861) = 217.9, p < .001), with treatment groups reporting significantly greater anxiety and depression symptoms than the control group (iCBT M diff = 1.78, antidepressant M diff = 2.11; both p < .001), and the antidepressant group reporting greater symptoms than the iCBT group (M diff = 0.34, p < .001). The same pattern was found for the CIT factor (F (2,861) = 35.60, p < .001), with both treatment groups having greater CIT scores than the control group (iCBT M diff = 0.68, p < .001; antidepressant M diff = 0.94, p < .001), and the antidepressant group being the most severe (versus iCBT M diff = 0.27, p = .011). There was no difference between the two treatment groups in terms of SW (M diff = 0.13, p = .465), with both groups reporting significantly higher SW scores than the control group (iCBT M diff = 0.82, p < .001; antidepressant M diff = 0.95, p < .001).
Baseline results: Healthy participants
To assess task validity, we first examined task performance in healthy participants. In line with previous findings, we found that healthy participants increased their learning rate (α) in response to increased volatility (log ratio M(SD) = 0.37(0.95), t (94) = −3.75, p < .001; Figure 2, top left). This means participants relied on more recent evidence to inform their choices under volatile conditions. Importantly, this effect of volatility appeared to be confined to participants’ learning rates, as there were no differences found in participants’ choice stochasticity (β; t (94) = 0.51, p = .613) or risk behavior (λ; t (94) = −0.40, p = .690) across volatility conditions. In the supplementary HBE analysis (Supplementary Table S10), we did not find evidence that healthy participants adjusted their learning rate to adapt to the change of volatility (95% HDI: [−0.22, 0.16]).
Baseline learning rate estimates from the MLE analysis across the three participant groups of the PIP study. Top: All groups displayed higher learning rates in response to more volatile conditions on the aversive learning task. Box plots represent median, upper and lower quartiles. Bottom: There was no association between degree of learning rate adaptation and anxious-depression symptom scores in the control participants (left) or the two treatment groups (centre: iCBT, right: antidepressants). Statistics pertain to the full regression model, but for illustration purposes, the residuals for learning rate adaptation are plotted on the y-axis, controlling for age and gender.

Figure 2. Long description
The Y-axis is labeled Learning Rate Adaptation Delta alpha, with a scale from negative 2 to 2. The chart contains three main sections from left to right.
1. Controls: Shows two adjacent violin plots for Baseline and Follow-Up. Individual data points are connected by light gray lines. A bracket above the pair indicates p equals .763. The box plots within the violins show a median near 0.
2. i C B T: This central section has a higher density of data points. The violin plots are wider, and the connecting lines are more numerous. A bracket above indicates p equals .756. The median for both Baseline and Follow-Up remains centered near 0.
3. Antidepressants: The rightmost section shows Baseline and Follow-Up violin plots with a bracket indicating p equals .196. The box plot for Follow-Up appears slightly higher than the Baseline, though the distribution remains largely centered around the 0 to 1 range.
In all three groups, the distribution of data points and the shape of the violin plots are visually similar between the two time points, indicating no significant change.
Next, we examined the relationship between anxious-depression and the degree to which individuals adjusted their learning rate in response to volatility. We found a non-significant trend for greater AD symptoms to relate to less adjustment of learning rate (b = −0.23, 95% CI = −0.48 to 0.02, p = .070; Figure 2, bottom left). Bayes factor (BF10 = 0.94) was close to 1, indicating inconclusive evidence for or against the null. In a sensitivity analysis where we excluded participants for potential inattentive responding (n = 14, see Supplementary Methods), this was further attenuated (b = −0.17, 95% CI = −0.45 to 0.10, p = .211, BF10 = 0.46; Supplementary Table S4). Likewise, this effect also attenuated when age and sex were not included as covariates (mimicking the original analysis by Browning et al., Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015): b = −0.14, p = .148. In a supplementary HBE analysis, the effect of AD on learning rate adaptation was also not significant (95% HDI: [−0.11, 0.04]; Supplementary Table S10).
Baseline results: iCBT and antidepressant groups
Next, we compared the treatment arms to healthy participants. In the principal analysis, we observed the same pattern as in controls; both the iCBT and antidepressant groups adopted a higher learning rate in volatile, versus stable, blocks of the aversive learning task (iCBT difference M(SD) = 0.37(1.11), t (676) = −8.69, p < .001; Antidepressant difference M(SD) = 0.26(1.02), t (94) = −2.47, p = .015; Figure 2 top center and right). Directly comparing the groups, a 2x3 (volatility by group) ANOVA found evidence for a main effect of volatility (F(1,864) = 37.53, p < .001) and evidence for an effect of group (F(2,861) = 3.38, p = .034) on log learning rate, but no evidence for an interaction between volatility condition and group (F(2,864) = 0.44, p = .646). Post hoc pairwise comparisons found that the main effect of group was driven by the iCBT group having lower learning rates than healthy participants (t (861) = 2.4, p = .041). The antidepressant group did not differ from either the healthy or iCBT participants. In the HBE analysis, the iCBT group increased their learning rate in the volatile compared to stable block (95% HDI: [0.09, 0.25]), but the antidepressant group did not (95% HDI: [−0.21, 0.24]). Comparing groups using the HBE sensitivity analysis, the iCBT group had a slightly larger adaptation than controls (95% HDI: [0.01, 0.42]) but was not different from the antidepressant group (95% HDI: [−0.08, 0.40]). The iCBT group also had lower learning rates than both groups overall (Supplementary Table S10).
Against our prediction, we did not find evidence for an association between AD and learning rate adaptation (Δα) within either the iCBT or antidepressant groups (b = 0.04, 95% CI = −0.08 to 0.15, p = .533, BF10 = 0.10, and b = 0.03, 95% CI = −0.27 to 0.33, p = .841, BF10 = 0.22, respectively) (Figure 2, bottom center and right). Bayes factor indicates strong and moderate evidence for the null, respectively. Moreover, there was no evidence for an association when we pooled the data from all three groups (b = 0.00, 95% CI = −0.08 to 0.08, p = .952, BF10 = 0.08), with strong evidence for the null. There was also no effect when we removed a subset of participants in the iCBT arm who were receiving medication at baseline (b = 0.02, 95% CI = −0.12 to 0.15, p = .808). In the HBE sensitivity analysis, there was also no significant association between AD symptoms and learning in the iCBT group (95% HDI: [−0.02, 0.11]) or the antidepressant group (95% HDI: [−0.17, 0.12]) (Supplementary Table S10). If anything, the direction of effect was opposite to the published literature for the iCBT group.
Longitudinal results: Test–retest reliability
We used the data from the healthy participant group (who received no intervention) to estimate the test–retest reliability of the task over the time between baseline and follow-up measurements (four weeks). The intra-class correlation (ICC2,1) for the estimates of learning rate was low across both the stable (ICC2,1 = 0.42, p < .001) and volatile blocks (ICC2,1 = 0.49, p < .001). The ICC of learning rate adaptation (Δα, the difference between the log learning rates for stable and volatile blocks) was poor: ICC2,1 = 0.23, p = .014. These estimates remained largely unchanged when excluding participants (n = 14) for potential inattentive responding (stable ICC2,1 = 0.41, p = .001; volatile ICC2,1 = 0.54, p < .001, Δα ICC2,1 = 0.25, p = .012). The three mental health factor scores had high ICCs amongst the healthy participants (AD ICC2,1 = 0.76, p < .001; CIT ICC2,1 = 0.78, p < .001; SW ICC2,1 = 0.72, p < .001). One reason for the poor reliability of parameters could be problems with model fitting. Indeed, the main analysis (which has not been assessed for recoverability previously) was shown to have modest reliability, particularly for the learning rate adaptation parameter, which had recoverability as low as r = .54 (Supplementary Methods, Supplementary Figures S1, S2).
Longitudinal results: treatment effects
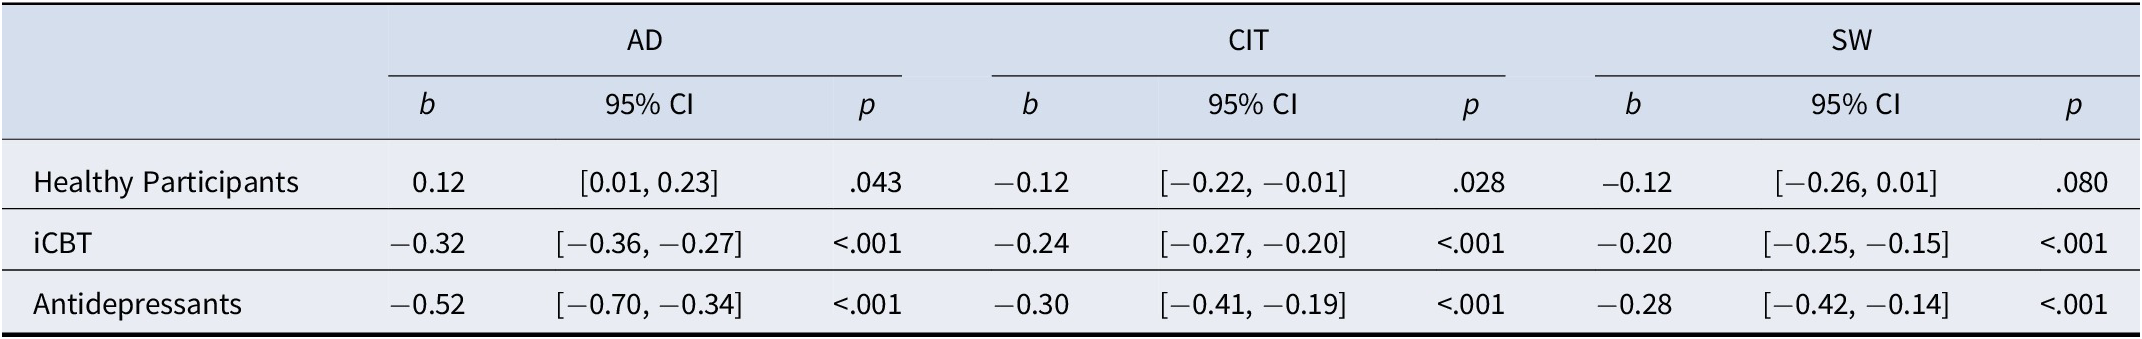
At four-week follow-up, both treatment groups showed substantial improvements across all mental health measures, with the largest effects being found amongst individuals who were taking antidepressants (Table 1). The healthy participants showed smaller improvements in CIT (b = −0.12, p = .028) and a marginal improvement in SW (b = −0.12, p = .08). Curiously, the control participants reported worse AD scores at follow-up (b = 0.12, p = .043), possibly reflecting regression to the mean due to the inclusion criteria. However, this effect attenuated when excluding participants for potential inattentive responding (Supplementary Table S5, p = .072).
Treatment effects (or, for healthy participants, time effects) on mental health factor scores, per group

Table 1. Long description
The table presents data for three mental health factors: A D (anxious-depression), C I T (compulsivity and intrusive thought), and S W (social withdrawal). For each factor, three metrics are reported: b (coefficient), 95% C I (confidence interval), and p (p-value).
* Healthy Participants:
- A D: b = 0.12, 95% C I [0.01, 0.23], p = .043.
- C I T: b = -0.12, 95% C I [-0.22, -0.01], p = .028.
- S W: b = -0.12, 95% C I [-0.26, 0.01], p = .080.
* i C B T Group:
- A D: b = -0.32, 95% C I [-0.36, -0.27], p < .001.
- C I T: b = -0.24, 95% C I [-0.27, -0.20], p < .001.
- S W: b = -0.20, 95% C I [-0.25, -0.15], p < .001.
* Antidepressants Group:
- A D: b = -0.52, 95% C I [-0.70, -0.34], p < .001.
- C I T: b = -0.30, 95% C I [-0.41, -0.19], p < .001.
- S W: b = -0.28, 95% C I [-0.42, -0.14], p < .001.
Note: AD: anxious-depression; CIT: compulsivity and intrusive thought; SW: social withdrawal.
All three groups continued to show learning rate adaptation at follow-up (healthy participant log ratio M(SD) = 0.40(0.87), t (94) = −4.48, p < .001; iCBT M(SD) = 0.39(0.99), t (676) = −10.13, p < .001; antidepressant M(SD) = 0.44(1.07), t(94) = −3.98, p < .001). A linear mixed effect model that included volatility, group, and time, as predictors of learning rate (α) confirmed that there was a main effect of volatility (b = 0.37, 95% CI = 0.16–0.58, p < .001), but no main effect of time (b = −0.12, 95% CI = −0.32 to 0.09, p = .266). A main effect of group remained, with iCBT participants having slightly lower learning rates than the healthy participant group (b = −0.18, 95% CI = −0.36 to −0.01, p = .048). We found no evidence for any interaction effects of time by group (antidepressant b = 0.04, 95% CI = −0.25 to 0.34, p = .772; iCBT b = 0.17, 95% CI = −0.05 to 0.39, p = .137), time by volatility (b = 0.04, 95% CI = −0.26 to 0.33, p = .813), nor time by group by volatility (antidepressant b = 0.14, 95% CI = −0.27 to 0.56, p = .500; iCBT b = −0.02, 95% CI = −0.33 to 0.29, p = .906). These effects remained consistent when excluding for potential inattentive responding (see Supplementary Table S6) and in the HBE analysis (Supplementary Table S10; Supplementary Figures S4 and S5).
While no significant interaction was observed, we present the simple effects of time on learning rate adaptation (Δα) within each group for the interested reader (healthy participants: b = 0.04, 95% CI = −0.19 to 0.26, p = .763, BF10 = 0.02; iCBT: b = 0.02, 95% CI = −0.09 to 0.12, p = .756, BF10 = 0.00; antidepressants: b = 0.18, 95% CI = −0.09 to 0.45, p = .196, BF10 = 0.06; see Figure 3). The lack of evidence for any effects of time suggests neither overall learning rate nor learning rate adaptation improves following treatment.
Learning rate adaptation (Δα) at baseline and follow-up from the MLE analysis, for each of the participant groups. There was no evidence for changes in learning rate adaptation over time, despite significant treatment gains (in terms of mental health factor scores) in both the iCBT and antidepressants groups. P-values correspond to the simple effects of time on learning rate adaptation, within each group. Box plots represent median, upper and lower quartiles.

Figure 3. Long description
A graph with a vertical Y axis labeled Learning Rate Adaptation Delta alpha ranging from minus 2 to 2. The X axis displays three distinct groups from left to right.
* Controls in pink. The baseline and follow-up violin plots are nearly identical, centered around 0. A bracket above connects them with a p value of point 7 6 3.
* i C B T in dark blue. This group has a higher density of data points. The baseline and follow-up distributions are stable, centered slightly above 0. A bracket above shows a p value of point 7 5 6.
* Antidepressants in light blue. The baseline and follow-up distributions show a slight upward shift in the median, but remain largely overlapping. A bracket above shows a p value of point 1 9 6.
In all three groups, individual data points are connected by light gray lines between baseline and follow-up, indicating individual trajectories. Each plot includes a central box plot showing the median, upper, and lower quartiles.
Individual differences in treatment effects
Finally, we tested if changes in learning rate adaptation were associated with changes in AD scores following treatment. Simple correlations did not find evidence for an association in either the healthy participants (r (93) = .15, 95% CI = −0.06 to 0.34, p = .160) or the iCBT group (r (675) = .02, 95% CI = −0.05 to 0.10, p = .549). There was, however, evidence for a negative correlation within the antidepressants group (r (93) = −.32, 95% CI = −0.49 to −0.13, p = .001), such that a decrease in symptoms was associated with an increase in learning rate adaptation (Δα) (Supplementary Figure S3). This association remained when excluding inattentive responding (Supplementary Table S7). In the HBE analysis, there was no evidence for an association in healthy participants (r (93) = .01, 95% CI = −0.19 to 0.21, p = .93), but a weak positive correlation within the iCBT group (r (675) = .08, 95% CI = 0.00–0.15, p = .05), such that symptom improvement was related to a worsening of learning rate adaptation. The effect was reversed in the antidepressant group and significant (r (93) = −.37, 95% CI = −0.53 to −0.18, p = .001, Supplementary Figure S7).
Discussion
When faced with a volatile environment, increasing our learning rate and keeping track of the best course of action is optimal. Some evidence suggests this ability is diminished amongst individuals with anxiety and depression. However, there have been a series of recent failures to replicate the effect (Hammond et al., Reference Hammond, Xu, Ai and Van Dam2023; Jassim et al., Reference Jassim, Waade, Parsons, Petzschner, Rua, Rodgers, Baron-Cohen, Suckling, Mathys and Lawson2025; Satti et al., Reference Satti, Wille, Nassar, Cichy, Schuck, Dayan and Bruckner2025), albeit in relatively small samples. In a large treatment-seeking sample with a range of anxious-depression symptoms, we found little evidence for an association between anxious-depression and learning rate adaptation at baseline or follow-up and no evidence that adaptation improves following treatment. However, in the group receiving antidepressants, those who had the biggest reductions in anxious-depression had the greatest increases in learning rate adaptation.
All three groups adopted a higher learning rate when in a volatile environment, which both replicates earlier work (Behrens et al., Reference Behrens, Woolrich, Walton and Rushworth2007) and confirms that our aversive learning task successfully manipulated volatility. But, we found no significant relationship between anxious-depression and learning rate adaptation in healthy controls. A non-significant trend was observed, which diminished when we excluded participants who displayed inattentive responding and was not significant when analyzed using a hierarchical Bayesian approach. Likewise, we found no effect in the iCBT or antidepressant medication groups and no difference in learning rate adaptation between these patients and healthy participants. This is particularly notable as the iCBT group is the largest group studied to date in this task (n = 677). Taken together, we did not find robust support for any association between anxious-depression symptoms and learning rate adaptation.
Given that there was no significant association between mental health and learning rate adaptation at baseline in the patient groups, it is perhaps unsurprising that we observed no significant changes in learning rate adaptation following intervention. This is not because the treatments were ineffective; the treatment arms saw improvements in symptoms over their first four weeks of treatment, with the largest improvements observed for individuals taking antidepressants. This suggests that learning rate adaptation (at least as measured by this task) is not a state marker of anxious-depression symptoms, and treatment does not modify learning rate or its adaptation at the group level. The only exception was the observation that reductions in AD in the antidepressant group following treatment were associated with increases in learning rate adaptation. This result is potentially interesting, and the effect was robust to sensitivity analysis. However, we believe it should nonetheless be treated cautiously. This result emerged only in the antidepressant group and was in the context of a failure to find (a) pre-post changes in learning rate adaptation in the antidepressant group, (b) a group difference between healthy participants and the antidepressant group at baseline, (c) any significant cross-sectional association between learning rate adaptation and AD within the antidepressant group at baseline, and (d) the poor test–retest reliability and parameter recovery of the learning rate adaptation metric. Future work is therefore required to establish if this effect is reproducible.
Indeed, the poor test–retest reliability of the learning rate adaptation measure in the healthy participant group may be a crucial explanation for the lack of effects observed. Reliability sets the ceiling for any association that can be observed between that measurement and another variable. To our knowledge, this is the first study to report the test–retest reliability of this measure, and future work should establish if alternative versions have similarly poor psychometric properties. However, recent studies examining test–retest reliability of learning rate parameters in other tasks converge with the present study. For example, Vrizzi et al. (Reference Vrizzi, Najar, Lemogne, Palminteri and Lebreton2025) report learning rate reliabilities ranging from r = .10–0.19, Schaaf, Weidinger, Molleman, and van den Bos (Reference Schaaf, Weidinger, Molleman and van den Bos2024) report r = .02–.27, and Shahar et al. (Reference Shahar, Hauser, Moutoussis, Moran, Keramati, Consortium and Dolan2019) found that values ranged from r = .15–.39. A more recent study found the split-half reliability to be low-to-moderate for learning rate in a very similar task but did not report on the reliability of the adaptation measure itself (Satti et al., Reference Satti, Wille, Nassar, Cichy, Schuck, Dayan and Bruckner2025). This said, the interpretation of reliability here is further complicated by the lack of strong parameter recovery of learning rate parameters and should be the focus of future work using this task and this suite of models.
A second explanation for these results could be the reliance on online experimentation methods that may be vulnerable to poor quality data. However, in the same sample we also examined metacognition before and after treatment (Fox et al., Reference Fox, Lee, Hanlon, Seow, Lynch, Harty, Richards, Palacios, O’Keane, Stephan and Gillan2023) and replicated previously established associations between metacognitive bias, AD and CIT (Rouault, Seow, Gillan, & Fleming, Reference Rouault, Seow, Gillan and Fleming2018) in addition to changes following treatment that depended on the magnitude of clinical improvement. Moreover, and in contrast to the reliability of our task measure, we found excellent reliability on mental health factor scores (e.g. anxious-depression). This suggests that the test–retest reliability of the loss-avoidance aversive learning task specifically is poor, despite good data quality overall in the study.
Limitations
The PIP study intended to study early treatment effects spanning the first 4 weeks of the treatment course. We chose a short duration for this study because prior work has shown that over 75% of eventual SSRI responders start to respond by week 4 (Nierenberg et al., Reference Nierenberg, Farabaugh, Alpert, Gordon, Worthington, Rosenbaum and Fava2000). We aimed to balance measuring an adequate response with the risk of study attrition or treatment switching. However, we recognize that antidepressants and iCBT are often delivered over several weeks (Andersson, Carlbring, Ljótsson, & Hedman, Reference Andersson, Carlbring, Ljótsson and Hedman2013), if not years (Cartwright et al., Reference Cartwright, Gibson, Read, Cowan and Dehar2016), and it can take several weeks before all clinical changes occur. For this reason, it is possible that future studies may discover that cognitive changes occur after longer periods than studied here. The lack of adequate control groups for both treatment groups further challenges our interpretation of the longitudinal findings. While we did include a healthy participant group as a comparator, this is insufficient to isolate the actual effects of iCBT and antidepressants on learning rates amongst patients, for which a randomized controlled design is necessary. The tentative results in the antidepressant group may warrant further study, as there is increasing evidence that pharmacological interventions modify depression-relevant reinforcement learning (Lan & Browning, Reference Lan and Browning2022). The present study used a loss of points task. Although that design was similar to Gagne et al. (Reference Gagne, Zika, Dayan and Bishop2020), it remains possible that variants of the task that use primary threat avoidance (as in Browning et al., Reference Browning, Behrens, Jocham, O’Reilly and Bishop2015) are more sensitive to individual differences in anxiety. However, Satti et al. (Reference Satti, Wille, Nassar, Cichy, Schuck, Dayan and Bruckner2025) tested this, and found that the use of primary reinforcers had no impact on their (null) findings.
Finally, while all three groups were technically well-powered to detect effects based on the prior literature, it is possible that there is a true effect, but it is smaller than previously thought. There is a growing appreciation in psychiatry that mental health is complex, effect sizes are small, and the samples required to estimate brain-behavior associations are larger than the literature suggests (Marek et al., Reference Marek, Tervo-Clemmens, Calabro, Montez, Kay, Hatoum, Donohue, Foran, Miller, Hendrickson, Malone, Kandala, Feczko, Miranda-Dominguez, Graham, Earl, Perrone, Cordova, Doyle and Dosenbach2022). Although the field awaits a comprehensive assessment, it may be the case that the same is true for cognition-behavior associations.
Conclusion
This study replicated previous cross-sectional findings that healthy individuals increase their learning rate in response to greater volatility in their environment. However, in contrast to previous findings, we found little evidence to suggest that this adaptation was related to levels of anxious-depression symptoms. We also found no clear evidence to suggest that learning rate adaptation changes on a group level following two common psychiatric interventions despite significant improvements in self-reported symptoms. This suggests that, at least for the specific task used in this study, learning rate adaptation may not be a robust trait or state-like marker of anxious-depression severity, nor is it a causal mechanism of symptom remission.
Supplementary material
The supplementary material for this article can be found at http://doi.org/10.1017/S0033291726105698.
Data availability statement
Data are available on submission of a data access request form to gillancl@tcd.ie, and all code used to model and analyse the data collected in this study is publicly accessible on the OSF project page: https://osf.io/2bevp/.
Acknowledgements
We gratefully acknowledge Timothy Behrens and Michael Browning for providing modelling scripts that formed the foundation of the modelling conducted in this manuscript. We also thank the participants who gave their time to help us with this research.
Funding statement
This project was funded by a grant from MQ: transforming mental health to CMG (MQ16IP13) with support from an industry co-fund for the PhD studentship of CTL from Research Ireland and SilverCloud Health (EPSPG/2020/8).
Competing interests
C.T.L., S.H., and D.R. are former employees of Amwell Health, which was the provider of iCBT (SilverCloud) in this study. SS is an employee of Mindset Technologies Ltd; however, this research was conducted prior to their employment.




 Open access

