Introduction
According to first admission rates, the annual incidence of schizophrenia-like psychosis for those over the age of 60 is forecast to increase by 11% with each five-year increase in age (Van Os et al., Reference Van Os, Howard, Takei and Murray1995). Despite such figures, there is a paucity of research in this area: only 1% (Cohen et al., Reference Cohen, Vahia, Reyes, Diwan, Bankole and Palekar2008) of all published articles in mental health examined aging and schizophrenia over the previous decade. In the year 2000, experts began to bridge this gap by achieving an international consensus regarding diagnosis, nomenclature, treatment guidelines, and future research objectives for the onset of psychosis in later life (Howard et al., Reference Howard, Rabins, Seeman and Jeste2000). Two diagnostic categories were proposed: late onset schizophrenia (LOS) and related psychoses (illness onset after 40 years of age) and a subset of LOS: very late onset schizophrenia-like psychosis (VLOSLP: onset after 60 years). These types of psychotic disorder can only be assigned if the corresponding symptoms cannot be attributed to an affective disorder or a focal or progressive structural brain abnormality.
The LOS literature has largely addressed the question of whether it is an etiologically distinct disorder or simply a schizophrenia-spectrum illness developing in later life. Although the debate remains open and is complicated by diagnosis and nomenclature disagreements, the majority of evidence appears to support the latter hypothesis (Vahia et al., Reference Vahia, Palmer, Depp, Fellows, Golshan and Kraemer2010). Known etiology and risk factors associated with later-life psychosis are paranoid-schizoid personality traits, female gender, social isolation, leaving one's country of birth, and feeling like an outsider (Almeida et al., Reference Almeida, Howard, Levy and David1995; Mitter et al., Reference Mitter, Reeves, Romero-Rubiales, Bell, Stewart and Howard2005). Apart from gender, all of these risk factors are similar to those observed when psychosis emerges before 40 years of age (termed here early onset schizophrenia: EOS).
The symptomatology of EOS and LOS has been compared most frequently using casenote data. Schneiderian first-rank symptoms are common regardless of age of onset (Pearlson et al., Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989; Cohen et al., Reference Cohen, Vahia, Reyes, Diwan, Bankole and Palekar2008; Vahia et al., Reference Vahia, Palmer, Depp, Fellows, Golshan and Kraemer2010), and similar levels of delusional perception, bizarre delusions, and delusions of reference have been found (Howard et al., Reference Howard, Castle, Wessely and Murray1993a; Reference Howard, Almeida and Levy1993b; Castle et al., Reference Castle, Wessely, Howard and Murray1997). However, there appear to be some phenomenological differences: LOS has a higher prevalence of visual, tactile, and olfactory hallucinations as well as persecutory delusions and third-person running commentary across several studies. As many as 93% of LOS individuals have been found to experience systematic persecutory delusions compared with 71% of EOS (Howard et al., Reference Howard, Castle, Wessely and Murray1993a); and this pattern is similar at first hospital admission and discharge (Sato et al., Reference Sato, Bottlender, Schröter and Möller2004). The increase of paranoid delusions appears to be somewhat related to both chronological age and age of onset (Pearlson et al., Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989; Häfner et al., Reference Häfner, Hambrecht, Loffler, Munk-Jorgensen and Riecher-Rossler1998). Pearlson et al. (Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989) found that an older EOS group (μ age = 66.4) was more likely to have delusions than a younger EOS group (μ age = 32.4), but that both had significantly fewer persecutory delusions than a LOS group (μ age = 69.5). A five-year joint population-based and clinical study showed disorganization (disordered sense of self, incoherence of thought) decreased and paranoid-systematic delusions increased with chronological age across the whole onset range, 15 to over 75 years (Häfner et al., Reference Häfner, Hambrecht, Loffler, Munk-Jorgensen and Riecher-Rossler1998). A particular feature of LOS would seem to be systematized “partition” delusions (usually paranoid in nature) whereby a person or other object or force enters their home through the wall: Pearlson et al. (Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989) found this phenomenon in roughly half their late onset group compared with 14% of early onset patients.
Psychotic disorders in adults with LOS are also commonly associated with a lack of awareness of the presence of a mental disorder (poor insight), and compliance with treatment is typically poor (Almeida et al., Reference Almeida, Levy, Howard and David1996). A late-onset cohort is less likely to display formal thought disorder (Pearlson et al., Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989; Howard et al., Reference Howard, Castle, Wessely and Murray1993a; Castle et al., Reference Castle, Wessely, Howard and Murray1997), affect flattening, or blunting than their younger counterparts (Howard et al., Reference Howard, Almeida and Levy1993b; Sato et al., Reference Sato, Bottlender, Schröter and Möller2004). However, Häfner et al. (Reference Häfner, Riecherrossler, Anderheiden, Maurer, Fatkenheuer and Loffler1993) found a higher frequency of negative symptoms and an extended course in women over 35 years of age.
Current evidence concerning how LOS differs from EOS has used formal psychiatric rating scales most usually from casenotes, and is often restricted to presence/absence of judgments. Greater detail of the phenomenology of psychotic symptoms is missing and this study seeks to address this lacuna using multi-factorial continuous measures of the two main domains of positive psychotic experiences: hallucinations and delusions. The Psychotic Symptom Rating Scales (PSYRATS: Haddock et al., Reference Haddock, McCarron, Tarrier and Faragher1999) is a well-established interview-based measure of a range of qualities of hallucinations and delusions and the distress engendered. It has been used to assess the effectiveness of psychological interventions for psychosis. The PSYRATS has been shown to demonstrate good inter-rater reliability, internal consistency, and convergent validity with the Positive and Negative Syndrome Scale (PANNS; Kay et al., Reference Kay, Opler and Lindenmayer1989) in those with chronic schizophrenia (Haddock et al., Reference Haddock, McCarron, Tarrier and Faragher1999) and first-episode psychosis (Drake et al., Reference Drake, Haddock, Tarrier, Bentall and Lewis2007).
We aimed to characterize the frequency, duration, and distress related to the psychotic symptoms of LOS, in addition to comparing a LOS sample to an EOS sample. Based on the prior literature we hypothesized greater severity of persecutory delusions and hallucinations, and poorer insight in LOS when compared to EOS. In addition to a standard EOS group, we aimed to compare the delusions and hallucinations in LOS to those of both an age matched EOS group (i.e. differing in age of onset but not chronological age) and a chronicity matched EOS group. We hoped to elucidate further whether LOS/EOS differences are due to age of onset of illness. Although not a main aim of this study, we have reported its convergent validity against the PANNS – one of the most commonly used schizophrenia symptom measures.
Methods
Participants
All participants were required to have a DSM-IV diagnosis of schizophrenia, schizophrenia-affective disorder, or delusional disorder. Onset of psychosis was defined as participant's age at first contact with services. Consistent with the recommendation of Howard et al. (Reference Howard, Rabins, Seeman and Jeste2000), we used a cut-off of 40 years old to differentiate LOS from EOS. The LOS group consisted of 34 participants and the EOS group of 235 participants. Participants for both groups were recruited from four mental health NHS Trusts, largely in London; some as part of the Psychological Treatment for the Prevention of Relapse in Psychosis (PRP) trial (ISRCTN: 83557988) and additional LOS participants specifically for this study. Participants were required to have active psychotic symptoms and not to have a diagnosis of substance-induced psychosis or a primary affective disorder. Participants with significant English language comprehension or expression difficulties were also excluded. Additionally, participants were excluded if they had a known organic brain or neurological disorder, including dementia. As an additional check, those over 65 years old were screened for degenerative memory disorders using the Mini-Mental State Examination (MMSE; Folstein et al., Reference Folstein, Folstein and McHugh1975). A MMSE cut-off of 24 or less was used in accordance with previous research (Howard et al., Reference Howard, Castle, Wessely and Murray1993a).
Measures
Positive and Negative Syndrome Scale (PANSS)
The PANSS is a 30-item scale, which assesses symptoms associated with schizophrenia over the past 72 hours. Each item of the PANSS ranges from 1 (absent) to 7 (extreme). Four scores: PANSS Total (30 items), Positive Scale (seven items), Negative Scale (seven items), and General Psychopathology (16 items) can be produced. The greater presence of a symptom is indicated by higher PANSS scores. Lack of judgment and insight regarding the presence of mental illness, depression, and anxiety were assessed using the corresponding items from the PANSS; all are seven-point scales, ranging from 1 (absent) to 7 (extreme).
Psychotic Symptom Rating Scales (PSYRATS)
The PSYRATS is a standardized semi-structured interview designed to assess the subjective characteristics of auditory hallucinations and delusions. Symptom dimensions over the past week were rated. The delusions subscale (DS) has six items: duration and frequency of preoccupation, intensity of distress, and the amount of distressing content, conviction, and disruption to life. Each item is scored on a five-point ordinal scale 0 (not endorsing item) to 4 (fully endorsing item). The auditory hallucinations subscale (AHS) has 11 items: frequency, duration, controllability, loudness, location, severity and intensity of distress, amount and degree of negative content, beliefs about the origin of voices, and disruption to life.
Anxiety and depression
The Beck Depression Inventory-II (BDI-II, Beck et al., Reference Beck, Steer and Brown1996) is a 21-item questionnaire (scored 0–3) that is widely used to measure depressive symptoms by self-report. The Beck Anxiety Inventory (BAI: Beck et al., Reference Beck, Epstein, Brown and Steer1988) is a 21-item scale (0–4) that assesses physiological anxiety symptoms over the past week.
Procedure
Informed consent (following NHS ethical approval) was obtained for all participants and onset of illness was confirmed after reviewing the medical notes. Participants were interviewed face to face using the PANSS and PSYRATS scales respectively. In addition, participants’ demographic details, including age, gender, age of onset of illness, ethnicity, past suicide attempts, and employment, marital, and living status were recorded.
Results
The data were analyzed using non-parametric statistics throughout as very few variables met assumptions of normality. Thus chi-square and Wilcoxon tests were used to compare groups with categorical and continuous variables respectively. Spearman's ρ was calculated when two continuous variables were correlated.
Demographics
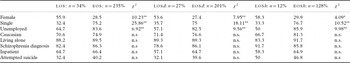
The groups were compared on demographic variables (see Table 1). Consistent with group allocation, the median age of onset was 44.5 years for the LOS group and 24 years for the EOS group (z = −9.43, p = 0.00). The LOS participants were older than the EOS participants at assessment (median 56.5 vs. 36.0 respectively; z = −7.82, p < 0.01). However, the length of illness in years (chronological age–age of onset) was significantly shorter for the LOS than the EOS group (median 5.5 vs. 9.0 respectively; z = −2.42, p = 0.02).
Descriptives (N = 269)

Note: LOS = late-onset schizophrenia; EOS = earlier-onset schizophrenia; LOSd = LOS with delusions; EOSd = EOS with delusions; LOSh = LOS with hallucinations; EOSh = EOS with hallucinations; *p < .05; **p < .01; n.s = not significant.
No differences were found between LOS and EOS groups in respect of ethnicity, diagnosis, or inpatient/outpatient status. As expected, around twice as many women were present in the LOS group (56%) as compared with the EOS group (29%). Individuals in the LOS group were also more likely to have been married at some point (32% single, 18% married, 44% separated/divorced, and 6% widowed), although the majority of both groups were living alone at the time of assessment. Unemployment was less likely in the LOS group (when retirement was classified as employment) than their EOS counterparts; however, the grounds for retirement (age vs. ill health) were not known. Though there were approximately the same proportions of inpatients and outpatients in both groups, this factor was studied further. None of the symptom-related dependent variables (PANNS or PSYRATS) were related to in/out patient status either as a main effect or in interaction with age of onset (LOS vs. EOS).
Reliability and convergent validity for PSYRATS in LOS
The PSYRATS for both DS and AHS was highly internally consistent according to Cronbach's α (0.94 and 0.97 respectively). The DS (and not AHS) was significantly correlated with the positive PANSS total, global PANSS total, and PANSS overall total (p < 0.05). No association was found with the PANSS negative total. Correlation coefficients ranged from 0.52 to 0.61. However, the only PANSS score that specifically measures hallucinatory behavior was significantly correlated with the AHS, as well as all its dimensions (p < 0.01). These Spearman's ρ correlation coefficients ranged from 0.67 to 0.82.
Group comparisons: LOS and EOS
Delusions were equally represented in the two groups (EOS = 85%, LOS = 82%). Contrary to predictions, more hallucinations were reported by the EOS than the LOS group (LOS = 57%, EOS = 35%; χ 2 = 5.65, df = 1, p = 0.02). A greater number of earlier-onset participants experienced both hallucinations and delusions than the late-onset participants (LOS = 27%, EOS = 49%; χ 2 = 5.81, df = 1, p = 0.02).
The LOS and EOS groups performed similarly on the PANSS positive, negative, global, and overall totals. Lack of insight was similar and substantial in both groups and correlated with overall PANSS (ρ = 0.26, p < 0.01) and positive symptom (ρ = 0.40, p < 0.01) severity. There were no differences in the PANSS depression and anxiety scores, or BDI/BAI scores between the LOS and EOS groups. To explore the characteristics of the PSYRATS further, the delusion and hallucination subscales were looked at separately using only those that endorsed the relevant positive symptoms.
Delusional subsamples (LOS: n = 27; EOS: n = 201)
The subsample of those with delusions was similar to the full sample in terms of demographic characteristics (Table 1). Consistent with hypotheses, the LOS delusional sample displayed greater levels of PANNS suspiciousness/persecution (z = −2.28, p = 0.02) and reduced judgment and insight (z = −2.39, p = 0.02) than the delusional EOS group. The commonest LOS delusional rating was “moderate–severe” (marked distrustfulness or clear-cut persecutory delusions), while for the EOS group this was “moderate” (distrustfulness without fully formed delusions). A similar pattern was observed for insight, whereby the EOS group tended to have “vague or shallow recognition of illness” and the LOS group “acknowledged past but not present psychiatric disorder.” Also reflecting the severity of delusional beliefs, unusual thought content was significantly greater in the LOS group than the EOS group (z = −2.39, p = 0.02).
Turning to the PSYRATS, higher levels of belief-conviction were found in the LOS group compared with the EOS group (z = −2.63, p = 0.01). None of the other PSYRATS dimensions differed significantly between groups. For both groups, the amount and duration of preoccupation were positively correlated (p > 0.05) with the amount and intensity of distress along with the disruption caused to life. The correlation coefficients were more substantial in LOS (ranging from 0.39 to 0.54 compared to 0.16 to 0.28 for the EOS group).
Delusions in chronological age matched groups
Each LOS case (n = 27) was matched to the nearest EOS case in age and gender resulting in an EOS group (n = 27) with a median age of 52.5 (LOS = 57, no significant difference). As expected, this results in a longer duration of illness in the EOS group (z = −5.13, p = 0.00; EOS = 24 years, LOS = 6 years).
Belief-conviction on the DS was no longer significant between onset groups – neither was suspiciousness/persecution or lack of judgment and insight on the PANSS. The PANSS positive totals (z = −2.73, p = 0.01) were lower in LOS than EOS (medians of 18.5 vs. 22). The unusual thought content item also differed (z = −2.64, p = 0.02); the medians indicated that ideas held by LOS individuals were most “frequently distorted and occasionally quite bizarre” compared with most frequently “strange and fantastic thoughts” in EOS.
Delusions in chronicity matched groups
The 27 LOS delusional cases were then matched with 27 EOS cases of the same gender with the most similar length of illness in years. Both groups obtained medians of six years length of illness.
Belief-conviction on the DS remained significantly higher in LOS group compared with EOS (z = −3.19, p = 0.00), so did PANSS suspiciousness/persecution (z = −2.09, p = 0.04) and lack of insight (z = −3.21, p = 0.00). There was a trend for intensity of delusional distress to be higher in the LOS group (z = −1.84, p = 0.07). Overall, the LOS group had more symptoms on the PANSS global total (z = −2.08, p = 0.04; LOS median = 36, EOS median = 32).
Hallucination Subsamples (LOS = 12, EOS = 134)
The demographic characteristics of the hallucination subgroups were similar to the full sample (Table 1.) The percentages found for frequency (χ 2 = 20.99, df = 4, p = 0.00), loudness (χ 2 = 9.31, df = 3, p = 0.03), and beliefs about origin of voices (χ 2 = 13.43, df = 4, p = 0.01) were significantly different between LOS and EOS groups. The direction of the differences was unclear for frequency and beliefs about the origin of voices. Notably, 50% of the LOS group reported hearing “whispers” compared with 24% of the EOS group. A strong trend towards quieter voices was also found when the dimensions were collapsed into “whispers” versus “greater than or equal to voice-level” and treated as ordinal (χ 2 = 3.9, df = 1, p = 0.05).
The frequency, loudness, and beliefs about origin of voices were independent of the other AHS items in the LOS group. In comparison, for the EOS group voices that were present more frequently throughout the week were more unpleasant (Spearman's ρ = 0.18, p = 0.04) and caused more disturbance to life (Spearman's ρ = 0.2, p = 0.02). The louder the voices sounded for EOS participants, the greater the perceived amounts of distress (Spearman's ρ = 0.18, p = 0.04).
For the admittedly small LOS group, the amount of unpleasant content was highly predictive of distress (ρ = 0.7, p < 0.01); and also predicted lower perceived control (ρ = −0.61, p < 0.05). As only 12 LOP individuals were identified with hallucinations, further subgroup analysis matching for age or chronicity was not undertaken.
Discussion
The LOS group were on average nearly 20 years older with onset well over 20 years later than the EOS group, thus typically they had experienced fewer years of illness. The 56% female majority observed here is consistent with earlier studies. Two-thirds of this LOS cohort had been married, nearly half divorced/separated, and 6% widowed, reflecting general trends in the research: other authors have also found that LOS individuals at some point maintained employment or homemaker roles (Jeste et al., Reference Jeste, Harris, Krull, Kuck, McAdams and Heaton1995; Castle et al., Reference Castle, Wessely, Howard and Murray1997).
Delusions and hallucinations
In terms of subjective experience of delusional symptoms, LOS was characterized by greater belief-conviction and greater levels of suspicion/feelings of persecution than EOS, but by similarly marked levels of distress and disruption to life. Distrustfulness of others was found to be high regardless of onset but feelings of persecution were more apparent in the LOS group. Higher levels of persecution were not observed when compared to age and gender matched EOPs, contrary to the findings of Pearlson et al. (Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989). When compared with EOS delusions of similar chronicity, LOS delusions were more severe, persecutory, and tended to be more distressing suggesting that the age of onset is relevant. It remains unclear why paranoia and persecutory delusions increase with age of onset. Hassett hypothesizes that “despair,” fragmentation of self-image, and paranoid fears are due to failure to fully negotiate Erikson's maturational task of “ego-integrity” (Hassett, Reference Hassett1997), which involves resolving feelings from the past, adapting to aging, and accepting the inevitability of death.
Data concerning bizarreness or unusualness of delusional content was somewhat inconsistent. In the sample as a whole, there were more unusual thought contents to LOP delusions; but when matched for chronological age, EOS delusions were the more bizarre. It remains unclear as to the reasons for this, but perhaps chronological age rather than age of onset is important in influencing unusualness of delusional content. One tentative hypothesis that would be consistent with the results is that unusualness of content is magnified by factors associated with aging that further limit ability of people with schizophrenia to effectively attend to and process feedback about the unusualness of a belief. These factors may include increased sensory impairment and mild cognitive deficits (Prager and Jeste, Reference Prager and Jeste1993). Social isolation may also be greater in older people (McPherson et al., Reference McPherson, Smith-Lovin and Brashears2006), further limiting access to opportunities for feedback. The EOS sample's more bizarre delusions in the age-matched groups may be because they have more chronic problems than the LOS group, possibly further increasing cognitive deficits and social isolation and further limiting feedback.
Contrary to the hypotheses and in comparisons to previous case-file reviews (Pearlson et al., Reference Pearlson, Kreger, Rabins, Chase, Cohen and Wirth1989; Howard et al., Reference Howard, Castle, Wessely and Murray1993a; Castle et al., Reference Castle, Wessely, Howard and Murray1997), hallucinations were under-represented in this LOS group (35%). However, Mayer et al. (Reference Mayer, Kelterborn and Naber1993) also found that paranoia-related hallucinations did not differ by age of onset of illness. Preliminary findings from this study do suggest that voices were experienced differently in the LOS group; 50% heard whispering voices compared with 24% of the EOS group. The, albeit limited, data suggested that whispers were found as distressing as louder hallucinations in LOS, unlike in EOS where whispers were associated with lower distress and anxiety. The results also suggested that LOS and EOS groups differed regarding the frequency and origin of voices, with greater externality in LOS. LOS, and hallucinations in particular, has been previously linked with increased beliefs about feeling influenced by an outside force, and to hearing difficulties (Howard et al., Reference Howard, Rabins, Seeman and Jeste2000).
Insight and conviction
Consistent with previous studies, insight (recognition of illness and treatment compliance) in LOS was poor and was not related to illness course or duration (Almeida et al., Reference Almeida, Levy, Howard and David1996). Matching subsamples’ analyses demonstrated that increased age (regardless of onset) might account for decreased insight. Similar again to past findings, insight was not related to negative symptoms and declined as severity of positive symptoms increased (Almeida et al., Reference Almeida, Levy, Howard and David1996).
Belief-conviction about the perceived reality of delusional beliefs has not previously been explored within LOS but was predictably perhaps high given the high levels of persecution reported. As belief-conviction in LOS was not associated with increased grandiosity, disorientation, or unusualness of thought content, as it was in EOS, delusional conviction may be determined somewhat differently later in life.
Higher belief-conviction and lower insight were both associated with lower anxiety in the EOS but not LOS participants. Poorer insight was associated with less depression in EOS but with more depression in LOS. Ideas that poor insight may be protective of self-esteem in EOS may not hold in LOS, perhaps because insight has different determinants in the latter.
Perceived distress
The PSYRATS demonstrated that the perceived distress associated with beliefs was as marked in LOS as EOS. Levels of depression did not vary significantly according to age of onset consistent with previous studies (Sato et al., Reference Sato, Bottlender, Schröter and Möller2004; Huang and Zhang, Reference Huang and Zhang2009; Vahia et al., Reference Vahia, Palmer, Depp, Fellows, Golshan and Kraemer2010). Anxiety was also similar despite age of onset of illness, which Moore et al. also document in VLOSLP (Moore et al., Reference Moore, Blackwood, Corcoran, Rowse, Kinderman and Bentall2006).
Limitations
From cross-sectional data of this kind, it is strictly impossible to separate the effects of chronicity and chronological age from age of onset. Thus, it is not possible to determine whether differences between LOS and EOS arise from age cohort and/or illness historical factors. Defining onset of illness as the first time an individual makes contact with psychiatric services (although common practice) also means the duration of untreated illness also cannot be accounted for, and this may well be longer in LOS. The effects of treatment history are also unknown. An omission to the phenomenology of LOS in particular was the lack of specific information about “partition” delusions that may form a subtype of paranoid delusions. A further limitation is the small number of LOS patients identified with hallucinations: it is not possible to determine if this is a reliable finding, and limits the conclusions that can be drawn about hallucinations here. Similarly, limited by small sample size is the studies’ ability to shed light on differences between inpatients and outpatients in the two groups.
Conclusions
The delusions of late onset psychosis were characterized by greater belief-conviction and paranoid/persecutory themes. When matched for chronicity, late onset delusions are more severe suggesting age of onset is relevant to the formation and maintenance of delusions and can lead to greater levels of distress than is common in early onset psychosis. Although hallucinations were not common in our sample, they were as distressing in late onset psychosis as in early. In contrast with early onset data, even quiet or whispered “voices” were as distressing to late onset participants. Clinicians should pay particular attention to even seemingly non-intrusive hallucinations in older people. Insight as a whole is frequently poor in late onset participants and this is particularly the case for those with more severe positive symptoms. This presents a common challenge in clinical settings aiming to engage individuals with late onset psychosis. Detailed assessment of the subjective experiences of people with LOS, such as with the instruments used here, can help guide clinical interventions and monitor symptomatic change.
Conflict of interest
None.
Description of authors’ roles
O. Mason and J. Stott designed the study; R. Sweeting and O. Mason collected the data; and all authors were involved in analyzing the data and writing up the paper.
Acknowledgments
We are very grateful indeed to the research team involved in the Psychological Treatment for the Prevention of Relapse in Psychosis (PRP) trial (ISRCTN: 83557988).