Introduction
Glottic mobility and competence play important roles during deglutition and phonation. Unilateral vocal fold paralysis is an important cause of glottic immobility. Unilateral vocal fold paralysis related voice, voice-related quality of life and respiratory problems are well described in the literature.Reference Behrman1–Reference Spector, Netterville, Billante, Clary, Reinisch and Smith3 However, few studies have focused on swallowing and aspiration problems.Reference Nayak, Bhattacharyya, Kotz and Shapiro4, Reference Cates, Venkatesan, Strong, Kuhn and Belafsky5 Aspiration reportedly occurs in about half of patients with unilateral vocal fold paralysis.Reference Leder, Suiter, Duffey and Judson6, Reference Jang, Lee, Jeon and Lee7 Vagal nerve paralysis is an aetiological factor in approximately 6 per cent of patients with dysphagia.Reference Leder and Ross8 However, glottic insufficiency is the main cause of swallowing problems in patients with unilateral vocal fold paralysis.Reference Jang, Lee, Jeon and Lee7, Reference Tabaee, Murry, Zschommler and Desloge9, Reference Domer, Leonard and Belafsky10
The cricopharyngeal muscle is the principal structure of the high-pressure area of the upper oesophageal sphincter. This muscle is active during rest and inactive during swallowing, allowing food passage to the oesophagus. Although the innervation of the cricopharyngeal muscle and upper oesophageal sphincter is controversial, the recurrent laryngeal nerve, pharyngeal branches of the vagus and the pharyngeal plexus are considered to participate.Reference Sasaki, Kim, Stevenson and Czibulka11, Reference Mu and Sanders12 The upper oesophageal sphincter is the most important area in oropharyngeal dysphagia and is usually evaluated by anatomical tests; its physiology is interpreted indirectly. In addition, it is difficult to assess this area either endoscopically or radiologically.
Manometry provides the most beneficial results in patients with oropharyngeal dysphagia.Reference Hila, Castell and Castell13 Manometric evaluation of the upper oesophageal sphincter yields objective data that may explain the underlying physiology. Although high-resolution manometers have become available in recent years, conventional solid-state manometers are still thought to be reliable.Reference Herbella and Patti14 We hypothesised that the upper oesophageal sphincter would be affected manometrically in patients with unilateral vocal fold paralysis because of vagal nerve paralysis, and that this effect would contribute to the swallowing pathology. In this study, we evaluated the upper oesophageal sphincter pressure and dysphagia of patients with unilateral vocal fold paralysis in comparison with that of healthy controls.
Materials and methods
Our study protocol was approved by the ethics committee (number 2016/129). Patients diagnosed with unilateral vocal fold paralysis due to vagal nerve pathology from January 2016 to October 2017 were informed of the study, and those who were willing were included in the study.
Patients aged less than 18 years and those with a disease onset less than 6 months prior were excluded from the study. Patients were also excluded if they had: a history of vocal medialisation, laryngeal cancer or previous laryngeal resection, neurological deficits other than vagal paralysis that may contribute to swallowing pathology, an inability to complete manometric evaluation, and/or a history of exposure to radiation or any other additional pathology.
The control group consisted of age- and sex-matched healthy volunteers with normal swallowing and healthy vocal folds.
Diagnoses of vocal fold paralysis were made based on flexible fibre-optic endoscopic examination findings. At our voice and swallowing pathologies clinic, all patients with unilateral vocal fold paralysis undergo a functional endoscopic swallowing evaluation and a modified barium oesophagus study to identify swallowing impairments. Thus, the enrolled patients underwent conventional solid-state manometry after functional endoscopic swallowing evaluation. Control patients underwent functional endoscopic swallowing evaluation followed by manometric evaluation.
Manometric assessment
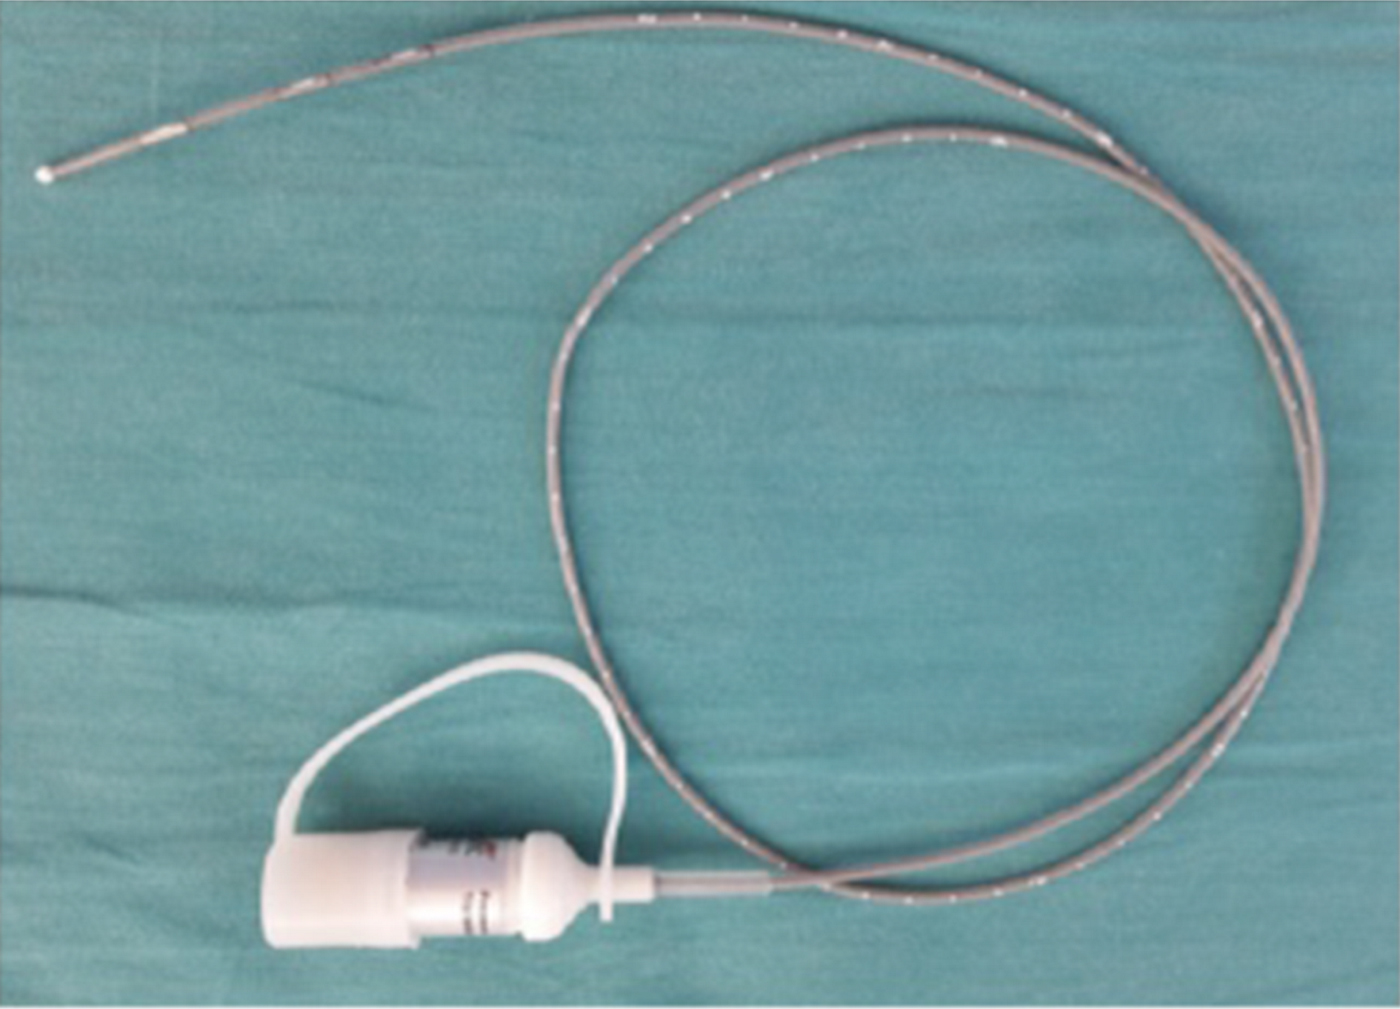
Before the procedure, patients confirmed that they did not use any medication that could affect the evaluation. The flexible manometry probe integrated in the swallowing unit (KayPentax, Lincoln Park, New Jersey, USA) was used. The solid-state manometry probe (model CTS3; Galtek, Hackensack, New Jersey, USA) was 100 cm in length, 2.1 mm in diameter and met the required catheter standards (Figure 1).
The manometry catheter used in our clinic.

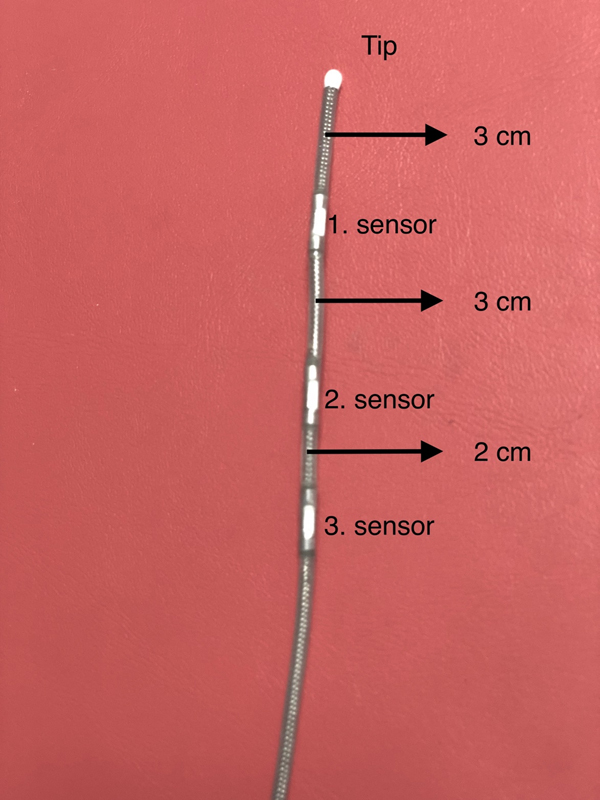
Pressure measurements were made using three sensors, of which the first was placed in the upper oesophageal sphincter 3–5 cm proximal to the sphincter. The manometer catheter is shown in Figure 2. The display was set at a frequency of 500 Hz and a pressure of −100 to + 250 mmHg. Before the procedure, the catheter was calibrated using a manometry calibration kit (Medical Measurements, Hackensack, New Jersey, USA).
The tip of the solid-state manometry catheter showing the sensor locations.

The patient's head was held in the neutral position. The endoscope was inserted through the nasal cavity, and an assistant inserted the manometry catheter through the other nostril to allow the probe to reach the hypopharynx and the high-pressure zone. By moving the probe forward and backward, the first sensor was positioned in the high-pressure zone of the upper oesophageal sphincter for 10 seconds to assess upper oesophageal sphincter basal pressure. Patients performed dry swallows, and wave recordings were taken by computer to measure the upper oesophageal sphincter residual pressure and relaxation time. The other sensors received signals from the pharynx. Sensors 2 and 3 recorded simultaneously during swallowing to evaluate pharyngeal peak pressure.
During the procedure, an assistant stabilised the catheter. All procedures were repeated at least three times and performed by the same two experienced physicians to optimise measurements.
Evaluation scales
Patients in the study and control groups completed the Turkish version of the Eating Assessment Tool 10 (‘T-EAT-10’) swallowing questionnaire,Reference Demir, Arslan and Karaduman15 the MD Anderson dysphagia questionnaire and the reflux symptom index.Reference Belafsky, Postma and Koufman16 Two experienced physicians evaluated penetration aspiration scale scores based on functional endoscopic swallowing evaluation records.
Results
The study and control groups included 30 and 24 patients, respectively. The study group consisted of 15 men (50 per cent) and 15 women (50 per cent), with a mean age of 53.43 ± 11.113 years. The control group consisted of 13 men (54.2 per cent) and 11 women (45.8 per cent), with a mean age of 48.54 ± 13.062 years. No significant difference in sex or age was observed between the groups (p > 0.05).
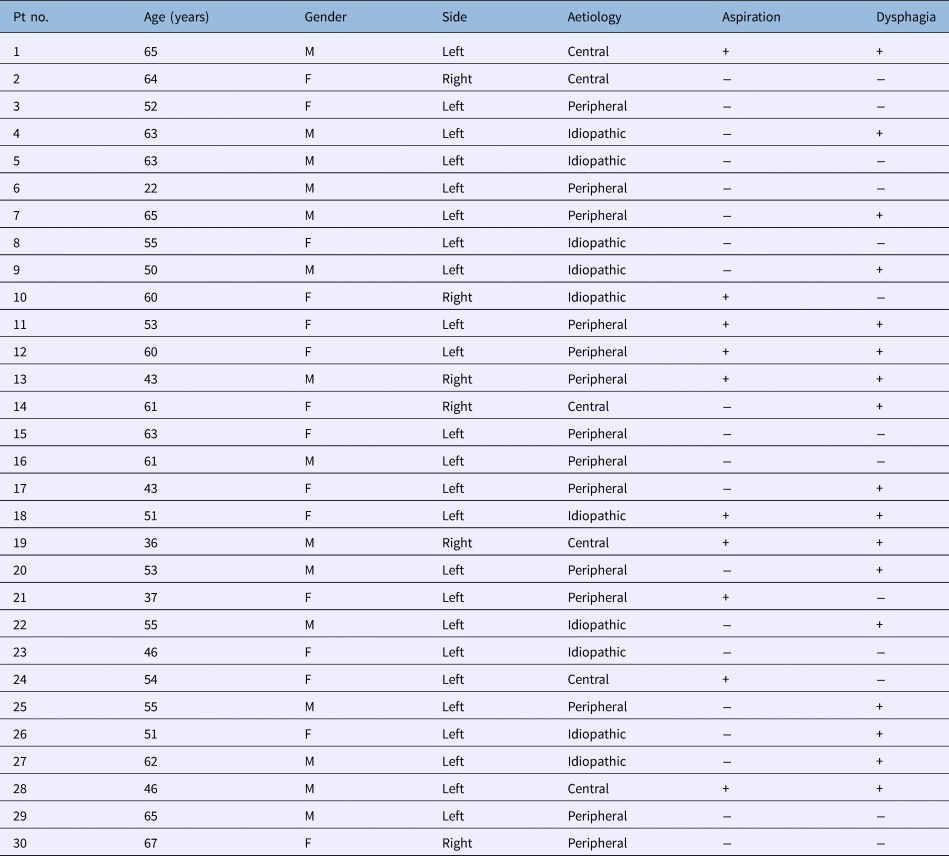
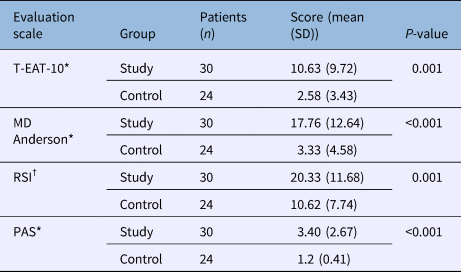
Vocal fold paralysis was most frequent on the left side (n = 24, 80 per cent). Aspiration was observed in 10 of the 30 study group patients (33.3 per cent). Dysphagia was observed in 17 of the 30 patients (56 per cent) (Table 1). The scores of the Turkish version of the Eating Assessment Tool 10, MD Anderson dysphagia questionnaire, reflux symptom index and penetration aspiration scale were significantly higher in the study group compared with the control group (Table 2).
Patients’ demographics, with aspiration and dysphagia status

Pt no. = patient number; M = male; F = female; ‘+’ = positive; ‘−’ = negative
Evaluation scale data

*Mann–Whitney U test; †independent two-sample t-test. SD = standard deviation; T-EAT-10 = Turkish version of the Eating Assessment Tool 10; RSI = reflux symptom index; PAS = penetration aspiration scale
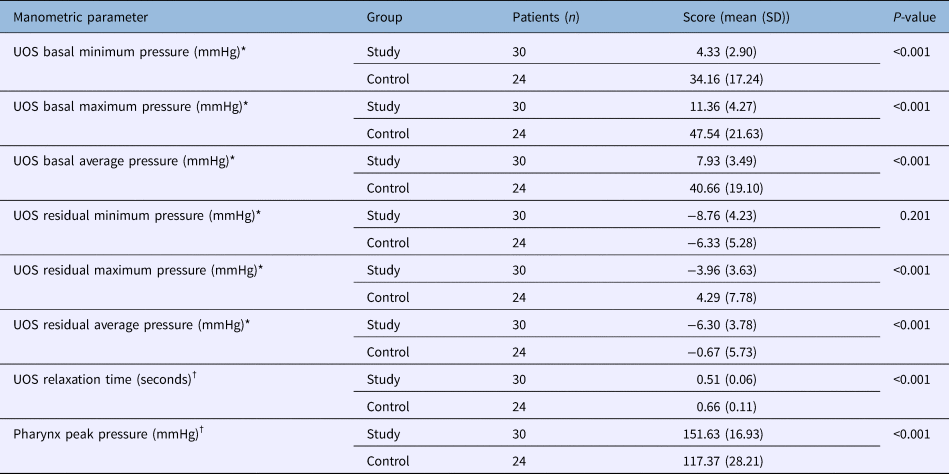
The mean values, standard deviations and statistical comparisons of the manometric data of the two groups are shown in Table 3. The minimum, maximum and average upper oesophageal sphincter basal pressures were lower in the study group than in the control group (p < 0.001). The sphincter relaxation time was significantly shorter in the study group than in the control group (p < 0.001). The minimum upper oesophageal sphincter residual pressure did not differ significantly (p = 0.201), but the maximum and average upper oesophageal sphincter residual pressures were significantly lower in the study group than in the control group (p < 0.001). The mean peak pressure of the two sensors in the pharynx during swallowing was significantly higher in the study group (p < 0.001).
Manometric data

*Mann–Whitney U test; †independent two-sample t-test. SD = standard deviation; UOS = upper oesophageal sphincter
Discussion
Patients with unilateral vocal fold paralysis have considerable swallowing and reflux problems. Manometric evaluation of the upper oesophageal sphincter region revealed decreased basal and residual pressures and upper oesophageal sphincter relaxation duration in patients with vocal fold paralysis. Peak pharynx pressure during swallowing was higher on pharyngeal recordings. The data in this study enabled identification of the hypotonic upper oesophageal sphincter area in patients with unilateral vocal fold paralysis.
Aspiration and penetration scores improve during treatments seeking to improve voice parameters in patients with unilateral vocal fold paralysis.Reference Cates, Venkatesan, Strong, Kuhn and Belafsky5, Reference Bhattacharyya, Kotz and Shapiro17 However, in some patients, dysphagia and aspiration continue even after glottic closure.Reference Nayak, Bhattacharyya, Kotz and Shapiro4, Reference Bhattacharyya, Kotz and Shapiro17 Therefore, glottic gape may not be the sole cause of dysphagia and aspiration problems in this population.Reference Domer, Leonard and Belafsky10, Reference Bhattacharyya, Kotz and Shapiro17 Few studies have addressed this issue, and other contributing factors are not fully understood. Physiological changes in the upper oesophageal sphincter region may play a role in deglutition problems, as the vagus nerve participates in the innervation of this area.
Deglutition problems and manometric changes in the upper oesophageal sphincter in vocal immobility remain debated, and only a few relevant studies have appeared. Henderson et al. evaluated eight patients with vocal fold paralysis using a water-perfusion manometer, but the results were unsatisfactory.Reference Henderson, Boszko, VanNostrand and Pearson18 Wilson et al. evaluated the upper oesophageal sphincter in patients with unilateral vocal fold paralysis and healthy controls using a solid-state conventional manometer.Reference Wilson, Pryde, White, Maher and Maran19 They found that the basal pressure was lower in those with central vagal pathologies, while the residual pressure was lower in peripheral and idiopathic cases.
Recently, Pinna et al. evaluated the swallowing pathologies of 16 patients with peripheral vagal paralysis, and compared their results with the data obtained in previous studies using a high-resolution manometer.Reference Pinna, Herbella, de Biase, Vaiano and Patti20 The residual pressure in the upper oesophageal sphincter was low in one-third of these patients and normal in the remaining two-thirds. Patients with aspiration had lower basal, residual and epiglottal upper oesophageal sphincter pressures. Patients with dysphagia had a lower epiglottal pressure and higher basal upper oesophageal sphincter pressure. The authors concluded that dysphagia was associated with decreased pharyngeal pressure, while aspiration was associated with decreased upper oesophageal sphincter pressures.Reference Pinna, Herbella, de Biase, Vaiano and Patti20
In this study, the minimum, maximum and mean upper oesophageal sphincter basal pressures were significantly lower in patients with unilateral vocal fold paralysis than in controls (p < 0.001), likely due to inadequate muscle contraction caused by paralysis and vocal fold immobility. Such hypotonicity of the sphincter during rest can lead to secondary problems such as laryngopharyngeal reflux. In support of this notion, reflux symptom index scores indicative of reflux were significantly higher in the study group.
Whereas the minimum upper oesophageal sphincter residual pressure of the study subjects was similar to that of the controls (p = 0.201), the maximum and mean values were significantly lower (p < 0.001). These results suggest that the upper oesophageal sphincter muscles also have difficulty during relaxation. Relaxation of the upper oesophageal sphincter depends on inhibition of the cricopharyngeal muscle and other upper oesophageal sphincter muscles; this relaxation opens the oesophagus to allow the passage of food. Our findings suggest that the upper oesophageal sphincter cannot attain sufficient relaxation, and this may hamper the passage of food. The measurement of relaxation pressure is difficult, and values can show marked variation among swallows. For this reason, the average of measurements obtained during multiple swallows was used in the present study. In addition, the pressure values obtained differ according to the type and quantity of food. In our study, both groups performed three dry swallows.
Domer et al. evaluated the upper oesophageal sphincter diameter in a barium swallow study and found that the diameter was smaller, but not significantly so, in patients with unilateral vocal fold paralysis.Reference Domer, Leonard and Belafsky10 The cited authors also reported pharyngeal weakness in patients with unilateral vocal fold paralysis, and concluded that this may contribute to swallowing impairment. Some studies have shown pharyngeal weakness to be involved in swallowing impairment in patients with unilateral vocal fold paralysis.Reference Jang, Lee, Jeon and Lee7
Wilson et al. reported that pharyngeal pressures were higher in patients with unilateral vocal fold paralysis, albeit not significantly so.Reference Wilson, Pryde, White, Maher and Maran19 Moreover, pharyngeal pressures were higher in patients with peripheral lesions and lower in those with central lesions. High-resolution manometric studies have yielded markedly different results.Reference Nativ-Zeltzer, Logemann, Zecker and Kahrilas21 Pinna et al. evaluated patients with vagal paralysis using a high-resolution manometer; the epiglottal pressure was higher in half of the patients.Reference Pinna, Herbella, de Biase, Vaiano and Patti20 The epiglottal pressure was lower in patients with aspiration than in those without aspiration. Moreover, patients with dysphagia had lower epiglottal pressure than did patients without dysphagia.
In our study, the mean peak pressure values obtained in the pharynx were significantly higher in patients with unilateral vocal fold paralysis compared with healthy controls. This is likely a result of compensation of the pharyngeal muscles. Such compensation may explain the high pharyngeal pressures detected in the present study. The healthy contralateral pharyngeal muscles and other muscles not innervated by the vagus may compensate for the weakness over time. We excluded acute stage patients from this study; we included only patients in whom paralysis had developed more than six months prior. However, the pharyngeal pressures reported in previous studies indicate that the mean values of the study and control groups in this study were normally distributed.Reference Leonard, Rees, Belafsky and Allen22
Bhatia and Shah reported that the relaxation duration during swallowing was 0.6–1.0 seconds.Reference Bhatia and Shah23 In our study, the relaxation durations were 0.51 seconds in the study group and 0.66 seconds in the control group (p < 0.001). All patients were assessed during dry swallowing, as the amount of bolus can affect the relaxation duration. Wilson et al. reported that the durations of contractions in the pharynx and upper oesophagus were shorter in patients with unilateral vocal fold paralysis than in controls.Reference Wilson, Pryde, White, Maher and Maran19
Aspiration has been detected in 33–42 per cent of patients with unilateral vocal fold paralysis.Reference Leder, Suiter, Duffey and Judson6, Reference Jang, Lee, Jeon and Lee7 Aspiration must be investigated and treated in such patients, as it may cause aspiration pneumonitis. Aspiration was observed in 33.3 per cent of our patients. The penetration aspiration scale scores of the patients with unilateral vocal fold paralysis were significantly higher than those of the controls. The swallowing and dysphagia assessment scales, the Turkish version of the Eating Assessment Tool 10, and the MD Anderson questionnaire scores were significantly higher in the study group.
• The upper oesophageal sphincter is the most important area for oropharyngeal dysphagia
• The cricopharyngeal muscle is the upper oesophageal sphincter's main structure and is innervated by the recurrent laryngeal nerve
• The upper oesophageal sphincter was evaluated in unilateral vocal fold paralysis patients to understand its effect on swallowing pathology in these patients
• Manometric evaluation revealed decreased basal and residual pressures and upper oesophageal sphincter relaxation duration
• Peak pharynx pressure during swallowing was higher on pharyngeal recordings
• The study data enabled identification of a hypotonic upper oesophageal sphincter area in unilateral vocal fold paralysis patients
This study has some limitations, the most important of which is the small number of patients enrolled. However, the formation of a homogeneous study group is difficult because of the rarity of unilateral vagal paralysis. Manometric evaluation is not yet part of clinical examinations of these patients; thus, only volunteers were included in this study. In addition, the procedure is not tolerated by all patients. Electromyography was not utilised to determine the site and level of the vagal lesion causing vocal fold paralysis. However, this study aimed to evaluate dysphagia and the upper oesophageal sphincter in patients with vocal fold immobility. Additional studies with larger numbers of patients are required to enhance our understanding of swallowing problems in patients with unilateral vocal fold paralysis.
In conclusion, more than half of the unilateral vocal fold paralysis patients had dysphagia and one-third had aspiration. Upper oesophageal sphincter pressure values were lower in patients with unilateral vocal fold paralysis. Hypotonic sphincter may contribute to swallowing impairment in patients with unilateral vocal fold paralysis.
Competing interests
None declared