Introduction
First branchial cleft anomalies are rare. They are estimated to account for only 1–5 per cent of all branchial anomalies.Reference May and D'Angelo1–Reference Martinez Del Pero, Majumdar, Bateman and Bull4 Due to their infrequent presentation, diagnosis can be delayed and initial management may be inappropriate.Reference Prabhu and Ingrams5
Case report
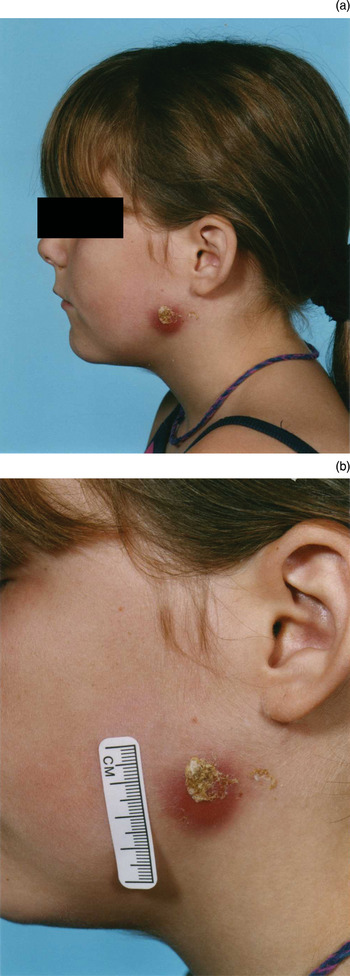
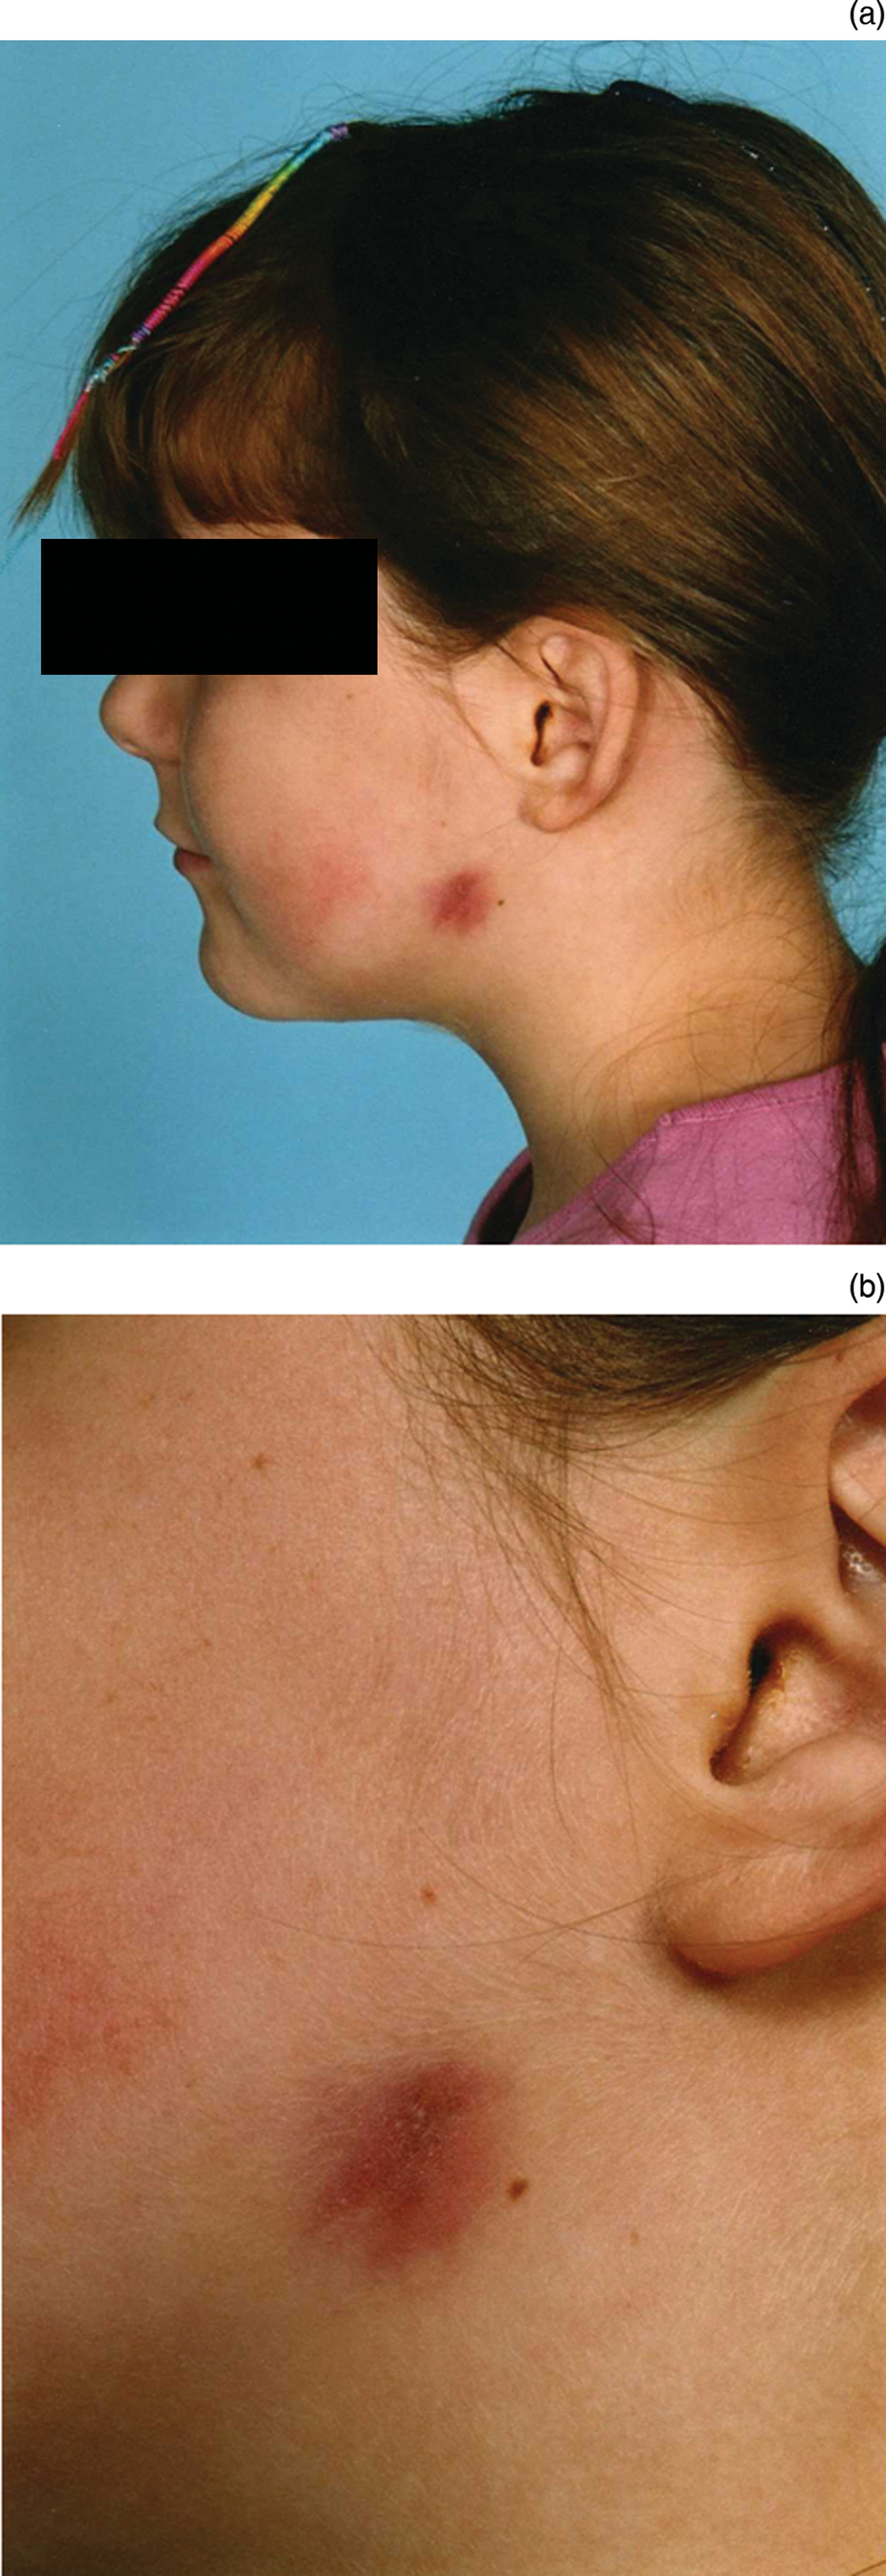
A 10-year-old girl presented with a 6-month history of localised erythema and swelling in the left parotid region (Figure 1). This was diagnosed as an isolated abscess. Aspiration was not considered appropriate in view of the patient's age. She was treated with intravenous co-amoxiclav together with incision and drainage under general anaesthesia. Culture and sensitivity testing of the drained pus demonstrated streptococci and anaerobes sensitive to co-amoxiclav. No sample was sent for histopathological analysis.
Clinical photographs showing the skin inflammation at presentation.

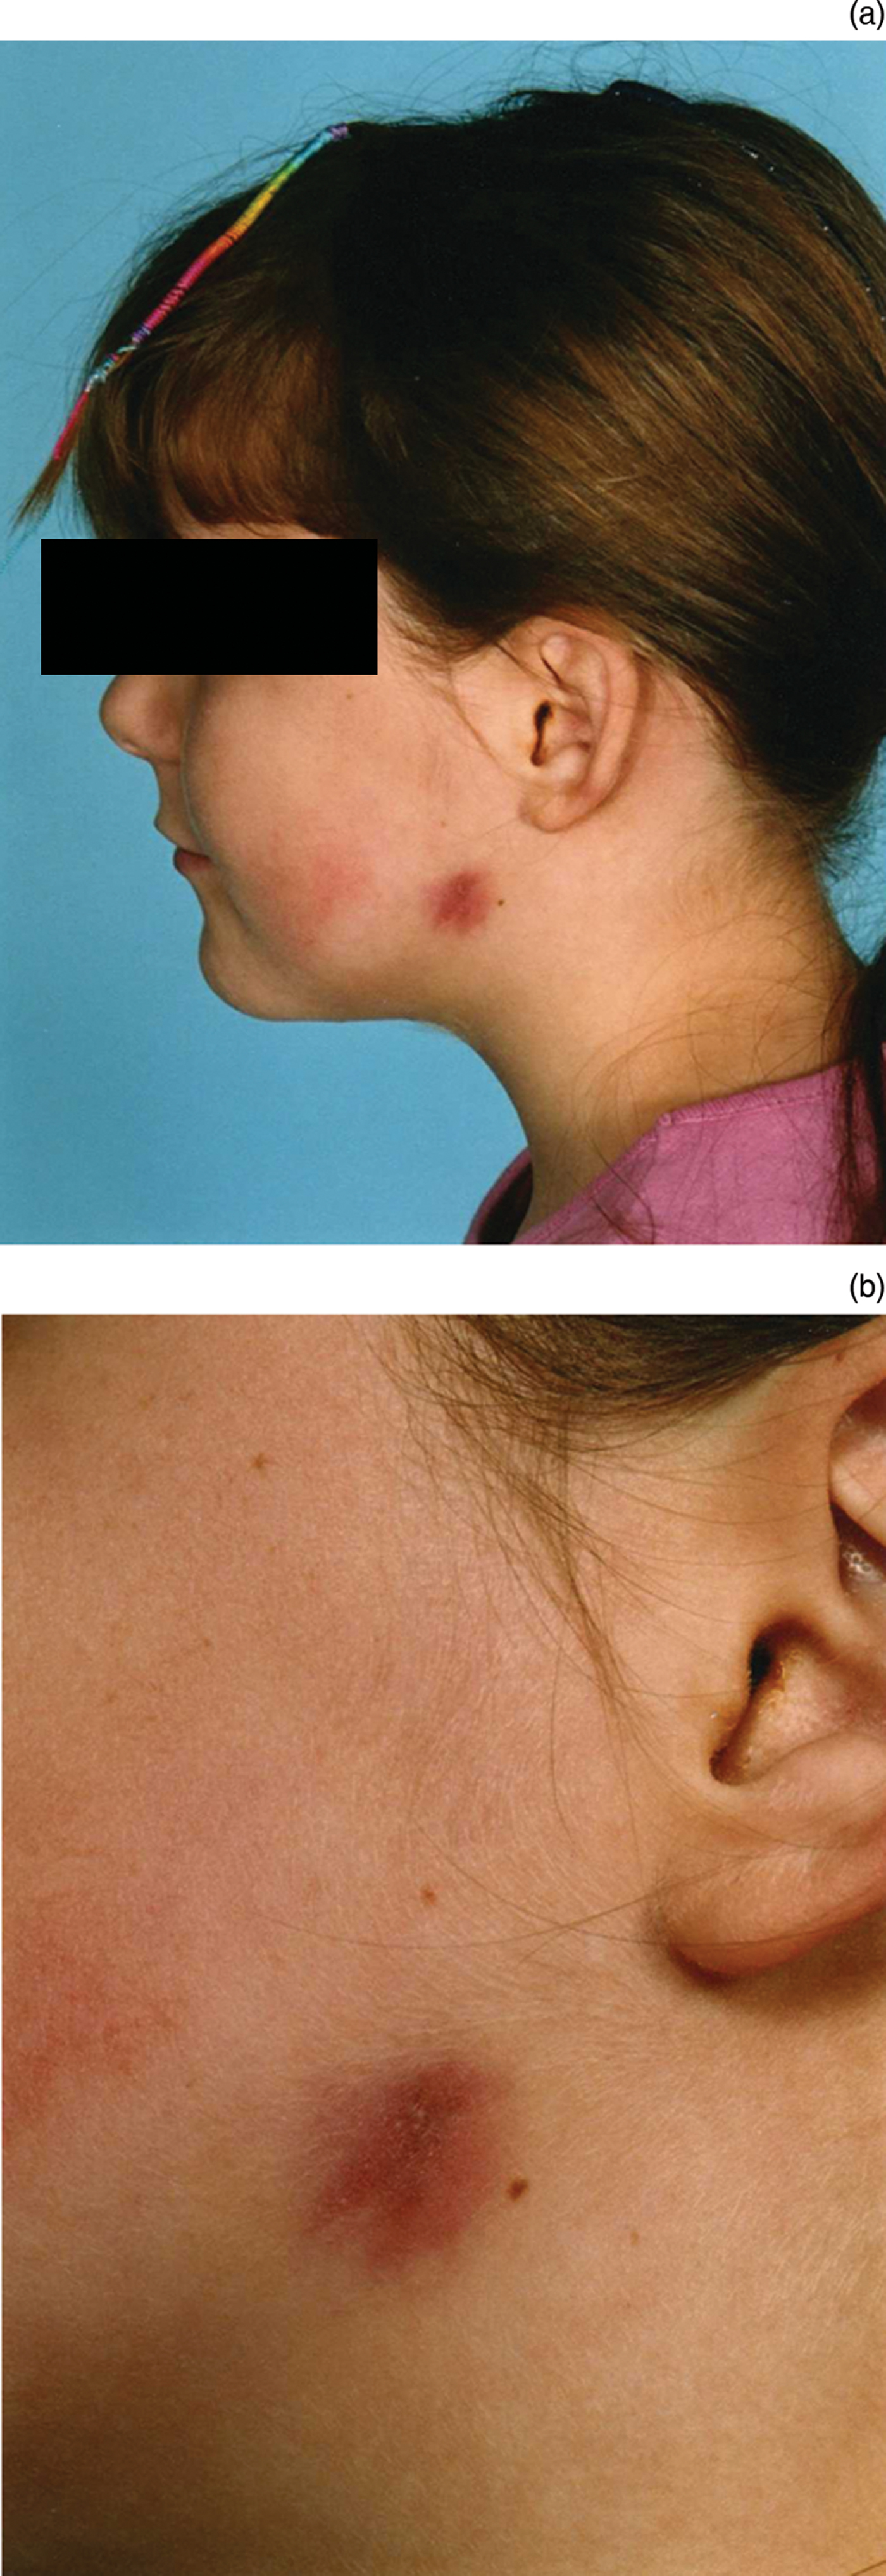
Review at three months showed some improvement in the area of inflammation (Figure 2). At nine months, it was concluded that the inflammation had settled, and the patient was discharged.
Clinical photographs showing the skin inflammation at three-month follow up, after intravenous antibiotics, incision and drainage.
Four years later, the patient re-presented to the senior author with multiple further episodes of discharge and failure of resolution of the area of inflammation. In addition to discharge, the patient also described pain which radiated to the left ear.
A first branchial cleft abnormality was suspected, although the differential diagnosis included atypical mycobacterial and actinomyces infections.
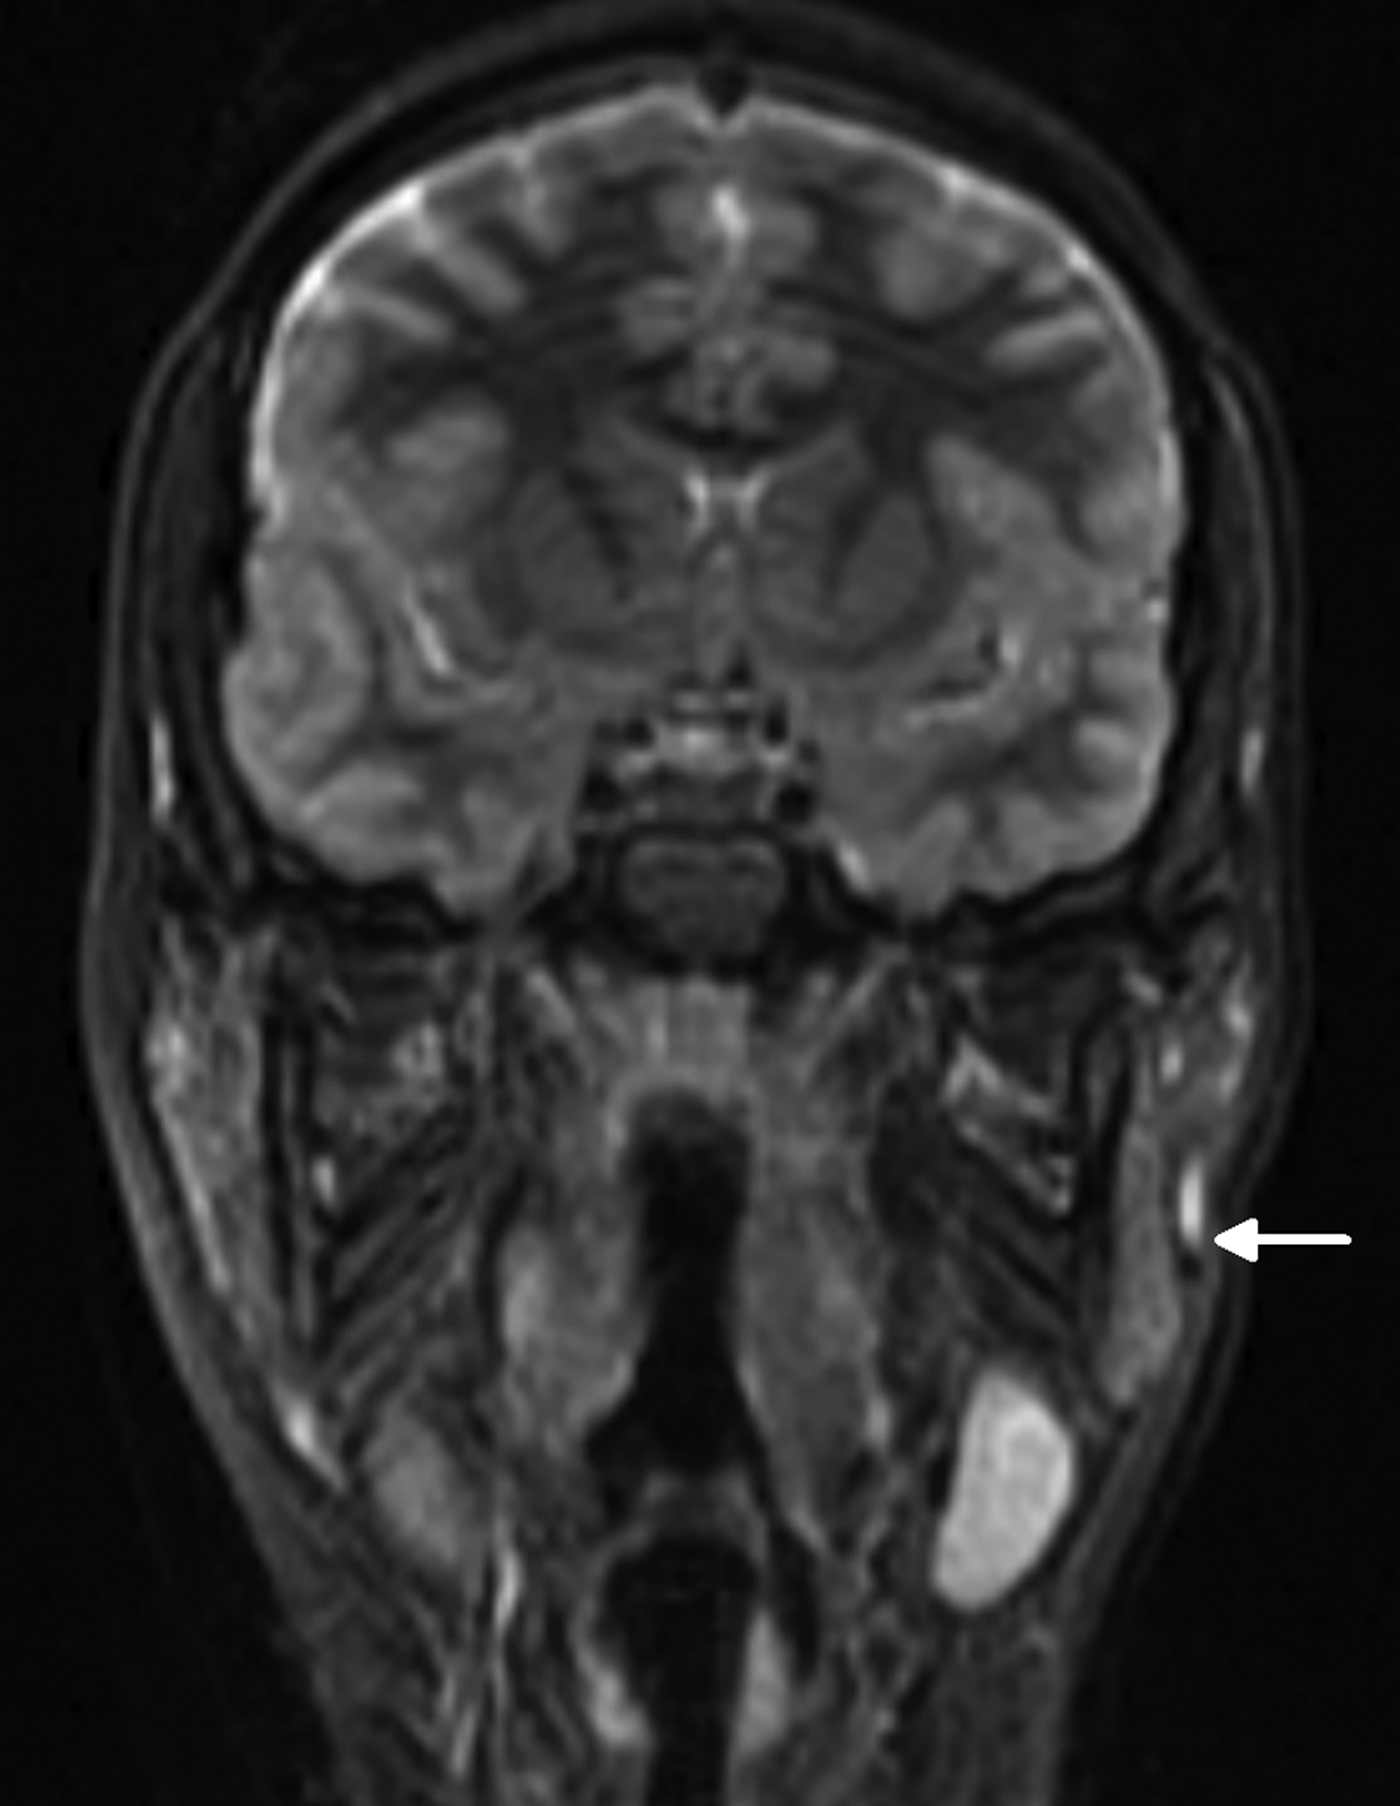
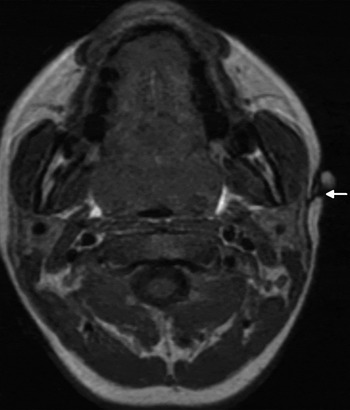
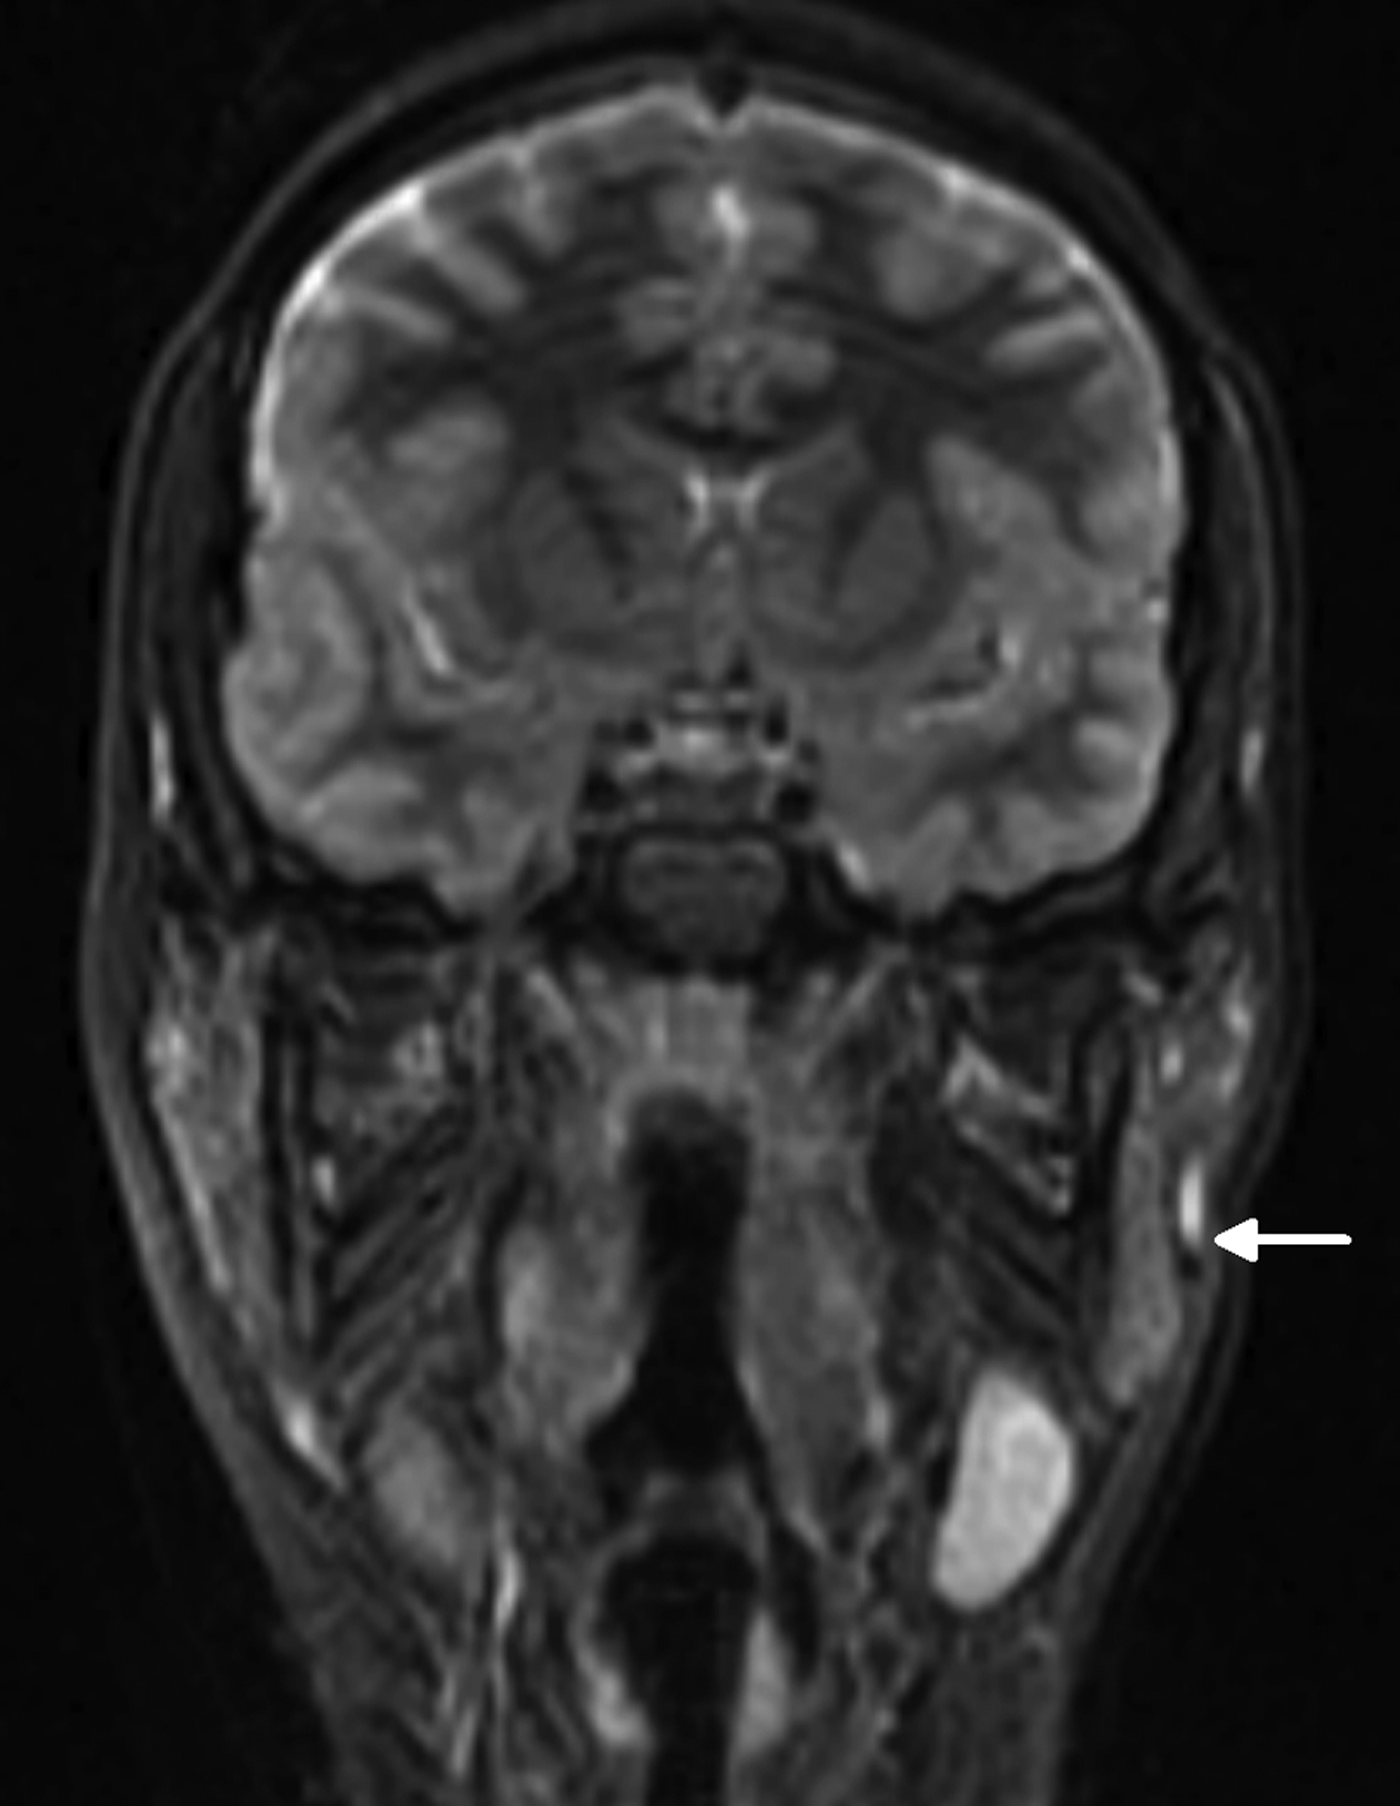
The lesion was investigated with magnetic resonance imaging. This demonstrated a fluid-filled sinus tract originating adjacent to the anterior wall of the cartilaginous left external auditory canal. The sinus tract was seen to extend anteriorly and inferiorly through the superficial lobe of the left parotid, and to open onto the left cheek lateral to the left masseter, with inflammation of the surrounding skin (Figures 3 to 5).
Fat-saturated, T2-weighted, axial magnetic resonance imaging scan showing a fluid collection (arrow) anterior to the cartilaginous left external auditory canal.

Coronal, short T1 inversion recovery magnetic resonance imaging scan showing the sinus tract (arrow) extending along the superficial lobe of the left parotid.
Axial, T1-weighted magnetic resonance imaging scan showing the opening of the sinus tract in the skin (arrow).

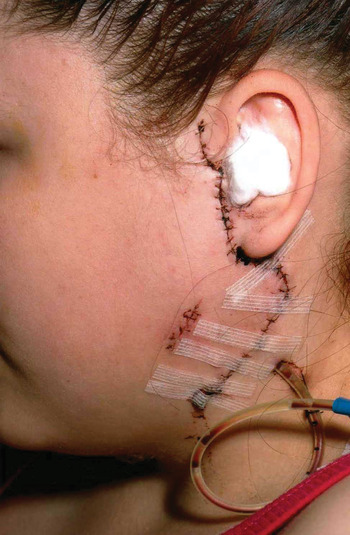
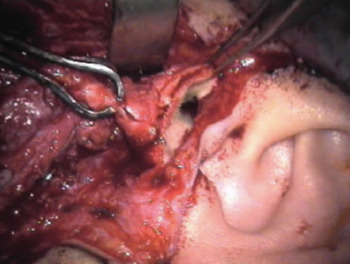
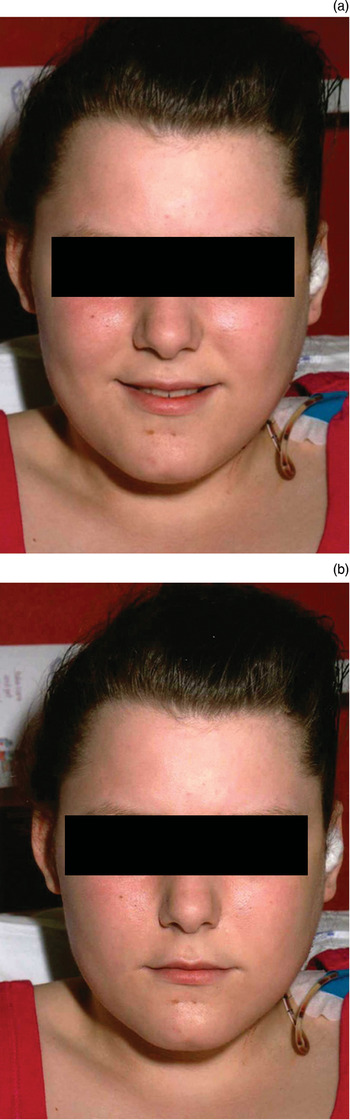
The tract was explored and excised under general anaesthesia. Two separate incisions were used, one at the site of the external opening on the lower face, and the second a classical parotidectomy incision (Figure 6). The tract was found to extend medial to the facial nerve and to terminate in the medial aspect of the anterior cartilaginous external auditory canal. The tract was cartilaginous and formed a duplicate external canal (Figure 7). Following excision, the external ear canal was reconstructed. The facial nerve and its branches were preserved (Figure 8). The ear canal was packed with bismuth iodoform paraffin paste (‘BIPP’) and the wound closed.
Post-operative clinical photograph showing the two separate skin incisions.

Peri-operative photograph showing the tract and the cartilaginous duplicate ear canal.

Clinical photographs showing post-operative facial nerve function.

The patient made an uneventful recovery.
Discussion
Branchial anomalies occur when there is disturbance in the maturation of the branchial apparatus during the fourth to eighth week of fetal development. In the normally developed fetus, the first branchial cleft gives rise to the external auditory canal and the lateral aspect of the tympanic membrane.
Anomalies of the first branchial cleft have previously been classified as anomalies of aplasia, atresia, stenosis and duplication of the external auditory canal.Reference Karmody, Bluestone, Stool and Scheetz6 The tract excised in this case was a duplication anomaly.
Typically, duplication anomalies demonstrate a normally developed external auditory canal along with a sinus tract extending from the external auditory canal to the skin of the face or neck. The position of the skin opening of the tract characteristically lies on a virtual line joining the tragus to the hyoid, whilst the upper end of the tract runs inferior or anterior to the external auditory canal and terminates at the osteo-cartilaginous junction.Reference Bull and Gleeson2 The course of the sinus tract is unpredictable and can run medial or lateral to the facial nerve; in addition, the course of the facial nerve and relevant landmarks may differ in children compared with adults.Reference Hussain and Gleeson7
Duplication anomalies have been subclassified by Work into types one and two.Reference Work8 This categorisation differentiates between tracts which arise from purely ectodermal material (type one) and tracts which in addition contain mesoderm-derived material in the form of a cartilaginous component. Case reports of duplicate tracts that do not fit within this classification (i.e. containing duplicate ossicles) have also been published.Reference Rockey, John and Herbetko9 The tract in our case was of the second type, which is also the more common type.
Magnetic resonance imaging, with its superior soft tissue resolution, is the investigation of choice for accurate delineation of branchial sinus tracts, before contemplating surgery. Fluid-filled sinus tracts show high signal intensity on T2-weighted images and short T1 inversion recovery (‘STIR’) images. The presence of an associated cyst is usually indicated by a well defined, rounded area of fluid signal.
• Diagnosis of first branchial arch anomalies requires heightened clinical suspicion of childhood neck swellings
• Magnetic resonance imaging delineates tract position and facial nerve relationship
The presentations of published first branchial cleft anomaly cases vary. They include otalgia, aural discharge, and as an incidental finding on imaging or otoscopic examination. However, the most common presentation is recurrent swelling, inflammation and discharge from a skin lesion. The differential diagnosis includes atypical mycobacterial and actinomyces infections. The former usually presents as unilateral cervical lymphadenopathy with altered skin coloration.Reference Evans, Smith, Thornton, Youngson and Gray10 The latter is characterised by the formation of abscesses, fibrosis and woody induration of the tissues, and by draining sinuses that discharge ‘sulphur granules’.Reference Oostman and Smego11
This case demonstrates such a presentation. It also emphasises the fact that clinicians should maintain a high index of clinical suspicion for the possibility of a sinus tract when dealing with a neck swelling in a child, in order to avoid inappropriate initial management.