





Introduction
Patients with cancer in palliative care endure many physical and psychological problems that significantly influence their ability to maintain quality of life (Gonçalves et al. Reference Gonçalves, Gaudêncio and Rocha2025; Ibrahim et al. Reference Ibrahim, Mohamed and Shahin2025; Mabonga et al. Reference Mabonga, Luvhengo and Chikanza2026). Symptom burden is often characterized by physical symptoms like pain, fatigue, and nausea, but many patients also experience significant psychological symptoms such as anxiety, depression, fear, uncertainty, emotional suffering, and existential distress related to disease progression and end-of-life concerns (Emery et al. Reference Emery, Butow and Lai-Kwon2022; Tao et al. Reference Tao, Lv and Zhong2024; Lu et al. Reference Lu, Liu and Zhang2025). These complex experiences are related to increased healthcare needs, decreased functional ability, and decline in overall well-being, highlighting the need for comprehensive approaches to the delivery of palliative care (Strang Reference Strang2022; Gonçalves et al. Reference Gonçalves, Gaudêncio and Paiva2024, Reference Gonçalves, Gaudêncio and Rocha2025).
Psychological distress and symptom burden are highly correlated and may affect each other bidirectionally throughout the cancer trajectory (Shafiq et al. Reference Shafiq, Malhotra and Teo2022). Physical symptoms can intensify emotional distress, and psychological distress can amplify the perception of symptoms, diminish coping capacity, and adversely impact patients’ overall functioning and quality of life (Strang Reference Strang2022; Gonçalves et al. Reference Gonçalves, Gaudêncio and Paiva2024, Reference Gonçalves, Gaudêncio and Rocha2025). This mutual relationship highlights the need for symptom management strategies that address both the physiological and psychosocial aspects of suffering in cancer, instead of just focusing on physical symptoms (Zarei et al. Reference Zarei, Kazemi and Bahrami2025; Paul Reference Paul2026).
Oncology nurses are crucial in delivering holistic palliative care due to their ongoing contact with patients and their ability to identify complex physical and emotional needs (Jefford et al. Reference Jefford, Howell and Li2022; Corriero et al. Reference Corriero, Giglio and Soloperto2025; Mirzadeh et al. Reference Mirzadeh, Pituskin and Au2025; Terziev et al. Reference Terziev, Petrova and Georgiev2026). The nurse’s role is more than symptom assessment and management and includes emotional support, therapeutic communication, psychosocial assessment, patient education, and individualized care planning (Bashkin et al. Reference Bashkin, Asna and Amoyal2023; de Munter Reference de Munter2023; Komatsu and Komatsu Reference Komatsu and Komatsu2023). Evidence suggests that structured nurse-led interventions can improve symptom management, increase patient satisfaction, and enhance palliative care outcomes. Therefore, integrating clinical judgment with comprehensive psychosocial assessment is essential for delivering person-centered oncology palliative care (Lanfear and Harding Reference Lanfear and Harding2023; Zhang et al. Reference Zhang, Hong and Chen2025; Ibrahim and Zaghamir Reference Ibrahim and Zaghamir2026; Ohana et al. Reference Ohana, DeKeyser Ganz and Shaulov2026).
Conventional healthcare practices tend to respond to deterioration only after severe symptoms have emerged, leading to late management and increased patient suffering (Jefford et al. Reference Jefford, Howell and Li2022; Corriero et al. Reference Corriero, Giglio and Soloperto2025; Terziev et al. Reference Terziev, Petrova and Georgiev2026). In this setting, laboratory markers may provide objective data on the underlying physiological changes associated with worsening symptoms as an adjunct to psychosocial assessment and patient-reported outcomes. Hemoglobin, C-reactive protein (CRP), albumin, sodium, potassium, calcium, and white blood cell (WBC) count are routinely monitored laboratory parameters in oncology practice and have been associated with symptom burden, inflammatory status, nutritional status, functional decline, and clinical outcomes in patients with advanced cancer (Özdemir et al. Reference Özdemir, Espinosa da Silva and Arangalage2023; Nemlander Reference Nemlander2025; Sah Reference Sah2025). The combination of objective laboratory findings with patients’ reported experiences might enable earlier detection of deterioration and help in the proactive management of symptoms, but laboratory indicators should complement, not replace, the assessment of patients’ subjective experiences, and psychological needs (Passaro et al. Reference Passaro, Al Bakir and Hamilton2024; Molla and Bitew Reference Molla and Bitew2025; Shah et al. Reference Shah, Aalam and Parveen2025).
Although there is a growing body of evidence for nursing interventions in oncology palliative care, few studies have explored psychosocial outcomes alongside symptom management approaches that incorporate objective clinical indicators. However, little is known about the relationship between laboratory parameters and symptom severity and whether the integration of these indicators with nursing clinical judgment can improve personalized symptom management strategies (AlDoughaim et al. Reference AlDoughaim, AlSuhebany and AlZahrani2024; Passaro et al. Reference Passaro, Al Bakir and Hamilton2024; Molla and Bitew Reference Molla and Bitew2025; Shah et al. Reference Shah, Aalam and Parveen2025). Therefore, future studies are needed to develop evidence-based predictive approaches that consider the multidimensional nature of suffering in patients with advanced cancer receiving palliative care, by integrating biological indicators, patient-reported symptoms, psychological assessment, and individualized nursing interventions to improve symptom control, emotional well-being, and quality of life.
Theoretical framework
This study is based on symptom management theory (SMT). SMT views symptom experience as a multidimensional phenomenon that is influenced by physiological, psychological, and environmental factors. SMT suggests that symptoms are not merely isolated clinical manifestations, but are influenced by the interaction between the individual’s health status, personal characteristics, treatment-related factors, and the surrounding environment. The theory is based on 3 linked dimensions, namely symptom experience, symptom management strategies, and symptom outcomes, informing assessment and intervention approaches in clinical practice (Dodd et al. Reference Dodd, Janson and Facione2001; Humphreys et al. Reference Humphreys, Janson, Donesky, Smith and Liehr2014; Conchon et al. Reference Conchon, Nascimento and Fonseca2015; Mathew et al. Reference Mathew, Doorenbos and Vincent2021; Chapman et al. Reference Chapman, Pini and Edwards2022).
In the context of oncology palliative care, psychological distress (anxiety, depression, fear, uncertainty, and emotional suffering) may affect the perception and response of patients to symptoms. SMT posits that psychological factors can alter the way symptoms are identified and understood, resulting in greater perception and burden. Psychological distress may thus contribute to a cycle where increased symptom awareness enhances distress, negatively affects coping responses, and consequently compromises quality of life (Dodd et al. Reference Dodd, Janson and Facione2001; Humphreys et al. Reference Humphreys, Janson, Donesky, Smith and Liehr2014; Conchon et al. Reference Conchon, Nascimento and Fonseca2015; Mathew et al. Reference Mathew, Doorenbos and Vincent2021; Chapman et al. Reference Chapman, Pini and Edwards2022).
The present study uses SMT by proposing a pathway through which psychological distress influences symptom perception, symptom response, and ultimately quality of life. Physiological indicators, including laboratory parameters, may also reflect underlying biological changes related to disease progression and treatment effects, which may contribute to severity of symptoms. Therefore, the combination of patient-reported symptoms and clinical and laboratory indicators offers a comprehensive perspective on symptom burden in patients receiving oncology palliative care (Wei et al. Reference Wei, Yan and Xiang2024).
According to the principles of SMT, nursing-led interventions should include systematic assessment of symptoms, early identification of symptom changes, and individualized management strategies to minimize symptom burden and optimize patient outcomes. Thus, this study developed and tested the predictive symptom management program based on SMT as a guiding framework, which can facilitate proactive nursing care by integrating symptom assessment tools, clinical judgment, and laboratory findings to improve symptom control and quality of life (Xu et al. Reference Xu, Chen and Shen2022; Weiss et al. Reference Weiss, Franck and Leutwyler2023; Wei et al. Reference Wei, Yan and Xiang2024; Lu et al. Reference Lu, Liu and Zhang2025; Holland et al. Reference Holland, Nohavicka and Harrop2026).
Conceptual framework
The study’s conceptual framework is based on 3 domains that comprise nursing-led intervention, patient-reported outcomes, and clinical biomarkers, as illustrated in Figure 1. The independent variable is a nurse-led predictive symptom management program which includes structured weekly assessments, symptom monitoring, and training, and individualized care based on laboratory findings. The dependent variables include Quality of life, which EORTC QLQ C30 measures; symptom burden, which ESAS assesses; psychological distress, which HADS measures; and functional status, which ECOG Performance Status evaluates. Laboratory indicators, such as hemoglobin, C-reactive protein, WBC count, electrolytes, and albumin, are moderators and predictive markers and provide objective clinical insight that may influence symptom experience and response to intervention (Saeed Reference Saeed2026). The framework predicts that the intervention will decrease the symptom burden and improve quality of life (QoL), because laboratory indicators will provide links between their results and symptom severity, enabling healthcare providers to design personalized nursing care plans and identify patients with a greater likelihood of experiencing a severe symptom increase.
Conceptual framework of the study.

Aim of the study
This study evaluated the effects of a nursing-led symptom management program on psychosocial outcomes, symptom burden, quality of life, and their relationship with selected laboratory indicators.
Objectives of the study
➢ To evaluate differences in psychological distress (anxiety and depression) between the intervention and control groups using the Hospital Anxiety and Depression Scale (HADS).
➢ To compare symptom burden and severity between the intervention and control groups using the Edmonton Symptom Assessment System (ESAS).
➢ To assess differences in quality of life between the intervention and control groups using the European Organisation for Research and Treatment of Cancer Quality of Life Questionnaire 30.
➢ To assess differences in functional status between the intervention and control groups using the Eastern Cooperative Oncology Group (ECOG) Performance Status.
➢ To examine the correlations between selected laboratory indicators (hemoglobin, CRP, WBC count, electrolytes, albumin, and calcium) and total symptom burden (ESAS) among all participants.
Method
Research design
The effectiveness of the nursing-led predictive symptom management program was evaluated in a quasi-experimental study with 2 parallel groups (intervention and control). This design was chosen to allow comparison of outcomes between patients receiving the intervention and those receiving standard care under real-world clinical conditions. This study was reported according to the Transparent Reporting of Evaluations with Nonrandomized Designs guidelines.
Study setting
The study was performed in the oncology and palliative care units of a governmental secondary-care hospital in Al-Kharj, Saudi Arabia. The hospital offers comprehensive oncology services including chemotherapy, supportive care, and palliative care management for adult cancer patients. The setting was chosen as it had a diverse population of patients and established palliative care services, which enabled the nursing-led intervention to be implemented and routine laboratory investigations and multidisciplinary care to be accessed.
Sample size determination
The sample size was estimated by G*Power software (version 3.1) based upon a priori power analysis for comparison between 2 independent groups. A medium effect size (d = 0.5), an alpha level (α = 0.05), and statistical power (1 − β = 0.80) were assumed, which are standard parameters in clinical research. Based on these inputs, the sample size needed was 128 participants (64 per group) (Kang Reference Kang2021). An additional 10–15% was added to cover possible dropouts or non-responses, bringing the final target sample size to 150 participants.
Sampling technique
All eligible patients who met the inclusion criteria were recruited during the study period by a consecutive sampling technique. Participants were recruited sequentially with allocation to intervention or control group (e.g., by order of admission to the unit or based on unit workflow) to ensure feasibility within routine clinical practice and to minimize disruption to care delivery.
Inclusion criteria
Participants were included if they met the following criteria
• Adult patients aged 18 years or older
• Diagnosed with any type of cancer and receiving palliative care
• Able to communicate verbally and provide informed consent
• Had available baseline laboratory investigations (e.g., hemoglobin, CRP, WBC, electrolytes)
• Had an expected survival of at least 3 months, allowing participation in the study period
Exclusion criteria
• Participants were excluded if they met any of the following criteria:
• Patients with severe cognitive impairment or altered consciousness preventing reliable self-reporting
• Patients in end-stage condition or actively dying
• Patients with diagnosed psychiatric disorders that could interfere with study participation
• Patients enrolled in another interventional clinical trial
• Patients with incomplete medical or laboratory records
Data collection tools
Data were collected using a structured set of standardized and researcher-developed instruments to comprehensively assess patients’ quality of life, symptom burden, psychological status, functional performance, and clinical characteristics.
Demographic and clinical data sheet
After an extensive review of the relevant literature, the researchers designed a structured data sheet for demographics and clinical data. It gathered data about participants’ baseline characteristics such as age, gender, marital status, educational level, and employment status. Furthermore, clinical data such as cancer type, stage of disease, duration of illness, treatment modality (chemotherapy, radiotherapy, and immunotherapy), comorbidities, and previous hospitalizations were collected. Further details were recorded on medication use, particularly analgesics and opioids, and prior contact with palliative care services. Content validity was established by an expert panel of oncology and palliative care experts. A pilot study was carried out on 10% of the sample for testing clarity and feasibility. The necessary changes were made accordingly.
Hospital Anxiety and Depression Scale
The HADS is a self-report screening instrument for psychological distress in the medically ill population, such as oncology and palliative care patients. It has two 7-item subscales that measure anxiety (HADS-A) and depression (HADS-D), while minimizing confounding by somatic symptoms (e.g., fatigue or sleep problems) that are common in medical illness. Each item is scored 0–3, with subscale scores of 0–21; higher scores suggest more distress, and scores above cut-offs (e.g., ≥8) suggest clinically significant anxiety or depression (Zigmond and Snaith Reference Zigmond and Snaith1983). The HADS has been validated in a wide range of languages and clinical settings with good internal consistency and construct validity. It is frequently used in oncology research to assess mood disorders and to evaluate psychological outcomes related to symptom management interventions (Zigmond and Snaith Reference Zigmond and Snaith1983).
Edmonton Symptom Assessment System – Revised
The Edmonton Symptom Assessment System – Revised (ESAS-r) is a brief patient-reported symptom intensity tool developed for palliative cancer populations which allows patients to rate the severity of 9 core symptoms – pain, tiredness, nausea, depression, anxiety, drowsiness, appetite, shortness of breath and overall well-being – on a 0–10 numerical rating scale (0 = no symptom, 10 = worst possible) allowing longitudinal tracking of symptom burden (Cleeland et al. Reference Cleeland, Mendoza and Wang2000). It is designed for repeated use in routine clinical and research settings to provide rapid screening and monitoring of symptom severity, where higher scores reflect increased symptom distress. ESAS-r has shown good internal consistency reliability (e.g., Cronbach’s α of around 0.85 in some populations) and concurrent validity with moderate to strong correlations with other validated symptom measures such as MDASI. Its brevity and clinical relevance make it especially useful in palliative care settings in which symptom monitoring drives care decisions (Cleeland et al. Reference Cleeland, Mendoza and Wang2000; Watanabe et al. Reference Watanabe, Nekolaichuk and Beaumont2011).
The Palliative Outcome Scale is frequently used in palliative care research, but the EORTC QLQ-C30 was chosen as it is a well-validated cancer-specific quality-of-life instrument that comprehensively assesses the domains of functioning, symptom burden, and global quality of life in oncology patients. Moreover, the ESAS-r was added to enable a focused assessment of symptom severity and symptom distress, thus complementing the quality of life assessment. Combined use of EORTC QLQ-C30 and ESAS-r allowed for a more comprehensive assessment of overall quality of life and specific symptom experiences of patients receiving oncology palliative care.
EORTC QLQ-C30 Version 3.0
The European Organization for Research and Treatment of Cancer Quality of Life Questionnaire – Core 30 (EORTC QLQ-C30, Version 3.0) is a widely accepted cancer-specific health-related quality of life patient-reported outcome instrument for international oncology research and clinical practice, assessing the impact of disease and treatment on QoL across cancer types (Aaronson et al. Reference Aaronson, Ahmedzai and Bergman1993). The questionnaire consists of 30 items comprising 5 functional scales (physical, role, emotional, cognitive, social), 3 symptom scales (fatigue, pain, nausea/vomiting), a global health/QoL scale, and 6 single-symptom items (e.g., dyspnoea, appetite loss) to address common patient concerns; responses are scored on 4- or 7-point Likert scales and converted to 0–100 scores, with higher scores on functioning indicating better QoL and higher scores on symptoms indicating worse symptom burden. It has been extensively validated for construct, discriminant, and criterion validity in diverse cancer populations and maintains acceptable internal consistency (Cronbach’s α generally >0.70) across most subscales, with demonstrated responsiveness to clinical change in longitudinal studies ((Aaronson et al. Reference Aaronson, Ahmedzai and Bergman1993).
ECOG performance status
The ECOG Performance Status is a clinician-rated functional assessment scale that is widely used in oncology research and clinical practice. It quantifies a patient’s ability to perform daily activities and self-care, ranging from 0 (fully active) to 5 (death), based on observable performance criteria such as ambulatory capacity and self-care ability. Its origins are in a 1982 publication by Oken and colleagues, and it is firmly embedded in trial eligibility criteria and prognostic modeling. The ordinal scoring is simple and allows for consistent classification and stratification of functional status. Its clinical relevance and predictive validity for outcomes such as survival have been supported by multiple studies. Inter-rater reliability may vary, but clinician training can improve consistency. ECOG status is a major prognostic and stratification measure in oncology and palliative care studies (Oken et al. Reference Oken, Creech and Tormey1982).
Laboratory investigations
Objective clinical indicators were collected from laboratory investigations to support the predictive symptom management approach. Data were collected from patients’ medical records using standardized hospital laboratory procedures. The parameters assessed included hemoglobin (Hb) to assess fatigue and dyspnoea due to anemia, CRP as a marker of systemic inflammation, and WBC count with differential to detect infection or inflammatory processes. Serum albumin levels were also measured to assess nutritional status, and levels of electrolytes (sodium, potassium, and calcium) were examined to identify imbalances associated with symptoms such as fatigue, confusion, and nausea. All laboratory measurements were done by calibrated automated analyzers to ensure accuracy and reliability. Data were collected at baseline and at regular intervals during the study period. These laboratory measures were combined with the nurses’ clinical judgment to help them identify worsening symptoms sooner and to determine appropriate individualized interventions in a timely manner.
Intervention: Nursing-led predictive symptom management program
A structured nursing-led predictive symptom management program was delivered to the intervention group, using laboratory indicators and clinical judgment to enable early identification and proactive management of symptom exacerbation. The program was implemented weekly in face-to-face sessions in the oncology outpatient clinic and palliative care units of the study hospital in Al-Kharj, Saudi Arabia. The program was implemented for 6 consecutive weeks. The sessions were approximately 30–45 minutes, and bedside follow-up continued during routine visits/admissions.
The intervention was delivered by oncology nurses with a minimum of 3 years of experience in oncology and palliative care who were trained. Before the study, nurses were given a structured training program including the study protocol, standardized assessment tools, interpretation of laboratory findings, and application of predictive clinical judgment. Learning was facilitated through interactive discussions, demonstration and return demonstration, case-based reasoning, guided counseling, and individualized education. Teaching aids included pictorial educational booklets, symptom monitoring charts, visual analog scales, and simplified laboratory interpretation guides; structured checklists provided consistency and reliability in assessments and interventions.
The program had 6 structured sessions, each with a specific focus. Session 1: Baseline Assessment and Orientation. This session consisted of a comprehensive assessment of quality of life, symptom burden, psychological status, functional performance, and laboratory investigations. Patients and carers were educated on the objectives of the program and the importance of early detection and reporting of symptoms. During Session 2, Symptom Assessment and Monitoring Training, patients were trained to monitor and report symptoms using numerical scales and symptom charts with demonstrations and visual aids. Moreover, nurses conducted emotional assessment and supportive counseling to help patients identify psychological distress, express fears and concerns related to the disease progression, and recognize the relationship between emotional distress and symptom perception.
Session 3, Integration of Laboratory Indicators, employed simplified charts to help patients understand the relationship between laboratory results such as hemoglobin, CRP, WBC count, and electrolytes and symptom development and promoted discussion. Session 4: Predictive clinical decision-making. Nurses talked about how they used laboratory results with their clinical judgment to predict patients at risk for exacerbation of symptoms and to create individualized care plans with the multidisciplinary team. The session also involved supportive communication techniques, coping assessment, and family participation to improve emotional support, improve collaboration between patient and carer, and manage psychosocial issues related to advanced cancer and palliative care.
Session 5, Symptom Management and Self-Care Strategies, included education about pharmacological and non-pharmacological interventions for pain, fatigue, nausea, anxiety, and other common symptoms, including demonstration and return demonstration of practical techniques (e.g., breathing exercises, relaxation, activity pacing). Carers were actively involved to facilitate adherence. Psychological coping strategies were also suggested, such as relaxation techniques, stress management approaches, emotional regulation strategies, and ways to reduce anxiety related to symptoms and disease uncertainty. In Session 6, evaluation and reinforcement, the clinician reviewed patient progress, reinforced strategies that the patient learned, ensured that the patient understood how to monitor symptoms, and helped the patient learn how to communicate with his/her healthcare providers for ongoing management of his/her condition. Emotional reinforcement and psychological support included encouragement, validation of patient concerns, and reinforcement of coping strategies. Patients with significant psychological distress were evaluated and referred to appropriate psychosocial or mental health support services as required.
Intervention was delivered at the patient level. Intervention group participants received individualized symptom assessment, laboratory review, education, and symptom-management support according to the structured nursing-led protocol. Individualized support included psychosocial assessment, therapeutic communication, emotional support, and guidance for patients and carers to cope with challenges of advanced cancer and palliative care. Group sessions were not conducted. The intervention was provided by registered nurses working in the oncology and palliative care units. All nurses had a bachelor’s degree in nursing at minimum and 3 or more years of clinical experience in oncology or palliative care. Prior to study implementation, the nurses were given standardized training in symptom assessment and interpretation of laboratory findings, administration of study instruments, and implementation of the nursing-led symptom management protocol to promote consistency in the delivery of the intervention.
Participants were followed up weekly with structured assessments and laboratory tests during the intervention period. Checklists and structured documentation were used by nurses to standardize evaluation and timely intervention. The control group was given routine standard care without structured predictive symptom management. There were no dropouts in the 6-week program, likely due to its short duration, its integration into routine clinical care, and the nursing team’s close involvement and follow-up.
The clinical-trial registry does not prospectively register this study. As the study commenced, the intervention was deemed a pragmatic nursing-led service evaluation within routine clinical practice. In view of the current international guidance on interventional studies, however, the absence of prospective registration is acknowledged to be a limitation of the study.
Statistical analysis
All data were analyzed by IBM SPSS Statistics version 26 (IBM Corp., Armonk, NY, USA). Descriptive statistics (frequencies, percentages, means, and standard deviations) were used to summarize participants’ demographic, clinical, and laboratory characteristics. The normality of continuous variables was tested before the inferential analysis using the Shapiro–Wilk test and visual inspection of histograms and Q–Q plots. The results indicated that the variables in the study were approximately normally distributed, and therefore parametric statistical tests were considered appropriate. Categorical variables were compared by Chi-square tests between the intervention and control groups. Independent-samples t-tests were used to compare continuous variables, including EORTC QLQ-C30 subscale scores, ESAS scores, HADS scores, ECOG performance status, and laboratory parameters. Effect sizes were calculated using Cohen’s d to determine the magnitude of difference between groups for continuous outcomes. The association between total ESAS scores and laboratory parameters was evaluated using Pearson correlation coefficients. All statistical tests were 2-tailed, and statistical significance was set at p < 0.05. Where possible, exact p-values are reported; for p-values <0.001, the value is given as p < 0.001.
Results
A total of 178 patients were assessed for eligibility. Of these, 18 did not meet the inclusion criteria, and 10 declined participation. The remaining 150 participants were enrolled and allocated to either the intervention group (n = 75) or the control group (n = 75). All participants completed the 6-week follow-up period and were included in the final analysis. The participant flow through the study is presented in Figure 2.
TREND participant flow diagram.

Figure 2 Long description
The TREND participant flow through a study is illustrated in a flowchart. It begins with the enrollment stage, where 178 patients receiving oncology palliative care were assessed for eligibility. Out of these, 28 were excluded for reasons such as not meeting inclusion criteria, being under 18 years, not receiving palliative care, cognitive impairment, other reasons, or declining to participate. This left 150 patients who met the inclusion criteria and consented to participate. The allocation stage shows the division into two groups: 75 patients were allocated to the intervention group, receiving a nursing-led predictive symptom management program for six weeks and 75 patients were allocated to the control group, receiving usual palliative care as routinely provided. In the follow-up stage, no participants were lost to follow-up in either group, with all completing the six-week intervention or usual care and assessments. Finally, the analysis stage indicates that all 75 participants in each group were included in the final analysis. The flowchart is labeled with ′TREND = Transparent Reporting of Evaluations with Nonrandomized Designs.′.
As shown in Table 1, the intervention (n = 75) and control (n = 75) groups demonstrated comparable baseline sociodemographic and clinical characteristics. The distributions of age, gender, marital status, educational level, and employment status were similar between groups. Likewise, no statistically significant differences were observed in cancer type, disease stage, duration of illness, treatment modality, comorbidities, previous hospitalizations, or analgesic use (all p > 0.05). These findings indicate that the intervention and control groups were well balanced at baseline, minimizing potential confounding and supporting the comparability of the study population prior to implementation of the nursing-led predictive symptom management program.
Demographic and clinical characteristics of the intervention and control groups (n = 75 per group)

Table 1 Long description
Demographic and clinical variables are listed by category with counts and percentages for the Intervention group and the Control group, plus a p-value for each variable. Age in years is grouped as 18 to 29, 30 to 44, 45 to 59, and 60 to 79, with Intervention 13, 17, 24, and 21 and Control 12, 18, 23, and 22. Gender includes Male and Female, with Intervention 34 and 41 and Control 33 and 42. Marital Status includes Single, Married, Widowed, and Divorced, with Intervention 18, 23, 17, and 17 and Control 17, 24, 16, and 18. Education includes None, Primary, Secondary, University, and Postgraduate, with Intervention 15, 18, 15, 16, and 11 and Control 16, 19, 14, 15, and 11. Employment includes Employed, Unemployed, Retired, and Student, with Intervention 24, 18, 20, and 13 and Control 23, 19, 20, and 13. Cancer Type includes Breast, Colon, Liver, Lung, Prostate, and Other, with Intervention 15, 13, 12, 18, 11, and 6 and Control 16, 12, 11, 19, 10, and 7. Cancer Stage includes I, II, III, and IV, with Intervention 18, 22, 21, and 14 and Control 19, 21, 20, and 15. Duration in months is grouped as 1 to 19, 20 to 38, and 39 to 57, with Intervention 25, 26, and 24 and Control 24, 27, and 24. Treatment Type includes Chemotherapy, Radiotherapy, Immunotherapy, and Combination, with Intervention 21, 18, 19, and 17 and Control 22, 17, 20, and 16. Comorbidities are No and Yes, with Intervention 39 and 36 and Control 40 and 35. Previous Hospitalizations are 0, 1, 2, 3, and 4, with Intervention 16, 18, 15, 13, and 13 and Control 17, 18, 14, 13, and 13. Analgesic Use is No and Yes, with Intervention 38 and 37 and Control 39 and 36.
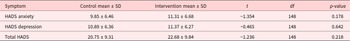
Table 2 presents the post-intervention comparison of psychological distress outcomes measured using the HADS. No statistically significant differences were observed between the intervention and control groups in anxiety (11.31 ± 6.68 vs. 9.85 ± 6.46; p = 0.178), depression (11.37 ± 6.27 vs. 10.89 ± 6.36; p = 0.642), or total HADS scores (22.68 ± 9.84 vs. 20.75 ± 9.31; p = 0.218). Although the intervention did not produce statistically significant improvements in psychological distress over the 6-week period, these findings provide a basis for evaluating the psychosocial effects of nursing-led symptom management.
Comparison of post-intervention HADS scores between the intervention and control groups

Table 2 Long description
Post intervention HADS outcomes are listed for control and intervention groups, with mean and standard deviation for each symptom and a t test result with degrees of freedom and p value. For HADS Anxiety, the control mean plus or minus standard deviation is 9.85 plus or minus 6.46 and the intervention mean plus or minus standard deviation is 11.31 plus or minus 6.68, with t negative 1.354, df 148, and p value 0.178. For HADS Depression, the control mean plus or minus standard deviation is 10.89 plus or minus 6.36 and the intervention mean plus or minus standard deviation is 11.37 plus or minus 6.27, with t negative 0.465, df 148, and p value 0.642. For Total HADS, the control mean plus or minus standard deviation is 20.75 plus or minus 9.31 and the intervention mean plus or minus standard deviation is 22.68 plus or minus 9.84, with t negative 1.236, df 148, and p value 0.218. Across all three rows, the intervention group mean is higher than the control group mean.
Note: An independent-samples t-test was used for comparisons between groups. Statistical significance was set at p < 0.05.
HADS = Hospital Anxiety and Depression Scale; SD = standard deviation; df = degrees of freedom.
As shown in Table 3, symptom burden after intervention was significantly lower in the intervention group than in the control group. The total ESAS scores were significantly lower in the intervention group (34.04 ± 8.86 vs. 41.51 ± 8.48; p < 0.001) with a large effect size (Cohen’s d = 0.86). Pain scores were also significantly lower in the intervention group (4.13 ± 3.07 vs. 5.71 ± 3.30; p = 0.003; d = 0.50). There were no significant differences between the groups in the other symptom scores, but several symptoms, including anxiety and general well-being, showed favorable trends toward improvement after the nursing intervention.
Comparison of post-intervention symptom burden (ESAS) scores between the intervention and control groups (n = 75 per group)

Table 3 Long description
Post intervention ESAS symptom scores are listed for control and intervention groups using mean plus or minus standard deviation, along with t, df, p value, and effect size Cohens d. Pain: control 5.71 plus or minus 3.30, intervention 4.13 plus or minus 3.07, t 3.022, df 148, p value 0.003, d 0.50. Tiredness: 4.77 plus or minus 3.04 versus 5.49 plus or minus 3.48, t minus 1.349, df 148, p value 0.180, d minus 0.22. Nausea: 4.76 plus or minus 3.48 versus 5.08 plus or minus 3.14, t minus 0.592, df 148, p value 0.555, d minus 0.10. Depression: 5.63 plus or minus 3.19 versus 5.08 plus or minus 3.14, t 1.058, df 148, p value 0.292, d 0.17. Anxiety: 5.59 plus or minus 2.74 versus 4.73 plus or minus 3.28, t 1.730, df 148, p value 0.086, d 0.28. Drowsiness: 4.99 plus or minus 3.02 versus 4.91 plus or minus 3.31, t 0.155, df 148, p value 0.877, d 0.03. Appetite: 5.11 plus or minus 3.06 versus 5.08 plus or minus 3.29, t 0.051, df 148, p value 0.959, d 0.01. Shortness of Breath: 4.85 plus or minus 3.28 versus 5.05 plus or minus 3.02, t minus 0.388, df 148, p value 0.698, d minus 0.06. Well being: 5.81 plus or minus 3.32 versus 5.07 plus or minus 2.89, t 1.468, df 148, p value 0.144, d 0.24. Total ESAS Score: control 41.51 plus or minus 8.48, intervention 34.04 plus or minus 8.86, t 5.259, df 147, p value less than 0.001, d 0.86.
Note: Cohen’s d was calculated to estimate effect size. An independent-samples t-test was used for group comparisons. p < 0.05 was considered statistically significant.
ESAS = Edmonton Symptom Assessment System; SD = standard deviation; df = degrees of freedom.
As shown in Table 4, there were no statistically significant differences between the intervention and control groups in the post-intervention quality-of-life outcomes based on the EORTC QLQ-C30, including the functional domains, symptom scales, and global quality-of-life score (all p > 0.0). Fatigue showed a borderline difference between the groups (p = 0.053), while the global quality-of-life score remained similar (52.15 vs. 51.91; p = 0.958). This indicates that the intervention period of 6 weeks was too short to result in measurable improvements in overall quality of life.
Comparison of post-intervention quality of life (EORTC QLQ-C30) scores between the intervention and control groups (n = 75 per group)

Table 4 Long description
Post intervention EORTC QLQ C30 subscale scores are listed as mean values for a control group and an intervention group, each with 75 participants, along with t, df, and p value. Physical functioning shows control mean 49.32 and intervention mean 51.88, t minus 0.548, df 147, p value 0.585. Role functioning shows 49.21 and 50.81, t minus 0.356, df 148, p value 0.723; emotional functioning shows 47.11 and 49.80, t minus 0.614, df 148, p value 0.540; cognitive functioning shows 50.05 and 52.76, t minus 0.565, df 148, p value 0.573. Social functioning shows 46.99 and 43.69, t 0.729, df 148, p value 0.467. Fatigue shows 43.85 and 53.41, t minus 1.949, df 148, p value 0.053; pain shows 51.48 and 54.48, t minus 0.620, df 148, p value 0.536; nausea and vomiting shows 50.35 and 55.19, t minus 0.982, df 148, p value 0.328. Global QoL shows 52.15 and 51.91, t 0.052, df 148, p value 0.958.
Note: An independent-samples t-test was used for comparisons. Higher functional scores indicate better functioning, whereas higher symptom scores indicate greater symptom burden. Statistical significance was set at p < 0.05.
EORTC QLQ-C30 = European Organisation for Research and Treatment of Cancer Quality of Life Questionnaire-Core 30; SD = standard deviation; df = degrees of freedom.
Table 5 shows that there was no significant difference in post-intervention functional status measured by the ECOG Performance Status Scale between the intervention and control groups (2.57 ± 1.80 vs. 2.59 ± 1.72; p = 0.963). These findings indicate that the nursing-led predictive symptom management program did not substantially affect functional performance over the 6-week intervention period.
Comparison of post-intervention functional status (ECOG performance status) between the intervention and control groups (n = 75 per group)

Table 5 Long description
Post-intervention functional status is reported as ECOG Final, with columns for Control Mean plus or minus SD, Intervention Mean plus or minus SD, t, df, and p-value. For ECOG Final, the control group mean is 2.59 with SD 1.72. The intervention group mean is 2.57 with SD 1.80. The t value is 0.046 with df 148. The p-value is 0.963.
Note: An independent-samples t-test was used for comparison between groups. Statistical significance was set at p < 0.05.
ECOG = Eastern Cooperative Oncology Group Performance Status; SD = standard deviation; df = degrees of freedom.
Baseline laboratory parameters were comparable between intervention and control groups (Table 6). There were no statistically significant differences in hemoglobin, CRP, WBC, sodium, potassium, calcium, or albumin levels (all p > 0.05), suggesting similar laboratory profiles prior to implementation of the intervention.
Baseline laboratory parameters of the intervention and control groups (n = 75 per group)

Table 6 Long description
Baseline laboratory categories are listed for intervention and control groups, each reported as n percent, with a p value for each variable. Hemoglobin in grams per deciliter: 8 to 9.99, 21 (28.0) vs 22 (29.3); 10 to 11.99, 23 (30.7) vs 22 (29.3); 12 to 15, 31 (41.3) vs 31 (41.3); p value 0.533. C reactive protein in milligrams per liter: 0.1 to 20, 29 (38.7) vs 25 (33.3); 20.1 to 30, 21 (28.0) vs 21 (28.0); 30.1 to 49.2, 25 (33.3) vs 29 (38.7); p value 0.983. White blood cell count in times 10 to the third per microliter: 3.1 to 6.0, 21 (28.0) vs 34 (45.3); 6.1 to 8.5, 29 (38.7) vs 23 (30.7); 8.6 to 11.9, 25 (33.3) vs 18 (24.0); p value 0.939. Sodium in millimoles per liter: 135 to 138.5, 22 (29.3) vs 23 (30.7); 138.6 to 141.5, 29 (38.7) vs 29 (38.7); 141.6 to 145, 24 (32.0) vs 23 (30.7); p value 0.809. Potassium in millimoles per liter: 3.5 to 3.9, 31 (41.3) vs 28 (37.3); 4.0 to 4.4, 27 (36.0) vs 32 (42.7); 4.5 to 5.0, 17 (22.7) vs 15 (20.0); p value 0.225. Calcium in milligrams per deciliter: 8.0 to 9.0, 24 (32.0) vs 24 (32.0); 9.1 to 10.2, 32 (42.7) vs 28 (37.3); 10.3 to 11.0, 19 (25.3) vs 23 (30.7); p value 0.292. Albumin in grams per deciliter: 3.0 to 3.6, 29 (38.7) vs 25 (33.3); 3.7 to 4.3, 20 (26.7) vs 16 (21.3); 4.4 to 5.0, 26 (34.7) vs 34 (45.3); p value 0.497.
Note: Chi-square test was used for comparison of categorical laboratory variables.
Hb = hemoglobin; CRP = C-reactive protein; WBC = white blood cell count; Na = sodium; K = potassium; Ca = calcium.
At specific time points during the intervention period, significant differences between groups for selected laboratory markers were observed (see Table 7). Hemoglobin levels were significantly higher in the intervention group than in the control group at Weeks 4–6 (all p < 0.05), sodium levels were higher at Weeks 5 and 6 (p = 0.001 and p = 0.010, respectively); potassium levels were higher at Week 6 (p = 0.020), and calcium levels were higher at Week 4 (p < 0.001). There were no significant differences in CRP, WBC, and albumin levels during the 6-week follow-up (all p > 0.05).
Comparison of selected laboratory markers monitored during the 6-week intervention

Table 7 Long description
Laboratory markers are listed by parameter and week from week 1 through week 6, with columns for control mean and standard deviation, intervention mean and standard deviation, t, df, and p value. For haemoglobin, control and intervention means are 11.11 and 11.51 at week 1, 11.45 and 11.41 at week 2, 11.38 and 11.67 at week 3, 10.69 and 11.46 at week 4 with p value 0.024 marked with an asterisk, 10.41 and 11.82 at week 5 with p value 0.000 marked with an asterisk, and 10.57 and 11.28 at week 6 with p value 0.018 marked with an asterisk. For CRP, means range from 21.42 to 25.09 in control and 23.90 to 26.60 in intervention across weeks 1 to 6, with p values 0.853, 0.188, 0.758, 0.290, 0.224, and 0.306. For WBC, means range from 6.96 to 7.81 in control and 7.01 to 7.80 in intervention, with p values 0.489, 0.521, 0.355, 0.903, 0.492, and 0.357. For sodium, means are 139.95 and 139.17 at week 1, 139.59 and 140.39 at week 2, 140.13 and 139.44 at week 3, 139.75 and 140.10 at week 4, 137.90 and 140.26 at week 5 with p value 0.001 marked with an asterisk, and 138.16 and 139.98 at week 6 with p value 0.010 marked with an asterisk. For potassium, means are 4.32 and 4.27 at week 1, 4.23 and 4.26 at week 2, 4.27 and 4.24 at week 3, 4.14 and 4.28 at week 4, 4.30 and 4.29 at week 5, and 4.06 and 4.24 at week 6 with p value 0.020 marked with an asterisk. For calcium, means are 9.42 and 9.52 at week 1, 9.40 and 9.43 at week 2, 9.42 and 9.55 at week 3, 8.66 and 9.43 at week 4 with p value 0.000 marked with an asterisk, 9.53 and 9.49 at week 5, and 9.35 and 9.55 at week 6. For albumin, means are 3.99 and 3.98 at week 1, 3.99 and 4.06 at week 2, 3.92 and 3.91 at week 3, 3.92 and 3.97 at week 4, 3.91 and 4.07 at week 5, and 3.92 and 4.00 at week 6, with p values 0.945, 0.482, 0.879, 0.587, 0.083, and 0.432.
Note: An independent-samples t-test was used for comparisons between groups at each follow-up time point.
Hb = hemoglobin; CRP = C-reactive protein; WBC = white blood cell count; Na = sodium; K = potassium; Ca = calcium; SD = standard deviation; df = degrees of freedom.
* Significant at p < 0.05.
Table 8 shows the correlations of Week 6 symptom burden with selected laboratory markers in the intervention group. CRP was weakly positively correlated with total ESAS scores in a statistically significant manner (r = 0.180, p = 0.028), suggesting that higher inflammatory status was associated with higher symptom burden. Total ESAS scores were not significantly associated with hemoglobin, WBC count, sodium, potassium, calcium, or albumin (all p > 0.05).
Correlations between Week 6 symptom burden (ESAS) scores and selected laboratory markers in the intervention group (n = 75)

Table 8 Long description
Pearson correlation coefficients and p values are listed for week 6 symptom burden scores against seven laboratory parameters in the intervention group. Haemoglobin has Pearson r minus 0.148 with p value 0.071. White blood cells have Pearson r 0.080 with p value 0.330. Sodium has Pearson r minus 0.081 with p value 0.322. Potassium has Pearson r minus 0.050 with p value 0.543. Calcium has Pearson r minus 0.107 with p value 0.194. Albumin has Pearson r minus 0.043 with p value 0.598.
Note: Pearson correlation coefficient was used to examine associations between symptom burden and laboratory parameters.
ESAS = Edmonton Symptom Assessment System; Hb = hemoglobin; CRP = C-reactive protein; WBC = white blood cell count; Na = sodium; K = potassium; Ca = calcium.
* Significant at p < 0.05.
Discussion
The aim of the study was to evaluate the effectiveness of the nursing-led predictive symptom management program, including systematic symptom assessment, individualized nursing interventions, and selected laboratory indicators in patients receiving oncology palliative care. The findings provide important insights into the multidimensional nature of palliative outcomes. Improvements in physical symptom burden may precede measurable changes in psychological distress, quality of life, and functional status. The intervention resulted in a significant reduction in overall symptom burden and pain severity. However, the psychological outcomes measured by the HADS, quality of life indicators, and functional status did not show statistically significant improvements within the 6-week intervention period. These findings underscore the complicated process of adaptation in patients with advanced cancer, where physical comfort, emotional adjustment, and existential well-being often progress at different rates.
The results showed significant improvements in symptom burden; however, the present study found no statistically significant differences between the intervention and control groups in anxiety, depression, or overall psychological distress following the 6-week nursing-led predictive symptom management program. The findings suggest that targeting only the physical symptoms might be insufficient to yield detectable changes in psychosocial well-being in a relatively short intervention period. Psychological distress in patients receiving oncology palliative care is a multidimensional experience that is influenced not only by physical symptoms but also by emotional, existential, and social challenges, from the perspective of the researchers.
Patients with advanced cancer frequently experience uncertainty about disease progression, fear of death, anticipatory grief, disruption of family roles, and concern about loss of independence, all of which may continue despite good symptom control. Previous evidence suggests that patients with cancer, especially those receiving palliative care, often experience anxiety, depression, and adjustment difficulties, and that psychological distress is often only modestly related to the severity of physical symptoms (Mitchell et al. Reference Mitchell, Chan and Bhatti2011).
Recent evidence also supports the high prevalence of psychological distress in patients with advanced cancer, and highlights the multiple interacting factors that shape it, such as disease progression, fear of death, uncertainty, symptom burden, and psychosocial vulnerabilities. A recent meta-analysis reported a significant prevalence of depression among patients with advanced cancer receiving palliative care, indicating the ongoing psychological burden experienced by this population (Deng et al. Reference Deng, Li and Xu2026). In addition, the available evidence emphasizes the need for specific psychosocial interventions for cancer-related distress, as psychological symptoms may not sufficiently improve with symptom-focused care alone (Schiess et al. Reference Schiess, Song and Schädelin2026).
Likewise, symptom burden and emotional suffering may take partially independent paths, underscoring that effective symptom management does not necessarily lead to immediate psychological recovery. Emerging evidence indicates that the combination of palliative care with treatment for patients with advanced cancer results in improvements in quality of life (Hui et al. Reference Hui, Dev and Bruera2015), yet the impact on anxiety and depression is often modest, emphasizing the complex nature of psychological distress and the importance of dedicated psychosocial interventions and symptom-focused care (Hui et al. Reference Hui, Dev and Bruera2015; Bader et al. Reference Bader, Farraj and Yamin2025).
One possible explanation for the lack of major improvements in psychological outcomes is that the emotional adaptation of patients with advanced cancer takes more intensive and longer psychosocial interventions than those offered in the current 6-week program. The intervention involved supportive communication, patient education, symptom monitoring, and tailored nursing care. Structured psychological interventions such as cognitive behavioral therapy, meaning-centered psychotherapy, dignity therapy, mindfulness-based interventions, or caregiver-focused support were not included. Coping strategies, resilience, illness uncertainty, social relationships, spiritual concerns, and perceptions of meaning and identity significantly influence psychological distress in patients with advanced cancer.
Thus, anxiety and depression may persist even if symptom severity is reduced. This interpretation is in keeping with evidence that psychological distress in advanced cancer follows a complex trajectory and is affected by multiple factors beyond the physical symptom burden, including uncertainty, fear of disease progression, existential concerns, coping capacity, and social support. In the case of integrated palliative care interventions, the improvements in symptom control and quality of life were not always associated with immediate improvements in anxiety and depression. This suggests that emotional outcomes may require longer follow-up and targeted psychosocial approaches (Grassi et al. Reference Grassi, Spiegel and Riba2017).
Moreover, there is evidence in meaning-centered psychotherapy that interventions aimed at existential suffering, personal meaning, and emotional adaptation can significantly improve psychological and spiritual well-being in patients with advanced cancer (Breitbart et al. Reference Breitbart, Rosenfeld and Gibson2010, Reference Breitbart, Pessin and Rosenfeld2018). In addition, recent systematic reviews suggest the inclusion of psychosocial interventions, noting that methods addressing distress, coping, and emotional adjustment provide added benefits beyond palliative care focused only on symptoms (Schiess et al. Reference Schiess, Song and Schädelin2026).
The substantial decrease in symptom burden experienced by the intervention group, though there were no statistically significant improvements in anxiety and depression, might be an important initial step towards later psychological adjustment and better quality of life. The researchers suggest that good symptom management may help reduce immediate physical suffering, improve patients’ sense of control, support communication with healthcare providers and family members, and create opportunities for improved coping and emotional adjustment over time.
A reduction in physical symptoms that in turn results in a reduction in immediate distress and subsequently results in improved coping and emotional adaptation, and the potential for improved psychological well-being and quality of life. This sequence is in keeping with the principles of holistic palliative care9 and Symptom Management Theory10 that recognizes a dynamic interaction between the experience of symptoms, individual responses, and health outcomes. Previous research has shown that treatments that target existential concerns, dignity, meaning, and psychosocial support can extend symptom-focused care to offer additional benefits for emotional well-being in populations with advanced cancer (Chochinov et al. Reference Chochinov, Kristjanson and Breitbart2011; Breitbart et al. Reference Breitbart, Pessin and Rosenfeld2018). Thus, future nursing-led predictive symptom management programs should incorporate routine distress screening, psychological counseling, coping enhancement strategies, family communication support, mindfulness-based approaches, and referral pathways for specialized psychosocial care to achieve more comprehensive improvements in palliative care outcomes.
The results of this study showed that the nursing-led predictive symptom management program had a significant impact on the overall symptom burden of oncology palliative care patients. The total ESAS-r score was significantly lower in the intervention group than in the control group (34.04 ± 8.86 vs. 41.51 ± 8.48; p < 0.001) with a large effect size (Cohen’s d = 0.86), indicating a clinically meaningful decrease in symptom distress. These findings underscore the importance of proactive nursing interventions with systematic symptom assessment, personalized symptom management, patient education, and ongoing monitoring. Symptom burden is a key driver of suffering and functional impairment in oncology palliative care, and the relief of multiple concurrent symptoms is an important component of high-quality palliative nursing care.
The findings are consistent with previous evidence that nurse-led palliative care interventions can improve symptom control through early identification of symptom changes, timely supportive interventions, and improved coordination of care. Early landmark studies (Bakitas et al. Reference Bakitas, Lyons and Hegel2009; Temel et al. Reference Temel, Greer and Muzikansky2010) have demonstrated that structured early palliative care models improve patient-reported outcomes by proactively addressing symptoms rather than reacting after deterioration. More recent research has further supported this approach by demonstrating that nurse-led palliative interventions have been associated with reduced symptom distress, enhanced patient empowerment, and improved continuity of care (Li et al. Reference Li, Hu and Zhou2024; Alghamdi et al. Reference Alghamdi, Alreshidi and Algarni2025; Al-Ghabeesh et al. Reference Al-Ghabeesh, Masalha and Thachuthara2026). The current findings extend this evidence by showing that integrating predictive symptom monitoring into routine nursing practice may be an effective approach to improve symptom outcomes over a relatively short intervention period.
Among individual symptoms, pain was significantly reduced in the intervention group with a moderate effect size (Cohen’s d = 0.50). This finding suggests the important role of nursing-led pain assessment, patient education, support for medication adherence and early identification of uncontrolled symptoms. Pain is one of the most common and distressing symptoms experienced by patients with advanced cancer and frequently interferes with sleep, mood, mobility and quality of life. This improvement is consistent with recent evidence that nurse-led palliative care programs are associated with clinically meaningful reductions in cancer-related pain.
In a meta-analysis, Phetlerthirunkul et al. (Reference Phetlerthirunkul, Tsianakas and Ayis2026) demonstrated that nurse-led palliative interventions had moderate improvements in pain outcomes by providing structured symptom assessment, patient education, and multidisciplinary collaboration. Similarly, Singh et al. (Reference Singh, Virdun and Rattray2025) noted that nurse-led needs assessments and individualized interventions are beneficial for reducing symptom burden and improving quality of life, with the extent of benefit varying depending on the intensity of interventions, follow-up periods, and patient characteristics.
The overall reduction in total symptom burden may also be due to the improvement in pain symptoms. In advanced cancer, symptoms often occur together in related clusters rather than as isolated problems. Pain may be related to fatigue, emotional distress, sleep disturbance and decreased participation in daily activities. Thus, effective pain control may have secondary benefits in terms of reducing the overall symptom experience and enhancing patients’ ability to engage in self-care and coping behaviors. Similarly, previous studies have suggested that clusters of symptoms should be managed comprehensively rather than focusing on single symptoms independently (Abdel-Aziz et al. Reference Abdel-Aziz, Zaghamir and Ibrahim2025; Büttcher et al. Reference Büttcher, Müller and Vetter2025).
Although individual symptoms such as fatigue, nausea, and appetite disturbance failed to show statistically significant differences between groups, the direction of the observed changes points to possible clinical benefits, which could require longer follow-up periods to attain statistical significance. Symptom responses in oncology palliative care are multifactorial, including disease course, treatment effects, nutritional status, psychological distress, and individual coping capacity. Thus, the rate of improvement of specific symptoms may differ depending on the underlying mechanisms leading to each symptom. Similar findings have been reported in recent systematic reviews, noting that while individual symptoms respond variably, there are significant overall improvements in symptom burden (Singh et al. Reference Singh, Virdun and Rattray2025; Shah et al. Reference Shah, Aalam and Parveen2025).
Fatigue is a particularly complex symptom, being influenced by biological, psychological, and social factors. Cancer-related fatigue is associated with inflammation, anemia, toxicity of treatment, sleep disturbance, emotional distress, and reduced physical activity. While the current study did not show a significant improvement in fatigue, the borderline difference in QoL fatigue scores (p = 0.053) suggests that the intervention might have affected experiences related to fatigue, but not to a statistically significant extent within 6 weeks. Evidence suggests that fatigue management often requires multimodal interventions over longer time periods that incorporate activity management, energy conservation strategies, nutritional support, psychological interventions, and symptom control (Motiwala et al. Reference Motiwala, Misra and Akbar2025).
Likewise, anxiety as an ESAS symptom did not achieve statistical significance but showed a favorable trend. This is important because anxiety related to symptoms may respond more quickly to supportive nursing communication and reassurance than the more global psychological disorders measured by HADS. This distinction between symptom-level anxiety and clinically significant psychological distress illustrates the complexity of emotional outcomes in palliative care. While monitoring symptoms might ease acute distress associated with uncontrolled symptoms, more profound psychological problems of prognosis, mortality, and existential uncertainty may require specialized intervention and a longer therapeutic process.
Findings of the association between symptom change and psychological outcomes in this study lend support to a sequential model of palliative care response. Physical symptoms are often immediate sources of distress and may be more amenable to structured nursing interventions. Reduced symptom severity can give patients more psychological resources to process emotional concerns, adapt to illness-related changes, and participate in meaningful activities. Therefore, the absence of immediate improvement in psychological outcomes should not undermine the importance of symptom reduction, as symptom control may be a prerequisite for subsequent emotional and quality of life improvements.
The intervention group had slightly higher scores in several functioning domains of the EORTC QLQ-C30 (physical, role, emotional, and cognitive functioning), but these differences were not statistically significant (p > 0.05). Likewise, there were no significant differences in global quality of life scores and ECOG performance status after the 6-week intervention. These findings suggest that although the nursing-led predictive symptom management program was effective in reducing symptom burden, improvements in broader quality-of-life outcomes may require a longer period of intervention and ongoing supportive care.
Among patients receiving oncology palliative care, quality of life is a complicated and multidimensional result dependent on physical symptoms, psychological distress, functional limitations, social relationships, treatment burden, and existential concerns. QoL, unlike symptom severity, which may improve in a relatively short time after specific nursing interventions, reflects cumulative changes across multiple domains of the patients’ lives. Therefore, the lack of a statistically significant improvement in QoL after 6 weeks may be expected, especially in patients with advanced cancer who are facing ongoing disease-related challenges. Earlier evidence indicates that significant improvements of QoL after palliative interventions are often gradually achieved over several months rather than a short follow-up period (Li et al. Reference Li, Hu and Zhou2024; Umarani et al. Reference Umarani, Magesh and Gopal2025).
The current results are consistent with previous studies showing that nurse-led mobile health interventions significantly improved QoL outcomes (Standardized Mean Difference (SMD) = 0.49, 95% Confidence Interval (CI) [0.17, 0.81]), but emphasized the importance of sustained patient participation and continuous follow-up (Zhang et al. Reference Zhang, Hong and Chen2025). In addition, results from early palliative care studies, including Zimmermann et al. (Reference Zimmermann, Swami and Krzyzanowska2014) and Umarani et al. (Reference Umarani, Magesh and Gopal2025), indicated that QoL improvements can be gradual with ongoing support for symptom management, psychosocial care, and coping and adaptation assistance.
The failure to demonstrate meaningful improvements in QoL despite reductions in symptom burden may also be reflective of the advanced illness trajectory of the study population. Oncology palliative care patients often have irreversible disease-related changes, treatment-related toxicity, and progressive functional limitations that may restrict rapid improvement in daily functioning. In that case, the preservation of stability may itself be a clinically relevant result. Maintaining QoL and functional status, in a time of progressive disease, can demonstrate that the intervention was able to alleviate extra suffering and help the patient adapt.
This interpretation is also supported by the findings on ECOG performance status. At Week 6, no statistically significant difference between groups was found (p = 0.963), indicating that functional ability was stable throughout the intervention period. Functional status in advanced cancer is strongly influenced by tumor burden, cachexia, treatment toxicity, and disease progression, which are often refractory to rapid improvement. Previous studies have shown that ECOG scores tend to be stable and not improve in patients with advanced disease, especially those with moderate functional impairment (Muhandiramge et al. Reference Muhandiramge, Orchard and Warner2022; Chernet et al. Reference Chernet, Desai and Rajendran2024). Thus, functional stability in the face of progressive illness may be an important achievement of palliative interventions.
These results are consistent with evidence from comprehensive models of supportive care. Kalsi et al. (Reference Kalsi, Babic-Illman and Ross2015) demonstrated that structured assessments and symptom management strategies can help preserve function and reduce treatment-related complications in vulnerable cancer populations. Similarly, Tang et al. (Reference Tang, He and Pang2025) found that electronic patient-reported outcome monitoring maintained physical functioning in patients with advanced cancer despite the lack of measurable improvement in performance status. Taken together, these results suggest that the success of palliative care should be judged not only by improvement scores but also by the prevention of decline, the preservation of independence, and the improvement of comfort.
The current study also investigated whether routine laboratory indicators could be useful in predicting and monitoring the symptom burden in oncology palliative care patients. Hemoglobin levels were significantly higher in the intervention group compared to the control group during Weeks 4–6, with improvements also noted in sodium levels at Weeks 5 and 6 and calcium levels at Week 4. However, consistent significant group differences were not observed for most laboratory parameters, including CRP, WBC count, potassium, and albumin. The improvement in hemoglobin levels seen may be of clinical relevance as anemia is a common complication in patients with advanced cancer and is associated with fatigue, weakness, reduced physical function, decreased activity tolerance, and worse quality of life (Aapro et al. Reference Aapro, Beguin and Bokemeyer2018).
Fatigue outcomes were not significantly improved in the present study, but improved hemoglobin levels may be an early physiological response that may contribute to subsequent improvements in energy, functional capacity, and overall well-being. However, symptom experiences are influenced by complex interactions among biological, psychological and social factors, and improvements in laboratory parameters may not immediately translate into measurable patient-reported benefits (Hui et al. Reference Hui, Hannon and Zimmermann2018).
Likewise, the alterations in sodium and calcium levels could be due to better clinical monitoring and early detection of possible physiological disturbances. Electrolyte abnormalities are relatively common in patients with advanced cancer and may contribute to fatigue, weakness, cognitive changes, and increased symptom distress (Rosner and Dalkin Reference Rosner and Dalkin2014). This suggests that the incorporation of laboratory monitoring in nursing-led symptom management may provide additional clinical information to support early identification of patients at risk of symptom deterioration, and timely supportive interventions. However, the small magnitudes of associations observed in the present study suggest that laboratory markers should be regarded as complementary clinical information rather than independent predictors of symptom experience. Modern palliative care principles suggest that the evaluation of symptom burden should be based on a multidimensional model that combines physiological indexes with self-reported symptoms, psychological status, functional status and social factors (Grassi et al. Reference Grassi, Spiegel and Riba2017; Hui et al. Reference Hui, Hannon and Zimmermann2018).
Correlation analysis showed a significant but weak positive correlation between CRP levels and total ESAS-r scores (r = 0.180; p = 0.028), indicating a modest association between higher inflammatory activity and higher symptom burden. This is in line with earlier evidence suggesting that systemic inflammation plays a role in the pathogenesis of cancer-related symptoms like fatigue, pain, anorexia, and general distress. Activation of inflammatory pathways through cytokines and metabolic changes may affect not only physical symptoms but also functional decline in advanced cancer populations (Amano et al. Reference Amano, Maeda and Morita2017; Carroll et al. Reference Carroll, Nakamura and Small2023).
However, the lack of strong correlations between most of the laboratory parameters and severity of symptoms highlights the multidimensional nature of symptom burden in palliative care. However, patient-reported symptoms are also influenced by biological abnormalities, as well as psychological distress, coping strategies, social support, treatment experience and personal perception of illness. Laboratory data should therefore be used as a complement to, not a replacement of, comprehensive symptom assessment tools such as the ESAS-r and clinical nursing judgment. This multidimensional approach is consistent with current models of symptom management that view symptoms as dynamic experiences influenced by physiological, psychological, and contextual factors rather than as isolated biological processes (Dodd et al. Reference Dodd, Janson and Facione2001; Hui et al. Reference Hui, Dev and Bruera2015).
From a clinical perspective, the findings support the integration of objective clinical indicators with patient-reported outcomes to improve proactive symptom management. Nurses are uniquely prepared to integrate laboratory interpretation with continuous symptom assessment, therapeutic communication, patient education, and individualized care planning. Such integration could support earlier recognition of clinical deterioration, better symptom control, and individualized delivery of palliative care. Previous evidence has demonstrated that effective palliative nursing practice requires integrating systematic symptom assessment with holistic approaches to meet physical, emotional, and psychosocial needs across the illness trajectory (Ferrell et al. Reference Ferrell, Temel and Temin2017).
Limitations
Several limitations should be considered when interpreting the findings of this study. First, the intervention period was relatively short (6 weeks), which may have limited the ability to detect significant changes in quality of life, psychological distress, and functional status. These outcomes may require longer periods to demonstrate measurable improvements, particularly among patients receiving palliative care.
Second, the study was conducted in only 1 governmental hospital, which may limit the generalizability of the findings to other healthcare settings, regions, and patient populations. Third, laboratory markers were only weakly associated with patient-reported symptom burden, suggesting that symptom experiences and psychological outcomes may be influenced by multiple interacting factors, including disease stage, comorbidities, treatment-related effects, and social support.
Fourth, the study did not assess important psychosocial variables that may mediate the relationship between symptom management interventions and psychological outcomes, including coping strategies, resilience, social support, spiritual well-being, caregiver burden, and illness uncertainty.
Finally, the study was not prospectively registered in a clinical trial registry, which should be considered when assessing the methodological rigor of the intervention. Future studies should employ multicenter designs with longer follow-up periods, prospective registration, and comprehensive assessment of clinical and psychosocial determinants. Such approaches would provide a more holistic understanding of symptom management outcomes among patients receiving oncology palliative care.
Recommendations
Future nursing-led interventions should move beyond symptom control to multidimensional supportive care approaches addressing the complex physical, psychological, social, and existential needs of oncology patients receiving palliative care. Interventions combining psychological counseling, meaning-centered care, dignity therapy, mindfulness-based approaches, coping enhancement strategies, family support, and resilience training should be explored to improve psychological adaptation and quality of life. We recommend multicenter Randomized Controlled Trial (RCTs) with larger sample sizes and longer follow-up duration to assess the long-term effects of integrated symptom and psychosocial management programs. Future research should also investigate the mediating role of psychosocial factors such as coping, social support, carer burden, and illness uncertainty with regard to symptom perception and psychological outcomes. More sophisticated analytic approaches, such as multivariate modeling, may also help elucidate the complex relationships between biological indicators, symptom burden, psychosocial factors and functional outcomes in oncology palliative care populations.
Nursing implications
Oncology nurses are central to the provision of holistic palliative care that encompasses not only physical symptom management but also psychological, emotional, and social support. Routine psychosocial assessment and systematic screening for distress (including anxiety and depression, emotional suffering, uncertainty, and unmet supportive care needs) should be incorporated early in clinical practice. Nurses should possess effective communication skills, counseling approaches, and therapeutic strategies to facilitate emotional expression, support coping, and promote patient-centered decision-making. Nurse-led symptom management programs should include a comprehensive symptom assessment, psychosocial assessment, carer support, and timely referral to psychological, social work, spiritual care, and supportive services as appropriate. Enhanced nurse competencies in predictive symptom assessment, communication, and psychosocial care can improve early intervention, strengthen continuity of care, and promote a more holistic approach to supporting patients and families across the palliative care trajectory.
Conclusion
The nursing-led predictive symptom management program was effective in reducing overall symptom burden, especially pain, and had the potential benefits to support individualized symptom control for patients receiving oncology palliative care. However, quality of life, psychological distress, and functional status did not significantly improve during the 6-week intervention period, indicating that short-term, symptom-focused interventions may not be sufficient to impact complex psychosocial outcomes. The results underline the importance of a comprehensive nursing model that combines proactive symptom management with psychological assessment, emotional support, and family-based care. Although laboratory indicators may help in the anticipatory monitoring of symptoms, the importance of addressing the patients’ needs for psychological and supportive care in advanced cancer care to foster adaptation, comfort, and quality of life remains paramount. Future models of palliative nursing practice should integrate clinical monitoring with comprehensive psychosocial interventions in order to provide truly patient-centered care.
Data availability statement
The original contributions presented in this study are available within the manuscript. For additional inquiries, please contact the corresponding author.
Funding
The authors extend their appreciation to Prince Sattam Bin Abdulaziz University for funding this research work through the project number (PSAU/2025/03/38525).
Competing interests
The authors declare that they have no competing interests.
Ethical approval
The study was conducted according to the principles of the Declaration of Helsinki and the relevant local regulations on human research. Ethical approval was obtained from the Institutional Review Board (IRB) of Prince Sattam Bin Abdulaziz University (SCBR-267/2024). Patients were assured of voluntary participation, confidentiality, and the right to withdraw at any time without affecting their care. All data were stripped of personal identifiers and stored securely to protect privacy. The intervention carried little risk, while the control group participants received usual palliative care and did not have treatment withheld. All procedures were performed in accordance with ethical standards for research involving vulnerable populations, including patients receiving oncology palliative care.
Ethics and consents
Written informed consent was obtained from all the participants prior to enrolment.




 Open access

