Introduction
Despite recent successes in reducing overall tobacco consumption in the United States, approximately 20.6% of the US population continues to smoke cigarettes (Centers for Disease Control and Prevention [CDC], 2011). In the US, up to 33% of smokers smoke nondaily (Tindle and Shiffman, Reference Tindle and Shiffman2011) (i.e., between 1 and 29 days out of every 30 (American College Health Association [ACHA], 2009)). Nondaily smoking is particularly common among young adults, with 19.9% reporting smoking on a nondaily basis (Wortley et al., Reference Wortley, Husten, Trosclair, Chrismon and Pederson2003). Nondaily smoking had been considered to be a transitional phase to heavier smoking (White et al., Reference White, Bray, Fleming and Catalano2009) or from daily smoking to quitting (Evans et al., Reference Evans, Gilpin, Pierce, Burns and Al1992, Okuyemi et al., Reference Okuyemi, Harris, Scheibmeir, Choi, Powell and Ahluwalia2002, Zhu et al., Reference Zhu, Sun, Hawkins, Pierce and Cummins2003); however, nondaily smoking may be a chronic pattern of cigarette use (Hassmiller et al., Reference Hassmiller, Warner, Mendez, Levy and Romano2003, Shiffman, Reference Shiffman2009, Hennrikus et al., Reference Hennrikus, Jeffery and Lando1996).
Research has documented significant risks of smoking-related morbidity and mortality related to nondaily smoking (Luoto et al., Reference Luoto, Uutela and Puska2000, Jimenez-Ruiz et al., Reference Jimenez-Ruiz, Kunze and Fagerstrom1998). In fact, light and nondaily smoking carries nearly the same risk for cardiovascular disease as daily smoking (Schane et al., Reference Schane, Ling and Glantz2010, Bjartveit and Tverdal, Reference Bjartveit and Tverdal2005, Pope et al., Reference Pope, Burnett, Krewski, Jerrett, Shi, Calle and Thun2009). However, nondaily smokers tend to discount personal health consequences (Moran et al., Reference Moran, Wechsler and Rigotti2004, Rollins et al., Reference Rollins, Malmstadt Schumacher and Ling2002, Luoto et al., Reference Luoto, Uutela and Puska2000, Woolcock et al., Reference Woolcock, Peat, Leeder and Blackburn1984), which may result in lower motivation to quit smoking.
Moreover, there is great variability in terms of whether nondaily smokers even believe that the notion of ‘quitting smoking’ is even relevant to them (Berg et al., Reference Berg, Parelkar, Lessard, Escoffery, Kegler, Sterling and Ahluwalia2010), as a majority of nondaily smokers do not identify as smokers (Berg et al., Reference Berg, Lust, Sanem, Kirch, Rudie, Ehlinger and An2009, Brown et al., Reference Brown, Carpenter and Sutfin2011) and tend not to perceive themselves as addicted (Gilpin et al., Reference Gilpin, Cavin and Pierce1997). In fact, nondaily smokers may engage in several cognitive tactics to consolidate their self-identities as a nonsmoker despite engaging in the behaviour of smoking (Hoek et al., Reference Hoek, Maubach, Stevenson, Gendall and Edwards2012, Brown et al., Reference Brown, Carpenter and Sutfin2011). Unfortunately, denial of being a smoker has been associated with a decreased likelihood of recent quit attempts (Berg et al., Reference Berg, Lust, Sanem, Kirch, Rudie, Ehlinger and An2009). Interestingly, previous research suggests that nondaily smokers (versus daily smokers) are more likely to be ready to quit in the next month and more confident that they can quit (Gilpin et al., Reference Gilpin, Cavin and Pierce1997), but ultimately are unsuccessful in their quit attempts (DiFranza et al., Reference DiFranza, Savageau, Fletcher, O'Loughlin, Pbert, Ockene and Wellman2007, Savageau et al., Reference Savageau, Mowery and DiFranza2009). While some nondaily smokers can abstain from smoking for extended periods of time without withdrawal (Rubinstein et al., Reference Rubinstein, Benowitz, Auerback and Moscicki2009), others may experience cravings and other signs of physiological addiction (DiFranza and Wellman, Reference DiFranza and Wellman2005, Rubinstein et al., Reference Rubinstein, Benowitz, Auerback and Moscicki2009, DiFranza, Reference DiFranza2011, DiFranza et al., Reference DiFranza, Savageau, Fletcher, Ockene, Rigotti, McNeill and Wood2002, Ursprung and DiFranza, Reference Ursprung and DiFranza2010).
These findings highlight the distinct psychological characteristics surrounding nondaily smoking. Unfortunately, motivation to quit among nondaily smokers has been difficult to assess for a number of reasons. Our traditional measures of cessation motivation have typically been designed for regular or heavy smokers. For example, the Treatment Self-Regulation Questionnaire (TSRQ) (Ryan and Connell, Reference Ryan and Connell1989) is a measure that has been applied to several health behaviours, including smoking, and assesses autonomous motivation, controlled motivation, and amotivation. Examples of items include: ‘Because I personally believe it is the best thing for my health’ (autonomous motivation), ‘Because I would feel guilty or ashamed of myself if I smoked’ or ‘Because I want others to see I can do it’ (controlled motivation), and ‘I really don't think about stopping smoking’ (amotivation). While some of these factors may be relevant to nondaily smokers in the young adult population, this scale was not intentionally developed for smoking nor was it specifically designed to evaluate motivational factors related to nondaily smoking cessation in young adults. Thus, research is needed to develop measures drawn from the literature specifically focusing on this group and that demonstrate both face validity and sound psychometric characteristics.
Previous qualitative research of young adult college students smoking an average of 13 days in the past 30 (Berg et al., Reference Berg, Parelkar, Lessard, Escoffery, Kegler, Sterling and Ahluwalia2010) identified several factors related to motivation to quit among nondaily smokers. First, the expense of smoking or the desire to save money motivated participants to quit smoking. Second, several participants reported concern about the impact of smoking on their health, both in the short term and long term. Third, while other research has documented that young adults may assign a lower level of social stigma to smoking (Hughes et al., Reference Hughes, Cohen and Callas2009), this research indicated that social factors served as motivators for quitting smoking, with disapproval of their smoking among their family, friends, partners, or roommates being prominent concerns. Many also stated that stigma associated with being a smoker from the general population was a deterrent to continuing to smoke. Several participants indicated that the smell, the bad taste, and the impact of smoking on appearance (e.g., yellow fingers and wrinkles) were motivators for cessation, as they both increased the level of social stigma they experienced and impacted their self-concept. Finally, many reported that preventing addiction to cigarettes was a motivator for cessation, which is unique to this smoker population (Berg et al., Reference Berg, Parelkar, Lessard, Escoffery, Kegler, Sterling and Ahluwalia2010).
Given this important public health issue, it is important to develop measures that assess reasons or motivation for cessation among nondaily smokers. Thus, the present study aims to develop a measure of motivation to quit among nondaily smokers in the young adult population. Specifically, we developed a scale assessing motivation for nondaily smoking cessation, and examined its reliability, factor structure, and concurrent validity. We hypothesised that measures of motivation should be related to other measures of motivation for cessation, confidence in ability to quit, prior cessation attempts, level of smoking, future intentions to quit smoking, smoker self-identity, and perceived harm of smoking.
Methods
Survey Participants and Procedures
In autumn 2010, students at six colleges in the Southeastern US were recruited to complete an online survey (for more details, see Berg et al., Reference Berg, Nehl, Sterling, Buchanan, Narula, Sutfin and Ahluwalia2011). Then in fall 2011, we randomly selected 2,000 participants of the 2010 survey and recruited them to participate in a follow-up survey. Students received an e-mail containing a link to the consent form with the alternative of opting out. Students who consented to participate were directed to the online survey. To encourage participation, students received up to three e-mail invitations to participate. As an incentive for participation, all students who completed the survey received a $10 gift card. Of the 2,000 students who received the invitation to participate, 718 (35.9%) returned a completed survey. The current analyses focused on the 105 participants who completed this 2011 survey, reported nondaily smoking (i.e., smoking between 1 and 29 days of the past 30 days), and provided complete data on their smoking behaviours. This sample size is deemed appropriate for the current analyses, as indicated by literature suggesting that the sample size needed for a factor analyses is the greater of the following: 1) five times the number of items or 2) 100 (Hatcher, Reference Hatcher1994; Kline, Reference Kline1979; Gorsuch, Reference Gorsuch1983). The Emory University Institutional Review Board approved this study, IRB# 00030631.
Measures
Demographic Characteristics
We assessed students’ age, gender, race/ethnicity, highest parental educational attainment (as a proxy of socioeconomic status), and type of school attended (two-year vs. four-year).
Nondaily Smoking Cessation Motivation Questionnaire
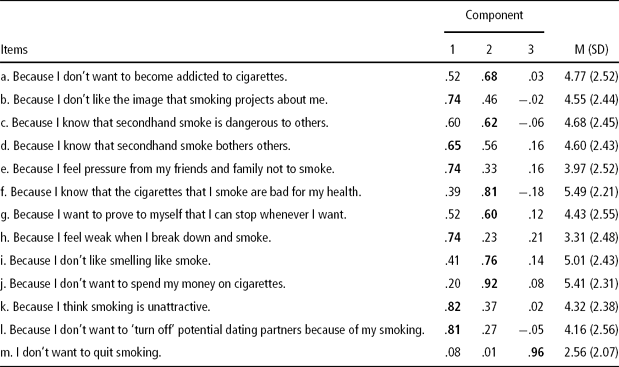
This scale was developed using results from our prior formative research (Berg et al., Reference Berg, Parelkar, Lessard, Escoffery, Kegler, Sterling and Ahluwalia2010) and was theoretically based on Self-Determination Theory (Deci and Ryan, Reference Deci and Ryan2002). Specifically, we examined dimensions of intrinsic and extrinsic motivation and how they related to autonomy and competence in the process of cessation. We focused on factors such as attitudes about the nondaily smoking (e.g., expense, impact on health), the role of social norms (e.g., concern about approval or disapproval from the social network vs. personal concern for the health of others), and concerns about personal volition related to the ability to smoke or quit smoking, and how the relevance and valence of these factors impacted motivation to quit smoking. The items were created by the research team and were screened for clarity and face validity by three experts in tobacco research. The Nondaily Smoking Cessation Motivation Questionnaire (NSCM) consists of 13 items. Participants were instructed to ‘On a scale of 1 to 7, indicate the extent to which you agree with the following statements’ with anchors of 1 = Not at all true, 4 = Somewhat true, and 7 = Very true. The stem leading into each statement was ‘I want to quit smoking because. . .’ Each item is listed in Table 2. The NSCM is scored by summing the Likert responses to all items, with the exception of item 10 (‘I don't want to quit smoking’), which is reverse scored, resulting in a total score. The possible range of scores was 13 to 91, with higher scores indicating greater endorsement of reasons for quitting overall.
Smoking Behaviours
We asked, ‘In the past 30 days, on how many days did you smoke a cigarette (even a puff)?’ (ACHA, 2008; CDC, 1997). Using the ACHA and the Substance Abuse and Mental Health Association (ACHA, 2009; Office of Applied Studies, 2006) definitions, we categorised students who reported smoking from 1 to 29 days of the past 30 days as nondaily smokers. They were also asked, ‘Have you ever smoked cigarettes daily, that is, at least one cigarette every day for 30 days?’ Those indicating that they had were classified as former daily smokers.
Confidence and Motivation to Quit Smoking
Participants were asked, ‘On a scale of 0 to 10 with 0 being “not at all confident” and 10 being “extremely confident”, assuming you want to, how confident are you that you could quit smoking cigarettes starting this week and continuing for at least one month?’ and ‘On a scale of 0 to 10 with 0 being “I don't want to at all” and 10 being “I really want to”, how much do you want to quit smoking cigarettes?’ (Biener and Abrams, Reference Biener and Abrams1991; Maibach et al., Reference Maibach, Maxfield, Ladin and Slater1996).
Treatment Self-Regulation Questionnaire
Motivation to quit was measured using the 15-item Treatment Self-Regulation Questionnaire (TSRQ) (Ryan and Connell, Reference Ryan and Connell1989). The TSRQ contains items that measure autonomous motivation (six items), controlled motivation (six items), and amotivation (three items). Participants were asked to indicate the extent to which several motivators for change were relevant to them. Examples of items include: ‘Because I personally believe it is the best thing for my health’ (autonomous motivation), ‘Because I would feel guilty or ashamed of myself if I smoked’ (controlled motivation), and ‘I really don't think about stopping smoking’ (amotivation). Responses ranged from ‘not at all true’ to ‘very true’ and were on a 7-point scale. Scores ranged from 15 to 105, with higher scores indicating greater motivation. Construct validity was established for the scale (Ryan and Connell, Reference Ryan and Connell1989). In the present study, Cronbach's alphas for the Autonomous motivation, Controlled motivation, and Amotivation subscales were 0.88, 0.86, and 0.50, respectively.
Self-Efficacy Questionnaire
Self-efficacy was measured using the Smoking Self-Efficacy Questionnaire (SEQ-12) (Etter et al., Reference Etter, Bergman, Humair and Perneger2000). The SEQ-12 is a 12-item scale that measures confidence in one's ability to refrain from smoking in certain situations. The scale is two-dimensional with six items that measure abstinence self-efficacy for internal stimuli (e.g., ‘When I feel nervous”) and six items that measure abstinence self-efficacy for external stimuli (e.g., “When having a drink with friends”). Responses ranged from ‘not at all sure’ to ‘absolutely sure’ and were on a 5-point Likert scale. SEQ-12 scores ranged from 12 to 60 with higher scores indicating greater self-efficacy. Reliability in test-retest procedures was established for the scale along with content validity, construct validity, and predictive validity (Etter et al., Reference Etter, Bergman, Humair and Perneger2000). In the present study, Cronbach's alphas for the Intrinsic and Extrinsic subscales were 0.93 and 0.82, respectively.
Previous Quit Attempts
Participants were also asked, ‘During the past 12 months, how many times have you stopped smoking for one day or longer because you were trying to quit smoking?’ (California Department of Health and Human Services. Tobacco Control Section, 1999). This variable was dichotomised as having made at least one quit attempt in the past year versus not having made an attempt to quit.
Readiness to Quit
Readiness to quit was assessed by asking, ‘What best describes your intentions regarding quitting smoking?’ Response options were ‘never expect to quit,’ ‘may quit in the future, but not in the next 6 months,’ ‘will quit in the next 6 months,’ and ‘will quit in the next month’ (Prochaska and DiClemente, Reference Prochaska and DiClemente1984). For the present study, this variable was dichotomised as intending to quit in the next 30 days versus all other responses.
Social Smoking
To assess social smoking, participants were also asked, ‘In the past 30 days, did you smoke: mainly when you were with other people; mainly when you were alone; as often by yourself as with others; or not at all’ (Moran et al., Reference Moran, Wechsler and Rigotti2004). This variable was dichotomised as ‘social smoking’ (i.e., smoking mainly when with others) versus other responses.
Smoker Self-Concept
The extent to which participants maintained a self-identify of a smoker was assessed using the Smoker Self-Concept Scale (Shadel and Mermelstein, Reference Shadel and Mermelstein1996). Subjects were asked to rate the extent to which they agree with five items designed to assess the importance of being a smoker to their self-concept (ranging from 1 = strongly disagree to 10 = strongly agree). This scale has been shown to demonstrate reliability and validity (Shadel and Mermelstein, Reference Shadel and Mermelstein1996). In the present study, Cronbach's alpha for this scale was 0.92.
Perceived Harm
Participants were asked, ‘Do you believe there is any harm in having an occasional cigarette?’ with response options of ‘yes’ or ‘no’ (Minnesota Department of Health, 2008).
Data Analysis
Participant characteristics were summarised using descriptive statistics. Factor analyses were conducted to determine the underlying factor structure of the scale. In order to obtain internal consistency reliabilities for the scale and each subscale, we calculated Cronbach's alpha. As an additional measure of reliability, we also conducted a split-half reliability test. Subscale scores were examined in relation to sociodemographic, smoking-related, and psychosocial characteristics using correlations for continuous variables and t-tests for categorical variables. SPSS 19.0 was used for all data analyses. Statistical significance was set at α = .05 for all tests.
Results
Factor Analysis and Reliability
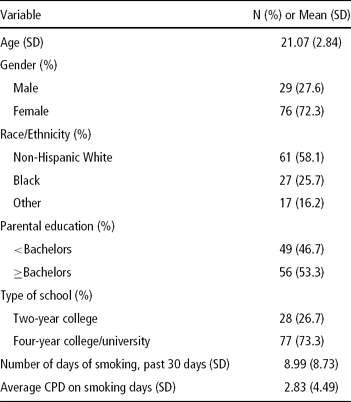
Participant characteristics of our study sample are included in Table 1. Factor analysis using principal components extraction with varimax rotation was applied to the 13 items of the Nondaily Smoking Cessation Motivation Questionnaire (NSCM). Following conservative guidelines for factor analysis detailed by Tabachnick and Fidell (Reference Tabachnick and Fidell1989), after the matrix was rotated, factors were retained whose eigenvalues were greater than 1.0 with factor loadings greater than .50. With the exception of one subscale, we also dictated that at least three items loaded onto a factor for it to be considered. Items included in the final scale, the factor loadings, and the means and standard deviations for each item are presented in Table 2.
Participant characteristics, N = 105

Nondaily Smoking Cessation Motivation Questionnaire factor analysis results
Note: Stem = ‘I want to quit smoking. . . .’
The average score on the NSCM was 56.95 (SD = 24.33). The NSCM yielded a Cronbach's alpha of 0.94. We tested the reliability of the scale using split-half reliability analysis, which indicated Cronbach's alphas of 0.70 and 0.67, with a correlation between forms of 0.57. The Spearman-Brown split-half coefficient was 0.73. Factor analysis of the items extracted three factors which accounted for 76.8% of the variance in scores. Eigenvalues and percent of variance accounted for by each component are as follows: Component 1, eigenvalue = 4.68, 36.0%; Component 2, eigenvalue = 4.23, 32.5%; and Component 3, eigenvalue = 1.08; 8.3%. All items had strong factor loadings. Component 1 was termed Controlled motivation (Cronbach's alpha = .92), Component 2 was termed Autonomous motivation (Cronbach's alpha = .93), and Component 3 was termed Amotivation (which consisted of only one item).
Concurrent Validity
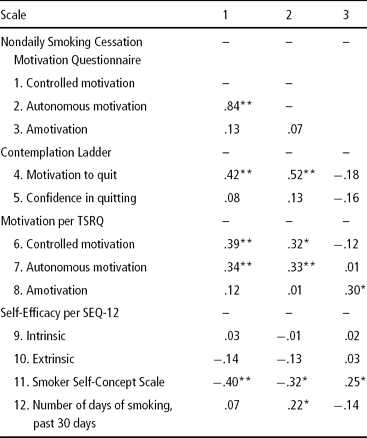
Table 3 presents correlations among the NSCM subscale scores and measures of Motivation and Confidence per the Contemplation Ladder, the subscales of the Treatment Self-Regulation Questionnaire, the subscales of the Self-Efficacy Questionnaire – 12 item, the Self-Identity Scale, and the number of days of smoking in the past 30 days. The NSCM – Controlled motivation subscale was positively associated with the NSCM – Autonomous motivation subscale, motivation per the contemplation ladder, the TSRQ – Autonomous motivation subscale, the TSRQ – Controlled motivation subscale, and negatively associated with the Self-Concept Scale. The NSCM – Autonomous motivation subscale was positively associated with motivation via the contemplation ladder, the TSRQ – Controlled motivation, and the TSRQ – Autonomous motivation subscale, and negatively with the Self-Concept Scale. The NSCM – Amotivation was positively association with the TSRQ – Autonomous motivation subscale, the Self-Concept Scale, and number of days smoked in the past 30 days. In addition, those reporting a quit attempt in the past year reported higher NSCM – Controlled Motivation (M = 28.11, SD = 10.87 vs. M = 22.88, SD = 13.17, p = .04) and higher NSCM – Autonomous Motivation (M = 34.22, SD = 8.36 vs. M = 27.05, SD = 13.86, p = .006). No differences were found in relation to readiness to quit, social smoker status, former daily smoker status, or perceived harm.
Correlations among Nondaily Smoking Cessation Motivation Questionnaire subscales and validated measures among young adult nondaily smokers
* Indicates p < .05.
** Indicates p < .01.
Notes: TSRQ = Treatment Self-Regulations Questionnaire; SEQ-12 = Self-Efficacy Questionnaire – 12 item.
Discussion
The current study is the first to develop and validate an instrument to assess factors related to motivation for cessation among young adult nondaily smokers. Results indicated high internal consistencies and factors that align with prior qualitative research (Berg et al., Reference Berg, Parelkar, Lessard, Escoffery, Kegler, Sterling and Ahluwalia2010). Interestingly, the subscales yielded through the creation of the newly developed Nondaily Smoking Cessation Motivation Questionnaire mirrored the factors present in the Treatment Self-Regulation Questionnaire. This is not surprising given our theoretical orientation (i.e., Self-Determination Theory). However, it is interesting that the items developed specifically for the young adult nondaily smoker population behaved similarly to items created to assess motivation for other health behaviour changes, and thus supports the robustness of this theoretical framework in describing motivational components related to health behaviour change. It is also important to note, however, that the development of this scale drew from the literature specifically focusing on young adult nondaily smokers and, thus, has face validity, which is critical in creating an instrument with high utility.
The NSCM – Controlled motivation subscale included items such as ‘Because I don't like the image that smoking projects about me,’ ‘Because I know that secondhand smoke bothers others,’ ‘Because I feel pressure from friends and family not to smoke,’ and ‘Because I feel weak when I break down and smoke,’ all of which are consequences of extrinsic motives. On the other hand, the NSCM – Autonomous motivation subscale included statements such as ‘Because I don't want to become addicted to cigarettes,’ ‘Because I know secondhand smoke is dangerous to others,’ ‘Because I don't want to spend my money on cigarettes,’ and ‘I don't like smelling like smoke,’ all of which are personally important motivators grounded intrinsically.
As hypothesised, the NSCM – Controlled motivation subscale and the NSCM – Autonomous motivation subscale were positively correlated with one another, and both were associated with other measures of motivation including the contemplation ladder, the TSRQ – Controlled motivation, and the TSRQ – Autonomous motivation. Interestingly, they were negatively correlated with the Smoker Self-Concept Scale. Prior research (Berg et al., Reference Berg, Lust, Sanem, Kirch, Rudie, Ehlinger and An2009) suggested that not identifying as a smoker was related to less likelihood of making a quit attempt. However, other research has also documented the lack of clarity involved in reporting quit attempts and cessation among nondaily smokers (Berg and Schauer, In press). This may have complicated earlier findings. These apparent contradictions related to how identifying as a smoker relates to motivation to quit and potential cessation may be related to measurement of identity as a smoker or to how nondaily smokers report motivation to quit smoking. The NSCM – Autonomous motivation subscale was positively associated with number of days of smoking in the past 30 days, which is a finding that warrants continued research to understand why nondaily smokers who smoke more frequently might have a greater personal stake in quitting. Perhaps their perceptions of personal risk due to greater smoking level account for this relationship.
As expected, the NSCM – Controlled and Autonomous motivation subscales were not correlated with measures of amotivation. It is interesting to note that not endorsing specific motives as personally relevant on these subscales was unrelated to reporting a lack of desire to quit per the NSCM – Amotivation subscale (or the TSRQ – Amotivation subscale). This is an important concept that was considered in scale development. We felt that the inclusion of this single item was critical in developing a scale that gave a more complete picture of motivation to quit among nondaily smokers. At a basic conceptual level, understanding which reasons are relevant for quitting smoking is different than asking if someone is motivated to quit smoking.
The NSCM – Amotivation was positively association with the TSRQ – Amotivation subscale, which in line with expectations. Interestingly, this subscale was also associated with the Self-Concept Scale. As stated earlier, this supports prior research documenting that those who identify as a smoker have been shown to be less likely to attempt to quit smoking (Berg et al., Reference Berg, Lust, Sanem, Kirch, Rudie, Ehlinger and An2009).
Finally, no measures of motivation per the newly developed NSCM were associated with any measure of confidence in quitting smoking. While we initially hypothesised that motivation would be associated with greater confidence in quitting, these findings demonstrate that motivation and confidence in quitting are distinct factors and provide evidence of discriminant validity among this population of young adult nondaily smokers.
Interestingly, other hypothesised relationships were also not demonstrated. No differences were found in relation to social smoker status, former daily smoker status, readiness to quit, or perceived harm. These null findings may reflect a number of phenomena previously documented. These issues may be related to our definitions of what a social smoker is or what young adult perceptions of how they identify themselves as smokers or social smokers (Berg et al., Reference Berg, Lust, Sanem, Kirch, Rudie, Ehlinger and An2009, Song and Ling, Reference Song and Ling2011). In addition, there is a great lack of clarity regarding how nondaily smokers conceptualise prior quit attempts and readiness to quit smoking among nondaily smokers (Berg and Schauer, In press, Berg et al., Under review). Finally, the fact that nondaily smokers tend to discount personal health consequences (Moran et al., Reference Berg, Schauer, Buchanan, Sterling, DeSisto, Pinsker and Ahluwalia2004, Rollins et al., Reference Rollins, Malmstadt Schumacher and Ling2002, Luoto et al., Reference Luoto, Uutela and Puska2000, Woolcock et al., Reference Woolcock, Peat, Leeder and Blackburn1984) suggests that, while perceived harm in the heavier smoker population may be a relevant motivational factor, it may be less relevant among nondaily smokers. Further research is needed to examine these counterintuitive findings.
Implications for Research and Practice
This study extends our ability to understand nondaily smokers in the young adult population and to appropriately assess factors related to motivation to quit smoking. In research, this scale could be investigated to determine if one's motivation to quit smoking predicts cessation or reduction in cigarette consumption. It might also help us to identify intervention targets specific to the nondaily smoker population. In the clinical setting, healthcare providers assisting young adults are faced with unique challenges in terms of identifying smokers, as nondaily smokers may not identify as smokers (Berg et al., Reference Berg, Lust, Sanem, Kirch, Rudie, Ehlinger and An2009, Levinson et al., Reference Levinson, Campo, Gascoigne, Jolly, Zakharyan and Tran2007). The concepts assessed within this scale may be helpful for practitioners to better discuss the topic of nondaily or low-level smoking with the young adult population.
Limitations
This study has some limitations. First, the survey sample was largely female and drawn from Southeast colleges. Despite the fact that this sample reflects the characteristics of these school populations and has good representation of White and Black racial backgrounds, it may not generalise to other college populations. Moreover, those with missing data that were excluded from this analysis did not differ in sociodemographic characteristics from the sample included in this analysis. Second, the survey response rate may seem low and might suggest responder bias. However, previous online research has yielded similar response rates (29‒32%) among the general population (Kaplowitz et al., Reference Kaplowitz, Hadlock and Levine2004) and a wide range of response rates (17‒52%) among college students (Crawford et al., Reference Crawford, McCabe and Kurotsuchi Inkelas2008). We are also unable to ascertain how many participants did not open the e-mail or had inactive email accounts, which impacts what the true ‘denominator’ for this response rate may have been. In addition, prior work has demonstrated that, despite lower response rates, internet surveys yield similar statistics regarding health behaviours compared to mail and phone surveys (An et al., Reference An, Hennrikus, Perry, Lein, Klatt, Farley and Ahluwalia2007). Also, we did not include additional items beyond the 13 items reported here. Thus, it is possible that other dimensions exist, but were not explored in this study. Also, our categorisation of nondaily smokers (i.e., smoking 1‒29 days in the past 30 days) may be a concern; however, less than 5% of our nondaily smoking sample smoked 25‒29 days of the past 30. In addition, we cannot ascertain the extent to which those nondaily smokers who completed the survey may have differed in important psychosocial or behavioural dimensions (e.g., motivation for cessation) from those who did not participate. Finally, the cross-sectional nature of this study limits the extent to which we can make causal attributions. Future research should examine the predictive validity of this finding in longitudinal studies examining smoking cessation motivation and its link to smoking cessation in this population.
Conclusions
The present study provided information about the development and validation of a scale designed to assess motivation to quit smoking among nondaily smokers within the young adult population. Given this emerging public health problem and the lack of validated measures to assess factors associated with nondaily smoking, this assessment may be critical in informing our intervention strategies and potentially for predicting cessation among young adult nondaily smokers.
Acknowledgements
We would like to thank our collaborators across the state of Georgia in developing and administering this survey.
Financial Support
This work was supported by the National Cancer Institute (1K07CA139114-01A1; PI: Berg) and the Georgia Cancer Coalition (PI: Berg).
Conflict of Interest
The authors declare no conflicts of interest.
Ethical Standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.