





There is conclusive evidence that neural tube defects (NTD) can be prevented by increasing the intake of folic acid (vitamin B9)(Reference Wald, Sneddon and Densem1,Reference Wald, Law and Morris2) . Extensive research has produced no credible evidence that folic acid is harmful(Reference Berry, Bailey and Mulinare3). Consequently, there is no scientific justification for a folic acid upper intake level (ULFootnote *). In spite of this, a folic acid UL of 1 mg/day was proposed by the Institute of Medicine in 1998(4), which significantly restricts the benefits of fortifying foods such as flour and rice with folic acid as a public health policy to prevent NTD. The UL makes it impossible to achieve fully effective fortification (FEF), a fortification level that maximises the prevention of NTD above which there is minimal extra prevention. Implementing FEF would quadruple the number of NTD cases prevented compared to fortification at current levels. Importantly, a UL for folic acid was, in fact, set in error because of a flawed analysis in a 1998 Institute of Medicine report which incorrectly concluded that higher folic acid intake could exacerbate the neuropathy of vitamin B12 deficiency. The error, only recognised in 2018, failed to use denominators when determining risk(Reference Wald, Morris and Blakemore5). A correct evaluation of the Institute of Medicine report showed that there was no evidence that folic acid exacerbates neuropathic vitamin B12 deficiency and even provided evidence that this was not the case(Reference Wald, Morris and Blakemore5). Abandoning the UL for folic acid removes an unnecessary barrier which would allow the implementation of FEF in the prevention of NTD.
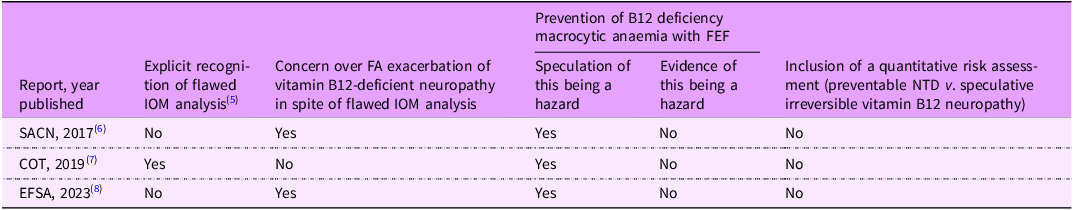
Two UK Government committees (Scientific Advisory Committee on Nutrition and Committee on Toxicology) have, nonetheless, produced reports that recommend retaining the UL of 1 mg folic acid a day(6,7) . More recently, a third report from the European Food Safety Authority has also done so(8). Table 1 summarises the considerations outlined in the three reports. In the Scientific Advisory Committee on Nutrition and European Food Safety Authority reports, retaining the UL was largely because of the now discredited risk of exacerbation of vitamin B12 neuropathy (the error identified in 2018). In all three reports, there was also concern expressed about the possible delay in diagnosing vitamin B12 deficiency. The concern is whether the chance finding of a macrocytic anaemia in a blood sample, taken as part of routine clinical practice, may prompt an investigation, in some individuals, to determine whether the macrocytic anaemia is caused by either a folate deficiency or a vitamin B12 deficiency and, then, treating the responsible deficiency if one were found. This is an example of opportunistic screening of unknown efficacy. It is further claimed that, if FEF resolves any vitamin B12 deficiency anaemia, there is a possibility that an irreversible B12-deficient neuropathy may be missed. Hence, it is suggested that with FEF the option for the opportunistic screening approach is lost. There is, however, no evidence that this opportunistic approach prevents irreversible B12-deficient neuropathy.
The opportunistic approach is, in any case, inherently limited because about 1 in 4 cases of vitamin B12 deficiency neuropathy has no macrocytic anaemia, so these cases will anyway be missed(Reference Lindenbaum, Healton and Savage9). Regarding the prevention of the B12 deficiency anaemia from folic acid as a hazard of folic acid is perverse. Folic acid is not harmful, including at intakes greater than 1 mg/day; it is more objectively regarded as a means of preventing the haematological part of B12 deficiency but not the neurological part.
Health policy is systematically influenced by omission bias, whereby an adverse outcome resulting from an action is regarded with greater concern than a worse adverse outcome resulting from failing to take that action(Reference Halpern, Truog and Miller10). Adherence to such an approach would mean that no public health action could be adopted because a hypothetical adverse effect, not based on evidence, could always be invoked as a possibility that could not be excluded. Instead, we suggest that policy should rest on weighing up risks – the risks (hazards) of not taking an action (thereby retaining UL based policy) which are substantial(Reference Wald, Law and Morris2,Reference Wald, Vale and Bestwick11) compared with the risks of taking the action (FEF) which are speculative and likely to be minimal or non-existent. In terms of NTD prevention, the risk of not implementing FEF is a failure to prevent about 80 % of NTD and, instead, prevent only about 20 % with mandated partial fortification at the levels adopted in many countries to avoid exceeding the UL. In the UK, this would fail to prevent 800, out of the approximately 1000 NTD that occur every year, and instead prevent just 200 with partial fortification. In terms of opportunistic screening, the risk of implementing FEF is the perceived possibility of missed cases of irreversible vitamin B12 neuropathy that might have been identified through observing a macrocytic anaemia. There is no evidence for this, and the number is likely to be exceedingly small or zero because vitamin B12 treatment, following the early symptoms of a neuropathy, would probably lead to B12 therapy while the disorder is still reversible. About 1 in 4 cases would anyway have to rely on such a policy of treating early symptoms. It is surely unsound policy to accept that three quarters of NTD cases will not be prevented (an estimate that is based on firm evidence) because of a possible and speculative risk that FEF might lead to an irreversible vitamin B12-deficient neuropathy that is unlikely(Reference Berry12).
If, for whatever reason, the possibility that FEF may lead to missed cases of irreversible vitamin B12-deficient neuropathy remains a concern and therefore holds back implementing FEF, the issue could be resolved if fortification included vitamin B12 at a level of about 0·2 mg/100 g flour, high enough for passive absorption of vitamin B12(Reference Berlin, Berlin and Brante13), necessary because active absorption could be impaired. Fortifying flour with vitamin B12 as well as folic acid would completely overcome the concern relating to FEF and would prevent all cases of vitamin B12 deficiency including those without a macrocytic anaemia. As with folic acid, there is no evidence that vitamin B12 is harmful. No tolerable UL has been established for vitamin B12 intake by any authority including European Food Safety Authority(14).
The folic acid fortification level to achieve FEF can be determined and monitored by measuring serum folate levels in a representative sample of about 200 adults, as has, for example, recently been done in the USA(Reference Lambert-Messerlian, James Sung and Palomaki15). The target fortification level is one that achieves a median population serum folate level of about 44 ng/ml – the level that has been shown in a randomised trial to prevent 83 % of NTD(Reference Wald, Sneddon and Densem1,Reference Wald, Vale and Bestwick11) . Achieving the target serum level would require setting an initial fortification level, say 1 mg per 100 g flour, and adjusting this as monitoring indicates the need to do so. At the same time, broadening the scope of fortification to include all flour and rice, rather than just non-wholemeal wheat flour, would ensure the policy applies equitably to all in society. Unfortified flour and rice could be labelled as such, with a health alert along the following lines: ‘Not fortified with folic acid (vitamin B9). Folic acid has been shown to prevent birth defects’. Monitoring should also include recording NTD rates through existing congenital malformation registries. A monitoring committee to ensure action is taken in a timely manner would be desirable.
The UK has mandated that by 13 December 2026, non-wholemeal wheat flour will be fortified at a level of 0·25 mg per 100 g flour(16). This is a welcome start but more can, and should, be done. Box 1 summarises the actions to achieve FEF in the prevention of NTD that deserve consideration by policymakers. In addition to the preventive effect on NTD: the policy would prevent macrocytic anaemia and, with co-fortification with sufficient B12, would prevent B12-deficient neuropathy. Implementation of the actions set out in Box 1 would be an excellent example of what public health agencies can and should achieve in the prevention of disease.
Policy actions to achieve fully effective folic acid fortification in the prevention of neural tube defects (NTDs)
-
• Abandon the upper intake level (UL) for folic acid.
-
• Increase the scope of what is fortified to all flour and rice.
-
• Increase folic acid fortification level to achieve a median population serum folate level of about 44 ng/ml.
-
• If missing cases of vitamin B12-deficient neuropathy are a concern, fortify all flour and rice with 0·2 mg B12 per 100 g flour.
-
• Monitor (i) serum folate levels in a sample of adults to ensure fully effective fortification is achieved and (ii) population NTD rates to demonstrate the preventive benefit.
-
• Label unfortified flour and rice: ‘Not fortified with folic acid (vitamin B9). Folic acid has been shown to prevent birth defects’.
Summary of considerations in three reports on folic acid

Table 1 Long description
A table with four rows and six columns comparing considerations in three reports on folic acid. The columns are Report, year published; Explicit recognition of flawed IOM analysis; Concern over FA exacerbation of vitamin B12-deficient neuropathy in spite of flawed IOM analysis; Speculation of this being a hazard; Evidence of this being a hazard; Inclusion of a quantitative risk assessment. The rows are SACN, 2017; COT, 2019; EFSA, 2023. Each row contains Yes or No values indicating the presence or absence of specific considerations.
SACN, Scientific Advisory Committee on Nutrition; COT, Committee on Toxicology; EFSA, European Food Safety Authority; IOM, Institute of Medicine; NTD, neural tube defect; FA, folic acid; FEF, fully effective fortification.
Financial support
None.
Competing interests
None.
Author contributions
Nicholas Wald initiated and composed the commentary. Nicholas Wald, Karen Wald and Jonathan Bestwick all contributed to the writing of the article.
Ethical standards
Not applicable.

 Open access

