The superior cavopulmonary anastomosis, also known as the bi-directional Glenn procedure, is a standard surgical palliation for single ventricle physiology before the completion of total cavo-pulmonary connection. Initially, used as an interim palliation only in high-risk patients,Reference Pridjian, Mendelsohn and Lupinetti 1 the bi-directional Glenn is now a routine stage preceding Fontan completion in all patients, with low operative risk and excellent short-term outcomes. Drawbacks of the superior cavopulmonary anastomosis include the development of pulmonary arteriovenous malformations in up to 60% of patients,Reference Bernstein, Brook, Silverman and Bristow 2 presumably due to the absence of a purported “hepatic factor”, thereby rendering some children increasingly cyanotic with time. The logical sequence after bi-directional Glenn has therefore been Fontan completion, incorporating inferior caval vein and hepatic venous flow to the pulmonary arteries, with near or complete separation of systemic and pulmonary circulations, and resolution of cyanosis if the pulmonary arteriovenous malformations regress.Reference Knight and Mee 3 In the presence of systemic venous anomalies including superior caval vein or tributary stenosis, thrombosis, hypoplasia, often leading to a network of inadequate collateral venous channels, or high-risk bilateral superior caval veins,Reference Iyer, Van Arsdell, Dicke, McCrindle, Coles and Williams 4 a bi-directional Glenn procedure may be a poor option. In these situations, an inferior cavopulmonary connection may provide a reliable source of pulmonary blood flow, avoid potential bi-directional Glenn failure, takedown, and a step backwards to shunted circulation, with resultant prolonged intensive care stay, morbidity, and even mortality.Reference Iyer, Van Arsdell, Dicke, McCrindle, Coles and Williams 4 It could theoretically accomplish one step forwards towards eventual Fontan completion, while providing hepatic venous return to the pulmonary arteries. The inferior vena cava-pulmonary artery shunt was first performed in 1993 by Macé et al. as a temporizing measure, with an intracardiac lateral tunnel, and transection with reimplantation of the superior caval vein elsewhere in the common atrium, in two patients with temporary contraindications to a Fontan completion.5 To our knowledge, we report the first successful primary extracardiac inferior cavopulmonary connection with satisfactory early follow-up.
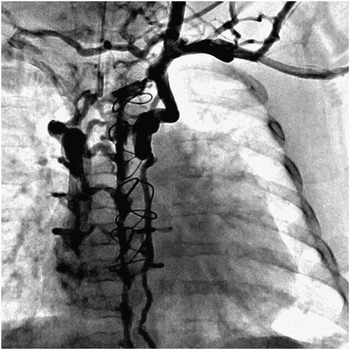
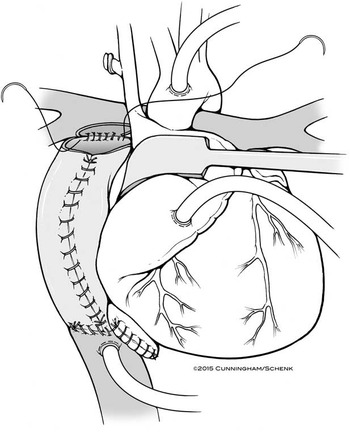
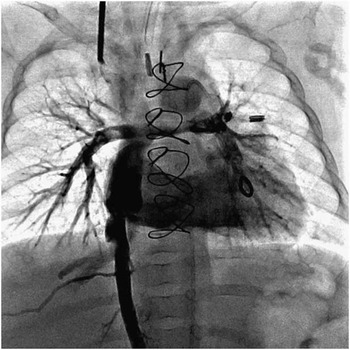
A 3-month-old male infant after a Norwood I operation with Sano modification for hypoplastic left heart syndrome presented for routine pre-Glenn evaluation. Ventricular function was normal with no semilunar or atrioventricular valve regurgitation. At catheterisation, pulmonary vascular resistance (2.94 Wood Units) and pulmonary artery pressures (18/13/15 mmHg) were normal, with adequate pulmonary arteries. The venogram demonstrated a thrombosed innominate vein and multiple veno–venous collaterals between a smaller right superior caval vein, a left remnant superior caval vein, the azygous vein, an accessory hemiazygous, and paravertebral plexuses (Fig 1). Attempts at interventional catheter improvement of the situation were unsuccessful. The surgery was deferred until nearly 6 months of age to encourage further superior caval vein growth, but intra-operative findings confirmed the unfavourable upper body venous anatomy for the planned bi-directional Glenn. After consulting with the referring paediatric cardiologist and family, we proceeded with primary inferior cavopulmonary connection. Through redo median sternotomy, arterial inflow was accomplished via the previous 3.5-mm GoreTex graft to the innominate artery, along with a low inferior caval vein and right atrial cannulation for venous return. The superior caval vein was mobilised, and the azygous vein was doubly ligated and transected, so that the future inferior caval vein–pulmonary artery conduit could travel unobstructed behind the superior caval vein–right atrial junction and avoid right pulmonary venous compression. Cardiopulmonary bypass was initiated and the procedure was performed on a beating heart. After takedown of the Sano shunt, the inferior caval vein was transected from the common atrium and the cardiac side was oversewn. A tube of bovine photofixed xenopericardium was created – with 14-mm diameter based on intra-operative inferior caval vein measurement – and anastomosed to the inferior caval vein opening. The pulmonary arteries were isolated, the underside opened, and anastomosed to the extracardiac conduit, working first between the aorta and the superior caval vein and then lateral to the superior caval vein (Fig 2). An intra-cardiac line was placed and tunnelled to the skin for common atrial pressure monitoring. Weaning from cardiopulmonary bypass was uneventful, with systemic oxygen saturations in the low eighties on a fractional inspired oxygen of 50%, pulmonary artery pressures via a femoral venous line of 14–18 mmHg, and atrial pressures of 4–6 mmHg. In the paediatric cardiac ICU, low-dose intravenous heparin was transitioned to oral Aspirin as with our standard post-Glenn protocol. Post-operative haemodynamics were stable, allowing planned early extubation, an uneventful 3-day ICU stay with removal of chest drains, and discharge to home on post-operative day eight. The infant maintained saturations in the low eighties on room air, had no abdominal symptoms, and was feeding and growing appropriately at 5 months post-operatively. A follow-up catheterisation (Fig 3) and CT-angiogram at 4 months post-operatively disclosed an open inferior caval vein–pulmonary artery connection, no veno–venous collateral systems in the lower body, and no hepatic venous congestion.
Pre-operative antero-posterior angiogram showing a small stenotic superior caval vein and multiple systemic veno–venous collaterals.

Artist’s illustration of the inferior cavopulmonary connection and the free lie posterior to the superior caval vein–common atrial junction.

Post-operative early injection angiogram showing the inferior cavopulmonary connection with widely patent anastomoses compatible with generous pulmonary artery flow.

Discussion
With anatomic concerns pertaining to upper body systemic veins, performing the standard superior cavopulmonary anastomosis may be a challenging forward step in single ventricle palliation. When considering optimal staging towards Fontan completion, it is paramount to protect the pulmonary arteries from hypertension while promoting pulmonary artery growth, and shorten the duration of shunted physiology yet avoid Glenn takedown. Faced with a patient with sub-optimal upper body systemic venous anatomy, likely due to vascular access-induced thrombosis of the innominate vein, we attempted and successfully performed a new alternative surgical operation – the primary extracardiac inferior cavopulmonary connection. This palliation allowed saturations equal to those expected after a standard bi-directional Glenn, the post-operative course was uneventful, of similar duration to a bi-directional Glenn, and, to date, has allowed the infant to feed and grow normally, without any evidence of morbidity. If a hepatic factor entity exists,Reference Bernstein, Brook, Silverman and Bristow 2 it may flow directly to the pulmonary arteries with the primary inferior cavopulmonary connection, and hopefully avoid the formation of troublesome pulmonary arteriovenous malformations leading to increased cyanosis.Reference Knight and Mee 3 A bubble-contrast echocardiographic study or angiography will be planned in the near future of our patient to study this potential phenomenon. Longer follow-up is certainly warranted to understand the fate of this new physiology and perhaps extend its indications: whether it leads to an unplanned inter-stage re-operation, will be an ideal set-up for future Fontan completion with the superior caval vein,5 or results in a final palliative stage not needing any further intervention, given the similar haemodynamics and oxygen delivery to a very largely fenestrated Fontan circulation.
Limitations to the technique and future considerations
In the absence of a right-sided pumping chamber, creating an inferior caval vein–pulmonary artery connection with laminar flow, which goes against gravity, in an infant who is not yet ambulating or even crawling may be haemodynamically sub-optimal. The true significance of this phenomenon compared with the bi-directional Glenn, which theoretically uses gravity to flow downwards is however unknown. The use of an interposition graft of any nature, which will not grow, may render future re-operations inevitable due to potential conduit outgrowth (patient-conduit size mismatch), although many centres uniformly use small conduits at Fontan completion.
Acknowledgements
The authors thank Kyle Cunningham and Michael Schenk for their superb surgical illustration.
Financial Support
This research received no specific grant from any funding agency, commercial, or not-for-profit sectors.
Conflicts of Interest
None.