Introductıon
Primary blast injuries typically affect the auditory system. High pressure with the general blast effect can trigger hearing loss, which can be conductive, sensorineural or mixed. In reports in the literature of the effects of blast trauma on the auditory system, there is hearing loss of any type and level in approximately 60 per cent of patients.Reference Cave, Cornish and Chandler1 Hearing losses can vary from a mild degree to a very advanced degree. Just as blast effect can affect the outer ear, there may also be tympanic membrane perforations of various dimensions in the middle ear, and ossicle chain ruptures and fractures.Reference Garth2,Reference Choi3 In the cochlea, mechanical damage is seen because of excessive force applied on basilar membranes with the blast effect. This can lead to separation of the support cells on the basilar membrane from inner and outer hair cells. In addition, it can cause ruptures resulting in the mixing of perilymph and endolymph, causing changes in the integrity of the tight cell connections in the reticular lamina, changes in membrane permeability or in the reticular lamina, and changes in the ionic environment of cochlear fluid. Loss of hair cells can be induced by the blast. Greater damage has been seen in outer hair cells than in inner hair cells. This damage in the cochlea is more evident in the basal section (at high frequencies) than in the apical section.Reference Choi3,Reference Patterson and Hamernik4 Perilymph fistula can be observed originating from rupture of the round window.
The otolith organs are formed from utricles and saccules, which contribute to postural stability by providing sensory input related to changes in gravity and linear acceleration. Saccules perceive linear acceleration in the vertical plane, whereas utricles are localised horizontally and perceive linear acceleration in the horizontal plane. Tests that have been developed to measure the otolith function have become more important in recent years. The cervical vestibular-evoked myogenic potential measures saccular and inferior vestibular nerve function, and the ocular vestibular-evoked myogenic potential measures the vestibular response from the utricle through the superior vestibular nerve.Reference Fife, Colebatch, Kerber, Brantberg, Strupp and Lee5
In addition to blast trauma affecting the cochlea, it also affects the vestibular system because of the close anatomical proximity. It is thought that there could be an effect in the utricle and saccule because of the proximity to the stapes. Damage forming in the utricle and saccule following the blast has been shown histologically in literature.Reference McCabe and Lawrence6,Reference Mangabeira-Albernaz, Covell and Eldredge7 However, this is a subjective clinical complaint in patients and the results of publications in literature related to observation in objective tests are conflicting. The aim of this study was to evaluate long-term dizziness subjectively with questionnaires and objectively with electrophysiological tests in patients with sensorineural hearing loss following exposure to blast trauma while serving in the Armed Forces.
Materials and methods
Approval for the study was granted by the Medical and Health Sciences Research Committee and the Non-Interventional Clinical Research Ethics Committee (decision no. 20/22, 12 February 2020). All procedures were applied in compliance with the Helsinki Declaration. The study was planned as a case–control study. The sample size was calculated using the G*power program to provide 0.95 power and 0.05 significance level. The patient group was formed of 25 military personnel (43 affected ears) who had experienced blast trauma while serving in the Armed Forces, and a control group was formed of 22 healthy adult volunteers (44 healthy ears).
All the patient group had been injured by handmade explosives. Although hearing loss developed immediately after the explosion, the patients were admitted to the ENT clinic in the late period as a result of intracranial and orthopaedic injuries. Informed consent for voluntary participation in the study was provided by all the study participants.
The control group was formed of healthy subjects who were age- and gender-matched to the military personnel patients who presented at the hospital because of blast trauma.
The inclusion criteria for the patient group were defined as no history of otological (ear membrane perforation, ear surgery, chronic otitis), neurological or ophthalmological problems, and diagnosed with sensorineural hearing loss because of blast trauma.
The inclusion criteria for the control group were normal results of otoscopic examination of both ears and pure tone average (PTA) of better than 20 dB, type A tympanogram and the presence of normal acoustic reflex, and no determination of any otological or neurological problems.
Following the otoscopic examination, the control group was administered pure tone audiometry, tympanometry, acoustic reflex, and cervical and ocular vestibular-evoked myogenic potential tests with both tone-burst and narrow-band level-specific Claus Elberling chirp stimuli. In addition to these examinations, the patient group also completed the Dizziness Handicap Inventory.
Pure tone audiometry
Air-conduction thresholds at 125–8000 Hz and bone-conduction thresholds at 250–4000 Hz were measured with the same device (AC40, Interacoustic, Denmark). Supra-aural TDH 39 earphones were used in the measurements. The PTA was calculated as the average of the 500, 1000, 2000 and 4000 Hz measurements.
Dizziness Handicap Inventory
The Dizziness Handicap Inventory aims to determine the change in the quality of life of patients with complaints of dizziness.Reference Jacobson and Newman8 The scale comprises 25 items related to the physical, functional and emotional status of patients. High points scored on the scale indicate that the quality of life of the patient is more negatively affected. Validity and reliability studies of the Turkish version of the inventory have been conducted.Reference Canbal, Cebeci, Duyan, Kurtaran and Arslan9
Cervical and ocular vestibular-evoked myogenic potential recordings
The tests were performed in a quiet room with the patient seated. The Interacoustic Eclipse EP 15 device (Interacoustics Eclipse EP15) and insert earphones (Ear tone ABR 3A; 3M, Minneapolis, MN, USA) were used in the tests. The device was calibrated by technicians licensed according to International Organization for Standardization 389-6 standards. For the cervical vestibular-evoked myogenic potential recording, an active (non-inverting (+)) electrode was placed on the sternum, reference (inverting (−)) electrodes were placed on the section adjoining the upper third of the two sternocleidomastoid muscles and the ground electrode was placed on the vertex (Ambu® Neuroline™ 720; Ambu, Ballerup, Denmark). Effective contraction of the sternocleidomastoid muscle was obtained by turning the head away from the side of the ear being tested and observing the visual feedback of the software throughout the test. As the P13N23 amplitude is affected by sternocleidomastoid muscle contraction, the study subjects were informed of the visual feedback obtained from the software during the electromyography (EMG) recording to keep the muscle activity at a stable level. To eliminate the effect of muscle fatigue, the narrow-band level-specific Claus Elberling chirp and tone-burst stimuli were applied randomly.
For the ocular vestibular-evoked myogenic potential recording, the reference electrodes (inverting) were placed 1 cm below both eyelids (over the inferior oblique muscle), the active (non-inverting (+)) electrode was placed on the chin and the ground electrode was placed on the forehead. The subjects were instructed to look continuously at a fixed point at approximately 30° upwards and a distance of 60 cm. The impedance of the electrodes was set at <5 kOhm. Responses formed to stimuli at 500-Hz tone-burst (TB) and 500-Hz narrow-band level-specific Claus Elberling chirp (360–720 Hz) were recorded separately for each ear. For the 500-Hz tone burst, the rise, plateau and fall times were 2, 2 and 2 ms, respectively. The stimulus time for the 500-Hz narrow-band Claus Elberling chirp between 360 and 720 Hz stimuli (up chirp) was 9 millisecond. The recordings for both stimuli were started at 95 dB nHL and were reduced by 5 dB nHL until the threshold was determined.
The cervical vestibular-evoked myogenic potential was defined as a biphasic P1N1 (P13N23) wave, characterised by positive polarity in approximately the 13th millisecond (P13) and negative polarity in approximately the 23rd millisecond (N23). The ocular vestibular-evoked myogenic potential was defined as negative polarity in approximately the 10th millisecond (N10) and positive polarity in approximately the 16th millisecond (P16). When the same form and latency were obtained when the tests were repeated twice, this was evaluated as a response. The EMG signals were amplified (×10 000) and filtered between 10 and 1000 Hz. The stimulus rate was set as 5.1/sn, analysis duration 55 ms and polarity as rarefaction. A total of 200 stimuli were obtained on average. To normalise the raw vestibular-evoked myogenic potential amplitudes for cervical vestibular-evoked myogenic potentials, the rectified EMG was taken into consideration. For muscle activity, the rectified muscle signal was kept at 20–200 μV during the recording.
Measurements were taken of P1 latency, N1 latency, P1N1 amplitudes and thresholds for each stimulus for 43 affected ears and 7 non-affected ears in the patient group, and for 44 healthy ears in the control group.
Statistical evaluation
The data obtained in the current study were analysed statistically using SPSS v. 22 software (SPSS, Chicago, IL, USA). Descriptive statistics were stated as mean ± standard deviation, median, minimum–maximum and interquartile range values. In the comparisons between the hearing threshold frequencies of the affected ears in the patient group, the Wilcoxon signed rank test with Bonferroni correction was used. In the comparisons of the hearing frequency thresholds between the affected and non-affected ears in the patient group, the student's t-test was applied to data showing normal distribution and the Mann–Whitney U test to data that did not show normal distribution. These two tests, according to the parametric assumptions, were also applied to the comparisons between the patient and control groups in respect of the cervical and ocular vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude for each stimulus. A value of p less than 0.05 was accepted as statistically significant.
Results
Evaluation was made of 43 ears affected by blast trauma in 25 patients and 44 healthy ears of 22 healthy control group subjects. The mean age of the subjects was 28.68 ± 7.25 years (range, 20–47 years) in the control group and 26.44 ± 7.25 years (range, 20–48 years) in the patient group. No significant difference was determined between the groups in respect of age (p = 0.222).
In the patient group, the mean time since the blast trauma was 41.16 ± 16.75 days (range, 22–65 days). The ears were affected bilaterally in 18 out of 25 patients and unilaterally in 7 out of 25 patients (4 left ear, 3 right ear). The mean Dizziness Handicap Inventory score of the patient group was 14.80 ± 23.38 (range, 0–88).
The PTAs and threshold values (dB HL) at 250, 500, 1000, 2000, 4000, 6000 and 8000 Hz of the 43 affected ears in the patient group are shown in Table 1.
Hearing thresholds of the affected ears in the patient group (n = 43)

PTA = pure tone average (500, 1000, 2000 and 4000 Hz); SD = standard deviation; min–max = minimum–maximum
In the comparisons of the 43 affected ears in the patient group at low frequencies (250–500 Hz), mid frequencies (1000–2000 Hz) and high frequencies (4000, 6000 and 8000 Hz), a statistically significant difference was observed between the 3 groups (Friedman test, p = 0.000). In the within-group comparisons, there was no significant difference between the hearing thresholds at low and mid frequencies, and there was determined to be a significant difference between the low and high frequencies and between the mid and high frequencies (Wilcoxon signed rank test with Bonferroni correction for low and mid frequencies was p = 0.154, for low and high frequencies was p = 0.000, and for mid and high frequencies was p = 0.000). The hearing thresholds at high frequencies were found to be significantly higher in the ears affected by blast trauma.
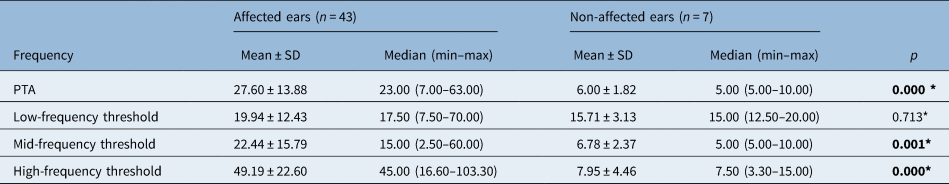
The comparisons of the PTAs and hearing thresholds at low, mid and high frequencies of the affected and non-affected ears in the patient group are shown in Table 2.
Comparisons of pure tone averages and hearing thresholds at low frequencies (250–500 Hz), mid frequencies (1000–2000 Hz) and high frequencies (4000, 6000 and 8000 Hz) of the affected and non-affected ears in the patient group

*Mann–Whitney U test. PTA = pure tone average (500, 1000, 2000 and 4000 Hz); SD = standard deviation; min–max = minimum–maximum
No statistically significant difference was determined between the two groups of affected and non-affected ears in the patient group in respect of hearing thresholds at low frequencies (p = 0.713). A statistically significant difference was determined in both groups between mid and high frequencies (p = 0.001 and p = 0.000, respectively). The difference in PTA between the groups was statistically significant (p = 0.000).
In all the 44 healthy control group ears, cervical and ocular vestibular-evoked myogenic potential responses were obtained with both 500-Hz tone-burst and 500-Hz narrow-band level-specific Claus Elberling chirp stimuli. In the patient group, a cervical vestibular-evoked myogenic potential response was not obtained in 3 of 43 affected ears (6.9 per cent) with both 500-Hz narrow-band and 500-Hz tone-burst level-specific Claus Elberling chirp stimuli. In 5 out of 43 ears (11.6 per cent), no 500-Hz tone-burst ocular vestibular-evoked myogenic potential response was obtained, and in 3 out of 43 ears (6.9 per cent) no 500-Hz narrow-band level-specific Claus Elberling chirp ocular vestibular-evoked myogenic potential response was obtained. There were 2 people who did not have 500-Hz tone-burst ocular vestibular-evoked myogenic potential response, but did have a 500-Hz narrow-band level-specific Claus Elberling chirp ocular vestibular-evoked myogenic potential response.
The cervical vestibular-evoked myogenic potential responses obtained with a 500-Hz tone-burst stimulus in the patient and control groups are shown in Figure 1. The comparisons of the 500-Hz tone-burst cervical vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude values between the patient and control groups are shown in Table 3. No statistically significant difference was determined between the patients and control groups in respect of the P1 latency, N1 latency and P1N1 amplitude values in the cervical vestibular-evoked myogenic potential test applied with a 500-Hz tone-burst stimulus (p = 0.467, p = 0.925 and p = 0.066, respectively).
Cervical vestibular-evoked myogenic potential sample of the patient (top) and control (bottom) groups with a 500-Hz tone-burst stimulus.

Comparison of 500-Hz tone-burst cervical vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude between the patient and control groups

p < 0.05 was considered significant. *Mann–Whitney U test. ms = millisecond; μV = microvolt; SD = standard deviation; min–max = minimum–maximum
The cervical vestibular-evoked myogenic potential responses with a 500-Hz level-specific Claus Elberling chirp stimulus of the patient and control groups are shown in Figure 2.
Cervical vestibular-evoked myogenic potential sample of the patient (top) and control (bottom) groups with a 500-Hz level-specific Claus Elberling chirp stimulus.

The comparisons of the 500-Hz level-specific Claus Elberling chirp cervical vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude values between the patient and control groups are shown in Table 4.
The comparison of cervical vestibular-evoked myogenic potential responses with a 500-Hz level-specific Claus Elberling chirp stimulus of the patient and control groups

p < 0.05 was considered statistically significant. *Mann–Whitney U test. ms = millisecond; μV = microvolt; SD = standard deviation; min–max = minimum–maximum
No statistically significant difference was determined between the patient and control groups in respect of the P1 latency, N1 latency and P1N1 amplitude values in the cervical vestibular-evoked myogenic potential test applied with a 500-Hz narrow-band level-specific Claus Elberling chirp stimulus (p = 0.576, p = 0.993 and p = 0.078, respectively).
The ocular vestibular-evoked myogenic potential responses obtained with a 500-Hz tone-burst stimulus in the patient and control groups are shown in Figure 3.
Ocular vestibular-evoked myogenic potential sample of the patient (top) and control (bottom) groups with a 500-Hz tone-burst stimulus.

The comparisons of the 500-Hz tone-burst ocular vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude values between the patient and control groups are shown in ×Table 5.
The comparison of ocular vestibular-evoked myogenic potential responses with a 500-Hz tone-burst stimulus of the patient and control groups

p < 0.05 was considered statistically significant. *Mann–Whitney U test. ms = millisecond; μV = microvolt; SD = standard deviation; min–max = minimum–maximum
No statistically significant difference was determined between the patient and control groups in respect of the P1 latency, N1 latency and P1N1 amplitude values in the ocular vestibular-evoked myogenic potential test applied with a 500-Hz tone-burst stimulus (p = 0.484, p = 0.933 and p = 0.289, respectively).
The ocular vestibular-evoked myogenic potential responses with a 500-Hz narrow-band level-specific Claus Elberling chirp stimulus of the patient and control groups are shown in Figure 4.
Ocular vestibular-evoked myogenic potential sample of the patient (top) and control (bottom) groups with a 500-Hz level-specific Claus Elberling chirp stimulus.

The comparisons of the 500-Hz narrow-band level-specific Claus Elberling chirp ocular vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude values between the patient and control groups are shown in Table 6.
The comparison of ocular vestibular-evoked myogenic potential responses with a 500-Hz level-specific Claus Elberling chirp stimulus of the patient and control groups

p < 0.05 was considered statistically significant. *Mann–Whitney U test. ms = millisecond; μV = microvolt; SD = standard deviation; min–max = minimum–maximum
No statistically significant difference was determined between the patient and control groups in respect of the P1 latency, N1 latency and P1N1 amplitude values in the ocular vestibular-evoked myogenic potential test applied with a 500-Hz narrow-band level-specific Claus Elberling chirp stimulus (p = 0.081, p = 0.062, p = 0.418, respectively).
Dıscussıon
The ear is one of the most frequently injured organs following blast trauma. In the literature, it has been reported that sensorineural, conductive or mixed-type hearing losses are seen with the effect of blast trauma. However, there are very few studies related to whether or not there is any change in the vestibular system with blast effect, and the results of those studies are extremely variable. The aim of the current study was to evaluate late-term dizziness subjectively and objectively in patients who had developed sensorineural hearing loss as a result of exposure to an explosion while serving in the Turkish Armed Forces. Objective assessment was done with cervical and ocular vestibular-evoked myogenic potentials. Although the study results showed that there was no significant change in otolith function with blast effect, there was seen to be an absence of cervical and ocular vestibular-evoked myogenic potential responses in some patients. A high Dizziness Handicap Inventory score was obtained by very few patients.
A blast (explosion) is the energy which generally occurs with the rapid transformation of solids or liquids to gas. Gas molecules heat up rapidly and move more quickly than the speed of sound with high pressure. Pressurised gas fills the same volume as liquid or solids. The high-pressure area expands and an excessive pressure peak is reached, which is known as shock wave. Low pressure, which is known to be a drop in atmospheric pressure, follows the shock wave and an overheated blast wind is formed.Reference Cave, Cornish and Chandler1 Blast injuries can be classified in five different categories: primary, secondary, and third, fourth and fifth degree. The ear is within primary blast injuries and damage or injuries develop as a result of excessive pressure or the low-pressure wave itself.
In the literature, hearing results following blast trauma show great variability. This can most probably be attributed to the proximity of the individual to the blast, the type and amount of explosive used, and the environment in which the explosion occurred. A 2017 study reported that hearing loss was sensorineural in 30 per cent of cases exposed to blast trauma, mixed type in 55 per cent and conductive type in 15 per cent.Reference de Régloix S, Crambert, Maurin, Lisan, Marty and Pons10 In the current study cases, with tympanic membrane perforation and ossicle chain pathologies were not included because these can greatly inhibit the response to vestibular-evoked myogenic potential tests.Reference Lee, Lee, Shin, Yeo, Park and Byun11
Cervical vestibular-evoked myogenic potentials showing the function of the ipsilateral saccule and inferior vestibular nerve, and ocular vestibular-evoked myogenic potentials showing the function of the contralateral utricle and superior vestibular nerve are non-invasive electrophysiological tests.Reference Fife, Colebatch, Kerber, Brantberg, Strupp and Lee5,Reference Felipe and Kingma12,Reference Erbek, Gokmen, Ozkiraz, Erbek, Tarcan and Ozluoglu13
When traditional acoustic stimuli are used, such as click, tone-burst and tone-pip, different neural regions along the cochlea cannot be stimulated at the same time. However, the chirp stimulus has been designed to compensate for the time delay in peripheral hearing by increasing the time synchronisation between neural structures.Reference Elberling, Callø and Don14 The chirp stimulus provides a stimulus to all the regions of the cochlea at approximately the same time. It is an acoustic stimulus whose frequency changes (increasing or decreasing) over time. This time synchronisation can provide a stimulus with a delay at higher frequencies compared with lower frequencies. However, the direct effect of this stimulus on the vestibular pathway is not yet clear.Reference Atcherson and Moore15 In the literature, several chirp stimuli have been defined, such as the Claus Elberling chirp, the wide-band chirp, the narrow-band chirp.
In this study, there were 2 patients in the patient group who did not respond with a 500-Hz tone burst in the ocular vestibular-evoked myogenic potential test, but did respond with a 500-Hz narrow-band level-specific Claus Elberling chirp stimulus. Ocular vestibular-evoked myogenic potential occurs from small amplitude waves because the eye muscles responding are extremely small. That the amplitude with the chirp stimulus was significantly larger compared with the tone-burst stimulus is extremely important in respect of increasing the detectability of the wave.
Studies in the literature vary in relation to the effect on the vestibular system in addition to the hearing system in blast trauma. There are studies that have reported that vertigo in blast trauma is due to secondary or third-degree mechanisms causing vibration in the central nervous system rather than inner-ear damage. Peripheral vestibular aetiologies following trauma include benign paroxysmal postonal vertigo, perilymphatic fistula and acute trauma to the utricle and saccule of the inner ear.Reference Darley and Kellman16 In a 2007 study of 258 patients exposed to blast trauma, dizziness was reported in 15 per cent of patients.Reference Cave, Cornish and Chandler1 In another study, dizziness was seen in 18 per cent of patients exposed to blast trauma who had no history of dizziness or imbalance. It has been reported that this symptom emerges in the later term. The Dizziness Handicap Inventory of moderate-severe level was observed 17 per cent of patients in the 6th month, but no significant difference was determined in the severity of dizziness evaluated with the Dizziness Handicap Inventory immediately after the trauma and in the 6th month.Reference Remenschneider, Lookabaugh, Aliphas, Brodsky, Devaiah and Dagher17
In a study by McCabe et al., guinea pigs were exposed to intense noise in the range of 136–150 dB sound pressure levels and the harmful effects were seen to be limited to the pars inferior (cochlea and saccule), whereas the pars superior (utricle and semi-circular canals) was relatively intact.Reference McCabe and Lawrence6 Another study in 2017 reported vertigo in 8 of 41 patients exposed to blast trauma. In four of these eight patients, nystagmus was also determined and in seven of the eight, tympanic membrane perforation. With the exception of one patient with stapes footplate fracture, who initially presented with irritative peripheral vestibular syndrome, the vertigo in all the other patients disappeared within three months.Reference de Régloix S, Crambert, Maurin, Lisan, Marty and Pons10
Scherer et al. compared dizziness in 24 US soldiers with blast-associated traumatic brain injury within the last year in two groups of symptomatic and asymptomatic patients. When the symptomatic patients with dizziness were examined with videonystagmography, unilateral vestibular hypofunction was seen more, and unexplained nystagmus associated with central vestibular dysfunction was reported in both groups. The authors stated that these vertigo cases are usually related to head trauma associated with secondary or third-degree blast injuries. In the same study, the cervical vestibular-evoked myogenic potential test was applied to 14 patients and there was seen to be no response on one side in 2 patients. Two of the 14 patients also showed abnormally prolonged P1 latency, suggesting potential saccular or medial vestibulospinal system dysfunction. In 2 of 18 patients in the Subjective Visual Vertical test, abnormal deviation to the right was observed, which suggested possible unilateral otolith involvement. In the Dizziness Handicap Inventory, the symptomatic group scores were found to be significantly different from those of the asymptomatic group. However, no information was provided about the hearing status of the patients.Reference Scherer, Burrows, Pinto, Littlefield, French and Tarbett18
In a 2018 study of patients exposed to fireworks explosions, dizziness was seen in 33 per cent. In the evaluation of the vestibular system of these patients, canal paresis was determined in the caloric test in 3 of 40 affected ears, and in the cervical and ocular vestibular-evoked myogenic potential tests, which could only be applied in 10 affected ears, cervical vestibular-evoked myogenic potential absence was determined in 8 ears, normal cervical vestibular-evoked myogenic potential in 2 ears, reduced amplitude ocular vestibular-evoked myogenic potential in 2 ears and no response to ocular vestibular-evoked myogenic potential in 4 ears. Hearing loss, cervical vestibular-evoked myogenic potential abnormality and ocular vestibular-evoked myogenic potential abnormality were seen at significantly higher rates than abnormality in the caloric test. From these results it was concluded that the cochlea, utricle and saccule were affected by blast trauma, but the semi-circular canals were protected from the blast effect.Reference Liao and Young19
Although vestibular damage is probably related to the close anatomical proximity of the utricle and saccule to the stapes footplate, it has been rarely reported, and these studies have associated the injury with saccular and utricular damage or direct head trauma. Utricle and saccule ruptures have been identified in the post-mortem findings of individuals who have died in explosions.Reference Cohen, Ziv, Bloom, Zikk, Rapoport and Himmelfarb20
In a 2014 study of 110 patients with blast trauma and a control group of 54 subjects, greater hearing loss at 500, 1000, 2000, 3000 and 6000 Hz was observed in the blast trauma group than in the control group, and dizziness was observed significantly more in the blast trauma patients. When dizziness was evaluated independently, it was observed to be correlated with increasing hearing thresholds.Reference Shah, Ayala, Capra, Fox and Hoffer21
In the current study, the mean Dizziness Handicap Inventory score of the patient group was found to be 14.80 ± 23.38 (range, 0–88). Of the 43 affected ears in the patient group, no cervical vestibular-evoked myogenic potential response was obtained with a 500-Hz tone-burst stimulus in 3 ears (6.9 per cent) and no ocular vestibular-evoked myogenic potential response was obtained with a 500-Hz tone-burst stimulus in 5 ears (11.6 per cent). The Dizziness Handicap Inventory score was found to be high in 2 patients, with one patient scoring 74 and the other 88. In the patient with a Dizziness Handicap Inventory score of 74, there was a cervical vestibular-evoked myogenic potential response and no response was observed in ocular vestibular-evoked myogenic potential. In the patient with a Dizziness Handicap Inventory score of 88, a response was observed to both cervical and ocular vestibular-evoked myogenic potentials. These results could show that in some patients a part of the vestibular pathway is affect by blast trauma. When the differences between the patient and control groups were examined, no statistically significant difference was observed between the two groups in respect of cervical vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude applied with 500-Hz tone-burst and 500-Hz narrow-band level-specific Claus Elberling chirp stimuli, and in ocular vestibular-evoked myogenic potential P1 latency, N1 latency and P1N1 amplitude. The findings of the current study that the tympanic membrane was intact in the patient group suggest that the vestibular system was protected from the blast effect. However, these tests were conducted at mean 41.16 days after the blast trauma so the findings could indicate that blast trauma creates no significant change in the vestibular system in the chronic period. The different results of the effect of blast trauma on the vestibular system in this study and in other studies in literature could be due to several reasons. The severity and duration of the blast to which the patient was exposed and the position of the individual at the moment of the explosion could explain the differences in the findings. Moreover, different vestibular tests used in different studies could be explained the different results. Because each vestibular test evaluates different regions of the vestibular pathway. Most studies in the literature have used a limited test battery in the evaluation of the vestibular system after blast trauma. This makes it impossible to evaluate all the vestibular pathways together. In the current study, the utricle, saccule, superior and inferior vestibular nerves, and related pathways were evaluated.
In the comparisons of the vestibular-evoked myogenic potential responses of the patient and control groups, statistically similar results were obtained with both the tone-burst stimulus and the chirp stimulus. From this result, it can be said that just as the chirp stimulus can be used in healthy individuals, it can also be used instead of the tone-burst stimulus in patient groups.
• Blast trauma affecting the cochlea may also affect the vestibular system because of the close anatomical proximity
• In cervical and ocular vestibular-evoked myogenic potential tests there was no significant difference in the comparison of P1 latency, N1 latency and P1N1 amplitude between the control and patient groups for both the tone-burst stimulus and the narrow-band level-specific Claus Elberling chirp stimulus
• The functions of otolith organs were not affected in the late period after blast trauma
The most important limitation of this study was the low number of subjects. However, the changes seen in the ear as a result of blast trauma are extremely heterogenous. These not only caused sensorineural hearing loss, but also tympanic membrane perforation at a high rate and ossicle chain ruptures. This study therefore only included patients with sensorineural hearing loss that was thought to have affected the cochlea, following blast trauma, and in addition to the cochlea and auditory system it was intended to determine to what extent the vestibular system was affected by the use of cervical and ocular vestibular-evoked myogenic potentials. Another limitation of the study was that not all the patients were evaluated in respect of the audiovestibular system immediately after the blast. The patients presented at the ear, nose and throat clinic on average 41.16 ± 16.75 days after the blast, and audiological and vestibular tests were then applied. Patients who presented in the first days after the blast or after 90 days were therefore excluded from the study. This suggests that at the time of presentation, the patients were in the late term of the blast trauma. Multi-organ injuries as a result of an explosion are seen extremely frequently, and as these injuries are often orthopaedic, these patients can only consult our polyclinic after their condition has stabilised.
Conclusıon
The vestibular function of young adults, as measured by cervical and ocular vestibular-evoked myogenic potentials and the Dizziness Handicap Inventory, is not affected by blast injuries in the long term. An extremely detailed examination of the vestibular system should be made following blast trauma and, if possible, a broad vestibular system evaluation test battery should be used that will be able to evaluate all parts of the vestibular system.
Competing interests
None declared