Clostridioides difficile infection (CDI) is common in the hospital setting, accounting for 15% of all healthcare-associated infections in the United States. Reference Magill, O’Leary and Janelle1 Based on data from the Centers for Disease Control Emerging Infections Program, the overall incidence rate of CDI in the United States in 2020 was 101.3 cases per 100,000 persons, with 51.2 cases being community-acquired and 50.1 cases being hospital-acquired. 2 Although the overall incidence of CDI has decreased over the last decade, the incidence of recurrent CDI has increased, highlighting the need to identify strategies to reduce recurrence. Reference Feuerstadt, Theriault and Tillotson3 Recurrent disease has been reported in 20%–35% of cases in the United States, with notable risk factors including advanced age, gastric acid suppressive therapy, infection with the hypervirulent NAP1/B1/027 strain, and most importantly, exposure to systemic antibiotics that may disrupt intestinal microflora and enable overgrowth of C. difficile. Reference Feuerstadt, Theriault and Tillotson3–Reference Finn, Andersson and Madin-Warburton7
The pathogenesis of CDI involves disruption of the microbiome, and cessation of antibiotics in patients with active CDI is critical to restoring normal bowel flora and improving CDI-related outcomes. In a trial evaluating the effect of concomitant antibiotics on response to fidaxomicin or oral vancomycin for CDI, patients who received concomitant antibiotics had a lower clinical cure rate, extended time to resolution of diarrhea, and a higher recurrence rate compared to those who did not require antibiotics. Reference Mullane, Miller and Weiss8 Nevertheless, antibiotics may remain necessary in patients with CDI due to new or persistent accompanying infections, and data to guide management in these circumstances are limited. Reference Fitzpatrick, Safdar, van Prehn and Tschudin-Sutter9
Current practice guidelines recommend a 10-day course of fidaxomicin or oral vancomycin for initial episodes of CDI, but they do not offer a separate recommendation for patients receiving concomitant antibiotics for part, or for the entirety of, their CDI treatment course. The major trials that established this 10-day duration of therapy either did not comment on the use of concomitant antibiotics or permitted use for up to 7 days without defining which agents were used and for what duration. Reference Cornely, Crook and Esposito10–Reference Guery, Menichetti and Anttila13 In 3 small, retrospective studies evaluating the impact of prolonging CDI-active therapy in patients requiring concurrent antibiotics, no reduction in disease recurrence with extension was observed. However, these studies were limited by prevalent use of oral metronidazole as primary treatment for CDI, lack of description of CDI disease severity, and short duration of follow-up or loss to follow-up. Reference Keats, Stitt and Chastain14–Reference Kaki, Brooks, Main, Jayaratne and Mertz16
Because CDI practice guidelines do not address duration of oral vancomycin treatment with concomitant systemic antibiotics that cannot be discontinued, vancomycin prescribing varies in this clinical scenario. It is unclear whether prolonging the duration of vancomycin in a high-risk cohort of hospitalized patients reduces the risk of disease recurrence. We evaluated vancomycin prescribing practices in patients with CDI who were continued on systemic antibiotics to determine whether prolonged durations of treatment beyond 14 days decrease the risk of CDI recurrence.
Methods
Study design
This was a retrospective cohort study of patients hospitalized with CDI between January 2017 and October 2022 at New York University Langone Health (NYULH) Manhattan campus (Tisch Hospital/Kimmel Pavilion), a 925-bed tertiary academic medical center. We obtained institutional review-board approval for this study. Patients were included if they were aged ≥18 years, had an initial episode of CDI confirmed by polymerase chain reaction (PCR), received treatment with oral vancomycin for at least 10 days, and required concomitant systemic antibiotics for >72 hours during vancomycin treatment while admitted. Patients were excluded if they were treated at any time with fidaxomicin or oral metronidazole for CDI or if they transitioned to hospice care or died during CDI treatment.
Institutional practice
Institutional policies are in place at NYULH that outline appropriate CDI testing requirements. The NYULH microbiology laboratory tests for CDI via polymerase chain reaction (PCR Xpert CD assay; Cepheid, Sunnyvale, CA) without a confirmatory enzyme immunoassay (EIA) to assess for toxin production. For this reason, diagnostic stewardship initiatives are in place to prevent false-positive results in patients colonized with CDI but not actively infected. These initiatives include rejection of formed stool specimens or samples sent within 30 days of a positive test, as well as rejection of samples sent within 24 hours of receipt of a bowel regimen, new tube feeds, or oral contrast media. Additionally, decision support within the Epic order (Epic, Verona WI) requires provider attestation that clinical suspicion for CDI is high and that the patient had 3 or more loose stools within 24 hours.
Guidelines also exist at NYULH to provide recommendations for CDI treatment and prevention in adults, but ultimately, decisions are at the discretion of the treating teams. Consistent with the Infectious Diseases Society of America (IDSA) guidelines, management of active CDI within the NYULH guideline is stratified based on disease severity and whether the episode is initial or recurrent. Reference Johnson, Lavergne and Skinner17 Differing from IDSA guidelines, NYULH guidelines recommend a 10-day duration of vancomycin as first-line therapy over fidaxomicin for initial nonfulminant CDI episodes, and treatment may be extended in patients with slow clinical improvement. Recommendations for fulminant CDI are consistent with IDSA guidelines. Reference Johnson, Lavergne and Skinner17 Additionally, discontinuation of all nonessential antibiotics is recommended, but no guidance is provided if this cannot be done due to accompanying infections. For prevention of recurrent episodes of CDI, patients at NYULH with a prior history of CDI who require exposure to systemic antibotics receive secondary prophylaxis with vancomycin 125 mg every 12 hours during antibiotic treatment and for 5 additional days after discontinuation of antibiotics.
Data collection and definitions
A list of patients hospitalized with CDI during the study period was obtained from an infection prevention and control (IPC) database of C. difficile events reported to the National Healthcare Safety Network (NHSN). This list was then matched to a list of patients who received concomitant antibiotics during concurrent admission, obtained from an Epic Clarity Reporting Database of patients on antibiotics. Finally, manual chart review of the electronic health record was utilized to further evaluate for inclusion and collect pertinent data. Baseline demographics, past medical history, risk factors for CDI such as acid suppressive therapy and immunocompromising conditions or medications, and CDI disease characteristics, including location of onset, severity, and clinical or laboratory markers at diagnosis were recorded. Location of CDI onset was defined consistent with NHSN definitions, stratified by community-onset, community-onset healthcare-facility associated, and hospital onset. 18 Individual categories of concomitant antibiotics received for at least 24 hours were collected and stratified based on risk of causing or exacerbating CDI, as previously categorized. Reference Mullane, Miller and Weiss8 All treatments for CDI were captured, including vancomycin duration while admitted and after discharge, vancomycin dosing strategy, and use of adjunctive therapies including intravenous metronidazole, vancomycin retention enemas, tigecycline, and intravenous immunoglobulins. Dosing strategy was categorized as either treatment (125, 250, or 500 mg every 6 hours) or prophylaxis (125 mg every 12 hours), and tapered dosing was consistent with IDSA guideline recommendations. Reference Johnson, Lavergne and Skinner17 Length of vancomycin therapy was categorized as either standard duration (10–14 days of treatment) or prolonged duration (>14 days of treatment).
Outcomes
The primary outcome was recurrence of CDI within 8 weeks of CDI treatment completion. Secondary outcomes included CDI recurrence, isolation of vancomycin-resistant Enterococcus (VRE), and mortality within 6 months of CDI treatment completion. Recurrence of CDI was defined by either retest (repeat positive PCR and clinical symptoms) or empiric retreatment (receipt of oral vancomycin or fidaxomicin treatment in the absence of a positive PCR test) because our institutional guidelines restrict the ordering of a repeat PCR within 30 days of a positive result. Isolation of VRE was captured by growth in clinical cultures or surveillance VRE stool screens recommended by hospital IPC policies for unique populations. Independent risk factors for CDI recurrence at 8 weeks were explored in a secondary analysis.
Statistical analysis
Categorical data are presented as frequencies, and continuous data are presented as medians and interquartile ranges (IQRs) for the full cohort, the standard-duration group, and the prolonged-duration group. Characteristics of patients receiving standard-duration treatment versus prolonged-duration treatment were compared using the χ 2 test and the Fisher exact test for categorical data and the Mann-Whitney U test for continuous data. Statistical significance was defined by a 2-sided P < .05. To identify risk factors for CDI recurrence within 8 weeks, a univariate analysis was conducted comparing patients who experienced recurrence to those who did not. To reduce omitted-variable bias, any patient, disease, or treatment characteristic with P ≤ .10 on univariate analysis was subsequently evaluated on multivariate analysis to determine independent predictors of CDI recurrence. A Kaplan-Meier analysis of time to CDI recurrence according to treatment group was conducted using a log-rank test. Time at risk began with the day following completion of vancomycin treatment. Statistical analyses were conducted with SPSS Statistics version 28 software (IBM, Armonk, NY). 19
Results
In total, 1,350 patients were screened for inclusion during the study period, of which 1,132 patients were excluded (Fig. 1). The primary reason for exclusion was lack of overlap between systemic antibiotics and oral vancomycin for >72 hours (n = 964). Among the 218 patients included, 78 (36%) received a standard duration and 140 (64%) received a prolonged duration. Patients in the standard-duration and prolonged-duration groups received vancomycin treatment for 13 (IQR, 11–14) days and 20 (IQR, 16–26) days, respectively (P < .001). Only 18 patients (8%) received vancomycin for 10 days.
Patient screening and inclusion. Note. ABX, systemic antibiotics; VAN, oral vancomycin; CDI, Clostridiodes difficile infection; TX, treatment.

Patient demographics and CDI characteristics are reported in Table 1. Most of the cohort was male (61%) with a median age of 65 years (IQR, 54–72) and a median Charlson comorbidity index of 4 (IQR, 2–6). Reference Quan, Sundararajan and Halfon20 Also, 52% of the cohort was immunocompromised, characterized by solid organ or bone marrow transplant, human immunodeficiency virus (HIV), and/or immunosuppressant medication use, 41% had diabetes and 8% had end-stage renal disease requiring hemodialysis. There were no significant differences in past medical history between the groups. Most CDI cases were hospital-acquired (54%) and were classified as nonsevere (39%), followed by severe (36%) and fulminant (25%). Community-onset CDI was more prevalent in the standard-duration group (44% vs 30%; P = .044). The hypervirulent NAP1/B1/027 strain was detected in 22 patients (10%) in the total cohort, which was similar between groups. Intensive care unit (ICU) admission at any time during oral vancomycin treatment was required in 32% of patients in each group. An infectious diseases specialist was consulted in 69% of patients in the prolonged-duration group compared to 54% of patients in the standard-duration group (P = .023).
Patient Demographics and CDI Characteristics

Note. CDI, Clostridiodes difficile infection; WBC, white blood cell; CO-HFCA, community-onset, healthcare-facility associated.
a Units unless otherwise specified.
b Immunosuppressants included antineoplastics, immunotherapy, and prednisone equivalents ≥20 mg for at least 2 weeks.
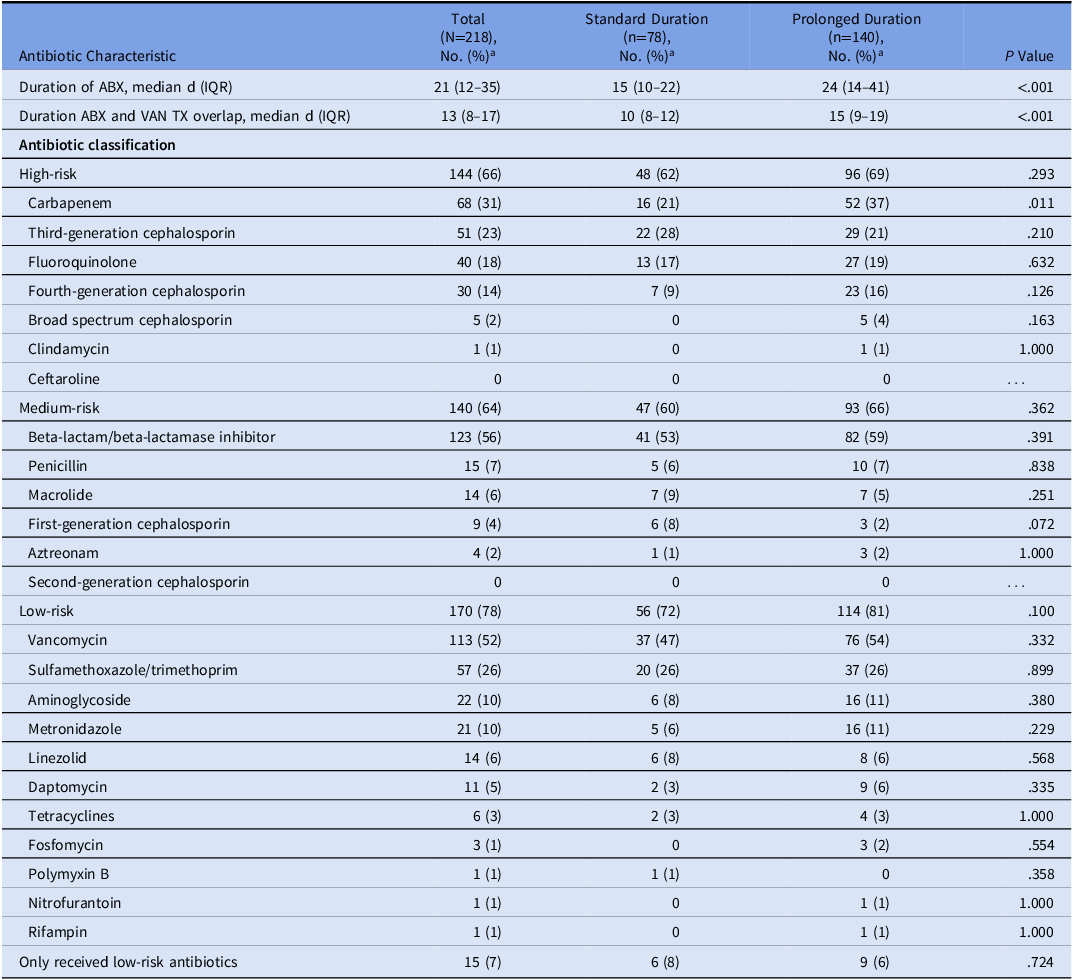
Systemic antibiotic characteristics are outlined in Table 2. Patients in the prolonged-duration group received concurrent antibiotics (overlapping with vancomycin treatment) for 15 days (IQR, 9–19), compared to 10 days (IQR, 8–12) in the standard-duration group (P < .001). Receipt of any high-risk antibiotics occurred in 66% of the cohort, with more carbapenem use in patients who received a prolonged duration of treatment (37% vs 21%; P = .011). Receipt of only low-risk antibiotics was uncommon overall (7%).
Systemic Antibiotic Characteristics

Note. ABX, systemic antibiotics; VAN, oral vancomycin; TX, treatment (VAN 125–500 mg every 6 h).
a Units unless otherwise specified.
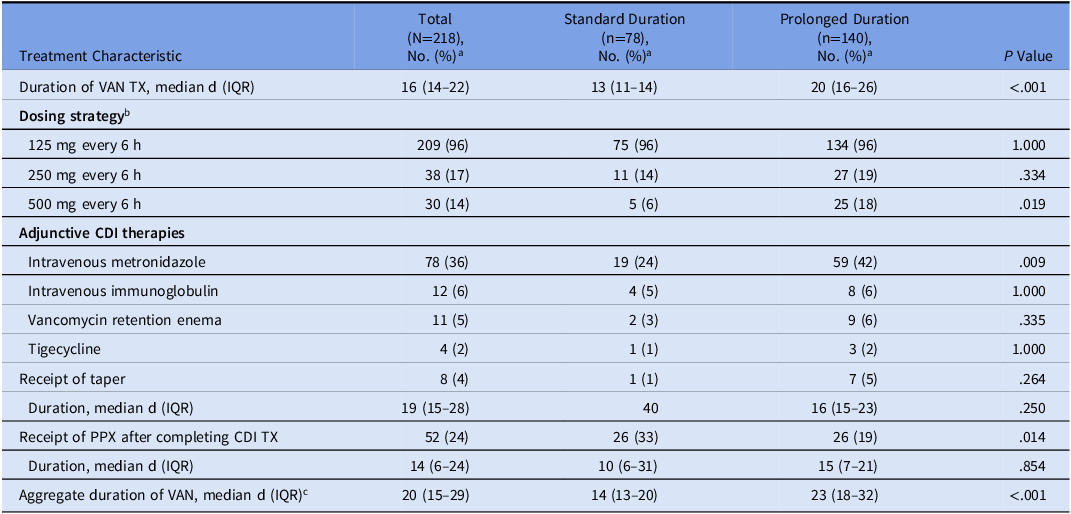
Table 3 summarizes CDI treatment characteristics. Although the vancomycin dosing strategy of 125 mg every 6 hours was used most frequently, 51 patients (23%) had at least 1 change in their dosing regimen during vancomycin treatment. The prolonged-duration group more commonly received vancomycin 500 mg every 6 hours (18% vs 6%; P = .019) and adjunctive IV metronidazole (42% vs 24%; P = .009). Vancomycin dose tapers and other CDI-active therapies were used infrequently. Upon completion of vancomycin treatment, step-down to prophylaxis occurred in 33% of patients in the standard-duration group compared to 19% in the prolonged-duration group (P = .014). Aggregate duration of vancomycin, which includes treatment, prophylaxis, and taper days, was significantly longer in the prolonged-duration group: 23 days (IQR, 18–32) versus 14 days (IQR, 13–20) (P < .001). Vancomycin prescribing relative to systemic antibiotic completion is displayed in Figure 2. Vancomycin was discontinued prior to antibiotics in 15 patients (7%), on the same day as antibiotics in 20 patients (9%), and after antibiotics in 183 patients (84%). Among patients who had vancomycin continued beyond antibiotic completion, most patients continued treatment dose (147 of 183, 80%) for a median of 6 days (IQR, 5–14) or prophylactic dose (30 of 183, 16%) for a median of 6 days (IQR, 5–22).
CDI Treatment Characteristics

Note. CDI, Clostridiodes difficile infection; VAN, oral vancomycin; TX, treatment (VAN 125–500 mg every 6 h); PPX, secondary prophylaxis (VAN 125 mg every 12 h).
a All values are reported as no. (%) unless otherwise specified.
b 51 (23%) patients had at least 1 change in their VAN TX dosing regimen.
c Aggregate duration included combined days of TX, PPX, and taper.
Prescribing patterns of VAN relative to the end date of ABX. Note. ABX, systemic antibiotics; VAN, oral vancomycin; TX, treatment (VAN 125–500 mg every 6 hours); PPX: secondary prophylaxis (VAN 125 mg every 12 hours).

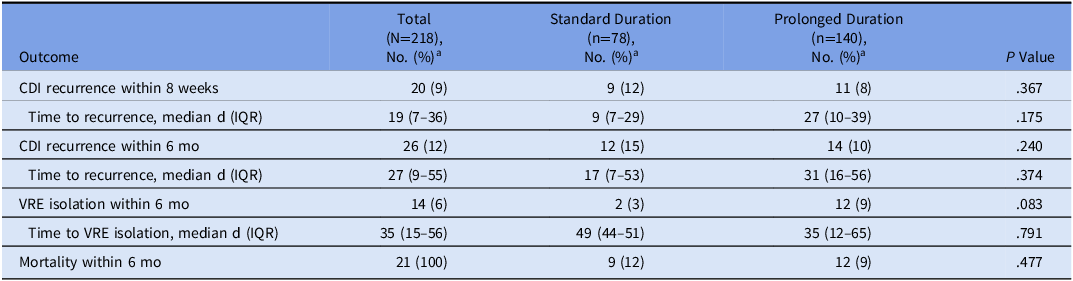
Outcome data are presented in Table 4. The primary outcome of CDI recurrence at 8 weeks occurred in 20 patients (9%) overall, 9 patients (12%) in the standard-duration group and 11 patients (8%) in the prolonged-duration group (P = .367). Among the 20 recurrences, 13 (65%) were confirmed by PCR (4 standard-duration and 9 prolonged-duration) and the remaining 7 were retreated in the absence of a positive PCR test (2 standard-duration and 5 prolonged-duration). CDI recurrence at 8 weeks was higher in patients with the NAP1/B1/027 strain than in patients with the standard strain: 6 of 22 (27%) versus 14 of 196 (7%), P = .008. When evaluating vancomycin prescribing relative to systemic antibiotic completion, there was no difference in CDI recurrence at 8 weeks among patients who continued vancomycin treatment after antibiotic discontinuation compared to vancomycin prophylaxis or taper after antibiotic discontinuation: 14 of 147 (10%) versus 2 of 36 (6%), P = .742. At 6 months, 26 patients (12%) had CDI recurrence, which was also similar between groups. We detected a numerically higher incidence of VRE isolated in patients who received prolonged duration; however, this was not statistically significant: 3% standard-duration versus 9% prolonged-duration (P = .083). All-cause mortality was 10% at 6 months: 12% standard-duration versus 9% prolonged-duration (P = .477).
Outcomes

Note. CDI: Clostridiodes difficile infection; VRE: vancomycin-resistant Enterococcus
a Units unless otherwise specified.
A Kaplan-Meier analysis of time to 8-week recurrence did not demonstrate a significant difference based on oral vancomycin treatment duration (log rank test P = .324) (Fig. 3). In the multivariable logistic regression model, independent predictors of recurrence at 8 weeks included discontinuation of vancomycin (any dose: treatment, prophylaxis, or taper) prior to systemic antibiotic completion (OR, 4.8; 95% CI, 1.3–18.1), NAP1/B1/027 strain (OR, 4.7; 95% CI, 1.5–14.5), and circulatory shock (OR, 3.5; 95% CI, 1.2–0.1) (Supplementary Table 1 online). Duration of vancomycin treatment and aggregate duration of vancomycin did not impact risk of recurrence.
Recurrence-free 8-week survival curve. Cumulative proportion of patients with recurrence estimated using a Kaplan-Meier survival model and compared using the log-rank test (P = .324). Time at risk began with the day following completion of VAN TX. Note. VAN, oral vancomycin; TX, treatment (VAN 125–500 mg every 6 h).

Discussion
In our analysis of a heterogeneous cohort of hospitalized patients receiving both oral vancomycin for CDI and concurrent systemic antibiotics for accompanying infections, vancomycin treatment was commonly extended beyond 14 days, but doing so did not reduce the risk of CDI recurrence within 8 weeks. Despite the IDSA guideline recommending a 10-day course of therapy for initial CDI episodes, real-world experience suggests that adherence to this guidance is low for patients who require concomitant antibiotics. In our study, only 36% of patients received CDI therapy for ≤14 days, which is similar to prior studies reporting that only 43%–47% of hospitalized patients received a standard treatment duration when also receiving concomitant antibiotics. Reference Keats, Stitt and Chastain14–Reference Kaki, Brooks, Main, Jayaratne and Mertz16 The median duration of vancomycin treatment in patients who had therapy prolonged was 20 days (IQR, 16–26), which is comparable to previously reported extended durations of 24–26 days. Reference Keats, Stitt and Chastain14,Reference Rajakumar, Jaber, Ali, Rennert-May and Sabuda15 Given the lack of available literature and treatment guidance from the IDSA for this population, we hypothesized reasons that clinicians may opt to prolong vancomycin treatment for CDI.
We detected notable differences between patients who received vancomycin for a standard versus a prolonged duration that may have affected prescribing decisions. Patients who received a prolonged duration appeared to have a higher severity of illness, evidenced by longer durations of overlapping antibiotics, more carbapenem use, and greater use of combination therapy directed toward CDI. Additionally, infectious disease service consultations were more commonly obtained in the prolonged-duration group, which may suggest more complex infections warranting specialist consultation. Likewise, these specialists may have directly influenced the decision to prolong vancomycin treatment, recognizing microbiome disruption as critical to disease pathogenesis and evolution. In contrast, patients who received a standard duration more often had community-acquired CDI, which has been associated with lower CDI severity and lower mortality. Reference Reveles, Pugh and Lawson21 Therefore, patient acuity and duration of concomitant antibiotics were likely the primary determinants of duration of vancomycin treatment.
The rates of CDI recurrence after vancomycin treatment completion in our cohort were low: 9% within 8 weeks and 12% within 6 months. Although recurrence was numerically lower at both time points in patients who received prolonged treatment, there was no significant difference compared to the standard-duration group. Our recurrence rates were lower than published studies evaluating patients with CDI requiring concomitant antibiotics, with rates reported to be 21% within 8 weeks and 16%–29% within 6 months. Reference Keats, Stitt and Chastain14–Reference Kaki, Brooks, Main, Jayaratne and Mertz16 There may be several reasons for this difference. Oral metronidazole was used for CDI in 30%–70% of patients included in prior studies, which has been demonstrated to be inferior to vancomycin for CDI in terms of clinical cure and recurrence. Reference Keats, Stitt and Chastain14–Reference Kaki, Brooks, Main, Jayaratne and Mertz16,Reference Di, Bai and Zhang22 Additionally, we evaluated only initial CDI episodes, whereas prior studies included patients with recurrent episodes who were at a significantly higher risk of subsequent recurrences. Reference Feuerstadt, Theriault and Tillotson3,Reference Song and Kim6 Lastly, our institution recommends secondary prophylaxis for all patients with a history of CDI requiring exposure to systemic antibiotics, a strategy that markedly decreases disease recurrence. Reference Maraolo, Mazzitelli and Zappulo23 Notably, the rate of VRE isolation within 6 months of vancomycin treatment completion in our cohort was numerically higher in patients who received prolonged vancomycin treatment, a finding consistent with prior studies and abstracts. Reference Rajakumar, Jaber, Ali, Rennert-May and Sabuda15,Reference Kaki, Brooks, Main, Jayaratne and Mertz16,Reference Johnson, Doll and Snider24 Indeed, prolonged vancomycin tapers have been demonstrated to maintain VRE colonization compared to shorter courses due to persistent disruption of intestinal microbiota. Reference Tomas, Mana and Wilson25 Strategies to decrease CDI recurrence must be balanced with the risk of VRE emergence, a well-documented consequence of vancomycin therapy. Reference Al-Nassir, Sethi, Li, Pultz, Riggs and Donskey26,Reference Sethi, Al-Nassir, Nerandzic and Donskey27
In our study, discontinuation of oral vancomycin prior to the completion of systemic antibiotics independently increased the risk of disease recurrence 5-fold. Thus, vancomycin prescribing relative to systemic antibiotics may implicate CDI recurrence to a greater extent than total vancomycin duration alone. This important finding questions the utility of continuing vancomycin treatment beyond a 10-day course and whether step-down to vancomycin prophylaxis may be a valuable strategy to minimize total drug exposure and disruption to colonic flora. If patients with CDI have clinical resolution of diarrhea at day 10 but require ongoing concomitant antibiotics, our data suggest that vancomycin therapy should be continued. Because gastrointestinal transit time affects the fecal pharmacokinetics of vancomycin, vancomycin administered less frequently (ie, every 12 or 24 hours) may provide enough protection if CDI diarrhea has resolved. Reference Gonzales, Pepin and Frost28 However, use of secondary prophylaxis in this population remains in equipoise and requires further study. Notably, prolonging vancomycin has been shown to delay recovery of indigenous microbiota responsible for colonization resistance to C. difficile compared to short-course vancomycin or fidaxomicin. Reference Tomas, Mana and Wilson25 Future studies are needed to compare CDI prevention strategies after treatment completion in patients requiring continuation of antibiotics.
This study had several limitations. This small, single-center retrospective analysis depended on the accuracy of documentation in the electronic health record. Our study groups were well-balanced with respect to characteristics that most notably affect CDI recurrence, but we cannot exclude the possibility of other confounding variables that may have influenced our results. Our institution’s practice of CDI testing via PCR without confirmatory EIA may have led to an overdiagnosis of events; however, diagnostic stewardship practices are in place to limit these occurrences. Due to the retrospective study design and inconsistent documentation, our ability to capture time to resolution of diarrhea was limited, which may have affected vancomycin treatment duration. Additionally, we hypothesized reasons that vancomycin treatment was prolonged, but we were unable to determine the exact rationale without querying prescribers. Step-down to vancomycin prophylaxis upon completion of vancomycin treatment was prevalent (24%), which may have affected the recurrence rate in our overall cohort. Also, we could not capture recurrent CDI events that may have occurred outside of the NYULH system. Lastly, we were unable to statistically power our analysis due to the anticipated small difference in the rate of the primary outcome between groups, based on prior data. Reference Keats, Stitt and Chastain14–Reference Kaki, Brooks, Main, Jayaratne and Mertz16,Reference Johnson, Doll and Snider24
In conclusion, we did not identify evidence to support prolonging the duration of oral vancomycin treatment beyond 10–14 days in all hospitalized patients with CDI requiring concomitant systemic antibiotics for accompanying infections. On the contrary, we found that discontinuation of any dosing regimen of vancomycin prior to antibiotic completion independently increased the risk of CDI recurrence at 8 weeks. Future prospective trials are warranted to explore these findings and to identify alternative risk reduction strategies.
Supplementary material
To view supplementary material for this article, please visit https://doi.org/10.1017/ice.2024.4
Acknowledgments
Financial support
No financial support was provided relevant to this article.
Competing interests
All authors report no conflicts of interest relevant to this article.