Kawasaki disease is the leading cause of acquired heart disease in the developed world.Reference Taubert, Rowley and Shulman 1 , Reference Newburger, Takahashi and Gerber 2 It is an acute, systemic vasculitis of uncertain aetiology, occurring predominantly in infants and children younger than 5 years of age.Reference Kawasaki, Kosaki, Okawa, Shigematsu and Yanagawa 3 Coronary artery aneurysms or ectasia develop in 15–25% of Kawasaki disease patients, during its acute stage, and may lead to myocardial infarction, sudden death, or chronic coronary insufficiency.Reference Iemura, Ishii, Sugimura, Akagi and Kato 4 In addition to causing acute coronary artery aneurysm and stenosis, Kawasaki disease has also been shown to have deleterious effects on coronary artery function years after the acute presentation. Another issue that raises concerns is vascular abnormalities other than those involving coronary arteries. Several reports indicated abnormal changes in the systemic vascular physiology in Kawasaki disease patients with persistent or regressed coronary artery lesions, including increased wall thickness and decreased distensibility of the carotid arteries,Reference Noto, Okada and Yamasuge 5 , Reference Cheung, Wong and Ho 6 and increased stiffness of central and peripheral arteries.Reference Cheung, Yung, Tam, Ho and Chau 7 Histological and pathological studies have identified aneurysms at other vascular tree sites, involving mainly small- to medium-sized vessels, including the femoral, iliac, renal, axillary, and brachial arteries.Reference Amano, Hazama and Hamashima 8
Although persistent coronary artery aneurysm only occurs in a minority of children with acute Kawasaki disease,Reference Singh, Bansal, Gupta, Kumar and Mittal 9 considerable attention has been focused in the past few years on the long-term outcome of this subgroup, mainly because of concerns regarding increased risk for morbidity and mortality, late after resolution of acute Kawasaki disease. Arterial function has been assessed in multiple studies in which the authors evaluated myocardial and coronary flow reserve with angiography,Reference Iemura, Ishii, Sugimura, Akagi and Kato 4 , Reference Suzuki, Yamagishi and Kimura 10 – Reference Yamakawa, Ishii and Sugimura 12 invasive flow measurements,Reference Hamaoka, Onouchi and Ohmochi 13 – Reference Mitani, Okuda and Shimpo 15 positron emission tomography,Reference Hauser, Bengel and Kuehn 16 , Reference Muzik, Paridon, Singh, Morrow, Dayanikli and Di Carli 17 and transthoracic Doppler ultrasound of the coronary arteries.Reference Cicala, Galderisi and Grieco 18 Abnormalities have been observed in both endothelial-mediated and endothelial-independent coronary artery vasodilation. In spite of the main focus on Kawasaki disease patients with coronary artery involvement, a small number of studies have also shown that even in patients with a history of Kawasaki disease without coronary artery dilation or ischaemia coronary flow reserve is impaired,Reference Suzuki, Yamagishi and Kimura 10 , Reference Hauser, Bengel and Kuehn 16 – Reference Cicala, Galderisi and Grieco 18 although conflicting results showed no difference from normal control subjects.Reference Iemura, Ishii, Sugimura, Akagi and Kato 4 , Reference Sugimura, Kato, Inoue, Takagi, Fukuda and Sato 11 , Reference Yamakawa, Ishii and Sugimura 12 These results, and the decreased number of new patients with Kawasaki disease with coronary artery aneurysm, revived the research interest in diagnostic assays for the assessment of endothelium dysfunction in children with Kawasaki disease without coronary artery aneurysm.Reference Mitani, Okuda and Shimpo 15 , Reference Ghelani, Singh and Manojkumar 19
In the healthy state, the endothelium produces a number of factors, including nitric oxide, that are essential for maintaining vascular homoeostasis. Several risk factors damage endothelial cells, lowering nitric oxide bioavailability. An impaired endothelial function has been associated with an increased risk of cardiovascular events. In spite of its relevance, endothelial function assessment has not yet been incorporated into routine risk stratification of patients with Kawasaki disease, mainly because of technical limitations.Reference Patvardhan, Heffernan, Ruan, Soffler, Karas and Kuvin 20 – Reference Kuvin and Karas 22 The use of novel digital tonometry device to measure endothelial function offers the possibility of an easily performed, rapid assessment of microvascular function, overcoming these limitations. The Endo-PAT device (Itamar Medical, Caesarea, Israel) is a commercially available system, consisting of a fingertip plethysmograph capable of sensing volume changes in the digit with each arterial pulsation. It has been validated in adult population to assess microvascular function,Reference Kuvin, Patel and Sliney 23 but its use among children is scarce.Reference Selamet Tierney, Newburger and Gauvreau 24 , Reference Haller, Stein and Shuster 25 Therefore, our aim was to evaluate for endothelial dysfunction in children and young adults as a long-term complication after Kawasaki disease using the Endo-PAT, comparing the results with matched normal controls.
Methods
Study population
The patients, selected from our outpatient clinic, were all aged >11 years and have had a diagnosis of acute Kawasaki disease for >5 years previously, diagnosed by standard criteria.Reference Newburger, Takahashi and Gerber 2 , Reference Ayusawa, Sonobe and Uemura 26 Patients were excluded if they have had coronary artery lesions during the acute Kawasaki disease stage, or if they had potentially confounding risk factors for endothelial damage, such as smoking, elevated LDL cholesterol, hypertension, diabetes mellitus, or a family history of premature cardiovascular disease, or if they were taking vasoactive medication. No other selection criteria were applied. In all, 19 patients (12 males) aged 15–27 years (mean age, 21 ± 6 years) were studied. Management of the acute Kawasaki disease was determined by the patient's own physicians. In addition, 16 healthy age- and sex-matched control subjects (9 males, mean age, 21 ± 6 years) were studied. These subjects were normal individuals without risk factors for endothelial damage as listed above and were recruited from family and friends of hospital staff. None were taking medications or had a history of significant illness.
Study protocol
A history was obtained from all subjects, and a physical examination was performed, including supine blood pressure. All subjects had an electrocardiogram and an echocardiogram performed. The medical records of the Kawasaki disease patients were reviewed for details of their acute illness. Endothelial function was assessed through peripheral arterial tonometry, as described below; the peripheral arterial tonometry study was repeated 1 month later, in order to assess the reproducibility of the data.
Peripheral arterial tonometry
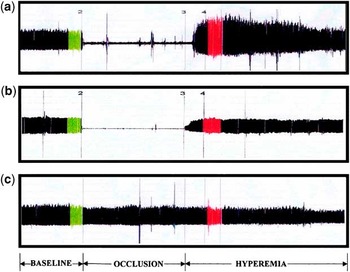
Endothelial function tests were performed in a dedicated laboratory, in a quiet environment, with controlled temperature and humidity, during the morning period, between 9:00 and 12:00 am, at least two hours after a light breakfast without ingestion of caffeine or other xanthines. Pulse wave amplitude was assessed before and during reactive hyperaemia by peripheral arterial tonometry (Endo-PAT 2000, Itamar Medical Limited, Israel), as previously described in detail (Fig 1).Reference Nohria, Gerhard-Herman, Creager, Hurley, Mitra and Ganz 21 , Reference Kuvin, Patel and Sliney 23 In brief, baseline pulse wave amplitude data were collected using plethysmographic finger cuffs, placed on the index finger of both hands, for a period of 5 minutes. An ischaemic stimulus was induced by cuff occlusion, that is, inflation of a brachial cuff to a supra-systolic pressure of 200 mmHg for 5 minutes, and the pulse wave amplitude – reactive hyperaemia index was calculated as the ratio of the average pulse wave amplitude value, over a 1-minute epoch starting after cuff release, to the pre-occlusion baseline pulse wave amplitude value. The augmentation index, a measure of arterial stiffness, was also computed, as the difference from the two systolic peaks, derived from the baseline period's mean peripheral arterial tonometry waveform ensemble. A reactive hyperaemia index cut-off value of 1.67 was used for diagnosing endothelial dysfunction, as previously defined by Bonetti et al.Reference Bonetti, Pumper and Higano 27
( a and b ) Pulse wave amplitude recordings with peripheral arterial tonometry at baseline (green) during supra-systolic cuff occlusion and during reactive hyperaemia (red) in the ischaemic arm are demonstrated. ( c ) Peripheral arterial tonometry recordings from the contralateral finger not undergoing reactive hyperaemia testing are shown. ( a ) Healthy individual with no cardiovascular risk factors showing a steady-state peripheral arterial tonometry signal (baseline), complete disappearance of the signal during cuff inflation (occlusion), followed by an increased peripheral arterial tonometry signal during recovery (hyperaemia). ( b ) Individual with coronary artery disease showing a blunted finger peripheral arterial tonometry response during reactive hyperaemia. ( c ) Peripheral arterial tonometry recording from the contralateral finger in the same patient (reproduced with permission from Kuvin et al. Assessment of peripheral vascular endothelial function with finger arterial pulse wave amplitude, Am Heart J, 2003; 146: 168–174).

Statistical analysis
Continuous variables are expressed as mean ± standard deviation, unless otherwise specified. Categorical variables are given as frequencies and percentage of patients. Normality of the distributions of the continuous variables was analysed with the Kolmogorov–Smirnov test. Student's t-test was used to assess all paired data in the same group. Comparisons between groups were made using the Mann–Whitney U-test. The chi-square test was used for categorical variables. A value of p < 0.05 was considered statistically significant. Data were analysed using SPSS software version 18 (IBM Corporation, United States of America).
Results
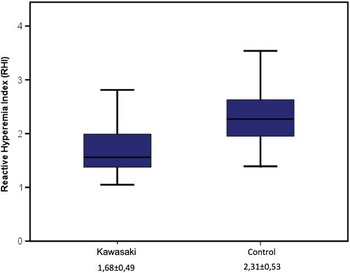
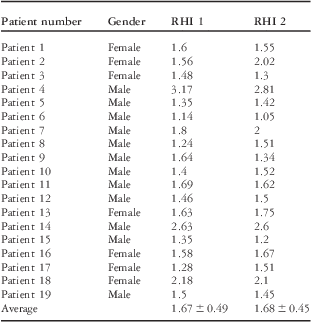
Table 1 summarises the patient characteristics of each group. Groups were comparable in terms of gender distribution (women: 37% versus 43%), age (21 ± 6 years), and body surface mass (22.8). All subjects were well, with normal clinical and electrocardiogram evaluation. The Kawasaki disease patients had normal left ventricular function and normal coronary arteries on echocardiography. The endothelium function studies disclosed endothelium dysfunction in the majority (68%) of Kawasaki disease patients, when compared with a significantly lower percentage of control subjects (12%). There were significant group differences in pulse wave amplitude-derived reactive hyperaemia index, with Kawasaki disease patients having a significantly lower reactive hyperaemia index when compared with the control group (1.67 ± 0.49 versus 2.31 ± 0.53; p = 0.001, Fig 2). Pulse wave amplitude-derived augmentation index was similar in both groups (−10 ± 7 versus −11 ± 5; p > 0.005). The reactive hyperaemia index values were reproducible; no statistically significant changes were found at the 1-month Endo-PAT retest (Table 2; p = 0.7856).
Demographic characteristics of the subjects.

Values shown are mean ± SD
Pulse wave amplitude-derived reactive hyperaemia index in Kawasaki disease and control groups. The reactive hyperaemia index values were significantly lower in the Kawasaki disease patients than those in the male control subjects.

RHI values for the Kawasaki disease group.

RHI = reactive hyperaemia index
Values shown are mean ± SD. RHI 1 – basal reactive hyperaemia index value; RHI 2 –reactive hyperaemia index value, 1 month after the first test.
Discussion
This study has shown that endothelial dysfunction is a long-term complication in patients after Kawasaki disease, even in patients without detectable coronary involvement during the acute illness. This is the first study, to our knowledge, to show microvascular endothelial dysfunction in Kawasaki disease patients, as all the previous studies assessed the arterial and endothelial function of large- and medium-sized vessels. We have also demonstrated that peripheral arterial tonometry is a feasible, safe, and reproducible technique, in the child population, to study endothelial function.
Kawasaki disease occurs worldwide in both endemic and community-based epidemic forms, in children of all races. It is a medium-vessel vasculitis with predominant involvement of the coronary arteries. The search for an aetiologic agent has been wide ranging. Some investigators believe that an infectious agent triggers a typical immune response, in phenotypically susceptible individuals, resulting in the clinical manifestations of the disease. Regardless of the initiating event, Kawasaki disease is accompanied by significant derangements in the immunoregulatory systemReference Duong, Silverman, Bissessar and Yeung 28 – Reference Wang, Wu, Liu, Kuo and Yang 30 that lead to coronary inflammation and coronary artery abnormalities, dilatation, aneurysm formation, and giant aneurysms in some patients. Endothelial cell damage appears to occur as a result of this increased immune activity.Reference Leung 31 In addition to causing coronary artery aneurysm and stenoses, Kawasaki disease has also been shown to have deleterious effects on coronary artery function years after the acute presentation. In patients with persistent coronary artery aneurysm, coronary artery function has repeatedly been shown to be impaired compared with control subjects.Reference Iemura, Ishii, Sugimura, Akagi and Kato 4 , Reference Sugimura, Kato, Inoue, Takagi, Fukuda and Sato 11 , Reference Yamakawa, Ishii and Sugimura 12 , Reference Burns, Shike, Gordon, Malhotra, Schoenwetter and Kawasaki 32 , Reference Kato, Sugimura and Akagi 33 Coronary flow reserve is also abnormal in patients with a history of transiently dilated coronary arteries.Reference Iemura, Ishii, Sugimura, Akagi and Kato 4 , Reference Furuyama, Odagawa and Katoh 34 Even in patients with a history of Kawasaki disease without antecedent coronary artery dilation or ischaemia, impaired coronary flow reserve has been observed.Reference Suzuki, Yamagishi and Kimura 10 , Reference Hamaoka, Onouchi and Ohmochi 13 , Reference Hauser, Bengel and Kuehn 16 , Reference Furuyama, Odagawa and Katoh 34 The inflammatory insult associated with acute Kawasaki disease has the potential to affect not only the coronary arteries, but also all components of the cardiovascular system. Our finding of late functional abnormalities, of the endothelial-dependent microvascular relaxation, in the majority of the Kawasaki disease group in our study may be a consequence of this systemic inflammation. These findings raise concerns that the risk of late cardiovascular complications may not be confined to those patients with detectable early coronary artery aneurysm.
Although the first study of this kind was conducted more than a decade ago, only recently the interest in this area was revived, and a number of similar studies have appeared in the literature. Most of these studies were conducted in children with Kawasaki disease having coronary artery aneurysm. Our results are inline with the one from Dhillon et al,Reference Dhillon, Clarkson and Donald 35 which demonstrated abnormal flow-mediated dilation of the brachial artery in 20 male subjects, who were studied 5–17 years after the onset of Kawasaki disease, irrespective of whether they had developed aneurysms during the acute phase. Deng et alReference Deng, Xiang, Chang and Li 36 and Dalla Pozza et alReference Dalla Pozza, Bechtold, Urschel, Kozlik-Feldmann and Netz 37 have reported endothelial dysfunction in a small number of children with Kawasaki disease, but without coronary artery aneurysms. Our study adds evidence to these findings and suggests that the occurrence of Kawasaki disease may have lifelong consequences even when there is no discernible coronary artery involvement. The issue, however, is rather contentious. In studies of Japanese subjects, of comparable characteristics, only the ones who developed coronary artery aneurysms during the acute stage of Kawasaki disease had abnormal flow-mediated dilation.Reference Kadono, Sugiyama and Hoshiai 38 , Reference Ikemoto, Ogino, Teraguchi and Kobayashi 39 The authors of a recent studyReference McCrindle, McIntyre, Kim, Lin and Adeli 40 of 52 Canadian Kawasaki disease patients concluded that there was no evidence of long-term endothelial cell dysfunction late after Kawasaki disease. It is unclear whether these conflicting results are best explained by methodological issues or genetic differences of the populations studied.
Children with Kawasaki disease, with or without coronary artery lesions, may have a more adverse cardiovascular risk profile. Whether this is a cause or a consequence of an abnormal endothelial function has not yet been assessed.Reference McCrindle, McIntyre, Kim, Lin and Adeli 40 , Reference Noto, Okada and Karasawa 41 What is noteworthy is the fact that, in our sample, almost 70% of our Kawasaki disease group had an abnormal endothelial function, when compared with only 12% of the control group subjects.
Our findings may have surveillance and therapeutic implications for the Kawasaki disease patients who had no coronary artery involvement during the acute disease. In the current management practices, long-term follow-up of these patients is seldom undertaken. Our results suggest that children with Kawasaki disease may have long-term sequelae, even when there is no overt coronary artery involvement in the acute stage of the disease. Affected children should therefore be kept on long-term follow-up, and instructed to avoid known cardiovascular risk factors, such as sedentary lifestyle, overweight, high-lipid and -caloric meals, alcohol or tobacco use. Prospective work is required, in a larger population, to assess the potential benefit of therapeutic approaches to these patients. The availability of newer, simple, and reproducible non-invasive techniques will allow a more rigorous follow-up of the endothelial function in these patients, allowing a close monitoring of the therapeutical effectiveness.
Acknowledgement
The authors thank Technician Lurdes Medroa for her contribution performing the endopat studies and Eduardo da Cruz, MD, PHD, for his scientific support.