The study of practice variation in the care of children with CHD is a rapidly evolving field. To date, children born with hypoplastic left heart syndrome comprise one of the most complex and studied populations. The Pediatric Heart Network-funded Single Ventricle Reconstruction Trial randomly assigned 555 patients with hypoplastic left heart syndrome and other related single right ventricular anomalies to one of two shunt strategies during the Norwood procedure. Following randomisation, patients received the centre’s usual perioperative standard of care.Reference Ohye, Sleeper and Mahony1 The Single Ventricle Reconstruction Extension Study followed transplant-free survivors to age 6 years.Reference Newburger, Sleeper and Gaynor2 We previously leveraged these databases and found that practices surrounding both the Norwood and stage II procedures varied widely across centres participating in the Single Ventricle Reconstruction Trial for nearly every aspect of perioperative care.Reference Eckhauser, Pasquali and Ravishankar3, Reference Pasquali, Ohye and Lu4 These studies, while informative and clinically relevant, were purely descriptive in nature, and we were unable to show how practice variation affected clinical outcomes in this single ventricle population. In this study, we analysed the Single Ventricle Reconstruction data sets and hypothesised that similar practice variation occurred in the Fontan perioperative period. We also sought to generate hypotheses for specific centre-level variables that affected two common morbidities: total length of stay (length of stay) and prolonged pleural effusion.
Materials and methods
Population
Patients with hypoplastic left heart syndrome or related single, morphologic right ventricular anomaly, and a planned Norwood procedure were enrolled in the Single Ventricle Reconstruction Trial between May 2005 and July 2008. Eligibility criteria and methods for the Single Ventricle Reconstruction Trial were previously published.Reference Ohye, Gaynor and Ghanayem5 All data were collected at each centre on study forms and then compiled and audited in one central database. The Institutional Review Board of each centre approved the Single Ventricle Reconstruction studies, and parents/guardians provided informed consent.
Data collection
Detailed information regarding preoperative, operative, and postoperative care was prospectively recorded on standardised case report forms. All patients received care according to the centre’s usual practice. The operative period reflected only direct time spent in the operating room. The postoperative period included the interval between returning from surgery and hospital discharge after the Fontan procedure.
Preoperative variables included age and weight at surgery, presence of identifiable genetic syndrome or abnormalities, associated anatomic diagnoses, number of pre-Fontan catheterizations, and type of interventions. The perioperative/operative variables included type of stage II procedure, type of Fontan, fenestration status, total support time and perfusion techniques, and number and type of concurrent procedures. Deep hypothermic circulatory arrest was defined as >10 minutes of no circulatory flow. Periods of ≤10 minutes were allowed in the regional cerebral perfusion group to account for cannula repositioning and atrial septectomy, but the surgery was classified as no deep hypothermic circulatory arrest. The lowest temperature on bypass was recorded from a core measurement site (nasopharynx, rectum, or bladder).
Postoperative variables included hospital length of stay, postoperative interventions including interventional cardiac catheterisation; additional cardiac surgery; extracorporeal membrane oxygenation (initiated in the operating room or during postoperative hospitalisation), prolonged pleural effusion (i.e., pleural effusion requiring drainage >7 days post-Fontan); and in-hospital deaths. Postoperative complications were collected and divided into major versus minor categories using the Society of Thoracic Surgery definitions.Reference Jacobs, O’Brien and Jacobs6 Diagnosis, interventions, and significant complications were collected for patients readmitted ≤30 days after Fontan discharge.
Analysis
Analyses were performed using SAS version 9.4 (SAS Institute Inc., Cary, North Carolina, United States of America), with significance tested at level 0.05 unless otherwise stated. Aggregate frequencies for categorical variables, and mean ± standard deviation, median, and interquartile range for continuous variables were calculated for the study population. The total number of centres that utilised a particular practice or type of care was determined. For centres where the practice or type of care was utilised, the median value within the centre was calculated for continuous variables; the proportion of patients was calculated for dichotomous variables. Median, interquartile range of medians, and range of medians were then calculated using these centre-level median or proportion data from 14 centres. The results in the manuscript are listed as median (range of medians) unless otherwise specified. The results in the tables are expanded as median and interquartile and total ranges.
Classification and regression tree methodology was utilised to identify potentially important determinants of two outcomes of interest, length of stay, and prolonged pleural effusion, by selecting cut points of variables that predicted high versus low levels for median length of stay below or above the median across centres (<10 versus ≥10 days), and percentage of patients with prolonged pleural effusion below or above the median across centres (<9.5 versus ≥9.5%). This non-parametric technique works by selecting the predictor most associated with an outcome and determining its cut point using a binary split; this is the first node in the decision tree. The next set of “branches” in the tree is formed by finding the predictors most associated with the outcome within the groups determined by the first node, thus nesting the second set of predictors within the first predictor. The procedure continues iteratively, identifying predictors and adding branches to the prediction tree, until it stops at a final number of branches determined by a cost–complexity parameter. Receiver operating curves are constructed, with a higher area under the curve for a given model indicating a better predictive model.
All 14 centres were included in the centre-level classification and regression tree analyses, resulting in 14 sets of observations. Explanatory variables included as possible predictors were median centre value of the continuous variables age at Fontan and weight-for-age z-score, and proportion of patients at each centre with: concurrent procedure(s), deep hypothermic circulatory arrest use, lateral tunnel versus extra-cardiac Fontan, pre-Fontan catheterisation intervention(s), post-Fontan catheterisation intervention(s), post-Fontan surgical procedure(s), pleural effusion >7 days (for the length of stay model only), other postoperative complications during the Fontan hospitalisation, and other major postoperative complications (versus minor or no complication). To avoid double counting the prolonged pleural effusion (>7 days) complication, it was listed as a separate possible predictor and excluded from other postoperative complication categories. For both outcomes, two sets of classification and regression tree models were run, one with all possible predictors included and the second excluding the “other postoperative complication” variable, as a sensitivity analysis considering possible collinearity with the “other major complication versus minor/no complication” variables. Additional confirmatory analysis used logistic regression modelling to examine the relationships being tested in the classification and regression tree analyses; given the small sample size (14 centres), p-values <0.20 from the logistic regression analysis were considered as confirmatory or suggestive of possible relationships for future testing.
Results
Study population
The analytic cohort consisted of 14 centres with 320 of the original 549 Single Ventricle Reconstruction patients having the Fontan procedure before age 6 years (Supplemental Table 6). All patients included in the present analysis were transplant-free survivors enrolled in both Single Ventricle Reconstruction and the Extension Study (n = 380), with complete follow-up data through the Fontan hospitalisation performed between January 2007 and April 2013. Analytic sample criteria closely followed those for the recent Pediatric Heart Network patient-level investigation of Fontan length of stay.Reference Ravishankar, Gerstenberger and Sleeper7
Preoperative variables
Across centres, the median weight and age at Fontan were 13 kg (11–14.8) and 3.1 years (1.7–3.9), respectively (Supplemental Tables 1 and 2). A median of 21% of patients had ≥1 associated cardiac diagnoses (2–47%), and 7% (2–27%) had an identifiable genetic abnormality. Eleven centres reported that 100% of patients underwent a pre-Fontan cardiac catheterisation (range across all centres, 54–100%); for three centres, 54–97% of patients underwent catheterisation. Across all centres, 53% (13–91%) of patients had ≥1 catheter-based intervention. The type of stage II procedure varied across centres.
Perioperative variables
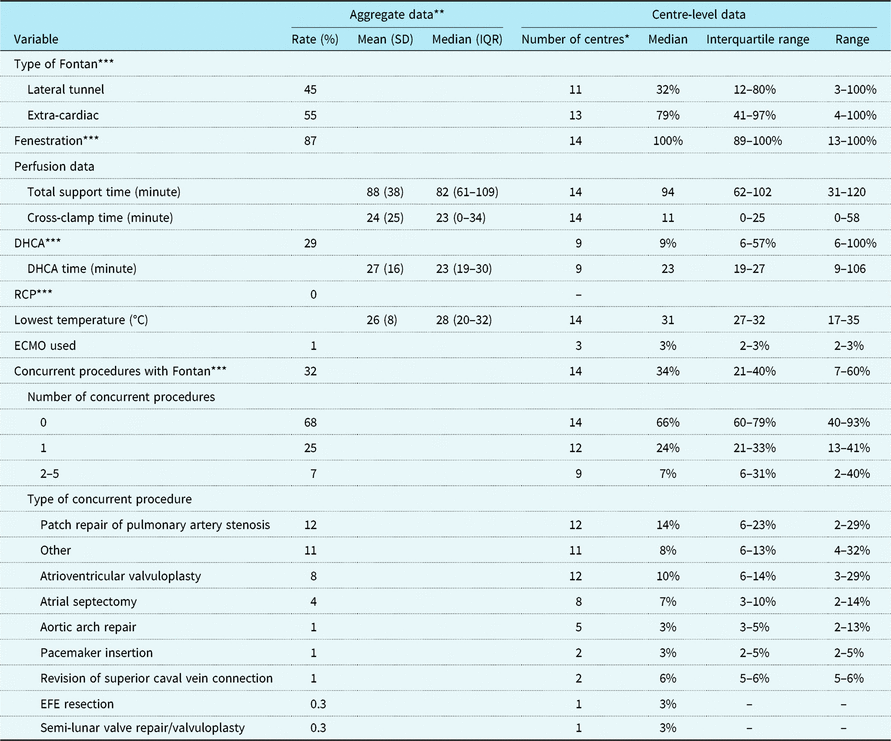
In aggregate for this cohort, 55% of patients received an extra-cardiac Fontan; 45% received a lateral tunnel operation (Table 1). At the 13 centres that performed extra-cardiac Fontan procedures, 79% (4–100%) of patients received an extra-cardiac Fontan. At the 11 centres performing lateral tunnel Fontan procedures, 32% (3–100%) of patients received this procedure. All patients received a fenestration in eight centres (range from 13 to 100%). Nine centres used deep hypothermic circulatory arrest in 9% (6–100%) of patients for 23 minutes (9–106 minutes). The lowest temperature on cardiopulmonary bypass across centres was 31°C (17–35). Concurrent cardiac procedures across all centres were performed in 34% (7–60%) of patients, the most common being pulmonary arterioplasty (14%).
Variation in Fontan operative/perioperative variables

DHCA = deep hypothermic circulatory arrest; ECMO = extracorporeal membraone oxygenation; EFE = endocardial fibroelastosis; RCP = retrograde cerebral perfusion.
* The number of centres refers to the number out of the 14 centres that used a particular practice or type of care.
** Aggregate data sample size was 320 except where indicated.
*** Type of Fontan and concurrent procedures with Fontan, n = 319; fenestration, DHCA and RCP, n = 318.
Postoperative variables
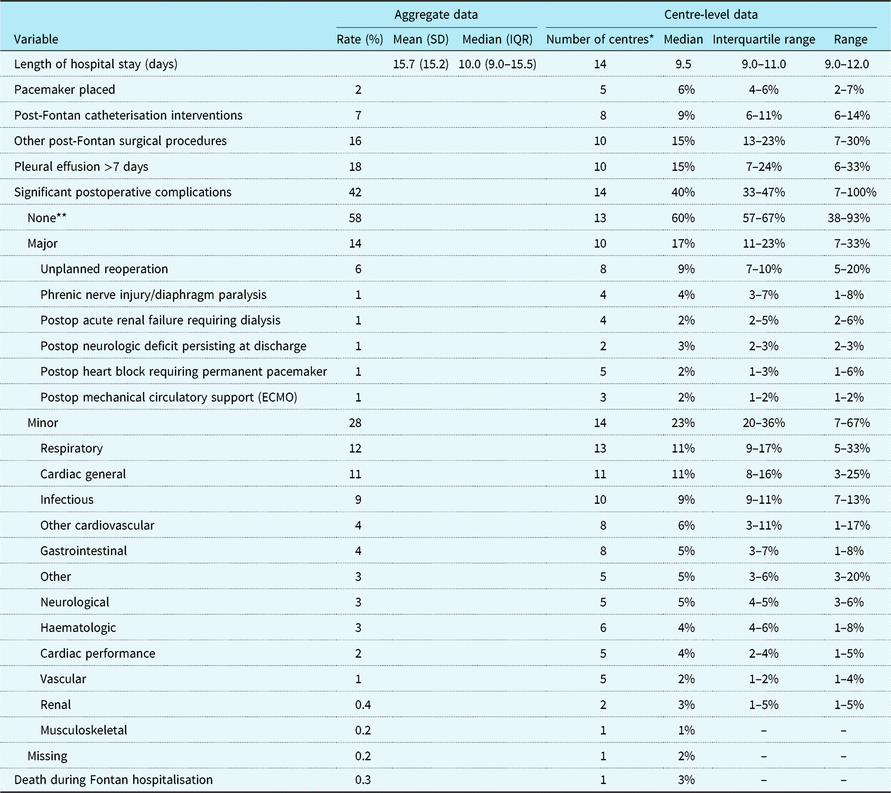
Total hospital length of stay, postoperative surgical procedures, the proportion of patients undergoing interventional cardiac catheterisations, and those with prolonged pleural drainage and postoperative complications varied among centres (Table 2 and Supplemental Table 3). Across centres, length of stay was 9.5 days (9–12). Prolonged pleural effusion occurred in 15% (6–33%) across 10 centres with ≥1 patient with this complication. A median of 40% (7–100%) of patients across centres had ≥1 complication, with 17% (7–33%) being major and 23% (7–67%) being minor. Overall, one patient died during the Fontan hospitalisation. The number of hospital readmissions and the primary diagnosis for readmission varied across centres (Supplemental Tables 4 and 5). In 10 centres with ≥1 readmission, the most common primary diagnosis was “respiratory” in 8% (3–33%) of patients.
Variation in Fontan postoperative variables

ECMO = extracorporeal membraone oxygenation.
* The number of centres refers to the number out of the 14 centres that used a particular practice or type of care.
** Includes 15 patients who had pleural effusion >7 days as their only postop complication.
Centre-level classification and regression tree analysis
Length of stay
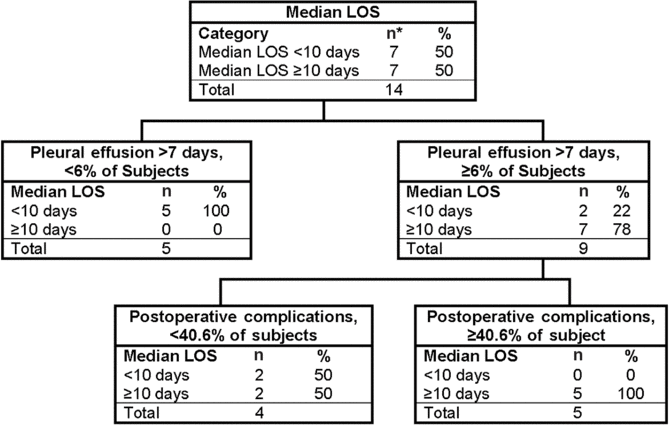
For the cohort, seven centres had a low median length of stay (defined as <10 days) and seven centres had a high length of stay (≥10 days). Classification and regression tree analysis identified two nested drivers of low versus high median length of stay proportion of patients with pleural effusion >7 days and proportion of patients with a postoperative complication (Fig 1). The median age at Fontan (<2.9 versus ≥2.9 years) was initially identified as a third predictor; however, this model was overfit with 100% accuracy, likely due to the third split being based on four centres, an insufficient sample size resulting from the small number of centres overall (n = 14, Supplemental Figure 1). Thus, the initial model was pruned to include only two splits for a better-fit final model. The classification and regression tree-determined cut-offs for these splits were ≥6% of patients with pleural effusion >7 days and ≥41% of patients with a postoperative complication. For this model, the sensitivity was 1.0, specificity was 0.71, and the receiver operator curve area under the curve was 0.96. In sensitivity analysis, running an alternative classification and regression tree model removing the “other postoperative complication” variables resulted in the generation of an another overfit model, with the same first split on prolonged pleural effusion <6 versus ≥6% of patients, but with second and third splits based on only one centre each (weight-for-age z-score <−0.37 versus ≥−0.37 and deep hypothermic circulatory arrest <57 versus ≥57% of patients). Notably, other major postoperative complications versus minor/none was not a significant predictor (Supplemental Figure 2). In confirmatory logistic regression, only pleural effusion >7 days was a possible predictor (p = 0.13).
Classification tree for median length of stay <10 versus ≥10 days by centre. *n refers to the number of centres having median length of stay (LOS) <10 versus ≥10 days, the median percentage across the 14 centres.

Pleural effusion >7 days
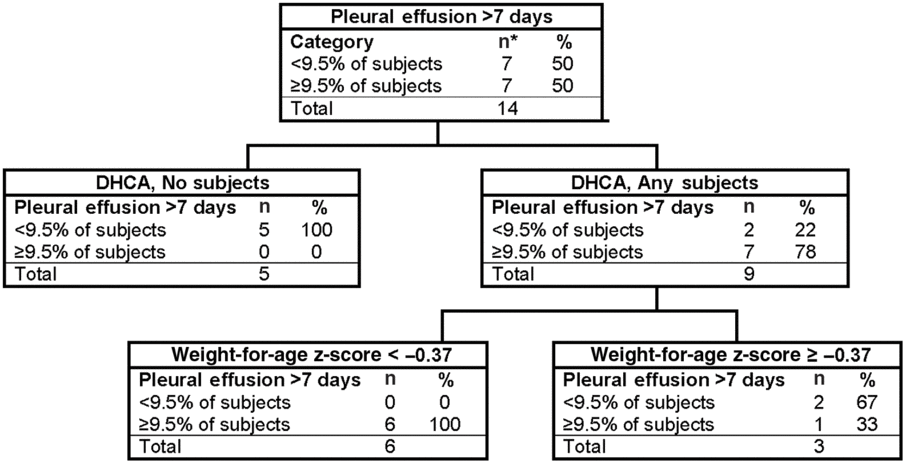
Across all centres, the median proportion of subjects having pleural effusion >7 days was 9.5%. Classification and regression tree analysis identified two nested drivers of low (<9.5%) versus high (≥9.5%) proportion of patients with prolonged pleural drainage, deep hypothermic circulatory arrest use and low weight-for-age z-score in those centres that did use deep hypothermic circulatory arrest (Fig 2). The cut-off for these predictors was of any use of deep hypothermic circulatory arrest and weight-for-age z-score <−0.37. This model had a sensitivity of 1.0, a specificity of 0.85, and a receiver operator curve area under the curve of 0.98. Pruning was not necessary for this outcome, and a second model excluding the “any other postoperative complication” variable had identical results. However, logistic regression modelling results were inconsistent with the classification and regression tree analysis, identifying a different set of potential predictors for having increased pleural effusion greater than days: lateral tunnel versus extra-cardiac Fontan (p = 0.10) and post-Fontan surgical procedures (p = 0.14).
Classification tree for percentage of patients with pleural effusion >7 days by centre. *n refers to the number of centres having <9.5 versus ≥9.5% of patients with pleural effusion >7 days by centre, the median percentage across the 14 centres. DHCA = deep hypothermic circulatory arrest.

Discussion
Our study is uniquely designed to evaluate centre-level compared to patient-level practice variation. This strategy allowed us to eliminate, as much as possible, the significant measured and unmeasured intra-patient variability and explore centre-level factors that were driving variation. We found a high degree of perioperative centre-level variability in care processes for children undergoing the Fontan procedure in the Single Ventricle Reconstruction cohort. These results are similar to the high degree of practice variability surrounding both the Norwood procedure and the stage II procedure.Reference Eckhauser, Pasquali and Ravishankar3, Reference Pasquali, Ohye and Lu4 In contrast to these descriptive reports, we also attempted to further evaluate two common, impactful, and easily captured outcomes: prolonged hospital length of stay (≥10 days) and prolonged duration of pleural drainage (>7 days) to target areas of interventions for future research.
Fontan hospital length of stay was chosen as an objective metric allowing each centre to compare itself with other centres. Both single and multi-centre studies of Fontan outcomes contain conflicting accounts of patient-level factors that drive hospital length of stay, including the need for greater resuscitation, hypoplastic left heart syndrome diagnosis, longer cardiopulmonary support times, longer length of stay at Stage II, ≥ moderate tricuspid regurgitation, and pre-Fontan complications.Reference Ravishankar, Gerstenberger and Sleeper7–Reference van der Ven, van den Bosch, Bogers and Helbing16 At the centre level, however, we found that prolonged length of stay was predominantly driven by both prolonged pleural drainage and postoperative complications with longer length of stay in centres with higher percentages of patients in these groups. When major versus minor/no complication was included as the sole postoperative complication explanatory variable in a second classification and regression tree model, it did not emerge as a meaningful predictor. We discarded our initial classification and regression tree model that showed older median age at Fontan (≥2.9 years) as a third driver of increased length of stay because the sample size was so small that we were able to predict with 100% accuracy the outcome, implying overfit of the model (Supplemental Figure 1). Despite this, the association of younger age at Fontan with shorter postoperative length of stay merits additional study as a modifiable risk factor for this surgery.
The presence of prolonged pleural effusion and smaller size were influential factors affecting Fontan outcomes. This is consistent with prior patient-level studies where prolonged pleural effusion was associated with worse mid-term outcomes, protein-losing enteropathy, and worse long-term survival.Reference Lo Rito, Al-Radi and Saedi17 In addition to being a marker of worse disease, prolonged pleural effusion also drove prolonged length of stay in this study. Patient-level factors including longer cardiopulmonary support times, hypoplastic left heart syndrome diagnosis, lower preoperative oxygen saturations, and postoperative infection have also been associated with prolonged pleural effusion but were not analysed in this study.Reference Lo Rito, Al-Radi and Saedi17, Reference Fedderly, Whitstone, Frisbee, Tweddell and Litwin18
Our additional classification and regression tree analysis allowed better understanding of the role of prolonged pleural effusion at the centre level. Deep hypothermic circulatory arrest and lower weight-for-age z-score were significant drivers for this outcome. In an analysis of postoperative Fontan outcomes for Single Ventricle Reconstruction Trial patients at the patient level, the use of deep hypothermic circulatory arrest was associated with decreased length of stay when using treatment centre as a predictor.Reference Ravishankar, Gerstenberger and Sleeper7 Presumably, this was from the decreased inflammatory response associated with deep hypothermic circulatory arrest. However, when treatment centre was removed as a variable from the analysis, deep hypothermic circulatory arrest was no longer associated with length of stay. In contradistinction, we showed that the five centres that did not use deep hypothermic circulatory arrest for any patient had a smaller proportion of patients with prolonged pleural drainage. Similarly, we found that for centres using deep hypothermic circulatory arrest, those with median patient weight-for-age z-score ≥−0.37 had a smaller proportion of patients with prolonged pleural drainage. These data support the findings of other investigators who reported a weight-for-age z-score <−2 is associated with significant morbidity after the Fontan procedure.Reference Wallace, Jaggers and Li19
Limitations
Our paper was not designed or powered to demonstrate a causal link between proposed drivers of length of stay or prolonged pleural effusion and these outcomes; however, the data inform some interesting hypotheses that are worthy of future investigation with careful considerations of important confounding factors in the study design. Our study also reflects the limitations described for practice variation around the Norwood and stage II procedures. The 14 participating centres were medium-to-high volume centres, and these data may not actually represent true variability globally. We were limited to data obtained in the Single Ventricle Reconstruction data sets and unable to analyse variability among all care processes or practices. We were unable to determine whether surgeon preference or specific anatomic findings accounted for the variability in the choice of type of Fontan. These limitations prohibited an analysis of patient-level variation based on risk factors versus individual complexities versus practice-based variation. Finally, we were limited by our small sample size of 14 centres in this centre-level analysis.
Conclusion
There is marked centre variability in the care and management of patients undergoing the Fontan procedure. Centres with greater proportions of patients with prolonged pleural effusion and higher proportion of postoperative complications had longer length of stay. In addition, in centres that used deep hypothermic circulatory arrest, patients with lower weight-for-age z-score scores had higher rates of prolonged pleural effusion. These data allow hypothesis generation for future, prospective, and collaborative testing.
Supplementary material
To view supplementary material for this article, please visit https://doi.org/10.1017/S1047951119002658
Acknowledgments
We acknowledge the NIH/NHLBI Pediatric Heart Network Single Ventricle Reconstruction Trial I and II data sets for all data in this manuscript.
Financial Support
This work was supported by National Heart, Lung, and Blood Institute grants HL068269, HL068270, HL068279, HL068281, HL068285, HL068288, HL068290, HL068292, and HL085057. This work is solely the responsibility of the authors and does not necessarily represent the official views of the National Heart, Lung, and Blood Institute or the National Institutes of Health.
Conflicts of Interest
None.