





Iodine is an essential trace element required for the synthesis of the thyroid hormones thyroxine (T4) and triiodothyronine (T3), which regulate growth, development and metabolism(Reference Zimmermann1). Adequate thyroid hormone production is particularly critical during pregnancy and early childhood, as iodine deficiency can impair neurodevelopment and lead to irreversible cognitive deficits(Reference Bath, Verkaik-Kloosterman and Sabatier2). Beyond early life, sufficient iodine intake remains important throughout adulthood to maintain normal thyroid function and prevent disorders such as goitre and hypothyroidism(Reference Zimmermann and Boelaert3).
As the human body cannot synthesise iodine, optimal status depends entirely on dietary intake. The UK Reference Nutrient Intake (RNI) for iodine in adults is 140 µg/d(4). In many populations, major dietary sources of iodine include dairy products, seafood and eggs, while iodised salt represents a primary source in countries with salt fortification programmes(5). However, iodine intake can vary substantially depending on dietary patterns, food availability and fortification practices.
At the population level, urinary iodine concentration measured from spot-urine samples is considered the gold standard biomarker of iodine status, reflecting recent iodine intake. However, urinary iodine concentration exhibits high intra-individual variability and does not accurately capture habitual iodine consumption(Reference Chen Wen, Guo and Tan6); therefore, it cannot be used for individual assessment of iodine status. Alternative biomarkers, such as serum thyroglobulin, provide complementary information but are costly and less practical outside large-scale surveys(Reference Vejbjerg, Knudsen and Perrild7). Consequently, dietary assessment methods play a crucial role in identifying individuals and population groups at risk of iodine deficiency and in characterising long-term intake patterns.
Traditional dietary assessment approaches, including weighed food diaries and repeated 24-h recalls, are regarded as reference methods for estimating nutrient intake but are labour-intensive and time-consuming and primarily reflect short-term consumption(Reference Cade, Thompson and Burley8). By contrast, dietary screening tools such as FFQ offer a more efficient and cost-effective approach to assessing habitual intake, particularly for micronutrients like iodine that are unevenly distributed across a limited number of foods. When appropriately developed and validated, iodine-specific FFQ can provide a practical means of identifying individuals at risk of deficiency. However, relatively few iodine-specific FFQ have been validated in European populations(Reference Głąbska, Malowaniec and Guzek9–Reference Combet and Lean11), and many have been developed only for specific subgroups, such as pregnant women(Reference Næss, Aakre and Kjellevold12,Reference Brantsaeter, Haugen and Alexander13) . Moreover, regional dietary differences highlight the importance of incorporating locally relevant iodine sources into such tools.
In the UK, only one iodine-specific FFQ has previously been validated(Reference Combet and Lean11); Combet et al. developed a UK-specific FFQ for women of childbearing age, demonstrating good agreement with 4-d food diaries and 24-h urinary iodine excretion(Reference Combet and Lean11). However, this tool did not include several emerging or relevant iodine sources, such as eggs and plant-based milk alternatives, which have become increasingly prominent as dietary patterns shift towards plant-based diets. As these alternatives are typically unfortified with iodine(Reference Nicol, Thomas and Nugent14), their substitution for cow’s milk may contribute to a lower iodine intake at the population level(Reference Nicol, Nugent and Woodside15).
Given ongoing changes in UK food availability, food composition and dietary patterns, there is a clear need for an updated, validated iodine-specific screening tool that reflects contemporary food consumption patterns among adults. Therefore, the present study aimed to develop and validate the Iodine Intake Risk Score (IoRISC), a simple, rapid iodine-specific screening tool to classify UK adults as having insufficient, sufficient or excessive iodine intake. The IoRISC screening tool was designed to capture habitual intake in line with current dietary trends, including the use of plant-based milk alternatives, and to provide a practical method for identifying individuals at risk of inadequate iodine intake in both research and applied settings.
Methods
Development of the iodine-specific screening tool
We first developed an FFQ–based screening tool in 2017(Reference Alvarez-Goel16) to assess the risk of low iodine intake in women of reproductive age. From 2018–2020, three iterations of the IoRISC screening tool were tested in small feasibility studies (n 16, n 26, n 21) (Reference Patel, Heighington-Wansbrough and Bath17–Reference Lutek and Bath19) that also compared the tool’s estimated iodine with that from a 4-d food diary. Pitfalls of the IoRISC screening tool were addressed with each iteration to improve usability and clarity with some options.
The screening tool comprised five main food categories: (i) milk, (ii) dairy products, (iii) eggs, (iv) fish and seafood and (v) meat and poultry. The foods were selected based on their established contribution to iodine intake in the UK diet. Introductory questions assessed the use of iodine-containing supplements, use of iodised table salt and types of milk consumed (cow’s milk, goat’s milk or plant-based alternatives). Intake frequency was captured using ten response options ranging from ‘never/rarely’ to ‘six or more times per day’, encompassing monthly, weekly and daily consumption patterns. The milk section included six portion size options (e.g. a glass of milk and milk on breakfast cereal).
Pilot study
We conducted a pilot study in 2023 to adapt the screening tool for use in all adults (>18 years), given increasing evidence that iodine deficiency is not confined to women of reproductive age(20), particularly amid rising consumption of plant-based milk alternatives(Reference Nicol, Nugent and Woodside21). The 2023 pilot study (n 16) used a modified version of the 2018 screening tool(Reference Patel, Heighington-Wansbrough and Bath17) to assess clarity, usability and completeness of dietary iodine capture in a broader adult population.
Following the 2023 pilot study, several refinements were made, including additional food items across sections and revisions to the portion-based milk consumption questions for improved clarity. More detailed questions on plant-based milk alternatives were added to reflect the diversity of brands and fortification practices in the UK market(Reference Nicol, Thomas and Nugent14). In the fish and seafood section, ‘samphire’ and ‘any other fish/seafood’ items were added, ‘canned tuna’ was expanded to include all tuna products and ‘nori’ and ‘seaweed snacks’ were combined into a single food item. In the dairy-products section, a new item was introduced to capture mixed dishes containing cheese or cream, reflecting commonly consumed dairy-rich foods that may have been underreported in earlier versions of the tool. This refined version of the IoRISC screening tool formed the final instrument used in the validation study conducted between 2023 and 2025.
Validation study design
Recruitment and subject eligibility
Recruitment took place between October 2023 and September 2025. Eligible participants were healthy adults aged 18 years and over, including individuals following vegetarian or vegan diets. Exclusion criteria included pregnancy or breastfeeding, a history of thyroid disease or thyroid medication use and participation in another dietary intervention study.
Ethical approval and informed consent
Ethical approval was granted by the Faculty of Health and Medical Sciences Ethics Committee, University of Surrey, UK (reference: FHMS 22-23 060 EGA). All participants received a participant information sheet detailing study procedures and a privacy notice outlining how data would be handled in accordance with the relevant data protection acts.
Participants completing the study online provided informed consent via mandatory tick boxes within the survey platform, preventing continued participation without consent. Written informed consent was obtained from in-person participants. Following study completion, participants identified as having insufficient or excessive iodine intakes based on both dietary assessment methods were provided with tailored dietary advice.
Questionnaires and dietary assessment methods
Participants were first enrolled through an online screening questionnaire that collected contact information and confirmed eligibility based on the inclusion and exclusion criteria. Eligible participants were then invited to complete a short baseline questionnaire collecting sociodemographic information, including age, sex, body weight and education level.
Participants completed two dietary assessment methods in sequence: (i) the refined IoRISC screening tool, designed to capture long-term habitual intake, and (ii) a 6-d estimated food diary, used as the reference measure. A 6-d recording period was selected to better represent habitual intake, as shorter recording periods (3 or 4 d(Reference Combet and Lean11,Reference Næss, Aakre and Kjellevold12,Reference Condo, Makrides and Skeaff22,Reference Rasmussen, Ovesen and Bülow23) ) may not adequately capture infrequently consumed iodine-rich foods, such as fish.
Both dietary assessment methods included questions on the use of dietary supplements, iodised table salt and specific milk types consumed (cow’s milk, goat’s milk or plant-based milk alternatives with brand information). Following submission, participants were contacted via email to clarify any incomplete or ambiguous diary entries.
Estimation of iodine intake from food diaries
Participants recorded all foods, beverages and supplements consumed over six consecutive days, including at least one weekend day, to capture day-to-day variation in intake. For each entry, participants reported the date and time, food description, portion size, brand name (where applicable) and cooking method.
All food diaries were analysed by a single researcher using Nutritics(24) to estimate individual mean iodine intake across 6 d, assumed to reflect habitual intake. Iodine intake from supplements was included where applicable.
Estimation of iodine intake from the screening tool
For each food item included in the screening tool, mean portion size and iodine concentration wasdetermined using UK food composition tables(Reference Finglas, Pinchen and Berry25) and Nutritics(24). Where iodine content data were unavailable (e.g. for samphire), published analytical data were used(26). Iodine content values for plant-based milk alternatives were obtained from a UK market survey(Reference Nicol, Thomas and Nugent14). Iodine contributions from supplements were derived from manufacturer information and adjusted for reported consumption frequency.
All data were processed in Microsoft Excel(27), where each participant’s responses were coded to estimate daily iodine intake. Monthly and weekly consumption frequencies were converted to daily equivalents (e.g. 2–3 portions per month = 0·08 portions per d), and this information was combined with the iodine-per-portion estimates to give a daily total.
Survey responses were exported directly from Qualtrics Online Surveys in a pre-coded format. Each participant was assigned a unique identification code to prevent duplicate entries. Time to complete the IoRISC screening tool (in minutes) was estimated using Qualtrics-recorded timestamps for survey start and completion.
Statistical analysis
Sample size was determined using G*Power software (version 3.1) based on a χ 2 goodness-of-fit test, with 80 % power, two df, a medium effect size estimated from pilot data and an alpha level of 0·05. The minimum required sample size was 108 participants, consistent with previous research indicating that 50–100 subjects are sufficient to validate an FFQ within a population group(Reference Cade, Thompson and Burley8).
All analyses were conducted in R(28) (version 2025.09.2). Normality was assessed using the Shapiro–Wilk test on the distribution of paired differences between iodine intake estimated from the screening tool and the food diaries. As the paired differences were not normally distributed, non-parametric tests were used. Descriptive statistics are presented as medians and interquartile ranges (IQR).
Iodine intake was categorised as insufficient (<140 µg/d), sufficient (140–600 µg/d) or excessive (>600 µg/d). These categories were based on UK Dietary Reference Values for adequate intake in adults(4) and the European Food Safety Authority Tolerable Upper Intake Level(29). The proportion of participants with intakes below the Lower RNI (<70 µg/d(30)) was also reported.
Cross-classification tables were constructed to evaluate the extent to which the screening tool and food diaries classified participants into the same iodine intake category. Agreement between classifications was assessed using Cohen’s kappa (κ) statistic, interpreted according to Landis and Koch’s criteria(Reference Landis and Koch31), where Kappa values of 0·01–0·20 represent a slight agreement, 0·21–0·40 fair agreement, 0·41–0·60 moderate agreement, 0·61–0·80 substantial agreement and 0·81–1·00 near-perfect agreement.
Sensitivity was defined as the proportion of participants correctly identified by the IoRISC screening tool as iodine insufficient (true positives), while specificity represented the proportion correctly identified as sufficient (true negatives), using the food diaries as the reference measure.
Comparisons between estimated iodine intake from the screening tool and the food diaries were made using the Wilcoxon signed-rank test, and associations were assessed using Spearman’s correlation coefficient. Agreement between methods was evaluated with Bland–Altman plots, with limits of agreement calculated as the mean difference ± 1·96 × sd.
Exploratory subgroup analyses were also conducted according to milk consumption pattern (cow’s milk only consumers, mixed cow’s milk and plant-based milk consumers and plant-based milk only consumers) to assess the IoRISC screening tool performance across dietary groups.
Results
Participant characteristics
A total of 108 participants completed the validation study (Table 1). The majority were female (73 %), with a median BMI of 23·7 kg/m2 (IQR 21·1–25·7). Twelve participants (11 %) reported use of iodised salt, and ten (9 %) reported consuming iodine-containing supplements.
Demographic characteristics (n 108)

Table 1. Long description
A table with demographic characteristics of 108 participants. The table has 10 rows and 3 columns. The columns are labeled Characteristics, n, and %. The rows are grouped into categories: Age, Gender, BMI, Specific diet, Main milk type consumed, Iodised salt users, and Iodised supplement users. Row 1: Age, 18-24 years, 29, 27 percent. Row 2: Age, 25-34 years, 23, 21 percent. Row 3: Age, 35-44 years, 23, 21 percent. Row 4: Age, 45-54 years, 9, 8 percent. Row 5: Age, 55-64 years, 15, 14 percent. Row 6: Age, 65+ years, 9, 8 percent. Row 7: Gender, Male, 29, 27 percent. Row 8: Gender, Female, 79, 73 percent. Row 9: BMI, <18.5, 3, 3 percent. Row 10: BMI, 18.5-24.9, 69, 64 percent. Row 11: BMI, 25.0-29.9, 28, 26 percent. Row 12: BMI, >30, 7, 6 percent. Row 13: Specific diet, None, 94, 87 percent. Row 14: Specific diet, Pescetarian, 3, 3 percent. Row 15: Specific diet, Lacto-ovo-vegetarian, 7, 6 percent. Row 16: Specific diet, Vegan, 4, 4 percent. Row 17: Main milk type consumed, Cow’s milk, 77, 71 percent. Row 18: Main milk type consumed, Goat’s milk, 1, 1 percent. Row 19: Main milk type consumed, Plant-based milk, 30, 28 percent. Row 20: Iodised salt users, 12, 11 percent. Row 21: Iodised supplement users, 10, 9 percent.
Milk consumption patterns varied across the cohort: 48 % (n 52) reported exclusive consumption of cow’s milk, 21 % (n 23) consumed only plant-based milk alternatives and 24 % (n 26) consumed both cow’s milk and plant-based alternatives, while 7 % (n 8) reported consuming no milk or milk alternatives. When asked which type of milk they used most frequently, 71 % reported cow’s milk, 28 % plant-based alternatives and 1 % goat’s milk.
The median time that participants took to complete the IoRISC screening tool was 4 min (IQR 3–7 min).
Estimated daily iodine intake
Median daily iodine intake estimated by the IoRISC screening tool was 145 µg/d (IQR 91–211), compared with 140 µg/d (IQR 83–193) derived from 6-d food diaries. According to the food diaries, 50 % of participants had an iodine intake below the RNI (<140 µg/d), and 17 % had intake below the Lower RNI (70 µg/d). Using the IoRISC screening tool, 47 % of participants were classified as having an iodine intake below the RNI and 14 % below the Lower RNI.
Analysis of food-group contributions to iodine intake estimated from the IoRISC screening tool showed that milk and fortified plant-based milk alternatives contributed a median of 37 % (IQR 5–58 %) of total iodine intake, fish and seafood contributed 21 % (IQR 8–29 %) and other dairy products accounted for 22 % (IQR 13–36 %).
Agreement between methods
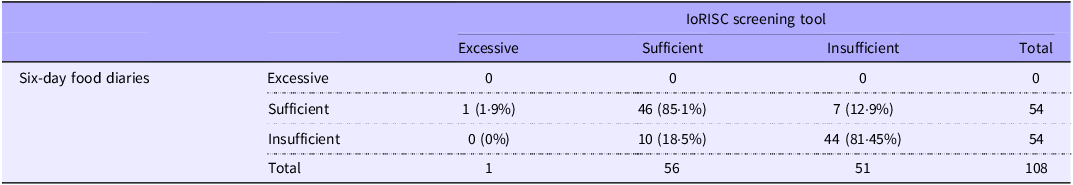
Substantial agreement was observed in the classification of iodine intake, with Cohen’s kappa of 0·68 (p < 0·0001). Cross-classification analysis confirmed high concordance between the IoRISC screening tool and food diaries in identifying individuals with insufficient and sufficient iodine intake. The IoRISC screening tool demonstrated a sensitivity of 82 % and a specificity of 87 % compared with the food diary reference method (Table 2).
Cross-tabulation of iodine intake classified as iodine sufficient, insufficient or excessive*, assessed by the IoRISC screening tool and the 6-d food diaries (n 108)

Table 2. Long description
A table with four rows and five columns comparing iodine intake classifications. The columns are labeled Screening tool with sub-columns Excessive, Sufficient, Insufficient, and Total. The rows are labeled Six-day food diaries with sub-rows Excessive, Sufficient, Insufficient, and Total. Row 1: Excessive, 0, 0, 0, 0. Row 2: Sufficient, 1 (1.9 percent), 46 (85.1 percent), 7 (12.9 percent), 54. Row 3: Insufficient, 0 (0 percent), 10 (18.5 percent), 44 (81.45 percent), 54. Row 4: Total, 1, 56, 51, 108.
IoRISC, Iodine Intake Risk Score.
Data are frequencies (% within the 6-d food diary classification).
Sensitivity: 81 % (proportion correctly identified as iodine insufficient); specificity: 85 % (proportion correctly identified as iodine sufficient).
* Iodine intake was categorised as insufficient (<140 µg/d), sufficient (140–600 µg/d) or excessive (>600 µg/d).
There was no statistically significant difference between iodine intake estimated by the IoRISC screening tool and the 6-d food diaries (p = 0·07; Table 3). A strong positive correlation was observed between the two methods (Spearman’s rs = 0·70, p < 0·0001).
Daily iodine intake as assessed by the IoRISC screening tool and the 6-d food diaries (n 108)

Table 3. Long description
A table comparing iodine intake assessed by a screening tool and a 6-day food diary. The table has 2 rows and 5 columns. The columns are labeled Median, IQR, Minimum, and Maximum, all measured in micrograms per day (µg/d). The row labels are Screening tool and Six-day food diary. Row 1: Screening tool, Median: 145, IQR: 91–211, Minimum: 19, Maximum: 715. Row 2: Six-day food diary, Median: 140, IQR: 83–193, Minimum: 5, Maximum: 547.
IQR, interquartile range; IoRISC, Iodine Intake Risk Score.
Bland–Altman analysis indicated a mean absolute difference of 17·6 µg/d between the IoRISC screening tool and food diaries, with limits of agreement ranging from –163 to 198 µg/d (Figure 1). Only six participants (approximately 6 %) fell outside the limits of agreement, indicating minimal systematic bias between methods.
Bland–Altman plot of agreement between the iodine intake estimated from the IoRISC screening tool and the 6-d food diary (n 108). The solid line indicates the mean difference between the two methods (18 µg/d), and the dashed lines indicate the limits of agreement corresponding to ±1·96 sd (lower agreement: −163 µg/d, upper agreement: 198 µg/d).

Subgroup analysis by milk consumption patterns
Exploratory subgroup analyses were conducted according to milk consumption patterns to assess the performance of the IoRISC screening tool. Among those who exclusively consumed cow’s milk (n 53), the median iodine intake estimated by the IoRISC screening tool was higher than that estimated from food diaries (186 v 146 µg/d). In this subgroup, the screening tool demonstrated moderate sensitivity (65 %) and high specificity (93 %) for identifying insufficient iodine intake compared with the food diary reference method. Among mixed cow’s milk and plant-based milk consumers (n 25), median iodine intakes were similar between methods (152 v 162 µg/d), and classification performance was high, with a sensitivity of 90 % and specificity of 100 %. Among exclusive consumers of plant-based milk (n 22), median iodine intake was also similar between methods (86 v 92 µg/d). In this subgroup, the screening tool demonstrated high sensitivity (90 %) but lower specificity (50 %). These subgroup analyses should be interpreted cautiously due to the small sample sizes.
Discussion
This study developed and validated a novel iodine-specific dietary screening tool (IoRISC) for UK adults, designed to capture contemporary dietary patterns, including the increasing consumption of plant-based milk alternatives. The IoRISC screening tool demonstrated strong agreement with 6-d food diaries, with substantial agreement in classifying participants by iodine sufficiency. The high sensitivity and specificity indicate that the IoRISC screening tool effectively identifies individuals with insufficient and sufficient iodine intake. Furthermore, the IoRISC screening tool showed comparable median iodine intake (145 µg/d v 140 µg/d), with a strong correlation with food diaries. Exploratory subgroup analyses suggested that classification performance remained high among mixed cow’s milk and plant-based milk consumers and that the IoRISC screening tool retained high sensitivity for identifying insufficient iodine intake among plant-based milk consumers. Collectively, these findings demonstrate that the IoRISC screening tool provides a valid, rapid and low-burden method for assessing habitual iodine intake in UK adults.
The need for such a screening tool has become increasingly urgent. Recent data from the National Diet and Nutrition Survey(20) indicate that median urinary iodine concentration among adults aged 19–64 years has now fallen below the WHO threshold for sufficiency(32). Furthermore, UK iodine status has shown a gradual year-on-year decline since monitoring began(33). National Diet and Nutrition Survey dietary-intake data similarly demonstrate that a substantial proportion of adults, particularly adolescent girls and women of reproductive age, have iodine intake below recommendations(20).
In the present study, although median dietary iodine intake was comparable to UK reference values, half of the participants were classified as having an insufficient iodine intake based on the food diaries. This pattern is consistent with National Diet and Nutrition Survey findings, where population median intakes may appear adequate while masking a significant subgroup with low intake(20). The relatively high prevalence of insufficiency observed may partly reflect the characteristics of the study sample, which included a large proportion of younger adults, a group previously shown to consume less iodine-rich foods such as milk and dairy products(20). Together, these findings reinforce the importance of accessible tools that rapidly identify individuals at risk of iodine deficiency.
When compared with previously validated iodine-specific FFQ, the present IoRISC screening tool offers several improvements. The only previously validated UK-specific iodine FFQ was developed for women of childbearing age and did not include emerging dietary sources such as eggs and plant-based milk alternatives(Reference Combet and Lean11). Other European tools have often been population-specific (e.g. pregnant women) and did not account for evolving dietary trends(Reference Głąbska, Malowaniec and Guzek9,Reference Næss, Aakre and Kjellevold12,Reference Brantsaeter, Haugen and Alexander13,Reference Rasmussen, Ovesen and Bülow23,Reference Mulligan, Luben and Bhaniani34) . By incorporating both traditional iodine-rich foods and newer products influenced by shifts toward plant-based diets, the present screening toolprovides a more comprehensive representation of current UK dietary patterns.
Compared with the previously validated UK iodine FFQ, which reported a specificity of 81 % and sensitivity of 45 % using food diaries as the reference method(Reference Combet and Lean11), the present screening tool demonstrated similar specificity (87 %) alongside greater sensitivity (82 %). This improved classification performance may reflect the broader food coverage of the questionnaire, including plant-based milk alternatives and updated information on iodine fortification practices, thereby reducing the misclassification of individuals as iodine insufficient(Reference Głąbska, Malowaniec and Guzek9,Reference Næss, Aakre and Kjellevold12) .
This study is the first to validate an iodine-specific screening tool in a mixed-sex UK adult population while explicitly accounting for plant-based alternatives and contemporary fortification practices. As these products are increasingly used as substitutes for cow’s milk and are typically low in iodine, their inclusion is critical for accurate dietary assessment. The integration of up-to-date market data(Reference Nicol, Thomas and Nugent14) on iodine content in plant-based alternatives further enhances the IoRISC screening tool’s relevance for both research and public health monitoring.
The efficiency and adaptability of the screening tool represent key strengths with important implications for public health practice. With a median completion time of only four minutes, the tool is well-suited for large-scale deployment in population surveys, primary care settings, community health programmes and digital health platforms. The questionnaire format lends itself readily to automation, online delivery and integration into electronic health systems, allowing real-time estimation of iodine intake and immediate feedback to users. Future development could include implementation as a freely accessible online tool providing personalised feedback and practical dietary advice, which could further increase its accessibility and public health utility. Integration into electronic health systems could also facilitate its use alongside routine dietary assessment and counselling. Moreover, the IoRISC screening tool could be readily translated and culturally adapted for use in other countries, provided that locally relevant iodine food sources and fortification practices are incorporated. Such scalability offers significant potential for improving iodine surveillance and prevention strategies globally.
From a public health perspective, the availability of a rapid and validated iodine screening tool could facilitate early identification of low iodine intake before clinical deficiency develops. This may support targeted dietary counselling, evaluation of fortification policies and population monitoring, particularly in settings where biomarker assessment is impractical or resource-intensive. In the context of declining iodine status in the UK and increasing dietary diversification, such tools may play a crucial role in preventing iodine deficiency disorders across the life course.
Several limitations should be acknowledged. Participants were predominantly from health-related academic backgrounds, which may influence dietary behaviours and nutrition awareness(Reference O’Kane, Pourshahidi and Farren35). Biomarkers of iodine status, such as urinary iodine concentration or serum thyroglobulin, were not included, limiting direct comparison with biochemical measures. While some previous validation studies incorporated urinary measures(Reference Combet and Lean11), correlations with dietary tools have often been modest(Reference Combet and Lean11), reflecting the inherent variability of short-term biomarkers and the fact that urinary iodine concentration is not a suitable biomarker for an individual. Reproducibility was not assessed(Reference Cade, Thompson and Burley8), as participants identified as iodine insufficient received dietary advice that may have altered subsequent intake. Finally, although continuous iodine intake estimates and agreement analyses were assessed, the screening tool was primarily designed to classify individuals into iodine sufficiency categories rather than to provide precise quantitative estimates of iodine intake. Consequently, diagnostic classification performance was prioritised over exact agreement for continuous intake values, which may limit direct comparability with some earlier FFQ studies focused primarily on quantitative intake estimation(Reference Combet and Lean11,Reference Næss, Aakre and Kjellevold12,Reference Condo, Makrides and Skeaff22) .
Despite these limitations, the present study provides strong evidence that the IoRISC screening tool is a valid, efficient and practical method for assessing habitual iodine intake in UK adults. By incorporating a comprehensive range of iodine sources reflective of modern dietary patterns and demonstrating high classification performance across differing milk consumption patterns, the tool addresses important gaps in existing dietary assessment methods. Given the ongoing decline in iodine status in the UK, the IoRISC screening tool offers a timely resource to support research, clinical practice and public health strategies aimed at identifying and reducing iodine inadequacy.
Supplementary material
To view supplementary material for this article, please visit https://doi.org/10.1017/S0007114526108721.
Data availability statement
The IoRISC screening tool and data that support the findings of this study are available from the corresponding author upon reasonable request.
Acknowledgements
The authors thank the participants for taking part in the study.
Authorship
K.N. and S.C.B. designed the study. K.N. collected and reviewed data and conducted the statistical analysis. S.G., W.K.W., S.G., G.M., E.H. and A.K. assisted with data collection. K.N., A.P.N., J.V.W., K.H.H. and S.C.B. interpreted the data. K.N. wrote the first draft of the manuscript; all authors edited and approved the final manuscript.
Financial support
K.N. was supported by the Biotechnology and Biological Sciences Research Council FoodBioSystems (BB/T008776/1). The funder had no role in the design, analysis or writing of this article.
Competing interests
S.C.B. has received an honorarium each from Oatly UK and Dairy Council Northern Ireland for delivering webinars and lectures to healthcare professionals. A.N. has received an honorarium from Dairy Council Northern Ireland for delivering a lecture to healthcare professionals. Other authors have no conflicts of interest to declare.



 Open access

