Chylothorax in children following cardiac surgery is associated with poor clinical outcomes and increased resource utilisation.Reference Zuluaga 1 – Reference McCulloch, Conaway, Haizlip, Buck, Bovbjerg and Hoke 6 The reported frequency of chylothorax after cardiac surgery in children varies from 1.3 to 4.7%, with even higher rates and greater variation described in neonates and infants (9.2–15.8%).Reference Chan, Russell, Williams, Van Arsdell, Coles and McCrindle 2 – Reference Biewer, Zurn and Arnold 4 , Reference Beghetti, La Scala, Belli, Bugmann, Kalangos and Le Coultre 7 – Reference Borasino, Diaz, El Masri, Dabal and Alten 12
A more detailed understanding of postoperative chylothorax is still lacking. Studies to date examining patient risk factors and outcomes associated with chylothorax have generally been single-centre studies limited by a small sample size. In addition, our understanding of variation in chylothorax rates across centres is limited to analyses of administrative data.Reference Mery, Moffett and Khan 3 Reliance on administrative data sets is subject to significant case ascertainment inaccuracies and an inability to perform proper risk adjustment – both of which create margins for error when comparing outcomes and performance between centres.Reference Pasquali, Peterson and Jacobs 13 , Reference Pasquali, He and Jacobs 14 A better understanding of patient and centre-level factors associated with chylothorax could inform initiatives aimed at improving prevention and management of this important complication.
The objective of this study was to utilise prospectively collected clinical data within a large multicentre cardiac ICU-specific registry to describe the current epidemiology of postoperative chylothorax, identify risk factors, and evaluate variation in rates across centres.
Materials and methods
Data source
The Pediatric Cardiac Critical Care Consortium is a quality-improvement collaborative that collects data on all patients with primary cardiac disease admitted to the cardiac ICU service of participating hospitals.Reference Gaies, Cooper and Tabbutt 15 At the time of this data analysis, 15 centres were submitting cases to the clinical registry.
Each participating centre has a trained data manager who enters data into the registry. The data managers adhere to a standardised Pediatric Cardiac Critical Care Consortium data definitions manual, which shares common definitions for surgical variables with the International Pediatric and Congenital Cardiac Code and Society of Thoracic Surgeons Congenital Heart Surgery Database as previously described.Reference Gaies, Cooper and Tabbutt 15 Participating centres are audited on a regular basis, and the audit results suggest comprehensive, accurate, and timely submission of data by participating centres.Reference Gaies, Donohue and Willis 16 The University of Michigan Institutional Review Board provides oversight for the Pediatric Cardiac Critical Care Consortium data coordinating centre; this study was reviewed and approved with waiver of informed consent.
Case selection
We analysed all hospitalisations of patients <18 years of age, including cardiac surgery and at least one cardiac ICU encounter between 1 October, 2013 and 30 September, 2015. For patient-level analyses with multiple cardiac ICU encounters, we included data from a patient’s cardiac ICU encounter associated with the index (first) operation only. For comparison of rates between centres, two centres that had submitted <50 cases at the time of the analysis were excluded because of the small sample size; these centres reported 0 chylothoraces.
Data variables and outcomes
Chylothorax was defined in the Pediatric Cardiac Critical Care Consortium as the presence of lymphatic fluid in the pleural space requiring an intervention during the cardiac ICU encounter. Examples of interventions include placement of a chest tube, medication therapy, or a change in diet. Data collectors record the date and time of chylothorax diagnosis, as well as other therapies and complications. Patient, preoperative, operative, and postoperative clinical variables were chosen a priori for evaluation as potential risk factors for chylothorax. These exposure variables included patient age, weight, ethnicity, genetic abnormalities, non-cardiac anomalies, preoperative conditions including use of mechanical ventilation, mechanical circulatory support, and history of necrotising enterocolitis, surgical complexity, surgical procedure group, cardiopulmonary bypass duration, use of an aortic cross-clamp, use of circulatory arrest, delayed sternal closure, central venous line use, and systemic venous stenosis or thrombosis. Weight-for-age z-scores were calculated using World Health Organization or Centers for Disease Control standards, according to patient age. 17 The Society of Thoracic Surgeons-European Association for Cardiothoracic Surgery Mortality Categories were used to classify surgical complexity.Reference Jacobs, Jacobs and Maruszewski 18 We also explored an alternative procedure classification by categorising patients into one of the following four groups: single-ventricle operations with or without aortic arch repair and biventricular operations with or without arch repair. Patients who underwent hybrid stage I palliation were classified in the group “single ventricle without arch repair”. Outcome variables evaluated included total duration of postoperative mechanical ventilation, postoperative cardiac ICU stay, and hospital length of stay.
Statistical analysis
Data are presented as frequencies or percentages for categorical variables and as medians with interquartile ranges for continuous variables. Rates of chylothorax in the overall cohort and at each participating institution are described as percentages. Risk factors for chylothorax and the association of chylothorax with postoperative outcomes were evaluated using the method of generalised estimating equations, to account for within-centre clustering, and multivariable logistic or linear regressions, as appropriate. Factors associated with chylothorax development in the unadjusted analysis (p<0.1) were subsequently included in the multivariable analysis to determine independent association with the development of chylothorax. Adjusted odds ratios (OR) and 95% confidence intervals (CI) are reported. We analysed the relationship between chylothorax and surgical mortality adjusting for factors known to be associated with mortality in the current Society of Thoracic Surgeons mortality risk model.Reference O’Brien, Jacobs and Pasquali 19 As there is currently no standard risk-adjustment model for the outcomes of duration of mechanical ventilation, or cardiac ICU and hospital length of stay, we also adjusted the relationship between chylothorax and these outcomes for factors included in the Society of Thoracic Surgeons mortality risk model.
To describe case-mix-adjusted rates of chylothorax across hospitals, we identified baseline patient factors – present at admission and not influenced by intensive care practice – associated with chylothorax at p<0.1 in the multivariable analysis described above, including neonate or infant status, chromosomal abnormality or genetic syndrome, major non-cardiac congenital anomalies, and single-ventricle procedure groups. These factors were included in a logistic regression model used to calculate an expected rate of chylothorax at each centre; bias-corrected confidence intervals of the odds ratio for each predictor were derived by 1000 bootstrap samples to generate the final model. The reported case-mix-adjusted rate of chylothorax was calculated as follows: (observed rate/expected rate)×overall observed rate.
Results
Study population
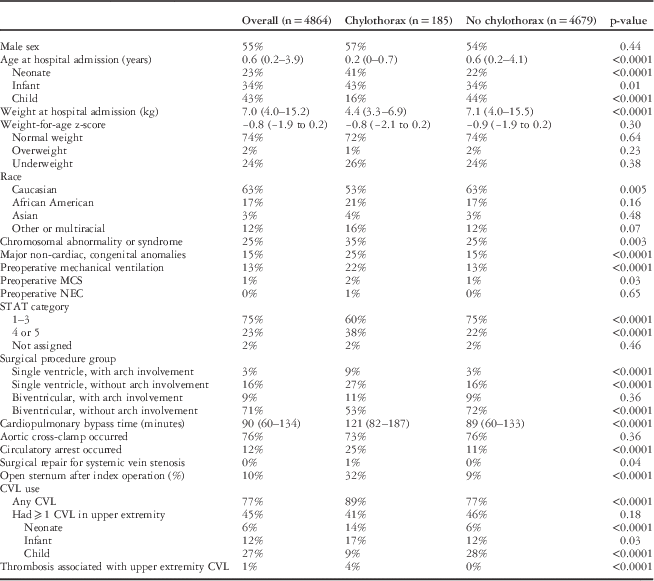
A total of 4864 hospitalisations from 15 centres were included. The characteristics of the overall study population are displayed in Table 1. Neonates and infants comprised 57% of the cohort, and 23% were in surgical mortality risk categories 4 or 5. The frequency of postoperative chylothorax in the overall cohort was 3.8% (n=185). Higher rates of chylothorax were observed in the following patient subgroups: neonates (6.9%), infants (4.8%), single-ventricle physiology (6.9%), chromosomal abnormalities or syndromes (5.2%), and major non-cardiac anomalies (6.4%).
Patient characteristics and univariate analysis.

CVL=central venous line; MCS=mechanical circulatory support; NEC=necrotising enterocolitis; STAT=Society of Thoracic Surgeons-European Association for Cardiothoracic Surgery
Data displayed as medians (interquartile range) or % as appropriate
Centre variation in rate of chylothorax
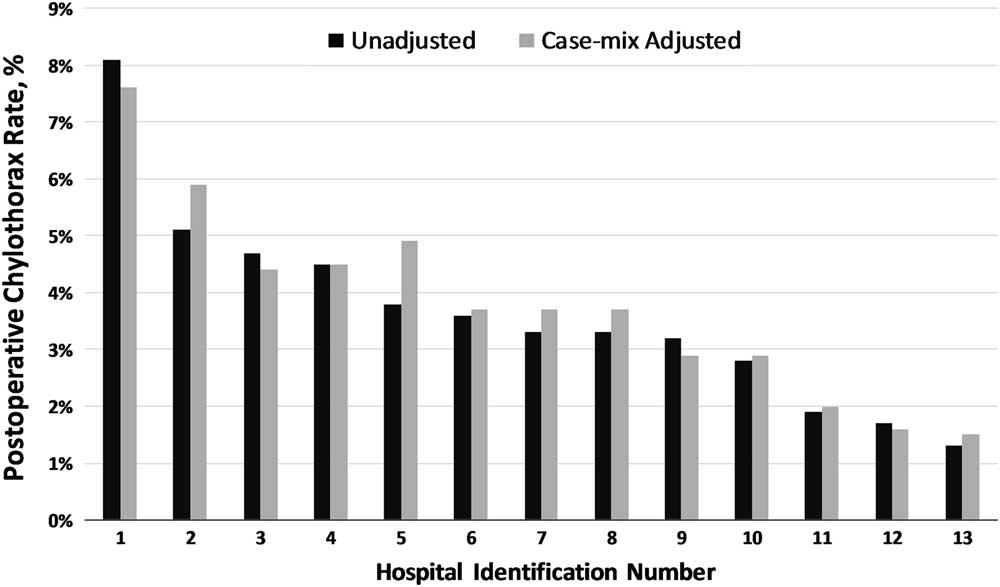
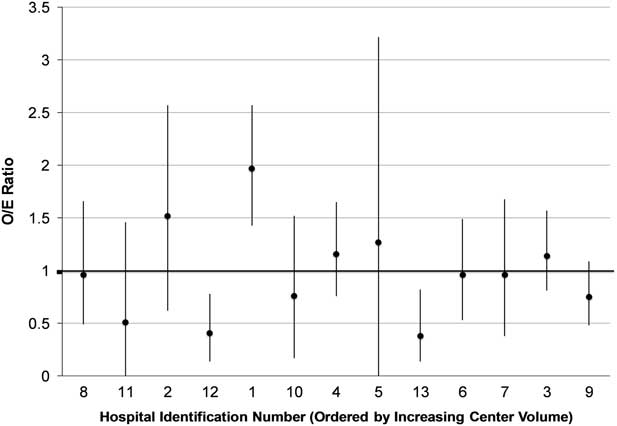
At the centre level, the adjusted rates of postoperative chylothorax varied from 1.5 to 7.6%. Figure 1 shows unadjusted and case-mix-adjusted rates of chylothorax observed at each centre. There was no association between the adjusted rates of postoperative chylothorax and centre volume (Fig 2).
Postoperative chylothorax rates by centre. Values are expressed as the percentage of postoperative cardiac ICU hospitalisations that developed chylothorax. Dark bars represent the unadjusted rates, and the light bars represent case-mix-adjusted rates. This portion of the analysis excluded data from two centres that submitted <50 cases at the time of the analysis and had 0 chylothoraces.

Adjusted postoperative chylothorax observed-to-expected ratios ordered by increasing centre volume. Dots represent the case-mix-adjusted ratios for each centre, and error bars represent 95% confidence intervals. Hospitals are ordered along the x-axis by increasing centre volume as measured in the annual volume of index operations (range 206–601, interquartile range 244–341). This portion of the analysis excluded data from two centres that submitted <50 cases at the time of analysis and had 0 chylothoraces.

Risk factors for chylothorax
Univariate comparisons between patients with and without postoperative chylothorax are demonstrated in Table 1. Significant patient and preoperative factors associated with the development of chylothorax included neonate and infant status, lower weight on admission, non-Caucasian race, chromosomal abnormalities, major non-cardiac anomalies, and the need for preoperative mechanical ventilation or mechanical circulatory support (all p<0.05). Significant operative variables included surgical complexity, single-ventricle operations both with and without arch repair, cardiopulmonary bypass time, and use of circulatory arrest during surgery (all p<0.0001). Postoperative factors included delayed sternal closure, systemic venous stenosis, upper-extremity central venous line use in younger patients, and thrombosis associated with upper-extremity central venous line (all p<0.05).
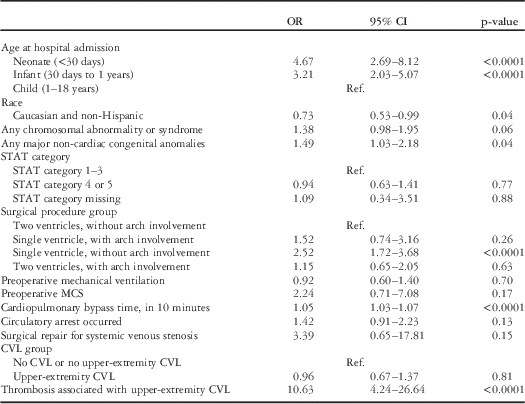
In the multivariable analysis (Table 2), neonates were four times more likely to develop postoperative chylothorax compared with older children (OR 4.7; 95% CI 2.7–8.1). Other significant independent risk factors included non-Caucasian race, single-ventricle anatomy, extracardiac anomalies, longer duration of cardiopulmonary bypass, and thrombosis associated with upper-extremity central venous lines. Preoperative mechanical ventilation, surgical complexity, and upper-extremity central venous line use did not remain predictive of chylothorax risk in multivariable analysis.
Factors associated with chylothorax development after cardiac surgery, multivariable analysis.

CI=confidence interval; CVL=central venous line; MCS=mechanical circulatory support; OR=odds ratio; Ref.=reference category; STAT=Society of Thoracic Surgeons-European Association for Cardiothoracic Surgery
Major interventions for chylothorax
The frequency of chest tube insertion in patients with chylothorax was 32% in the entire cohort and varied from 13 to 65% among centres that reported at least five cases of chylothorax during the study period. Pleurodesis and thoracic duct ligation were performed in 4 and 11% of patients with chylothorax, respectively.
Impact of chylothorax on outcomes
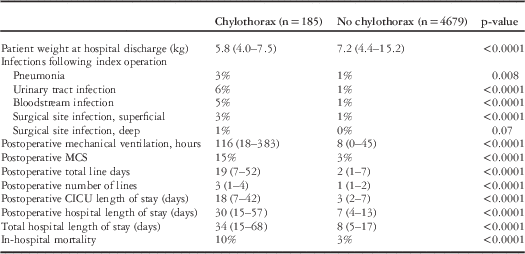
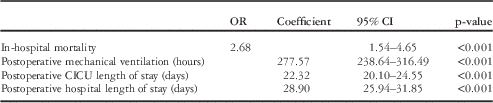
Table 3 displays clinical outcomes in patients with and without chylothorax. Significant differences were identified in the rates of postoperative infections, duration of postoperative mechanical ventilation, invasive line utilisation, length of stay, and mortality. In-hospital mortality occurred in 10% of patients who developed chylothorax compared with 3% of the cohort without chylothorax (p<0.0001). In multivariable analyses (Table 4), postoperative chylothorax continued to be significantly associated with longer duration of postoperative mechanical ventilation, longer postoperative cardiac ICU stay and total hospital stay, and higher in-hospital mortality (all p<0.001).
Clinical outcomes and resource utilisation associated with postoperative chylothorax; univariate analysis.

CICU=cardiac ICU; MCS=mechanical circulatory support
Data displayed as median (interquartile range) or % as appropriate
Clinical outcomes and resource utilisation associated with postoperative chylothorax; multivariable analysis.

CI=confidence interval; CICU=cardiac ICU; OR=odds ratio
Discussion
This study from the Pediatric Cardiac Critical Care Consortium is the first to utilise prospectively collected, multicentre, clinical registry data to describe the epidemiology and centre variation of postoperative chylothorax rates in children following cardiac surgery. In this cohort, 3.8% of postoperative hospitalisations were complicated by chylothorax requiring treatment in the cardiac ICU. More importantly, the current analysis identified five-fold variation of the case-mix-adjusted centre rates of postoperative chylothorax, suggesting opportunity for improvement.
Accurately identifying variation in rates after adjustment for case-mix differences is an important antecedent step to understanding the underlying centre-level practices that influence this variation. Although single-centre studies and an analysis of administrative data have suggested that variation among centres may exist, study-design limitations failed to account for the potential impact of case-mix differences, ascertainment bias, and disparate chylothorax diagnostic criteria.Reference Chan, Russell, Williams, Van Arsdell, Coles and McCrindle 2 – Reference Mery, Moffett and Khan 3 , Reference Bauman, Moher, Bruce, Kuhle, Kaur and Massicotte 8 – Reference White, Seckeler, McCulloch, Buck, Hoke and Haizlip 11 In contrast to previous reports relying on administrative data, the present analysis supports the notion that “high-performing” centres exist with low risk-adjusted rates of postoperative chylothorax, irrespective of centre volume.Reference Mery, Moffett and Khan 3 The next step is to leverage the collaborative learning fostered by the Pediatric Cardiac Critical Care Consortium, identify best practices at the high-performing centres and share process-improvement strategies.
Several important practice-independent risk factors were identified. Neonates and infants who underwent cardiac surgery carried a three- to four-fold increased risk compared with older children. Higher incidence of postoperative chylothorax has been reported by smaller, single-centre studies who focussed on children <1 year of age.Reference Biewer, Zurn and Arnold 4 , Reference Borasino, Diaz, El Masri, Dabal and Alten 12 In the context of analyses controlling for procedure-type and complexity, the finding of increased risk in younger patients may be attributable to differences in the lymphatic system of younger patients such as increased surface area and/or friability that predispose them to disruption and leakage.
Similar to other reports, our analysis demonstrated an association between extracardiac anomalies with the incidence of chylothorax. Although the exact link is unclear, it is possible that some of these conditions are associated with anatomical or functional abnormalities of the lymphatic system. Anatomical variations and abnormalities of the lymphatic system have previously been associated with conditions involving chylous fluid leakage.Reference Dori, Keller and Fogel 20 Some authors report emerging successful treatment of these conditions via interventional procedures such as embolisation of collateral lymphatic vasculature.Reference Dori, Keller and Fogel 20 , Reference Dori, Keller, Rychik and Itkin 21 A better understanding of the potential link between certain extracardiac anomalies and lymphatic abnormalities may help us identify patients predisposed to the development of chylothorax and refer those most likely to benefit from these novel therapeutic techniques.
In contrast to previous reports, our study did not find that surgical complexity confers additional risk for the development of chylothorax.Reference Mery, Moffett and Khan 3 , Reference Milonakis, Chatzis and Giannopoulos 10 , Reference White, Seckeler, McCulloch, Buck, Hoke and Haizlip 11 We did find a significant association between single-ventricle operations and postoperative chylothorax. Single-ventricle palliations that predispose patients to systemic venous hypertension such as the bidirectional cavopulmonary (Glenn) shunt and the Fontan procedure have been linked to postoperative chylothorax.Reference Zuluaga 1 – Reference Mery, Moffett and Khan 3 These findings highlight the complex, multifactorial aetiology of chylothorax development. Surgical complexity classification does not capture the postoperative physiological risk of systemic venous hypertension imposed by Glenn and Fontan operations – both designated within surgical mortality risk category 2. As the use of real-time data capture from patient monitoring becomes more widespread, we may be better able to investigate, understand, and case-mix adjust for the precise haemodynamic physiology that predisposes some patients to the development of postoperative chylothorax.Reference Rusin, Acosta and Sheckerdemian 22
In the postoperative period, central venous thrombosis and upper-body central venous line location have been associated with the development of chylothorax.Reference Biewer, Zurn and Arnold 4 , Reference Beghetti, La Scala, Belli, Bugmann, Kalangos and Le Coultre 7 , Reference Borasino, Diaz, El Masri, Dabal and Alten 12 It is postulated that upper-body venous obstruction, either due to the presence of thrombus or due to a catheter, increases resistance to lymphatic drainage from the thoracic duct into the innominate vein.Reference Borasino, Diaz, El Masri, Dabal and Alten 12 Thrombosis associated with an upper-extremity central venous line occurred relatively infrequently in our population, but this risk factor was independently associated with chylothorax. Contrary to the recent literature, our study demonstrated that upper-body central venous line insertion site alone was not independently associated with chylothorax. On the basis of the suspected underlying pathophysiology, the location of the line tip may be of greater importance than the insertion site. Data on line tip location were not collected for this cohort or reported by Borasino et alReference Borasino, Diaz, El Masri, Dabal and Alten 12 and may represent an area where our populations differed, resulting in discrepant findings. Preventative strategies such as avoiding upper-extremity central venous line placement or providing anticoagulation when one is present in patients at increased risk for chylothorax warrant further investigation.
The impact of postoperative chylothorax on clinical outcomes appears significant. The current analysis found chylothorax to be associated with an increased risk of in-hospital mortality even after controlling for other baseline factors impacting outcome.Reference O’Brien, Jacobs and Pasquali 19 Patients who developed chylothorax also had longer risk-adjusted durations of postoperative mechanical ventilation, cardiac ICU, and hospital stays. The granularity and time-stamped nature of the clinical data collected in the Pediatric Cardiac Critical Care Consortium registry permitted us to understand the relationship of therapies and events, thus strengthening our understanding of measured associations with chylothorax.
There are several limitations to this analysis. Most importantly, by the nature of the database, only complications, including chylothorax, treated in a cardiac ICU encounter are recorded. Chylothorax that developed in the non-cardiac ICU ward in a patient who never returned to the cardiac ICU would not be included in our analysis. As such, we may be underestimating the incidence of chylothorax. In addition, because our definition does not require measurement of pleural fluid chemistries, it is possible that some non-chylous effusions with a milky appearance are treated and coded as chylothorax, which may overestimate the incidence. Those centres that do not aggressively intervene when chylothorax is present may have a falsely low incidence, and some cases of chylothorax may go unrecognised if no fluid analysis occurs; however, this definition represents the consensus opinion of multiple members of the cardiac ICU clinical community on the Pediatric Cardiac Critical Care Consortium database committee, and as such is broadly indicative of how chylothorax is diagnosed and managed in the current era. Although the analysis included 4864 hospitalisations from 15 centres, the number of patients who developed chylothorax is still relatively small, and thus there was limited power to identify an association with rare risk factors. In addition, although we were able to examine variation in the rates of chylothorax across centres, detailed information regarding centre practices and management strategies are not available in the database and could not be analysed in this study.
Chylothorax after cardiac surgery in children is a complication associated with significantly increased morbidity and mortality. We observed five-fold variation in the adjusted rates of postoperative chylothorax across centres, suggesting potential opportunities for improvement. Future investigation should focus on resolving the possible biases discussed in this analysis, and then elucidating the processes that underlie this variation to identify centres most adept at preventing and managing chylothorax and disseminate best practices.
Acknowledgements
We acknowledge the data collection teams at all of the participating centres and the generous donors to the University of Michigan Congenital Heart Center and CHAMPS for Mott for their support of Pediatric Cardiac Critical Care Consortium.
Financial Support
Dr M.G. received support from the National Heart, Lung, and Blood Institute (K08HL116639, Principal Investigator) that indirectly supports this research. Dr M.G. received support for article research from the National Institutes of Health (NIH). His institution received grant support from the NIH (K08 award from NHLBI [Principal Investigator: M.G.]). Dr S.K.P. receives support from the Janette Ferrantino Professorship.
Conflicts of Interest
None.
Ethical Standards
The authors assert that all procedures contributing to this study comply with the ethical standards of the National Institutes of Health and with the Helsinki Declaration of 1975, as revised in 2008, and has been approved by the institutional committees of the University of Michigan.