Although Parkinson’s disease (PD) is classified as a movement disorder (Postuma et al., Reference Postuma, Berg, Stern, Poewe, Olanow, Oertel and Deuschl2015), it frequently includes a broad range of cognitive (e.g., executive dysfunction), emotional (e.g., depression), and somatic (e.g., sleep) nonmotor symptoms. Nonmotor symptoms are often harbingers of the classic hypokinetic syndrome, and they confer severe disability and are associated with increased mortality and decreased quality of life (Chaudhuri, Healy, & Schapira, Reference Chaudhuri, Healy and Schapira2006; Poewe, Reference Poewe2008; Schapira, Chaudhuri, & Jenner, Reference Schapira, Chaudhuri and Jenner2017). Consequently, many researchers have begun focusing their efforts on the assessment and treatment of nonmotor symptoms. For example, mild cognitive impairment (MCI) in PD has received more attention as an outcome in recent years (e.g., Aarsland et al., Reference Aarsland, Creese, Politis, Chaudhuri, Ffytche, Weintraub and Ballard2017; Pedersen, Larsen, Tysnes, & Alves, Reference Pedersen, Larsen, Tysnes and Alves2017; Riedel et al., Reference Riedel, Klotsche, Spottke, Deuschl, Förstl, Henn and Wittchen2008), as it has been shown to predict later conversion to PD dementia (Kehagia, Barker, & Robbins, Reference Kehagia, Barker and Robbins2010) and to be associated with lower quality of life (Lawson et al., Reference Lawson, Yarnall, Duncan, Breen, Khoo, Williams-Gray and Study Group2016; Schiehser et al., Reference Schiehser, Han, Lessig, Song, Zizak and Filoteo2009). Much of the cognitive literature in parkinsonian disorders has highlighted a profile characterized by poor attention (Génier Marchand et al., Reference Génier Marchand, Postuma, Escudier, De Roy, Pelletier, Montplaisir and Gagnon2018; Lawson et al., Reference Lawson, Yarnall, Duncan, Breen, Khoo, Williams-Gray and Study Group2016) and dysexecutive performance (Chahine et al., Reference Chahine, Weintraub, Hawkins, Siderowf, Eberly and Oakes2016; Dirnberger & Jahanshahi, Reference Dirnberger and Jahanshahi2013; Kudlicka, Clare, & Hindle, Reference Kudlicka, Clare and Hindle2011; Zgaljardic, Borod, Foldi, & Mattis, Reference Zgaljardic, Borod, Foldi and Mattis2003; Zgaljardic et al., Reference Zgaljardic, Borod, Foldi, Mattis, Gordon, Feigin and Eidelberg2006), but the neuropsychological impairments can be quite heterogeneous (Kehagia et al., Reference Kehagia, Barker and Robbins2010). Relatedly, performance-based measures of functional abilities (i.e., medication and financial management) are objective, ecologically valid lab-based assessments of daily living skills that have proven utility in detecting functional deficits in those with PD-MCI (Pirogovsky-Turk et al., Reference Pirogovsky-Turk, Schiehser, Obtera, Burke, Lessig, Song and Filoteo2014).
Two other classes of impactful nonmotor symptoms in PD are psychiatric and sleep syndromes. Depression, anxiety, apathy, and visual hallucinations are all common in PD (Aarsland, Marsh, & Schrag, Reference Aarsland, Marsh and Schrag2009; den Brok et al., Reference den Brok, van Dalen, van Gool, Moll van Charante, de Bie and Richard2015; Zgaljardic et al., Reference Zgaljardic, Borod, Foldi and Mattis2003) and are often associated with cognitive deficits (Dissanayaka et al., Reference Dissanayaka, Lawson, Yarnall, Duncan, Breen, Khoo and Burn2017; Goldman et al., Reference Goldman, Holden, Litvan, McKeith, Stebbins and Taylor2018; Hu et al., Reference Hu, Szewczyk-Królikowski, Tomlinson, Nithi, Rolinski, Murray and Ben-Shlomo2014). Sleep is frequently disrupted (Tandberg, Larsen, & Karlsen, Reference Tandberg, Larsen and Karlsen1998) and poor quality of sleep is related to reduced mental health (Borek, Kohn, & Friedman, Reference Borek, Kohn and Friedman2006). Although there are dozens of distinct sleep syndromes (Walker, Reference Walker2017), rapid eye movement (REM) sleep behavior disorder (RBD) is particularly relevant, as it is disproportionately prevalent in PD, with estimates ranging from 33 to 47% (Gagnon et al., Reference Gagnon, Bédard, Fantini, Petit, Panisset, Rompré and Montplaisir2002; Rolinski et al., Reference Rolinski, Szewczyk-Krolikowski, Tomlinson, Nithi, Talbot, Ben-Shlomo and Hu2014; Sixel-Döring, Trautmann, Mollenhauer, & Trenkwalder, Reference Sixel-Döring, Trautmann, Mollenhauer and Trenkwalder2011). RBD is a parasomnia, characterized by a lack of muscle atonia during the REM sleep phase, resulting in unwanted and occasionally violent motor behavior during dreams. RBD has been classified as an early nonmotor prodromal marker of both PD (Berg et al., Reference Berg, Postuma, Adler, Bloem, Chan, Dubois and Deuschl2015; Poewe, Reference Poewe2008) and Lewy body dementia (LBD; Berg et al., Reference Berg, Postuma, Bloem, Chan, Dubois, Gasser and Lang2014) – a disease with substantial neurobiological and phenotypic overlap with PD. Therefore, there is substantial clinical utility in the timely detection of RBD in order to inform early intervention. Moreover, the RBD syndrome itself (i.e., idiopathic RBD) is associated with cognitive deficits (Ferini–Strambi et al., Reference Ferini–Strambi, Di Gioia, Castronovo, Oldani, Zucconi and Cappa2004; Marques et al., Reference Marques, Dujardin, Boucart, Pins, Delliaux, Defebvre and Monaca2010), and it may account for a portion of the overall PD syndrome, as PD patients with RBD (PD/RBD+) have an altered motor profile (Postuma, Gagnon, Vendette, Charland, & Montplaisir, Reference Postuma, Gagnon, Vendette, Charland and Montplaisir2008), different patterns of neural activity on EEG (Gagnon et al., Reference Gagnon, Fantini, Bédard, Petit, Carrier, Rompré and Montplaisir2004), and a unique autonomic presentation (Postuma, Lang, Gagnon, Pelletier, & Montplaisir, Reference Postuma, Lang, Gagnon, Pelletier and Montplaisir2012) compared to PD patients without RBD (PD/RBD−), who can resemble healthy comparison (HC) participants across these variables.
With respect to cognitive outcomes in PD, RBD is a risk factor for dementia (Anang et al., Reference Anang, Gagnon, Bertrand, Romenets, Latreille, Panisset and Postuma2014; Nomura, Inoue, Kagimura, & Nakashima, Reference Nomura, Inoue, Kagimura and Nakashima2013; Postuma et al., Reference Postuma, Iranzo, Hu, Högl, Boeve, Manni and Puligheddu2019) and is associated with a higher prevalence of MCI (Gagnon et al., Reference Gagnon, Vendette, Postuma, Desjardins, Massicotte-Marquez, Panisset and Montplaisir2009; Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016). A number of studies have also examined overall cognitive performance in PD/RBD+ and many (Chahine, Amara, & Videnovic, Reference Chahine, Amara and Videnovic2017; Gong et al., Reference Gong, Xiong, Mao, Shen, Hu, Huang and Liu2014; Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Marques et al., Reference Marques, Dujardin, Boucart, Pins, Delliaux, Defebvre and Monaca2010; Rolinski et al., Reference Rolinski, Szewczyk-Krolikowski, Tomlinson, Nithi, Talbot, Ben-Shlomo and Hu2014; Sinforiani et al., Reference Sinforiani, Zangaglia, Manni, Cristina, Marchioni, Nappi and Pacchetti2006; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016), but not all (Bugalho & Paiva, Reference Bugalho and Paiva2011; Lavault et al., Reference Lavault, Leu-Semenescu, du Montcel, de Cock, Vidailhet and Arnulf2010; Plomhause et al., Reference Plomhause, Dujardin, Duhamel, Delliaux, Derambure, Defebvre and Monaca Charley2013; Sixel-Döring, Trautmann, Mollenhauer, & Trenkwalder, Reference Sixel-Döring, Trautmann, Mollenhauer and Trenkwalder2014), investigators have found that PD/RBD+ patients score lower on neuropsychological tests than PD/RBD− patients. However, these studies include a variety of methodological limitations including small sample sizes (e.g., Plomhause et al., Reference Plomhause, Dujardin, Duhamel, Delliaux, Derambure, Defebvre and Monaca Charley2013), the absence of a HC group (e.g., Bugalho & Paiva, Reference Bugalho and Paiva2011), the lack of performance-based measures of functional capacity (e.g., Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016), and the use of screening instruments rather than full neuropsychological batteries to assess cognition (e.g., Lavault et al., Reference Lavault, Leu-Semenescu, du Montcel, de Cock, Vidailhet and Arnulf2010). Those researchers that did assess multiple cognitive domains reported that PD/RBD+ underperformed relative to PD/RBD− patients in a variety of cognitive areas, but most predominantly in visuospatial/visuoconstructional skills (Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Marques et al., Reference Marques, Dujardin, Boucart, Pins, Delliaux, Defebvre and Monaca2010; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016), verbal learning (Erro et al., Reference Erro, Santangelo, Picillo, Vitale, Amboni, Longo and Barone2012; Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007), delayed memory (Erro et al., Reference Erro, Santangelo, Picillo, Vitale, Amboni, Longo and Barone2012; Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016), and executive functions (Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Sinforiani et al., Reference Sinforiani, Zangaglia, Manni, Cristina, Marchioni, Nappi and Pacchetti2006; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016). A final limitation of the RBD/cognition literature in PD is that, although psychiatric comorbidities are related to cognitive deficits, and RBD can be associated with higher levels of depression and anxiety (Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Rolinski et al., Reference Rolinski, Szewczyk-Krolikowski, Tomlinson, Nithi, Talbot, Ben-Shlomo and Hu2014; Sixel-Döring et al., Reference Sixel-Döring, Trautmann, Mollenhauer and Trenkwalder2011), no investigations to our knowledge measured and controlled for important psychiatric symptoms such as apathy when assessing RBD and cognition in PD.
We are only aware of two studies that have examined the relationship between RBD and cognition in a large PD sample compared to a HC sample using a full neuropsychological battery and measures of psychiatric functioning (Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016). Zhang and colleagues (Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016) recruited 32 PD/RBD+ patients, 42 PD/RBD− patients, and 36 HC participants from hospitals affiliated with Soochow University in Suzhou, China. RBD was diagnosed with the Mayo Sleep Questionnaire (Boeve et al., Reference Boeve, Molano, Ferman, Smith, Lin, Bieniek and Lucas2011) and the RBD Screening Questionnaire (RBDSQ). PD/RBD+ performed worse than PD/RBD− and HCs, and PD/RBD− performed worse than HC participants across a variety of cognitive tests, including tests of attention, episodic memory, visuospatial abilities, and executive functions; depression and anxiety did not differ between the two PD groups. Importantly, the authors did not administer any performance-based measures of functional capacity and did not measure apathy, which is a common psychiatric correlate of PD (Oguru, Tachibana, Toda, Okuda, & Oka, Reference Oguru, Tachibana, Toda, Okuda and Oka2010). Jozwiak and colleagues (Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017) reported on 53 PD/RBD+ patients, 40 PD/RBD− patients, and 69 HC participants recruited from Montreal General Hospital and nearby medical centers. RBD was diagnosed with polysomnography. PD/RBD+ performed worse on neuropsychological tests than PD/RBD− and a comparison group, but, contrary to expectations, PD/RBD− did not differ cognitively from HC participants. Moreover, the authors reported no differences between PD/RBD+ and PD/RBD− on sleep quality, depression, and anxiety measures, and there were no significant associations between cognitive performance and (a) sleep quality, (b) depression, and (c) anxiety. Finally, the study did not include performance-based tests of functional capacity and did not measure apathy in their sample.
Overall, the literature on the association between RBD and cognition in PD includes a variety of methodological limitations. Therefore, it is not surprising that findings are mixed in PD and a consensus has not been reached on the (a) cognitive profile and deficits associated with RBD, (b) influence of RBD on functional status, and (c) potential influence of important psychiatric comorbidities (such as apathy) on cognition in RBD. Therefore, the purpose of the current study was to address these issues by analyzing data from a large, well-characterized US sample characterized into three groups – PD/RBD+, PD/RBD−, and HC participants. Although the role of RBD in LBD is also of interest (Berg et al., Reference Berg, Postuma, Bloem, Chan, Dubois, Gasser and Lang2014), we focused our efforts on nonmotor symptoms in PD.
All participants completed a comprehensive neuropsychological evaluation, including performance-based tests of functional abilities, and we accounted for the potential mitigating influence of psychiatric symptoms on cognition. Based on the literature reviewed above, we aimed to examine the association between RBD symptomatology and cognitive, functional, and psychiatric outcomes. Specifically, we hypothesized that (1) PD/RBD+ patients would perform worse than PD/RBD− patients and HCs on tests of visuospatial/visuoconstructional skills, learning and memory, and executive functions. We also hypothesized that (2) the PD/RBD+ group would earn lower scores on performance-based measures of functional status compared to the PD/RBD− and HC groups. Finally, we hypothesized that (3) depression, anxiety, and apathy would be higher in the PD/RBD+ group compared to the PD/RBD− and HC groups, but that the relationship between RBD and cognitive performance and functional capacity would remain significant after controlling for psychiatric symptoms.
METHOD
Participants and Procedures
This retrospective investigation included 123 PD patients and 49 HC participants drawn from a longitudinal parent study on cognition in PD (results to be published in a subsequent paper). Study participants were recruited from the community and the Movement Disorders Clinic at the University of California, San Diego (UCSD) and VA San Diego Healthcare System, between 2009 and 2017. Participants provided informed consent and the study was approved by the local institutional review board.
PD patients were diagnosed by board-certified neurologists specializing in movement disorders based on the United Kingdom Parkinson’s Disease Society Bank Criteria (Hughes, Ben-Shlomo, Daniel, & Lees, Reference Hughes, Ben-Shlomo, Daniel and Lees1992). PD patients were excluded from the larger study if: (1) there were plausible secondary causes of PD, (2) they met criteria for dementia according to DSM-IV-TR (see Emre et al., Reference Emre, Aarsland, Brown, Burn, Duyckaerts, Mizuno and Dubois2007), or (3) they received scores of <124 on the Mattis Dementia Rating Scale (MDRS; Schmidt et al., Reference Schmidt, Freidl, Fazekas, Reinhart, Grieshofer, Koch and Lechner1994), as this cutoff score has been specifically recommended for screening dementia in PD (Llebaria et al., Reference Llebaria, Pagonabarraga, Kulisevsky, García-Sánchez, Pascual-Sedano, Gironell and Martínez-Corral2008). No participants for this present study were excluded based on this criterion. Furthermore, both PD and HC participants were excluded in the presence of other neurodegenerative disorders, a history of psychosis and/or untreated major depression, as well as history of treatment for substance abuse. PD patients receiving dopaminergic therapy (n = 118) during study participation were tested while on medication; levodopa equivalent dosage (LED) is presented in Table 1 (Tomlinson et al., Reference Tomlinson, Stowe, Patel, Rick, Gray and Clarke2010). Participants also self-reported any current clonazepam or other benzodiazepine use. Motor symptoms were assessed using Part III of the Unified Parkinson’s Disease Rating Scale (UPDRS; Goetz et al., Reference Goetz, Tilley, Shaftman, Stebbins, Fahn, Martinez-Martin and LaPelle2008) and a modified version of the Hoehn and Yahr rating scale (Goetz et al., Reference Goetz, Poewe, Rascol, Sampaio, Stebbins, Counsell and Seidl2004) to denote the disease stage. Moreover, PD-MCI status was also determined based on Level II criteria of the Movement Disorder Society Task Force Guidelines (Litvan et al., Reference Litvan, Goldman, Tröster, Schmand, Weintraub, Petersen and Aarsland2012). Participants completed a comprehensive neuropsychological test battery and additional neuropsychiatric and clinical measures at baseline and 2–3 years later for follow-up. Baseline neuropsychological, clinical, and functional assessments were used in the current analyses.
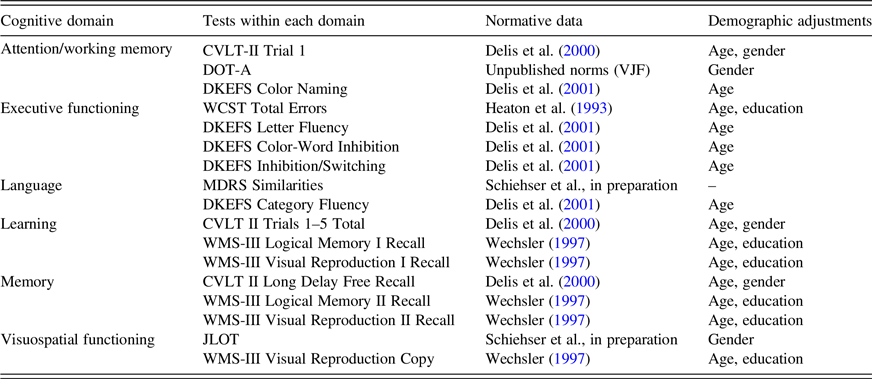
Neuropsychological assessment battery

CVLT-II = California Verbal Learning Test – Second Edition; DOT-A = Ascending Digit Order Test; DKEFS = Delis–Kaplan Executive Function System; WCST = Wisconsin Card Sorting Test; MDRS = Mattis Dementia Rating Scale; WMS-III = Wechsler Memory Scale-Third Edition; JLOT = Judgment of Line Orientation Test.
MEASURES
Rapid eye movement sleep behavior disorder
The RBDSQ (Stiasny-Kolster et al., Reference Stiasny-Kolster, Mayer, Schäfer, Möller, Heinzel-Gutenbrunner and Oertel2007) was used to assess self-reported presence and severity of RBD symptoms in all participants and to classify participants into clinically probable RBD-positive (pRBD+) and RBD-negative (pRBD−) groups, as detailed below. The RBDSQ has demonstrated validity in PD (sensitivity = 0.842, specificity = 0.962; Nomura, Inoue, Kagimura, Uemura, & Nakashima, Reference Nomura, Inoue, Kagimura, Uemura and Nakashima2011; Wang et al., Reference Wang, Wang, Yang, Wu, Zhao and Zhao2015).
Cognition
All participants completed a comprehensive neuropsychological assessment battery, which included measures commonly used for cognitive assessment of PD patients (Pirogovsky-Turk et al., Reference Pirogovsky-Turk, Moore, Filoteo, Litvan, Song, Lessig and Schiehser2017). The battery measured cognition in the following domains: attention/working memory, executive functioning, language, learning, memory, and visuospatial functioning. All raw scores were converted to standardized T-scores using published normative procedures and demographically corrected norms when available (see Table 1 for list of measures by cognitive domains). A global T-score composite was also created by averaging across all individual test scores.
Functional Skills
The Medication Management Abilities Assessment (MMAA; Patterson et al., Reference Patterson, Lacro, McKibbin, Moscona, Hughs and Jeste2002) was used as a performance-based assessment of participants’ capacity to carry out a prescribed medication regimen. The UCSD Performance-Based Skills Assessment (UPSA; Patterson, Goldman, McKibbin, Hughs, & Jeste, Reference Patterson, Goldman, McKibbin, Hughs and Jeste2001) finance subtest was used to measure performance-based functional capacity in the domain of financial management. Caregivers of PD patients completed the Instrumental Activities of Daily Living Scale (IADL; Lawton & Brody, Reference Lawton and Brody1969). Total scores were used for all functional skills measures; higher scores reflect better performance and functioning.
Neuropsychiatric Symptoms
State Trait Anxiety Inventory (STAI; Spielberger, Gorsuch, Lushene, Vagg, & Jacobs, Reference Spielberger, Gorsuch, Lushene, Vagg and Jacobs1983) and Trait and State total scores were used to measure anxiety (Barnes, Harp, & Jung, Reference Barnes, Harp and Jung2002). Severity of depressive symptoms and apathy were measured using the total scores of the Geriatric Depression Scale (GDS; Yesavage et al., Reference Yesavage, Brink, Rose, Lum, Huang, Adey and Leirer1982) and the Apathy Scale (Starkstein et al., Reference Starkstein, Mayberg, Preziosi, Andrezejewski, Leiguarda and Robinson1992), respectively. All measures have demonstrated reliability and validity in PD (Dissanayaka et al., Reference Dissanayaka, Lawson, Yarnall, Duncan, Breen, Khoo and Burn2017; Leentjens et al., Reference Leentjens, Dujardin, Marsh, Martinez-Martin, Richard, Starkstein and Goetz2008a, Reference Leentjens, Dujardin, Marsh, Martinez-Martin, Richard, Starkstein and Goetz2008b). Higher scores on all neuropsychiatric measures reflect higher symptomatology.
Statistical Analyses
PD patients were classified into pRBD+ (n = 58) and pRBD− (n = 65) groups using an established cutoff score of 6 on the RBDSQ (Nomura et al., Reference Nomura, Inoue, Kagimura, Uemura and Nakashima2011). Six HCs met criteria for pRBD based on this cutoff and were excluded from the analyses. Thus, a final sample of 172 (n = 49 HCs) participants were included. Given that item 6 on the RBDSQ directly assesses the cardinal symptom of RBD (i.e., movements while dreaming), we examined the utility of this item in predicting probable RBD status. Indeed, item 6 on the RBDSQ pertaining to dream enactment behavior distinguished the PD groups; odds of a probable RBD diagnosis increase by a factor of 4.71 given a positive response to item 6 (OR = 4.714, Wald z = 15.82, df = 1, p < .001).
Independent samples t-test, univariate analysis of variance (ANOVA), nonparametric Kruskal–Wallis one-way ANOVA (for nonnormally distributed variables), and chi-square analyses were conducted to examine differences in demographic and clinical characteristics between groups. Partial correlations, with cognitive diagnosis as a covariate, demonstrated comparable associations between pRBD status and individual cognitive domains to correlations that did not include cognitive status as a covariate. Therefore, more parsimonious models unadjusted for cognitive diagnosis are reported. We used univariate analysis of covariance (ANCOVA) and multivariate ANCOVA (MANCOVA) to examine differences between PD/pRBD+, PD/pRBD−, and HC participants on global neurocognitive functioning and individual cognitive domains, controlling for the effects of psychiatric symptom severity (i.e., simultaneously covarying for scores on the GDS, Apathy Scale, and trait anxiety component of the STAI; note, given the strong association between state and trait anxiety total scores, we only chose to covary for trait anxiety). Of note, we also performed univariate ANCOVA to compare groups on psychiatric and clinical variables given the significant differences in sex distribution between the PD and HC groups. However, analyses with and without sex as a covariate did not differ; thus, the results from analyses without sex as a covariate are reported. Tukey’s HSD or Bonferroni-adjusted alpha levels were used to evaluate statistical significance of pair-wise comparisons within each family-wise comparison across groups, that is, cognition, functional capacity, and psychiatric symptom severity.
RESULTS
Demographic and Clinical Comparison
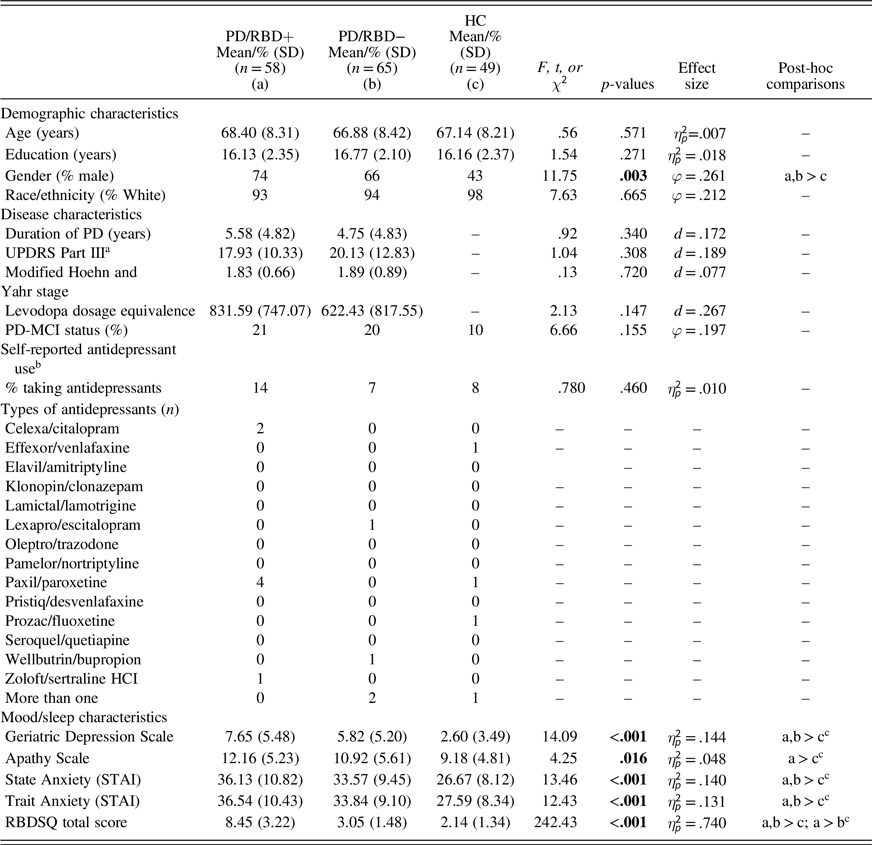
The PD/pRBD+, RD/pRBD−, and HC groups did not significantly differ in age, education, MCI status, and race/ethnicity (ps > .10). There were significant differences, however, in sex distribution (χ 2(2) = 11.75, p = .003), with a significantly greater proportion of women in the HC group compared to both PD groups. There were significant differences between the groups on the RBDSQ (F(2, 169) = 242.43, p < .001,  $\eta _p^2$= .74), with both PD/pRBD+ and PD/pRBD− groups reporting greater RBD symptoms compared to the HC group, and the PD/pRBD+ group also reporting greater RBD symptoms compared to the PD/pRBD− group. None of the participants in the study reported any current use of clonazepam and there were no group differences in self-reported antidepressant use.
Within the PD group, there was no difference between RBD groups in duration of PD (t (121) = −.96, p = .340), motor symptoms, as assessed by Part III of UPDRS (t (117) = 1.02, p = .308), the modified Hoehn and Yahr rating scale (t (116) = .36, p = .720), and LED (t (118) = −1.46, p = .147). Of note, there were also no significant differences between PD RBD groups in their medication status (on vs. off) while completing the UPDRS (χ 2(1) = .024, p = .878). Table 2 shows the demographic comparison between the groups and descriptive statistics for significant outcomes of interest.
Participant demographics and group statistics

UPDRS = Unified Parkinson’s Disease Rating Scale; STAI = State/Trait Anxiety Inventory; RBDSQ = RBD Screening Questionnaire; PD-MCI = Parkinson’s disease-mild cognitive impairment status.
Bold font denotes p < .05.
a No on versus off medication differences between groups.
b PD/RBD+: n = 52; PD/RBD−: n = 59; HC: n = 49.
c Tukey’s HSD.
PD and RBD effects on neuropsychiatric symptoms
State anxiety (F(2, 165) = 13.46, p<.001, $\eta _p^2$ = .14), trait anxiety (F(2, 165) = 12.43, p < .001, $\eta _p^2$ = .13), and depression severity (F(2, 167) = 14.09, p < .001, $\eta _p^2$ = .14) differed significantly between PD patients and HCs. Tukey’s post-hoc analyses indicated that the PD/pRBD+ and PD/pRBD− groups reported greater current depression and anxiety compared to the HCs. Similarly, there were significant differences between the groups on their scores on the Apathy Scale (F(2, 169) = 4.25, p = .016, $\eta _p^2$ = .05), with Tukey’s post-hoc comparison indicating that the PD/pRBD+ group endorsed greater severity of symptoms of apathy as compared to the HCs. No significant differences were found between the PD/pRBD+ and PD/pRBD− groups on psychiatric outcomes.
PD and RBD effects on neuropsychological performance
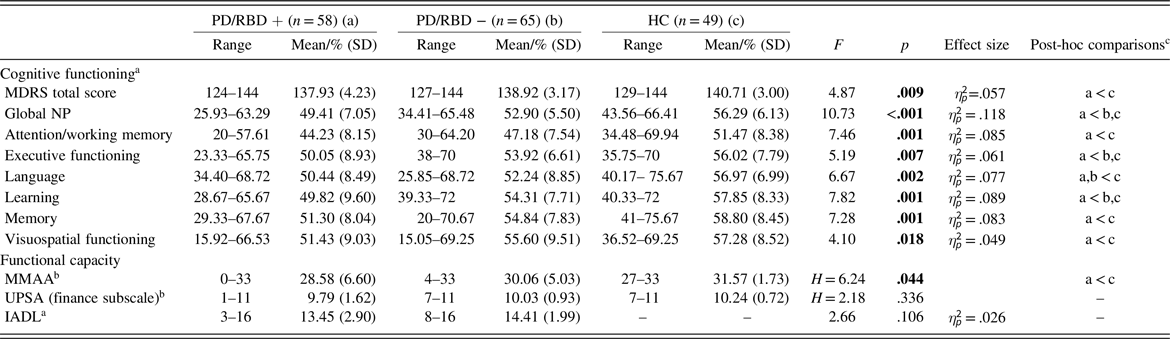
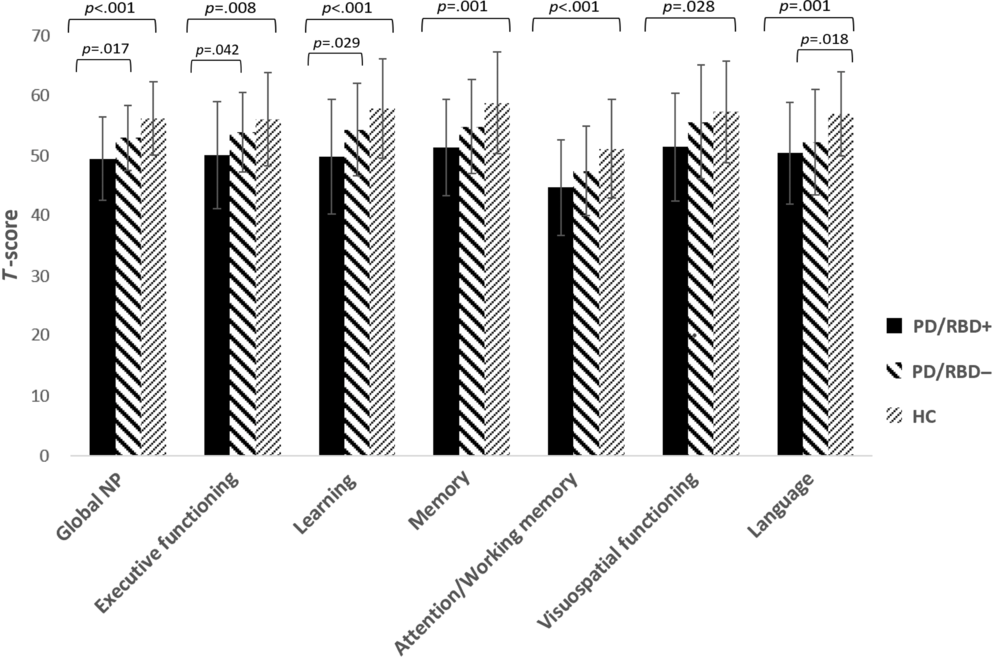
A three-group ANOVA, controlling for psychiatric symptom severity (depression, trait anxiety, and apathy), demonstrated a significant difference between the groups on global neurocognitive performance (F(2, 160) = 10.73, p < .001, $\eta _p^2$ = .12; see Table 3 for statistics). Post-hoc analyses using Bonferroni adjustments for multiple comparisons demonstrated that PD/pRBD+ patients exhibited poorer global neurocognitive functioning compared to the PD/pRBD− patients (p = .017) and HCs (p<.001). MANCOVA demonstrated significant differences among the groups on individual cognitive domains (F(12, 310) = 2.30, p = .008, Λ = .84, $\eta _p^2$ = .08), with effects across domains as follows: attention/working memory (F(2, 160) = 7.46, p = .001, $\eta _p^2$ = .09), executive functioning (F(2, 160) = 5.19, p = .007, $\eta _p^2$ = .06), language (F(2, 160) = 6.67, p = .002, $\eta _p^2$ = .08), learning (F(2, 160) = 7.82, p = .001, $\eta _p^2$ = .09), memory (F(2, 160) = 7.28, p = .001, $\eta _p^2$ = .08), and visuospatial functioning (F(2, 160) = 4.10, p = .018, $\eta _p^2$ = .05; see Figure 1). Specifically, Bonferroni-adjusted post-hoc analyses demonstrated that the PD/pRBD+ group had poorer executive functioning and learning performance compared to the PD/pRBD− group (ps < .05). Moreover, PD/pRBD+ patients had poorer neuropsychological functioning, generalized across all individual cognitive domains, as compared to HCs (ps<.03), while the PD/pRBD- patients had significantly lower scores compared to the HCs in the language (p = .018), and attention/working memory (p = .049) domains. Although not statistically significant, the PD/pRBD+ group had marginally significantly lower visuospatial functioning score compared to the PD/pRBD− group (p = .066). No other significant differences in cognitive performance were found.
Group differences on cognitive and functional outcomes

MDRS = Mattis Dementia Rating Scale; Global NP = global neuropsychological performance (calculated as an average of all individual cognitive measures); MMAA = Medication Management Abilities Assessment; UPSA = UCSD Performance-Based Skills Assessment; IADL = Instrumental Activities of Daily Living Scale. All cognitive domains report results using T-scores (M ± SD = 50 ± 10, range 20–80), except for MDRS total score, which is expressed as a total raw score (range 0–144).
Bold font denotes p<.05.
a Statistics reported from models controlling for psychiatric symptom severity (depression, trait anxiety, and apathy).
b Nonparametric Kruskal–Wallis test.
c Bonferroni adjustment for multiple comparisons.
PD/RBD status effects on neurocognitive performance.

PD and RBD effects on functional capacity
Nonparametric Kruskal–Wallis one-way ANOVA demonstrated no statistically significant group differences on performance-based functional capacity, as measured by the UPSA-Financial subscale (H(2) = 2.18, p = .336). However, there were significant group differences on MMAA (H(2) = 6.24, p = .044), such that the PD/pRBD+ group demonstrated significantly poorer performance as compared to the HCs using Bonferroni correction (p = .038). No other significant group differences in financial functional capacity were found. A two-group ANCOVA, controlling for psychiatric symptom severity, demonstrated no significant difference on IADL scores between PD/pRBD+ and PD/pRBD− patients F(1, 100) = 2.66, p = .11, $\eta _p^2$ = .03).
DISCUSSION
The primary objective of the current study was to characterize PD patients neuropsychologically based upon the presence or absence of RBD by examining differences in cognitive performance, psychiatric symptoms, and functional capacity between PD patients with and without probable RBD as well as compared to HCs. Our results indicated that the presence of RBD is associated with poorer neuropsychological functioning in PD. Specifically, pRBD in PD is associated with greater severity of apathy, worse cognition across all domains, and poorer functional capacity compared to healthy adults. Moreover, individuals with PD and pRBD demonstrated worse overall cognition, executive functioning, and learning compared to PD patients without RBD. Importantly, our study examined the unique variance in cognitive functioning accounted for by pRBD by controlling for psychiatric symptom severity; this suggests that the association between self-reported symptoms of RBD and cognition cannot be explained by symptoms of depression, anxiety, or apathy.
The current findings indicated that the presence of pRBD is associated with not only the severity of neurocognitive symptoms but also the neuropsychological profile. In this nondemented sample, PD patients without pRBD performed similarly to HC participants, with the exception of worse performance in the language and attention/working memory domains. However, in those nondemented PD patients with pRBD, a striking pattern of worse performances emerged across multiple domains, including executive functioning and verbal learning. Moreover, compared to PD patients without pRBD, PD/pRBD+ patients had poorer global neurocognitive functioning, with poorer performance on executive functioning and learning domains driving this relationship. Of note, PD/pRBD+ participants’ lowest cognitive performance was evidenced within the domain of attention and working memory. Differences in cognitive performance between the PD groups may partly be explained by the PD/RBD+ group evidencing their lowest scores within the domain of attention/working memory, which is known to subserve performance across higher-order functions such as executive functioning and learning. Moreover, previous studies have identified a profile characterized by poor attention in parkinsonian disorders as an important early cognitive feature of patients with RBD who later develop MCI and dementia (Génier Marchand et al., Reference Génier Marchand, Postuma, Escudier, De Roy, Pelletier, Montplaisir and Gagnon2018). Together, these results support our hypothesis of a unique cross-sectional association between pRBD and worse cognitive performance in nondemented PD patients, although the direction of this relationship remains unclear. These findings are consistent with previous studies associating RBD in PD with poorer verbal learning (Erro et al., Reference Erro, Santangelo, Picillo, Vitale, Amboni, Longo and Barone2012; Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007) and executive functioning (Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Sinforiani et al., Reference Sinforiani, Zangaglia, Manni, Cristina, Marchioni, Nappi and Pacchetti2006; Vendette et al., Reference Vendette, Gagnon, Décary, Massicotte-Marquez, Postuma, Doyon and Montplaisir2007; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016) compared to HCs and/or PD patients without RBD, as well as imaging studies implicating abnormalities in frontal and temporal regions and microstructural pathways subserving these cognitive functions (Ansari, Rahmani, Dolatshahi, Pooyan, & Aarabi, Reference Ansari, Rahmani, Dolatshahi, Pooyan and Aarabi2017; Ford et al., Reference Ford, Duncan, Firbank, Yarnall, Khoo, Burn and O’Brien2013; Lim et al., Reference Lim, Shin, Lee, Nam, Lee and Kim2016).
Though the presence of pRBD in PD was associated with lower scores across multiple cognitive domains in the current study, the average performance of the PD/pRBD+ group across these domains was not impaired. Furthermore, prevalence of PD-MCI was similar across the pRBD groups, which is inconsistent with previous studies (Gagnon et al., Reference Gagnon, Vendette, Postuma, Desjardins, Massicotte-Marquez, Panisset and Montplaisir2009; Jozwiak et al., Reference Jozwiak, Montplaisir, Latreille, Bourgouin, Gagnon, Postuma and Chouinard2017; Zhang et al., Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016). Compared to participants in these previous studies, participants within the current study endorsed higher levels of education (≥16 years on average), which may partially explain these findings. Similarly, average neuropsychiatric symptom severity scores do not indicate clinically elevated levels of depression or apathy within the PD groups.
With respect to functional skills, significant differences in performance-based medication management abilities were revealed between the PD/pRBD+ and HCs but not between PD/pRBD− and HCs. These findings suggest that there is a subgroup of nondemented individuals with PD – those with pRBD – with suboptimal functional medication management skills. This is important given that suboptimal medication adherence has been noted extensively in PD literature and linked to negative prognoses (Grosset, Bone, & Grosset, Reference Grosset, Bone and Grosset2005; Kulkarni et al., Reference Kulkarni, Balkrishnan, Anderson, Edin, Kirsch and Stacy2008; Leopold, Polansky, & Hurka, Reference Leopold, Polansky and Hurka2004). Given that cognitive impairment is associated with medication adherence in PD (Daley, Myint, Gray, & Deane, Reference Daley, Myint, Gray and Deane2012), findings from the current study highlight the clinical and scientific importance of evaluating PD patients for RBD to identify those at greatest risk for both cognitive and functional deficits related to medication management.
Regarding financial functional skills, results did not support the hypothesis that the PD/pRBD+ group would perform worse than the PD/pRBD− group. It may be that RBD-mediated cognitive deficits in PD are not severe enough to have a measurable impact on overlearned behaviors such as handling routine financial transactions (e.g., counting change, writing checks). Alternatively, it is possible that RBD affects financial skills in PD, but our functional assessment was not sensitive enough to detect this effect. Future research that focuses on RBD in relation to additional performance-based measures of functional capacity may yield important information.
Overall, the limited differences between the nondemented PD patients without pRBD and healthy adults across the majority of study outcomes are consistent with prior studies suggesting the presence of pRBD in individuals with PD as an indicator of a more severe subtype and greater risk for poorer outcomes (Fereshtehnejad et al., Reference Fereshtehnejad, Romenets, Anang, Latreille, Gagnon and Postuma2015). In a future paper, we will report on a longitudinal investigation examining the enduring effects of these pRBD-related outcomes in PD. The difference in language and attention/working memory functioning between the PD groups, regardless of pRBD status, and HCs, however, suggests that performance in this domain in linked to non-RBD pathology.
There are certain limitations of the current study that need to be considered. The study utilized convenience sampling and participants were primarily White and highly educated, thereby limiting the generalizability of the findings. There was greater representation of women in the HC group as compared to the PD groups; however, this is consistent with the well-documented gender difference noted within the PD literature (Van Den Eeden et al., Reference Van Den Eeden, Tanner, Bernstein, Fross, Leimpeter, Bloch and Nelson2003). Polysomnography was not used to confirm a definitive diagnosis of RBD and determination of probable RBD was not verified by a bed partner; however, the RBDSQ cutoff score used to identify RBD+ patients (≥6) has been shown to have high sensitivity and specificity in studies validating the measure in PD patients (Nomura et al., Reference Nomura, Inoue, Kagimura, Uemura and Nakashima2011; Wang et al., Reference Wang, Wang, Yang, Wu, Zhao and Zhao2015). Our results add to the evidence base supporting the utility of the RBDSQ as a practical and unobtrusive alternative to polysomnography and reports from informants—who may have limited availability or knowledge of the patient’s sleep behaviors—in assessing RBD in PD patients. Although Zhang and colleagues (Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016) also utilized the RBDSQ to classify their sample, they applied a different cutoff score (7) than the established cutoff of 6 (Nomura, Inoue, Kagimura, Uemura, & Nakashima, Reference Nomura, Inoue, Kagimura, Uemura and Nakashima2011) utilized in our study. Moreover Zhang et al. (Reference Zhang, Chen, Yang, Zhang, Fu, Shen and Liu2016) did not adjust for multiple comparisons, which may partially explain any inconsistencies between the two studies.
Despite these limitations, our findings suggest that PD/pRBD+ patients have a more impaired cognitive profile than PD/pRBD− patients and healthy adults and evidence poorer functioning compared to healthy adults. Specifically, compared to PD patients without pRBD, PD/pRBD+ patients have greater levels of cognitive impairment specific to learning and executive functioning. These findings underscore the importance of RBD assessment for improved detection and treatment of neuropsychological impairment. Recognition of the association between RBD and cognition, as well as adopting targeted interventions (e.g., cognitive training), could positively influence cognition, functional status, and mood in PD.
ACKNOWLEDGEMENTS
This work was supported by VA CSR&D (grant no: I01 CX000813; PI: Filoteo) and RR&D (grant no: I01 RX001691; PI: Schiehser) Merit Awards. Zanjbeel Mahmood, M.S., and Ryan Van Patten, Ph.D. are supported by the National Institute of Mental Health Institutional Training Grant in Geriatric Mental Health (grant no: T32 MH 19934, PIs: Dilip V. Jeste, M.D.; Elizabeth W. Twamley, Ph.D.).
CONFLICT OF INTEREST
The authors report no conflict of interests or financial disclosures.