



Dysphagia refers to the inability to safely and effectively transport food from the mouth to the stomach to obtain sufficient nutrients and water, which leads to difficulty in eating(Reference Sasegbon, Cheng and Hamdy1). Forty-six 3–59 % of stroke patients are complicated by dysphagia(Reference D’Netto, Rumbach and Dunn2), and 11–50 % of patients have dysphagia symptoms lasting more than 6 months(Reference Pacheco-Castilho, Vanin and Dantas3). Dysphagia after stroke can lead to complications,(Reference Minelli, Luvizutto and Cacho4) such as aspiration pneumonia, dehydration and malnutrition in patients, affecting nutrient intake and quality of life and hindering the progress of rehabilitation(Reference Jones, Colletti and Ding5).
Rehabilitation treatment for patients with dysphagia is a hot topic of concern(Reference Nakao-Kato and Rathore6), and dietary nutrition is the primary issue to be addressed in rehabilitation treatment(Reference Zielińska-Nowak, Cichon and Saluk-Bijak7). When patients leave the acute stage (such as after a stroke or neurological injury), their swallowing function begins to partially recover but is still insufficient to meet all nutritional requirements(Reference Grefkes and Fink8). During this transitional period, the commonly used nutritional support methods in clinical practice mainly include long-term indwelling of nasogastric tubes, intermittent tube feeding and thickened feeding(Reference Wu, Zhu and Zhou9). Although long-term indwelling of nasogastric tubes can ensure nutritional supply, it is prone to complications such as nasal mucosa damage and gastroesophageal reflux and may delay the natural recovery of swallowing function(Reference Wang, Tai and Hu10). In contrast, intermittent tube feeding and food trait adjustment have significant advantages. Intermittent tube feeding is only carried out when nutritional supplementation is needed during meals or at night. The tube is inserted into the oesophagus or stomach through the mouth or nose and removed immediately after the meal is completed(Reference Tanprasert, Tharathipphayakun and Ko-Iam11). This method can reduce the adverse reactions of long-term indwelling. Thickened feeding refers to the improvement of the safety and effectiveness of oral consumption by adding thickeners(Reference Wenzl, Schneider and Scheele12). This method is more consistent with physiological eating patterns and can also promote swallowing function training. However, an increase in the viscosity of the liquid may reduce the patient’s fluid intake, leading to a risk of dehydration for the patient(Reference Thiyagalingam, Kulinski and Thorsteinsdottir13).
It is worth noting that dehydration is widespread among patients with dysphagia but is often overlooked(Reference Tanrıverdi, Heybeli and Çalım14). Most existing studies focus on improving nutritional status and swallowing function, with significantly insufficient attention paid to hydration status. Especially when using thickened liquids, patients often reduce their water intake due to the uncomfortable taste. However, the relationship between this phenomenon and dehydration biochemical indicators still lacks systematic research. Intermittent tube feeding may theoretically better maintain the hydrated state, but the relevant evidence remains limited.
Based on this, this study aims to systematically compare the effects of intermittent tube feeding and thickened feeding on the risk of dehydration in patients with dysphagia after stroke. The study will focus on objective indicators, such as plasma osmotic pressure, and simultaneously evaluate the differential effects of the two treatment methods on nutritional status and swallowing function. The research results will provide an important basis for formulating individualised nutritional support plans in clinical practice and have significant clinical significance for improving patients’ rehabilitation and quality of life.
Methods
Research object
Purposive sampling method was adopted. Patients with dysphagia after stroke who were admitted to the Rehabilitation Department of the Affiliated Brain Hospital of Nanjing Medical University and the Rehabilitation Department of Zhongshan Rehabilitation Branch of the First Affiliated Hospital of Nanjing Medical University from March 2023 to October 2023 were selected. Inclusion criteria: (1) meeting the diagnostic criteria for stroke formulated by the Neurology Branch of the Chinese Medical Association and confirmed as cerebral infarction or cerebral haemorrhage by CT or MRI; (2) the drinking water test rating of the depression field is grade 3 or above; (3) vital signs are stable and the condition is in a stable period. (4) Age ≥ 18 years old, conscious and capable of cooperating to complete relevant treatment and nursing work; (5) both the patient and their family members were informed and voluntarily participated in the investigation. Exclusion criteria: (1) those with severe renal failure or heart failure who need to strictly limit fluid intake; (2) space-occupying lesions in the oral cavity and throat; (3) those undergoing parenteral nutrition or enterostomy; (4) those who are intolerant to intermittent catheterisation; (5) those who request to withdraw during the research process and (6) those whose conditions deteriorate during the participation period and who are unable to continue.
Research protocol
Grouping method
This study is a prospective observational study. The grouping was based on the nutritional intake mode after clinical decision-making. Forty-eight patients with dysphagia after stroke were selected and divided into the intermittent tube feeding group (intermittent oral tube feeding and intermittent nasal tube feeding) with twenty-four cases and the thickened feeding group with twenty-four cases.
Conventional treatment
Both groups received conventional rehabilitation training for dysphagia. (1) Oral sensory and motor training: This includes training of the facial muscle groups, pharyngeal ice stimulation training, laryngeal lifting training, Mendelssohn training and tongue pressure resistance feedback training. It is conducted twice a day, for 20 min each time. (2) Breathing and coughing reflex training: Guide the patient to perform pursed-lip breathing to improve respiratory function, that is, inhale through the nose and then exhale slowly through pursed-lip breathing (whistling) while contracting the abdomen. The ratio of inhalation to exhalation time is 1:2 or 1:3. (3) Sensory stimulation training: K-point stimulation, temperature perception stimulation, olfactory stimulation, gustatory stimulation, etc. (4) Low-frequency electrical stimulation therapy: The VitalStim neuromuscular low-frequency electrical stimulation device produced by Chattanooga Company of the USA is used for treatment. The stimulation electrodes are placed on both sides of the midline of the suprahyoid muscle group in the patient’s neck to stimulate the extralingual muscles and pharyngeal muscle groups. Select a bidirectional square wave with a width of 700 ms, a fixed frequency range of 30–80 Hz and a stimulation intensity of 7–10 mA. Do it once a day for 30 min each time.
Intermittent tube feeding method
The group was fed food and water through intermittent tube feeding. (1) Explain to the patient the purpose, methods, importance, precautions of intermittent tube feeding and obtain the patient’s cooperation. (2) Preparations: No. 14 gastric tube, food, cooking oil, warm water, 5 ml syringe, stethoscope and food injector. (3) Position: The patient should be in a sitting or semi-sitting position (with the head of the bed raised by at least 30 degrees). (4) Clean the secretions in the mouth and nose to ensure oral hygiene. (5) Intubation: Wear clean membrane gloves to smooth the front end of the gastric tube. Hold the front end of the gastric tube and insert it along the mouth or nasal cavity. When the insertion is 10–15 cm, instruct the patient to perform a swallowing action. If the patient has no swallowing reflex or the swallowing initiation is slow, a swallowing induction action (Mendelle technique) can be combined. Along with the swallowing action, the gastric tube can be smoothly inserted through the oesophagus into the stomach. The insertion length of the gastric tube is 45–55 cm. (6) Make sure the gastric tube is in the stomach to prevent it from mistakenly entering the trachea: draw back gastric juice, listen for the sound of gas passing through water and check for any bubbles. If choking, breathing difficulties, cyanosis or other conditions occur during intubation, it may accidentally enter the trachea. Remove it immediately, rest for a moment and then reinsert it. (7) Remove the gastric remnant, fix the gastric tube and use the high-lift platform method to secure it to the patient’s corner of the mouth. (8) Inject food paste or warm water. Intubate 3–4 times a day according to the patient’s condition. After the feeding is completed, remove the gastric tube, clean the mouth and nasal cavity. (9) After the gastric tube is used, rinse it with warm boiled water, dry it in the shade and store it. Place the patient, ask about their feelings and instruct them to maintain the eating position for 20 to 30 min.
Thickening feeding method
The group was fed food and water through the thickened feeding method. (1) The safety and efficacy of patients’ food intake were evaluated based on videofluoroscopic swallowing study, and the appropriate mouthful size and viscosity for patients’ food intake were determined. (2) Liquid foods were prepared using Sous S (a thickener based on xanthan gum). 1 g, 2 g and 3 g of Sous S were, respectively, added to 100 ml of water to make the liquid into three thicknesses: low, medium and high. For solid foods, first reduce the hardness of the food. Add an appropriate amount of liquid to the solid food and blend it into a paste through a mixer. During the blending process, add Susu U to make the food into three thicknesses: fine puree, fine filling and soft food. (3) Select the consistency of solids and liquids suitable for the patient to consume based on the results of swallowing angiography. When eating, the patient was guided to adopt an appropriate eating position. According to the condition, try to use an upright sitting position or a semi-sitting position. Follow the principle of taking a bite and choose an appropriate speed to eat to ensure the safety of swallowing. Adopt appropriate eating postures that facilitate swallowing, such as swallowing with the head back, head down and head turned and keep the mouth clean, supplemented by psychological guidance.
Research tools
Laboratory inspection
Plasma osmotic pressure
Plasma osmotic pressure (mmol/l) = 1·86 × (blood sodium + blood potassium) + 1·15 × blood glucose + urea nitrogen + 14(Reference Hooper, Abdelhamid and Ali15). An osmotic pressure of 275–295 mmol/l indicated a normal hydration state. A concentration of 295–300 mmol/l indicated a tendency to dehydrate. A concentration of ≥ 300 mmol/l indicated dehydration. Due to differences in regions, races and dietary structures, the reference value of osmotic pressure varied slightly. Relevant research from Japan, also in the Asian region, was adopted, and the critical value for dehydration was set at 295 mmol/l(Reference Shimizu, Kinoshita and Hattori16).
Total serum protein and Hb
The nutritional function of patients was evaluated by using total serum protein and Hb. Peripheral venous blood was collected from the patient in the early morning for blood biochemical tests.
Questionnaire survey
General Information Questionnaire
The general information questionnaire was adopted, including age, gender, educational level, medical expense payment method and primary caregiver. Information related to diseases includes the type of stroke, the grade of the Wada drinking water test, the history of chronic diseases and medication use.
Functional Oral Intake Scale
This scale was proposed by the Swallowing Research experimental team of the University of Florida in 2005 and was localised and revised by Zhu Yafang et al. in 2017. It is an assessment tool reflecting the current oral feeding function level of patients with dysphagia. A comprehensive assessment is conducted by observing the types and methods of food intake and the patient’s choking cough reactions, etc. FOIS was divided into seven grades. Grade 1: Inability to consume orally; Level 2: Dependent on tube feeding, with the minimum attempt to consume food or liquid; Level 3: Dependent on tube feeding, oral intake of a single texture of food or liquid; Level 4: Eating food of a single texture entirely orally; Level 5: Completely consuming a variety of textures of food orally, but requiring special preparation or compensation; Level 6: Completely oral feeding does not require special preparation, but there are specific food restrictions. Level 7: There are no restrictions on complete oral feeding. This scale is not restricted by the patient’s state of consciousness. By recording the feeding behaviours that have occurred in the patient, it can achieve dynamic assessment of the patient’s oral feeding function. The consensus validity of this scale is relatively high, with an inter-evaluator reliability of 0·862(Reference Crary, Carnaby and Shabbir17).
Swallowing Quality of Life Scale
This scale was initially developed by the McHorney research team in 2000 and finally revised in 2002. It was highly specific and specifically designed to assess the quality of life of patients with dysphagia, providing a quantitative tool for related research and clinical practice(Reference Duncan, McAuley and Walshe18). The Likert five-point scoring method was adopted. According to the frequency of symptom occurrence, they were rated from 1 to 5 points from severe to mild, with a total score ranging from 44 to 220 points. The higher the score, the better the quality of life for dysphagia. The Cronbach’s α coefficient range of the Chinese version of this scale was 0·708–0·933 (P < 0·01), the reliability correlation coefficient range among evaluators was 0·945–0·990 (P < 0·01) and the test-retest reliability correlation coefficient range was 0·965–0·992 (P < 0·01). The correlation coefficient of each item with its field ranged from 0·723 to 0·982 (P < 0·01), and the correlation coefficient of each item with its dimension was higher than that of other dimensions. Since the intermittent tube feeding group in this study could not achieve oral feeding, the ‘feeding time’ dimension was excluded in this study, and the remaining ten dimensions and forty-two items were investigated.
Numerical Rate Scale
NRS was used to assess the degree of thirst in patients. The NRS scale consisted of 11 numbers ranging from 0 to 10. Patients chose the appropriate number based on their subjective feelings to represent their sensation of thirst. The scoring criteria ranged from 0 to 10 points. A score of 0 indicates no thirst, 1–3 indicated mild thirst, 4–7 indicates moderate thirst and 8–10 indicated severe thirst. The higher the score of thirst degree, the more severe the degree of thirst. This method was simple and easy to understand and was more widely accepted by people with weak comprehension or poor eyesight. The correlation coefficient of the scale ranged from 0·77 to 0·91, and the test-retest reliability ranged from 0·67 to 0·85, indicating good reliability and validity.
Data collection
The researchers elaborated in detail on the purpose, content and significance of the study to the research subjects, ensuring their understanding, obtaining their consent and having them sign the informed consent form. Questionnaires were distributed before the treatment to collect the general information of the patients, and the FOIS scale, SWAL-QOL scale and NRS scale were measured. The plasma osmotic pressure, total serum protein and Hb of the patients were collected by laboratory tests. The same data were collected after 2 weeks of treatment. During the data collection process, each item of the scale was asked and filled out by the researchers. When the research subjects raised questions about the filled content, the researchers provided explanations. After the questionnaire was completed, the researcher carefully examined it. If there were any issues, they were verified on the spot to ensure the validity of the questionnaire.
Research ethics
This study was approved by the Ethics Committee of Nanjing Medical University, with the review number (2022) 806. The implementation of the project followed the principles of voluntariness and informed consent. Before collecting data, the consent of the research subjects must be obtained, and the purpose, methods and contents must be explained. In accordance with the principle of confidentiality and to protect personal privacy, the materials will only be used for this research and no personal information will be disclosed.
Quality control
During the research design stage, strict inclusion and exclusion standards are formulated based on the research objectives and the characteristics of the research population. The selected research tools were internationally recognised measurement tools, and the scale had good reliability and validity. The research plan was formed after repeated discussions among the members of the research team and was scientific and feasible. Throughout the entire treatment period, nurses operating intermittent tube feeding need to pass the relevant knowledge training and skills assessment of gastric tubes and have rich clinical practice. All the thickeners used were Susu produced by NUTRI Company of Japan, and clear and standardised standards and methods for the preparation of Susu had been established. During the entire intervention period, the head nurse and the researcher made overall arrangements and were responsible for handling difficult problems and emergencies. It was worth noting that all the research subjects were from the rehabilitation department of the hospital and none of them received intravenous treatment. The fluid intake was all provided through their respective feeding methods (intermittent tube feeding or thickened feeding). During the data organisation and analysis stage, all questionnaires were personally distributed and collected by the researchers themselves. Any unreasonable parts filled in the questionnaires were promptly corrected and improved. All biochemical test indicators were completed by the hospital’s laboratory department to ensure the validity and accuracy of the data collection. After the data were sorted out without error, it is checked and entered by two people to ensure the accuracy of the data.
Statistical analysis
Data were entered using Excel, and statistical description and analysis were conducted using SPSS 26·0. The Shapiro–Wilk test was used to test the normality of the data. The mean (standard deviation (
 $\bar{x} \pm s$
)) was used to describe plasma osmotic pressure, total serum protein, Hb, FOIS score, SWAL-QOL score, NRS score and measurement data such as age in general information. For the measurement data in the general information, such as gender, educational level, type of stroke, grade of the Wada drinking water test, past medical history and medication use, frequency and composition ratio were used for description. For univariate analysis, independent sample t test and analysis of variance were used for measurement data. The differences in plasma osmotic pressure before and after treatment in two groups did not conform to the normal distribution, so non-parametric tests were adopted. Count data were analysed using the χ2 test. P value < 0·05 was considered statistically significant.
Results
Comparison of general information of the two groups of patients
The comparison results of the two groups of patients in terms of age, gender, educational level, payment method, stroke type, Wada drinking water test grade, past medical history and medication use all showed no statistically significant differences (P > 0·05), as shown in Table 1. Figure 1 shows the inter-group trends of six key indicators (plasma osmotic pressure, thirst score, FOIS scores, SWAL-QOL scores, total protein and Hb).
Comparison of general information of the two groups

Table 1 Long description
The table compares two groups of patients, the thickened feeding group and the intermittent tube feeding group, across various variables. It has 11 rows and 10 columns. The columns are labeled as Variables, Category, Thickened feeding group (n 24) with sub-columns n, Mean, and SD, Intermittent tube feeding group (n 24) with sub-columns n, Mean, and SD, and t/x2, P. The rows are labeled as Age, Gender with subcategories Man and Woman, Degree of education with subcategories Primary school and below, Junior high school, High school or technical secondary school, and College degree or above, Payment method with subcategories Self-funded and Medical insurance, Stroke types with subcategories Cerebral haemorrhage and Cerebral infarction, Drinking water test grade with subcategories Level 3, Level 4, and Level 5, Past medical history with subcategories Hypertension, Diabetes, and CHD, and Medication situation with subcategories Diuretic and Beta-blockers. Each cell contains specific values relevant to the category and variable being compared. The table shows the mean, standard deviation, and statistical significance (P value) for each variable between the two groups.
Trend chart of key indicators.

Comparison of plasma osmotic pressure changes before and after treatment in the two groups
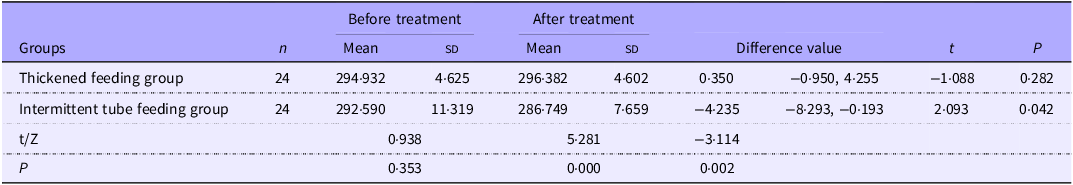
The results showed that there was no statistically significant difference in plasma osmotic pressure between the two groups of patients before treatment (t = 0·938, P = 0·353). There was no statistically significant difference in plasma osmotic pressure before and after treatment in the thickened diet group, while the plasma osmotic pressure in the intermittent tube feeding group decreased significantly after treatment, and the difference was statistically significant (P < 0·05), suggesting that the dehydration status of the patients improved. The difference in plasma osmotic pressure before and after treatment in the thickened diet group and the intermittent tube feeding group was statistically tested, and the data did not conform to the normal distribution. The rank sum test was used. The results showed that there was a statistically significant difference in the plasma osmotic pressure difference between the two groups before and after treatment. The absolute value of the plasma osmotic pressure difference score of intermittent tube feeding before and after treatment was significantly greater than that of the thickened diet group, suggesting that the dehydration improvement in the intermittent tube feeding group was better than that in the thickened diet group. Intermittent tube feeding is helpful to improve the hydration status of patients, as shown in Table 2.
Comparison of plasma osmotic pressure before and after treatment between two groups (
 $\overline {x\;} \pm {\rm{s}}$
)

Table 2 Long description
The table has 7 rows and 9 columns. The columns are labeled as Groups, n, Before treatment Mean, Before treatment SD, After treatment Mean, After treatment SD, Difference value, t, and P. The rows are labeled as Thickened feeding group, Intermittent tube feeding group, and t/Z. The Thickened feeding group row shows values: 24, 294.932, 4.625, 296.382, 4.602, 0.350, -0.950, 4.255, and 1.088. The Intermittent tube feeding group row shows values: 24, 292.590, 11.319, 286.749, 7.659, -4.235, -8.293, -0.193, and 2.093. The t/Z row shows values: 0.938, 5.281, and -3.114. The P row shows values: 0.353, 0.000, and 0.002.
Comparison of Numerical Rate Scale scores of the two groups of patients before and after treatment
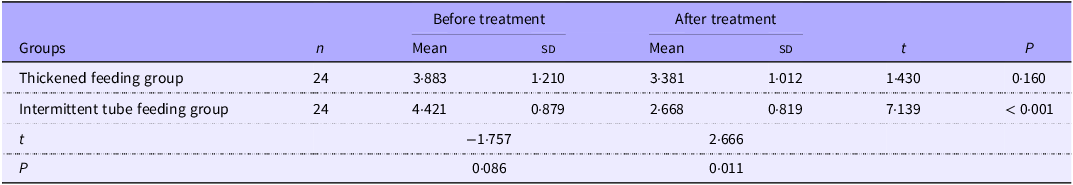
The results showed that there was no statistically significant difference in the NRS scores between the two groups before treatment (t = −1·757, P = 0·086). Compared with the thickened diet group, the thirst score of the intermittent tube feeding group was significantly lower after treatment, suggesting that the thirst condition of the patients improved, and the difference was statistically significant (P < 0·05). The differences in thirst scores of the two groups of patients before and after treatment were statistically tested. The data conformed to a normal distribution. Two independent sample t tests were used. The results showed that there was a statistically significant difference in the difference in thirst scores between the two groups before and after treatment. The absolute value of the difference in thirst scores of the intermittent tube feeding group before and after treatment was significantly greater than that of the thickened diet group. It is indicated that the improvement of thirst in the intermittent tube feeding group is better than that in the thickened diet group. Intermittent tube feeding is helpful in improving the thirst status of patients, as shown in Table 3.
Comparison of thirst indicators of the two groups before and after treatment (
 $\overline {x\;} \pm {\rm{s}}$
)

Table 3 Long description
A table comparing thirst indicators of two groups before and after treatment. The table has 7 rows and 8 columns. The columns are labeled as Groups, n, Before treatment Mean, Before treatment SD, After treatment Mean, After treatment SD, t, and P. The rows are labeled as Thickened feeding group, Intermittent tube feeding group, and t. The values in the table are as follows: Row 1: Thickened feeding group, 24, 3.883, 1.210, 3.381, 1.012, 1.430, 0.160. Row 2: Intermittent tube feeding group, 24, 4.421, 0.879, 2.668, 0.819, 7.139, < 0.001. Row 3: t, -, -1.757, -, 2.666, -, -, -. Row 4: P, -, 0.086, -, 0.011, -, -, -.
Comparison of Functional Oral Intake Scale scores and Swallowing Quality of Life Scale scores of the two groups of patients before and after treatment
The results showed that there were significant differences in FOIS score and SWAL-QOL score before and after treatment in the intermittent tube feeding group and the thickened diet group. The improvement of FOIS score and SWAL-QOL score after treatment was better than that before treatment (P < 0·05). Comparison between the groups after treatment: There were no significant differences in FOIS scores and SWAL-QOL scores between the intermittent tube feeding group and the thickened diet group, as shown in Table 4.
Comparison of FOIS scores and SWAL-QOL scores of the two groups before and after treatment (
 $\overline {x\;} \pm {\rm{s}}$
)

Table 4 Long description
The table compares FOIS scores and SWAL-QOL scores for two groups before and after treatment. It has 6 rows and 12 columns. The columns are labeled as Groups, FOIS scores Before treatment Mean, FOIS scores Before treatment SD, FOIS scores After treatment Mean, FOIS scores After treatment SD, t, P, SWAL-QOL scores Before treatment Mean, SWAL-QOL scores Before treatment SD, SWAL-QOL scores After treatment Mean, SWAL-QOL scores After treatment SD, t, P. The groups are Thickened feeding group and Intermittent tube feeding group. Row 1: Thickened feeding group, 3.081, 1.318, 5.290, 1.078, -6.349, < 0.001, 131.811, 26.168, 160.379, 20.130, -3.460, 0.002. Row 2: Intermittent tube feeding group, 2.629, 1.062, 4.791, 1.383, -6.103, < 0.001, 116.176, 24.767, 158.001, 20.942, -4.277, < 0.001. Row 3: t, 1.331, , 1.395, , , , 1.558, , 0.296, , , . Row 4: P, 0.190, , 0.170, , , , 0.132, , 0.769, , , .
FOIS, Functional Oral Intake Scale; SWAL-QOL, The Swallowing Quality of Life Scale (SWAL-QOL).
Comparison of changes in total serum protein and Hb before and after treatment between the two groups of patients
The results showed that there was no statistically significant difference in serum total protein and Hb among the groups before treatment (t = −1·711, P = 0·094; t = 0·814, P = 0·420). There was no statistically significant difference in serum total protein and Hb before and after treatment between the thickened diet group and the intermittent tube feeding group within the group (P > 0·05). The differences in serum total protein and Hb before and after treatment between the thickened diet group and the intermittent tube feeding group were statistically tested, and the data conformed to a normal distribution. Two independent samples t test were used. The results showed that there was no statistically significant difference in the differences of total serum protein and Hb between the two groups of patients before and after treatment, as shown in Table 5.
Comparison of total protein and Hb between the two groups before and after treatment (
 $\overline {x\;} \pm {\rm{s}}$
)

Table 5 Long description
The table presents data on total protein and hemoglobin (Hb) levels for two groups: the thickened feeding group and the intermittent tube feeding group, both before and after treatment. The table has 6 rows and 10 columns. The columns are labeled as follows: Groups, Total protein Before treatment Mean, Total protein Before treatment SD, Total protein After treatment Mean, Total protein After treatment SD, Hb Before treatment Mean, Hb Before treatment SD, Hb After treatment Mean, Hb After treatment SD. The rows are labeled as Thickened feeding group, Intermittent tube feeding group, t, and P. For the thickened feeding group, the total protein before treatment has a mean of 63.658 and an SD of 4.017, and after treatment, it has a mean of 65.120 and an SD of 7.026. The Hb before treatment has a mean of 120.961 and an SD of 13.003, and after treatment, it has a mean of 123.248 and an SD of 11.899. For the intermittent tube feeding group, the total protein before treatment has a mean of 65.779 and an SD of 4.554, and after treatment, it has a mean of 66.177 and an SD of 5.275. The Hb before treatment has a mean of 117.172 and an SD of 18.749, and after treatment, it has a mean of 117.918 and an SD of 15.517. The t values for total protein and Hb before treatment are -1.711 and 0.814, respectively, and the P values are 0.094 and 0.420, respectively. The t values for total protein and Hb after treatment are -0.589 and 1.336, respectively, and the P values are 0.559 and 0.188, respectively.
Discussion
Dehydration is an undesirable hydration state, characterised by a lack of water in the body and a reduction in the volume of body fluids(Reference Thomas, Cote and Lawhorne19). Dehydration can lead to a reduction in blood volume and an increase in blood viscosity, thereby increasing the risk of venous thromboembolism, expanding the infarct area and affecting the prognosis and quality of life of patients(Reference Bahouth, Bahrainwala and Hillis20). The results of this study indicate that the plasma osmotic pressure of patients in the intermittent tube feeding group was at a normal level after treatment. The plasma osmotic pressure of the patients in the thickened feeding group was higher than the normal level, showing a dehydrated state, which was consistent with the research results of Du Yan et al. Intermittent tube feeding involves inserting a catheter into the oesophagus or stomach when a patient needs to supplement nutrients and removing it after the meal. This approach enables timely water replenishment based on the patient’s needs, reducing the risk of low-intake dehydration. However, after thickening, the taste and appeal of food and liquids decline, resulting in a poor eating experience for patients and weak compliance. Thickened liquid is more likely to trigger gastric stretch receptors, thereby generating a feeling of fullness, leading to insufficient fluid intake and failing to ensure the patient’s water intake(Reference Wang, Charlton and Kohlwes21,Reference Steele, Alsanei and Ayanikalath22) . Murray et al. found that patients with dysphagia who consumed thickened liquids had a daily water intake that was only half of the minimum fluid intake for hospitalised patients(Reference Murray, Miller and Doeltgen23). A retrospective study showed that after food consistency adjustment, the ratio of blood urea nitrogen to creatinine in patients at discharge significantly increased(Reference Crary, Carnaby and Shabbir17). Moreover, thickened liquids cannot completely avoid the risks of aspiration and aspiration pneumonia. Due to fear and anxiety about eating, it leads to insufficient water intake, which is prone to dehydration(Reference Kaneoka, Pisegna and Saito24).
Thirst is a subjective feeling caused by physiological or behavioural factors, manifested as a lack of sufficient water in the body or a strong desire to drink water. It is a protective mechanism by which the body regulates fluid balance and maintains the homeostasis of the internal environment(Reference Lin, Li and Chen25). After treatment, the thirst score of patients in the thickened feeding group was significantly higher than that in the intermittent tube feeding group, indicating that the sense of thirst in the thickened feeding group was stronger. Thickened liquid leaves a film in the mouth after swallowing, which makes it impossible to relieve thirst and has a poor thirst-quenching effect. Intermittent tube feeding can replenish water at any time according to the patient’s needs, and the gastric tube is removed immediately after feeding, avoiding the dryness of the oral mucosa caused by the patient breathing through the mouth due to the nasal cavity being blocked by the indwelling gastric tube. Intermittent tube feeding can enhance the comfort of patients, preserve their self-esteem and have better compliance.
The results of this study show that the FOIS score and SWAL-QOL score of both the intermittent tube feeding group and the thickened feeding group increased after treatment, indicating that both intermittent tube feeding and thickened feeding can improve the swallowing function and quality of life of patients. Intermittent tube feeding conforms to the normal dietary habits of the human body. Repeated tube placement can continuously stimulate the muscle groups related to swallowing, promote muscle contraction, induce swallowing reflex, train the strength of laryngeal muscles and improve swallowing function(Reference Wu, Zhu and Zhou9). It is also conducive to conducting swallowing function rehabilitation training during the intermission of extubation, avoiding disuse atrophy of the hypopharyngeal muscle group and triggering the neuromuscular activity of the swallowing reflex, thereby achieving better rehabilitation training effects(Reference Zhang, Pan and Zong26). The gastric tube is removed immediately after intermittent tube feeding, which has a relatively small impact on the patient’s appearance. At the same time, it is convenient for facial cleaning, comfortable for breathing, reduces the psychological burden of self-illness, promotes the reshaping of the patient’s social role and improves the patient’s quality of life. The application of thickeners to increase the viscosity of food can slow down the speed at which food passes through the epiglottis, and less food will overflow from the back of the tongue into the airway before the initiation of pharyngeal swallowing, reducing the risk of aspiration. At the same time, it is necessary to enhance the patient’s control over the food mass during swallowing, making it easier for the patient to swallow and improving the safety of feeding for patients with dysphagia(Reference Icht, Bergerzon-Bitton and Kachal27). Oral feeding can stimulate the swallowing reflex, enhance the muscle coordination related to swallowing and promote the reconstruction of swallowing function. The patient’s choking and choking sensation when eating orally has been alleviated, which has enhanced the patient’s confidence in eating and recovery. The patient is willing to take on family and social roles, improving the patient’s quality of life.
Although this study provides important evidence for nutritional support strategies for patients with dysphagia after stroke, the following limitations still need to be pointed out. First, since this was an observational study, the total fluid intake of the two groups of patients could not be strictly controlled. We grouped the patients based on their medical history and the results of the swallowing assessment at admission, and the comparison of general data between the two groups of patients showed no statistically significant difference; therefore, the clinical characteristics have little impact on the outcome indicators. Second, this study is an observational study, and the groups were formed based on the way of nutritional intake methods determined by clinical decisions, which may have influenced the representativeness of the sample and lead to selection bias to some extent. Our sample sources are consistent, and clear inclusion and exclusion criteria have been set, which can reduce the heterogeneity of the samples to some extent. Moreover, the two groups were comparable in baseline characteristics. In the future, the samples can be matched based on propensity scores to reduce the influence of selection bias. Finally, the assessment of hydration status did not incorporate more comprehensive indicators such as plasma Na concentration and antidiuretic hormone levels, for the following reasons: The European Food Safety Authority and the Institute of Medicine of the USA have stated that the most reliable indicator for detecting hydration status is plasma osmotic pressure. The results of urine tests for assessing hydration status are prone to be affected by food and drugs. Judging dehydration by observing symptoms such as skin tension has a high degree of subjectivity, and the related symptoms are easily confused with those of ageing in the elderly, resulting in low accuracy. These methods are more suitable for initial screening in communities and nursing homes. In the future, a more complete assessment system for hydration status should be established, and further multi-centre and large-sample studies should be carried out.
Conclusions
In this prospective observational study, intermittent tube feeding can effectively improve the dehydration and thirst conditions of patients. In addition, just like the thickened diet, it can also improve the oral swallowing function and quality of life of patients with dysphagia after stroke. This study can provide evidence-based basis for the formulation of individualised nutritional support plans in clinical practice and optimise the nutritional management strategies for dysphagia after stroke.
Acknowledgments
Not applied.
(1) National Natural Science Foundation of China: No.82202818. (2) Project of “Nursing Science Funded by the 4th Priority Discipline Development Program of Jiangsu Higher Education Institutions (Jiangsu Education Department [2023] No.11)
Conceptualisation, Mengchao L.; Funding acquisition, S. C.; Methodology, Mengchao L.; Resources, Y. C.; Software, H. Y.; Supervision, J. S. and S. C.; Validation, Mengru L.; Visualisation, J. S.; Writing – original draft, Mengchao L., H. Y. and Mengru L.; Writing – review & editing, H. Y. and S. C.
The authors declare no conflict of interest.
The study was conducted according to the guidelines of the Declaration of Helsinki and approved by the Ethics Committee of Nanjing Medical University, with the review number (2022) 806. Written informed consent was obtained from all patients.
All raw data generated or analysed during this study are available from the corresponding author upon reasonable request.


 x¯±s
 x¯±s

 x¯±s

 x¯±s


