Case report
At 35 weeks of gestation, a 2.2-kg baby girl was born by Caesarean section for foetal distress. On examination of the child, the heart rate was 140 beats per minute, both pre-ductal and post-ductal saturations were 75%, and the blood pressure was 52/36 mmHg with no gradient between the upper and lower limbs. The praecordium was active with normal first and second heart sounds and a 2/6 systolic ejection murmur. A chest radiograph demonstrated a boot-shaped heart and the electrocardiogram showed sinus rhythm with right axis deviation. Echocardiography demonstrated a moderate outlet ventricular septal defect with anterosuperior deviation of the infundibular septum. There was dynamic infundibular and valvar pulmonary obstruction. There was a large aortopulmonary window extending from the main pulmonary artery into the right pulmonary artery.
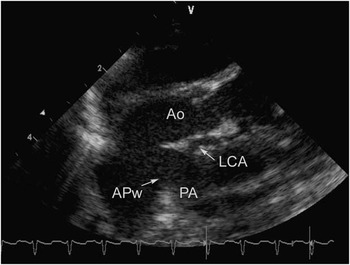
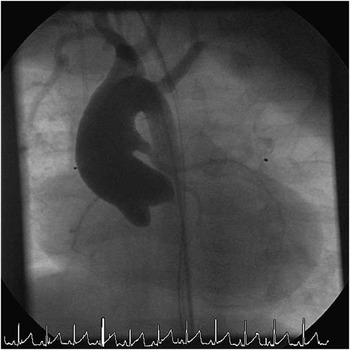
At 3 weeks of age, the infant had transient episodes of desaturation of up to 50% with bradycardia of up to 40 beats per minute and ST segment depression as seen on an electrocardiogram. Echocardiography confirmed that the left main coronary artery arose from the main pulmonary trunk proximal to the aortopulmonary window (Fig 1). Emergent surgical repair was undertaken under cardiopulmonary bypass via a median sternotomy. The aortopulmonary window was closed using a pericardial patch. The left coronary artery was baffled to the aorta using a pericardial baffle – Takeuchi repair – and a 3-mm Blalock–Taussig shunt was inserted from the right subclavian artery to the right pulmonary artery. The child was weaned from inotropic support within 3 days but failed extubation twice because of subglottic stenosis, which responded to laser ablation. Post-operative echocardiography demonstrated closure of the aortopulmonary window and an unobstructed baffle flow into the left coronary artery. The coronary arterial baffle partially occluded flow into the right pulmonary artery, which was shunt dependent. Angiography confirmed that the coronary arterial baffle was widely patent (Fig 2). The child underwent complete repair of the tetralogy of Fallot at 12 months of age with closure of the ventricular septal defect and patch repair of the right ventricular outflow tract. The child remains asymptomatic and well at home 3 years after surgical repair.
A high parasternal short-axis echocardiographic image demonstrating the aortopulmonary window and origin of the left coronary artery from the main pulmonary artery. Ao = aorta; APw = aortopulmonary window; LCA = left coronary artery; PA = main pulmonary artery.

An angiogram demonstrating the Takeuchi repair with unobstructed flow into the left coronary artery.

Discussion
Although there has been one previous report of an anomalous left coronary artery from the pulmonary artery in the setting of tetralogy of Fallot and an aortopulmonary window, this report presents the first pre-operative diagnosis of this constellation of findings.Reference Morell, Feccia, Cullen and Elliott 1 An anomalous left coronary artery from the pulmonary artery in association with an aortopulmonary window has also been described previously in the setting of interrupted aortic arch type B.Reference McMahon, DiBardino, Undar and Fraser 2 Interestingly, however, all four previous cases of complex aortopulmonary window in association with an anomalous coronary arterial origin were only diagnosed at the time of surgical intervention, with this patient being the first to have had this diagnosis before surgery.Reference Morell, Feccia, Cullen and Elliott 1 – Reference Bourlon, Kreitmann, Jourdan, Grinneiser, Schmitt and Dor 4
The precise mechanism of the haemodynamic compromise and myocardial ischaemia in this case is not clear. In the presence of an aortopulmonary window, one would assume that the anomalous left coronary perfusion would be maintained. In fact, the ST segment change is what alerted us to the anomalous coronary artery in this patient. The origin of the coronary artery from the proximal pulmonary artery in the setting of an obstructed right ventricular outflow tract may have contributed to coronary hypoperfusion. Although the aortopulmonary window would have resulted in a left-to-right shunt, this shunt may have been distal to the origin of the coronary artery, and changes in systemic or pulmonary vascular resistance may have contributed to myocardial hypoperfusion and ischaemia. The coronary arterial baffle provided adequate restoration of myocardial perfusion to allow this patient to proceed to complete repair of the underlying cardiac lesion.
This report serves to highlight the association of complex coronary arterial anatomy in the setting of tetralogy of Fallot and an aortopulmonary window. Close examination of the coronary arterial origins should be undertaken in such patients before and during surgical intervention.