Highlights
-
• The diagnostic yield of EEG in patients with recurrent events of TND was low.
-
• The impact of EEG on the diagnosis and treatment in patients with recurrent events of TND was low.
-
• Patients with interictal epileptiform discharges were more likely to be diagnosed with epilepsy and to initiate antiseizure medication (ASM) treatment.
Introduction
An electroencephalogram (EEG) is essential in the diagnosis and management of epilepsy. Reference Pillai and Sperling1 Epileptic seizures are only rarely recorded during standard and sleep-deprived EEGs; however, interictal epileptiform discharges (IEDs) can aid in seizure classification, definition of epilepsy syndromes, and evaluation of treatment efficacy and individual risk of seizure recurrence. Reference Pillai and Sperling1 Although highly specific for the diagnosis of epilepsy, IEDs can be observed in normal adults and in admitted adults with neurological or psychiatric disorders but without epilepsy, while IEDs cannot be demonstrated despite repeated EEG recordings in 10% of patients with epilepsy. Reference Pillai and Sperling1
Recurrent and stereotypical events of transient neurological dysfunction (TND) may be clinically similar to epileptic seizures. Reference Kotsopoulos, de Krom and Kessels2,Reference Mellers3 TND may present with diverse symptoms of a wide range of organic and non-organic disorders such as transient ischemic attacks, migraine, vertigo, psychosis and attention-deficit hyperactivity disorder. Reference Mellers3 Epilepsy is primarily a clinical diagnosis, and differential diagnosis is aided by detailed and accurate description of the symptoms and details on episode length and stereotypy. Reference Mielke, Meissner, Wagner, Joos and Schulze-Bonhage4 However, memory of the event may be fragmented, and witness reports may be generally unreliable and subject to considerable variability. Reference Hoppe, Poepel and Elger5–Reference Mannan and Wieshmann7 According to current guidelines, a routine EEG should be considered to support the diagnosis of epilepsy, and it is recommended that an EEG should not be used to exclude the diagnosis of epilepsy. 8
This study aimed to assess whether an EEG study changed the admission diagnosis of TNDs that included symptoms or signs that may have to be differentiated from focal seizures. Identification of clinical characteristics that are more likely to suggest a diagnosis of epilepsy may decrease the performance of unnecessary EEGs, thus facilitating diagnosis and treatment in patients with yet undiagnosed epilepsy.
Patients and Methods
The study was approved by the Ethics Committee at Shamir-Assaf Harofeh Medical Center, an 890-bed university-affiliated community hospital that serves a population of 1,500,000 in the central part of Israel. The EEG lab performs 2400–2700 neonatal, pediatric and adult EEG studies per year, and 45% to 47% of the EEGs are performed in inpatients.
The EEG laboratory computerized database was retrospectively searched for all the standard and sleep-deprived EEG recordings of adult patients admitted to the neurology or internal medicine departments and consecutively referred to the EEG laboratory due to recurrent and stereotypical events of TND during a 3-year period (2019–2021). Exclusion criteria included age <18 years, prior diagnosis of epilepsy, events that included loss of consciousness, and admission for long-term video-EEG monitoring.
Demographic and clinical data were recorded from admission and discharge summaries, follow-up notes, neurological consultation notes and medication logs, available in the inpatient domain of the computerized medical information management system, and included the following: age, gender, clinical semiology of the event, discharge diagnosis and initiation of antiseizure medication (ASM) treatment.
The EEG laboratory computerized database was searched for the following data: cause of referral to EEG, day of admission the EEG was performed, and EEG type (standard, sleep-deprived), duration and findings. All EEG recordings were reviewed by the author while blinded to the demographic data except for age. TNDs were classified as follows: speech impairment, sensory impairment (focal somatosensory, visual, dizziness/vertiginous or auditory symptoms), sided weakness, spacing out, confusion, involuntary movements and falling. The EEG findings were classified as follows: epileptiform discharges, background slowing with or without triphasic waves, that do not aid in the diagnosis of epilepsy and are commonly seen in encephalopathies, and normal EEG.
The digital EEGs were recorded from 21 electrodes placed according to the international 10–20 system. Additional electrodes were used to facilitate the detection of eye movements and of electrocardiogram and muscle artifacts.
Statistical analysis was done by SPSS version 28.0, Chicago, IL. Categorical variables were analyzed using Pearson’s χ 2 test and Fisher’s exact test, and t test was used to analyze continuous variables. Statistical significance was determined at p < 0.05.
Results
The study group included 145 patients, 74 men (51%), aged 18 to 97 years (mean: 63.4 ± 17.2) (Table 1). Standard (n = 135) (93.1%) and sleep-deprived (n = 10) (6.9%) EEGs of 22.5 ± 3.2 min (range: 20 to 40 min) were performed in 108 (74.5%) of the patients on admission days 1 to 3 (Table 1), 1 to 7 days (2.6 ± 1.5) following the last event of TND. The most common types of TND included speech impairment (n = 31) (21.4%), spacing out (n = 23) (15.9%) and somatosensory sensations (n = 22) (15.2%), and the most common discharge diagnosis was cerebrovascular diseases (n = 66) (45.5%) (Table 1). Data regarding the duration of TND were present in only 41 (28.3%) patients, and event duration ranged from minutes to several hours.
Demographic and clinical data of 145 patients with TND

Note: N(%).
ASM = antiseizure medication; EEG = electroencephalogram; TND = transient neurological dysfunction.
* Transient ischemic attack – 47, chronic stroke – 18, subdural hematoma – 1.
** Other diagnoses included the following: transient global amnesia (3), migraine with aura (3), trigeminal neuralgia (1), other headaches (3), pseudotumor cerebri (1), cerebellopontine meningioma (1), pain (radicular, musculoskeletal) (2), infection (meningitis, pneumonia, urinary tract infection) (3), sleep paralysis (1), myelopathy (1), cyclic vomiting (1), pre-syncope (1), dyskinesia (orofacial) (2), subcortical myoclonus (2), stiff person syndrome (1) ataxia (1), normal pressure hydrocephalus (1), Parkinson disease (1), parkinsonism (1) and peripheral dizziness (1).
*** Somatization (16) and psychosis (2).
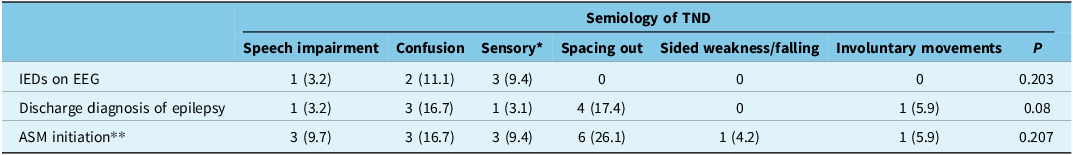
A clinical event did not occur during any of the EEG recordings, and no electrographic seizures or periodic patterns were recorded. IEDs were recorded in six (4.1%) patients and triphasic waves in two (1.4%) patients. Ten (6.9%) patients had a discharge diagnosis of epilepsy, and ASMs were initiated in 17 (11.7%) patients. IEDs were recorded in two patients who were diagnosed with epilepsy and initiated ASMs, and four patients who were alternatively diagnosed with migraine, cerebrovascular accident (CVA) with hemodynamic fluctuations, acute subdural hematoma and recurrent transient global amnesia (TGA). None of the patients who were not diagnosed with epilepsy had seizures during a 1.6- to 4.3-year follow-up. The EEG led to a change in diagnosis in one (0.7%) patient and to ASM initiation in three (2.1%) patients. Patients with IEDs were more likely to be diagnosed with epilepsy (33.3% vs 7.8% and 4.5%, respectively) (p = 0.025) and to initiate ASM treatment (50% vs 11.8% and 9.1%, respectively) (p = 0.011) compared to patients with background slowing or normal EEG recordings. The groups did not significantly differ regarding EEG duration and day of admission the EEG was performed. There was a trend toward more frequent IEDs in sleep-deprived than standard EEGs (20% vs 3%) (p = 0.056). The occurrence of IEDs and ASM initiation did not significantly differ according to the event type (Table 2). There was a trend toward a higher likelihood of a discharge diagnosis of epilepsy when the events consisted of confusion or spacing out compared to those with symptoms of speech or sensory impairment, sided weakness, falling and involuntary movements (p = 0.08) (Table 2).
Epileptiform discharges on EEG, discharge diagnosis of epilepsy and ASM initiation according to semiology of TND

Note: n(%).
ASM = antiseizure medication; EEG = electroencephalogram; IEDs = interictal epileptiform discharges; TND = transient neurological dysfunction.
* Including events that had somatosensory, visual or auditory symptoms and dizziness.
** ASMs were initiated in patients with the following diagnoses: epilepsy (n = 10), CVA with hemodynamic fluctuations (n = 1), transient ischemic attack (TIA) (n = 1), acute subdural hematoma (n = 1), somatization (n = 2) and diagnosis differed (n = 2).
Discussion
The diagnostic yield of EEG and its impact on discharge diagnosis and treatment in patients with recurrent stereotypical events of TND were low. Similarly, a low diagnostic yield of the EEG was previously reported in different types of seizure mimics. In patients with a diagnosis of syncope, only 1.5% to 2.4% of the EEGs showed epileptiform discharges. Reference Abubakr and Wambacq9,Reference Pires, Ganji, Jarandila and Steele10 IEDs were detected in 7.5% of the patients with suspected TIAs, Reference Bentes, Canhão and Peralta11 11% of patients with migraine, Reference Sethi, Ulloa, Solomon and Lopez12 9% of the patients with not otherwise specified headache, Reference Sethi, Ulloa, Solomon and Lopez12 6.3% of the patients with involuntary movements Reference Phamnguyen, Szekely and Swinburn13 and none of the patients with psychiatric presentation or functional neurological disorder. Reference Phamnguyen, Szekely and Swinburn13 We found that patients with IEDs on the EEG were more likely to be diagnosed with epilepsy and to initiate ASM treatment. The diagnosis of epilepsy is strongly supported by the presence of IEDs in the proper clinical context. Reference Weber14 IEDs can be observed in 0.5% to 4.7% of normal adults, and their occurrence rate among adult inpatients without neurological disease is similar to that in healthy subjects. Reference Pillai and Sperling1,Reference Bennett15 IEDs occur more frequently in admitted adults with psychiatric disorders and in those with neurological illness (i.e. stroke, cerebral tumors) but without epilepsy than in adults admitted for other conditions. Reference Bridgers16,Reference Zivin and Marsan17 IEDs are more frequent in subjects with migraine. Reference Schachter, Ito and Wannamaker18,Reference Sand19 In patients with TGA, their presence on the EEG is not synonymous with epilepsy. Reference Brigo, Igwe and Nardone20 Therefore, it is recommended that an EEG should not be used to exclude the diagnosis of epilepsy, 8 specifically when the clinical presentation supports a diagnosis of transient global amnesia, transient ischemic attacks, headache or syncope. Reference Langer-Gould, Anderson and Armstrong21,Reference Andre-Obadia, Lamblin and Sauleau22
Seizures are traumatic medical and psychological events, and the lack of ASM treatment in patients with new-onset epilepsy was previously associated with increased incidence of falls, fractures, motor vehicle accidents, emergency department visits and hospitalizations. Reference Kalilani, Faught and Kim23 According to current guidelines, it is recommended that immediate ASM treatment should be initiated following two unprovoked seizures 24 hours apart or an unprovoked first seizure with >60% risk of recurrent seizures (i.e. in the presence of prior brain insult, epileptiform discharges on the EEG, significantly abnormal brain imaging or a nocturnal seizure). Reference Krumholz, Wiebe and Gronseth24 In clinical practice, ASMs are also initiated in patients with repetitive seizures or seizure clusters. Reference Haut25 ASM treatment is initiated based on clinical judgment, when epilepsy is strongly suspected and usually before additional tests, that are needed for the diagnosis of epilepsy or for the determination of possible seizure etiology (i.e. brain MRI, sleep-deprived EEG, long-term video-EEG monitoring) are completed. Furthermore, the likelihood of recording IEDs in patients with epilepsy is influenced by multiple clinical and technical factors, and in 10% of the patients, IEDs cannot be demonstrated despite repeated EEG recordings. Reference Pillai and Sperling1 Therefore, it is expected that the ASM initiation rate will exceed the rate of IED occurrence, and it may partially explain the low impact of the EEG on discharge diagnosis.
In this study, there was a trend toward a higher likelihood of a discharge diagnosis of epilepsy when the events of TND included symptoms of confusion or spacing out than symptoms of speech or sensory impairment, sided weakness, falling, and involuntary movements. Ictal confusion is more common in elderly patients with seizures, and it is usually accompanied by additional motor and/or non-motor symptoms. Reference Pirgit and Beniczky26 Episodes of depersonalization, often described as a “spaced out” experience, may accompany a wide variety of psychiatric and neurological disorders; however, ictal experience of depersonalization is often accompanied by emotion of fear, autonomic symptoms, olfactory and auditory hallucinations, automatisms or speech impairment. Reference Lambert, Sierra, Phillips and David27,Reference Wirrell28 Epilepsy is a rare cause of sided weakness, isolated vertigo, aphasia, somatosensory, visual or atonic symptoms. Transient focal paralysis may rarely occur in negative motor seizures, characterized by cessation of the voluntary tonic muscle contraction or motor impersistence, with retained awareness and without preceding positive motor symptoms. Reference Lüders, Dinner, Morris, Wyllie and Comair29 Vestibular epilepsy is a rare cause of paroxysmal vertigo and dizziness, and the seizures usually include additional semiology, such as sensory or motor symptoms, disturbances of consciousness or autonomic phenomena. Reference Tarnutzer, Lee, Robinson, Kaplan and Newman-Toker30 Isolated aphasia is a rare ictal phenomenon; however, the seizures are brief, and additional seizure types are frequently reported. Reference Unterberger, Trinka, Ransmayr, Scherfler and Bauer31 Parietal lobe epilepsy is rare, and in seizures that arise from the primary sensory cortex, the tingling, numbness or pain usually spreads to adjacent body parts and may be accompanied by clonic motor activity and tonic posturing. Reference Chowdhury, Silva, Whatley and Walker32 Visual symptoms rarely occur as an isolated seizure manifestation in adults with occipital lobe epilepsy and are usually accompanied by motor symptoms. Reference Williamson, Thadani, Darcey, Spencer, Spencer and Mattson33,Reference Salanova, Andermann, Olivier, Rasmussen and Quesney34 Ictal atonic phenomena are rare in adult-onset epilepsy, and the seizure may include additional motor symptoms or altered consciousness. Reference Nguyen-Michel, Bornand and Balathazar35 And in pure focal primary motor epilepsy, most seizures consist of alternating tonic, clonic or atonic symptoms and evolve to ipsilateral and rarely contralateral limb. Reference Chowdhury, Silva, Whatley and Walker32,Reference Shaker, Li and Kobayashi36 Accurate description of event semiology is essential for the diagnosis of epilepsy; however, people with epilepsy may be unaware or have decreased memory of key symptoms of the seizure, and the description of seizure by witnesses may be inaccurate. Reference Mielke, Meissner, Wagner, Joos and Schulze-Bonhage37
Data regarding TND duration were present in less than 30% of our patients. Since focal seizures with preserved or impaired awareness are usually brief and last less than a minute, Reference Meritam Larsen, Wüstenhagen, Terney, Gardella, Aurlien and Beniczky38 data on seizure duration may have aided in differential diagnosis and contributed to the diagnosis of specific seizure types. Reference Wirrell, Tinuper, Perucca and Moshé39
This retrospective study has several limitations. Our study was hospital-based, and generalization to other clinical settings may be limited. The sample size was relatively modest, thus limiting the statistical power for some comparisons. Most of the patients had routine EEGs, and since the yield of IEDs in extended EEGs is increased compared to standard EEG recordings Reference Burkholder, Britton and Rajasekaran40 and IEDs can be precipitated by sleep deprivation, Reference Fountain, Kim and Lee41,Reference Roupakiotis, Gatzonis and Triantafyllou42 it is possible that a higher proportion of sleep-deprived EEGs or extended standard EEGs may have increased the yield of IEDs. In addition, this was a single-center study, and it is possible that the diagnostic yield may differ in other medical centers with different patterns of EEG use.
Conclusions
Our results suggest that the impact of the EEG findings on diagnosis and treatment in patients with recurrent and stereotypical events of TND is low. Further research is warranted on the effect of structured history on the use of inpatient EEG and its diagnostic yield in patients with TND.
Author contributions
Conceptualization: RGM; Data acquisition: RGM; Analysis or interpretation: RGM; Writing – original draft preparation: RGM; Writing – review and editing: RGM.
Funding statement
None.
Competing interests
None.