





Introduction
The community-based transition care programme (Comm-TCP) assesses the psychosocial needs of the older person, to guide provision of publicly-funded personal care, home care, nursing, and allied health to support older people to remain in the community (Coleman, Reference Coleman2003; Masters et al., Reference Masters, Halbert, Crotty and Cheney2008; Naylor and Keating, Reference Naylor and Keating2008; Heppenstall et al., Reference Heppenstall, Chiang and Hanger2018). Despite such programmes existing for over a decade in many countries, uncertainty continues about their core components and their methods of evaluation (Mcgilton et al., Reference Mcgilton, Vellani, Krassikova, Robertson, Irwin, Cumal, Bethell, Burr, Keatings and McKay2021; Naylor et al., Reference Naylor, Hirschman, Mccauley, Shaid, Hanlon, Whitehouse, Ghosh, Brown, Sullivan and Pauly2022). Consumers themselves (older people (people >65 years) and their caregivers) have infrequently been included in this examination (Walker et al., Reference Walker, Johns and Halliday2015; Hestevik et al., Reference Hestevik, Molin, Debesay, Bergland and Bye2019; Mcgilton et al., Reference Mcgilton, Vellani, Krassikova, Robertson, Irwin, Cumal, Bethell, Burr, Keatings and McKay2021).
Further, little detailed exploration of both older person and caregiver experiences of the programme exists. Rather, when perspectives of TCP consumers are gathered, healthcare staff perspectives, or a single component, of a programme are explored (Neiterman et al., Reference Neiterman, Wodchis and Bourgeault2015; Weeks et al., Reference Weeks, MacDonald, Martin-Misener, Helwig, Bishop, Iduye and Moody2018; Lawler et al., Reference Lawler, Taylor and Shields2023). For example, staff perspectives of ‘patient discharge planning’, identified barriers and facilitators to implementation of the TCP, including defining the interprofessional teams required (Weeks et al., Reference Weeks, MacDonald, Martin-Misener, Helwig, Bishop, Iduye and Moody2018). Additionally, perspectives of a single component of a TCP was explored finding that inclusion of family-assisted therapy differed between consumers based on what is (i) possible and (ii) important for a family now, and (iii) how individual families function (Lawler et al., Reference Lawler, Taylor and Shields2023). It is unknown how older people and/or their caregivers perceive how this community programme influences the ability of an older person to remain at home following this programme.
Person-centred care (PCC) is a theoretical approach used in healthcare communication (Mead and Bower, Reference Mead and Bower2000; McCormack and McCance, Reference McCormack and Mccance2006; Jo Delaney, Reference Jo Delaney2018) comprising specific factors including, ‘patient and health professional partnerships’, and ‘flexibility in health care provision’ (Jo Delaney, Reference Jo Delaney2018; Eklund et al., Reference Eklund, Holmström, Kumlin, Kaminsky, Skoglund, Höglander, Sundler, Condén and Meranius2019). A PCC approach to the organisation of health services, valuing mental and physical capacity in older people, is endorsed by the World Health Organisation (De Carvalho et al., Reference De Carvalho, Epping-Jordan, Pot, Kelley, Toro, Thiyagarajan and Beard2017). The PCC model was employed to examine how consumers with chronic health conditions navigated their care journeys, including via a TCP (Heslop et al., Reference Heslop, Cranwell and Burton2019). Despite PCC being viewed as crucial for delivering high-quality healthcare, gaps are still found in reporting of patient burden, caregiver burden, and unmet needs related to emotional health and self-autonomy in TCP (Allen et al., Reference Allen, Hutchinson, Brown and Livingston2014). We thus utilised the PCC model during analysis to explore how a Comm-TCP might demonstrate clinical practice commensurate with PCC components.
Aim
Therefore, the objectives of this study were to (i) explore consumer experiences with their participation in a Comm-TCP, specifically to explore and summarise the experience from the (ia) older person and (iib) caregiver perspective, and to (iii) consider the findings in the context of PCC.
Method
Study design
This qualitative study consisted of semi-structured interviewing of Comm-TCP older people and caregivers.
Setting and recruitment
The study was set in an established Comm-TCP (>10 years) linked to an Australian metropolitan (BLANK) hospital. The programme comprised health service-employed case managers, physiotherapists, occupational therapists, speech pathologists, and dietitians. Registered nurses, personal carers, and home care support workers were externally contracted by TCP case managers via private providers. People admitted to the Comm-TCP were primarily aged >65 years, following an acute hospital admission for any health condition, which required a maximum additional three months of support after hospital discharge.
To be eligible for study inclusion, older people enrolled in Comm-TCP (and/or caregivers) had to be involved a minimum of four weeks. Older people 65 years and older were included as such people were those primarily identified for the Comm-TCP by Aged Care Assessors at the time of study commencement (Australian Government Department of Health, 2015). Older people consented for themselves (or through a nominated caregiver responsible). In addition, caregivers could consent for themselves. Potential participants were identified by convenience sampling via the Comm-TCP clinicians at team meetings from study onset (30th April 2019) until January 2021. These potential study participants were approached by the main study researcher (Author1) over the telephone. Prospective participants were told that this study was initiated to help with health service improvement. Interviewers were blinded to the content of the participant’s TCP goals and intervention. Study participants could complete the interviews in the presence of others if they requested this.
Data collection
A semi-structured interview format (Suppl material 1) was followed by trained study personnel (Author1(B. Physio., PhD candidate), Author6 (RN)) that asked all study participants to reflect on their experience leaving the hospital, the challenges faced once home, and the Comm-TCP components they identified that supported or hindered them to remain at home. Interviews were audio-recorded, de-identified, uploaded to cloud storage, and allocated a unique code. All interviews were transcribed verbatim. In addition, demographic data were collected, i.e., type of participant (older person, caregiver), age of older person, sex of older person, primary reason for admission to Comm-TCP, admission modified Barthel Index, and number and type of co-morbidities.
Data analysis
The interview transcripts were read by the analysis team (Author1, Author3–5, Author2 (PhD candidate)). Authors 6, 1, and 3 worked in the same Comm-TCP team at different stages during conduct of the study. Any potential bias of the lead author was challenged during this study development and during qualitative analysis by opinions of clinicians with extensive work experience within Community-based TCP (authors 3, 4) as part of the dependability and confirmability aspects of the qualitative analysis phases. Transcripts were coded separately for Comm-TCP (i) older people and (ii) caregivers following the approach for content analysis to transform the textual data into themes and sub-themes (Graneheim and Lundman, Reference Graneheim and Lundman2004). Content analysis involved (i) back-and-forth reading of the interviews for data familiarity, (ii) extracting meaning units from the transcripts that corresponded to the study aims, (iii) acquiring shorter sections of meaning unit text (codes) iteratively to condense the text, and (iv) comparing the codes across the sample to achieve further abstraction and creation of categories (and sub-categories) (Graneheim and Lundman, Reference Graneheim and Lundman2004). Further, qualitative content analysis is appropriate when the nuance and meaning of textual information is unknown and is gathered iteratively from the data (Vaismoradi et al., Reference Vaismoradi, Jones, Turunen and Snelgrove2016).
The lead researcher created the first iteration of codes and categories, using NVivo™ software. Further development of the categories, sub-categories, and overarching themes occurred (including researchers with experience of qualitative research (Authors 1–2) over a series of meetings in 2021–2022. Finally, thematic findings for the two groups were mapped to the ‘person-centred care’ (PCC) model. To do this, the core constructs of PCC were derived from a recent meta-synthesis (Eklund et al., Reference Eklund, Holmström, Kumlin, Kaminsky, Skoglund, Höglander, Sundler, Condén and Meranius2019). Then tables were created for (i) older people and (ii) caregiver groups, whereby the sub-themes from our study would be mapped (or not) to each core construct.
Ethics
Ethical approval was gained from {Western Health Office for Research, Victoria, Australia} prior to study onset.
Findings
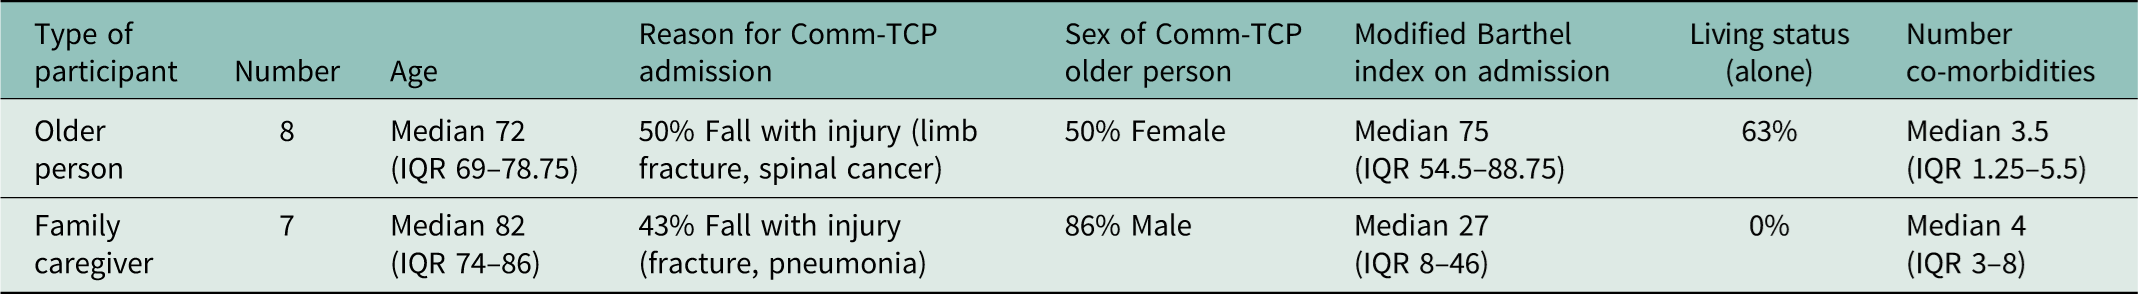
Twenty-five consumers were eligible to participate, with fifteen people consenting (n = 8 older people, n = 7 caregivers); and two consumers declined the invitation to participate. This study was conducted, according to the COREQ guidelines (Tong et al., Reference Tong, Sainsbury and Craig2007), from January 2019 with data collection concluding January 2021. Seven potential participants were not invited during the escalation of the Covid-19 emergency (research was suspended within the health service). Of the remainder, two became deceased prior to invitation to participate, and one was missed due to staffing issues (total n = 10). Interview duration ranged from 18.6 (Q1) to 29.0 (Q2) (IQR) minutes (median = 24.4 minutes). The characteristics of the older people are summarised in Table 1. Most consumers (14/15) elected to be interviewed with no other people present.
Summary of older people characteristics in ‘older people’ and ‘caregiver’ groups

Table 1. Long description
A table comparing characteristics of older people and their caregivers. The table has two rows and seven columns. Column headers are Type of participant, Number, Age, Reason for Comm-TCP admission, Sex of Comm-TCP older person, Modified Barthel index on admission, Living status (alone), and Number co-morbidities. Row 1: Older person, 8, Median 72 (IQR 69–78.75), 50 percent Fall with injury (limb fracture, spinal cancer), 50 percent Female, Median 75 (IQR 54.5–88.75), 63 percent, Median 3.5 (IQR 1.25–5.5). Row 2: Family caregiver, 7, Median 82 (IQR 74–86), 43 percent Fall with injury (fracture, pneumonia), 86 percent Male, Median 27 (IQR 8–46), 0 percent, Median 4 (IQR 3–8).
Note: IQR = interquartile range; modified Barthel Index = categorical measure of physical disability related to activities of daily living (0–100), where 0 = most disabled and 100 = complete functional independence.
Themes
The resulting themes were organised primarily according to time epochs following the time point whereby Comm-TCP was introduced to the older person and/or family caregiver in hospital, to the first few weeks at home, and finally beyond 4–6 weeks at home (Figures 1 and 2, and supplemental material for summarisation of the coding structure S2 (older person) and S3 (caregivers)). This organisation of themes was done to separate the textual data derived from interviews related to the participants’ understanding of hospital and the Comm-TCP staff care processes.
Older people themes and sub-themes.

Caregiver themes and sub-themes.

There were seven older people themes (as shown in Figure 1(i)–(vii)), and three caregiver themes (Figure 2 (i)–(iii)) organised from onset to end of Comm-TCP. Themes for each group will be discussed and mapped to the PCC against the research objectives.
Older people
Figure 1 illustrates sub-themes related to limited understanding about TCP and to own ideas about how to walk or to prevent falls. Immediately prior to hospital discharge and early when home, older people were preoccupied with their prolonged hospital admission for a complicated health condition (Theme (i)). Understanding how Comm-TCP would assist them returning home was unappreciated. The primary focus was adapting to an altered physical ability, following illness or injury. Pre-existing involvement with either family or external caregiver supports meant that additional Comm-TCP resources were considered superfluous.
Three themes featured once back home (Themes (ii)–(iv)). Firstly, older people could not do as much as was anticipated by themselves in hospital. Changes to physical ability acquired from a preceding fall, and own ideas how to prevent future falls featured.
‘If I use the one with the wheels on it …because my body what do you call it the …equilibrium part of it …..tends to go forward rather than back…and there’s a reason cos of this cos if I go back I’ve nothing to hold me ….and I fall. I’ve already fallen..’ (Older person 8)
Achievement of action plans for walking, often to complete toilet transfers for functional continence, were described. The assistance of external support workers in the context of altered mobility, night-time incontinence, and difficulty with cleaning up spills was required. Hygiene goals related to either having external care workers, or family members, supporting achievement of hygiene tasks. This is shown in the following example:
‘I mean I suppose you are fresh, they wash your hair, they wash your backside, All those things you can’t quite reach and you know at least you know you are clean. You’re not going to be smelling.. Have to make sure you are clean and things…’ (Older Person 2)
Ideas for generating alternative movement strategies arose by observing for themselves how their own physical environment limited their ability to complete personal care tasks:
‘ …someone coming to look and see if they can take the bath out so that I can just walk into the shower without having to step. If I didn’t have to step, then I wouldn’t need help to wash or things like that. I could do it myself..’(Older Person 2)
In addition, experiencing different movement strategies whilst in hospital was described. Specific methods, and mobility equipment, were identified as most appropriate by older people themselves. Older people independently changed mobility equipment once home or extended use of devices to another task (wheeled walking frame when hanging out laundry), often presented as contrary to the method recommended.
However, older people valued availing of learning different movement strategies, information from key health professionals, and devices once home. Having Physiotherapy and Occupational therapy staff to complement own ideas to achieve whole body postural tasks while training a spousal caregiver was noted. Access to a nurse for tailored diabetic education was also discussed as shown in the following
‘Well when I first started the ladies came about every day, yeah… every day through the week. After a period of time they felt they could cut that back so now they haven’t come in…’ (Older person 5)
There was a theme of uncertainty with how things would work out at home. This ‘uncertainty’ as a stand-alone theme permeated all the textual data either by being directly referenced, or through inability to provide any detail about whether the previous four-twelve weeks of Comm-TCP confirmed for them or not about how they would manage at home.
Finally, sub-themes (v)–(vii) described the gains observed by older people in themselves. Improvement in re-engagement with a familiar everyday task (moving about their own kitchen making pasta); and the recording of measurements of supported ‘standing up’ or ‘walking’ was reported. Walking ability, apart from toilet transfers, was prioritised with ideas about continuing this activity, often during everyday domestic tasks for example:
‘Be very careful where you are walking and you’ve got shoes on…So you’ve got to be careful when walking. No obstacles on the way, you know. So, that’s good. I don’t have any falls now. (Older person 6)
Lastly, another stand-alone sub-theme was that less help from others was needed as additional everyday tasks were achieved.
Caregivers
Immediately prior to hospital discharge and early at home were ‘challenges with discharge home on many fronts’. Figure 2 illustrates sub-themes about keeping loved ones at home, having a protracted hospital admission, or being offered resources not aligned to individual needs.
Continence needs were overwhelming for caregivers. This was manifested by needing to frequently physically support their older person to access the toilet, or as having interrupted sleep to attend to older person toileting needs. This toileting aspect involved unexpected and excessive amounts of cleaning of soiled materials late at night:
‘so full up the mattress protector and when I fold it starts dripping on the carpet, so here I am 5 o’clock in the morning …..kneeling down, I’m nearly 72….I’m not a spring chicken and you know’. (Caregiver 5)
In addition, taking on personal care tasks and addressing the daily routine for their older person was effortful for caregivers as in:
‘…the support has been great. It’s made me even more confident that there is such a help available only a phone call away. I was also aware before, but I didn’t apply for any help before. I thought I was doing okay but lately I start to feel. a neighbour of mine said you better start doing something it’s getting a bit too much. they were right ’(Caregiver 2)
Familiarity was gained with what was expected of caregivers and with Comm-TCP resources offered (Theme (ii)). Seven sub-themes featured here as shown in Figure 2. Availing of and using different types of hospital equipment with the older person, whilst completing everyday tasks, was expressed. This sub-theme included noting success in mastery of using equipment, leading to independent use in several cases.
‘now I can move him out of bed….he stays on the other chair for ½ an hour.…then I shift him back into bed ….I do that with the sara stedy.™ ..that equipment is really very good…’. (Caregiver 7)
Skill in equipment usage was described for attending to continence needs (use of a bed stick at night facilitated toilet access, promoting caregiver sleep). Mobility-related tasks (assisted standing up with postural equipment) for out-of-bed toileting, without others present, was achieved. Further, mastery of skills related to independence with a range of assisted personal care activities or managing to assist their older person to walk a few paces (with equipment) to reduce the level of external assistance required. An example of skills acquired is shown in the following:
‘the Physiotherapist came in…and she showed me how to help him, to lift him…also those .. slide sheets, in case ..he needed to be turned in bed or pulled up or anything . So my daughter and I were trained….to be able to manage that when he came home. And we did use those at the beginning, we did use those slide sheets, they’re a great idea…’ (Caregiver 7)
Other key resources, such as specific healthcare staff at crucial times, e.g., on weekends to address urinary catheter changes, were highlighted. Sourcing key information by contacting Comm-TCP staff for care supports, queries, and individualised support was described.
A stand-alone theme was knowledge of how to be a caregiver by observing other family members in caring roles. There was inability to describe how caregivers acquired their knowledge and practical skills in the Comm-TCP caring context apart from their own life experience.
Finally, beyond the initial four weeks at home, three sub-themes were found (Theme (iii)). There was all-consuming ongoing care for the older person. Ongoing care for someone who is physically and/or cognitively worsening was specifically expressed. Further, caregivers sought their own information channels to access residential aged care for the older person. Needing emotional support, beyond Comm-TCP interventions, and other family assistance at home were described. Caregivers articulated that their own physical health and leisure needs were impacted due to caring duties. If long-term care support was ongoing, the current situation at home with the older person would be untenable.
Mapping of PCC to study findings
Following data analyses, two members of the study team (Author1, Author3) assessed if the sub-themes could be mapped to individual components of PCC (Eklund et al., Reference Eklund, Holmström, Kumlin, Kaminsky, Skoglund, Höglander, Sundler, Condén and Meranius2019) (Suppl material 4–5). Overall, we found that many sub-themes clearly aligned with PCC constructs: ‘relationship’, ‘communication’, ‘shared-decision-making’, ‘holistic focus’, ‘individualised focus’, and ‘coordinated care’, i.e., both caregiver and older people groups indicated that these constructs were present in their care. However, it was difficult to identify whether the domains of ‘empathy’, ‘respect’ and ‘engagement’ were present. There was overlap of sub-themes across multiple constructs in both groups. Examples of where evidence was lacking that PCC did/did not occur for particular caregivers (‘shared decision-making’ and ‘co-ordinated care’) and older people (‘individualised focus’, ‘coordinated care’) were also found.
Discussion
Our findings provide a nuanced exploration about how a Comm-TCP was perceived by people designed to derive the most benefit: the consumers. The caregiver group revealed the unrelenting demands made on them physically and emotionally to keep older people at home. Continence care while caregiving was identified as exhausting, although key equipment was availed of, and functional task achievements formed a steep learning curve. The caregivers were caring for a more dependent group (reflected by the lower disability score). In contrast, the older people described their navigation of resources to access carer support, to safeguard against future falls, and to address walking. These older people were higher functioning, a high proportion lived alone, with two-thirds sustaining an injurious fall, and little cognitive difficulty. So, our findings are also influenced by different levels of disability in the two groups. Unfortunately, both consumer groups were unable to explain at three months what aspects of the programme increased or decreased their confidence with remaining at home.
Our findings build somewhat on research conducted by (Walker et al. (Reference Walker, Johns and Halliday2015)) who found that TCP was ‘a disempowering system’, with ‘complexities of control’ whilst older people adapted to their new recovery status. Over half of the (Walker et al. (Reference Walker, Johns and Halliday2015)) study cohort were post fracture and >75 years of age like our study population. Although our consumers did express some frustration communicating with support services, this finding was not predominant. It must be recognised that the Comm-TCP ‘model of care’ had recently launched at the time of the (Walker et al., Reference Walker, Johns and Halliday2015). Perhaps communication difficulties were readily perceived in this new programme (TCP) at that time that could account for this difference. In our study, having ready access to health professional and domestic care workers to address pressing consumer priorities i.e., basic care needs, and safety for walking, was resoundingly highlighted.
When community programmes like Comm-TCP are evaluated, primarily quantitative, organisational data are utilised, such as, hospital readmission (Comans et al., Reference Comans, Peel, Hubbard, Mulligan, Gray and Scuffham2016; Heppenstall et al., Reference Heppenstall, Chiang and Hanger2018) and falls (Peel et al., Reference Peel, Hubbard and Gray2013; Sezgin et al., Reference Sezgin, O’Caoimh, Liew, O’Donovan, Illario, Salem, Kennelly, Carriazo, Lopez-Samaniego, Carda, Rodriguez-Acuña, Inzitari, Hammar and Hendry2020). Outcomes are often reported utilising effectiveness (Sezgin et al., Reference Sezgin, O’Caoimh, Liew, O’Donovan, Illario, Salem, Kennelly, Carriazo, Lopez-Samaniego, Carda, Rodriguez-Acuña, Inzitari, Hammar and Hendry2020) and safety quality (Peel et al., Reference Peel, Hubbard and Gray2013; Sezgin et al., Reference Sezgin, O’Caoimh, Liew, O’Donovan, Illario, Salem, Kennelly, Carriazo, Lopez-Samaniego, Carda, Rodriguez-Acuña, Inzitari, Hammar and Hendry2020) indicators without consideration of how these programmes are perceived by consumers. The dilemma of what to evaluate in TCPs has been highlighted recently in a published scoping review in Canada (Mcgilton et al., Reference Mcgilton, Vellani, Krassikova, Robertson, Irwin, Cumal, Bethell, Burr, Keatings and McKay2021). Cations et al. (Reference Cations, Lang, Crotty, Wesselingh, Whitehead and Inacio2020) has also suggested a need to capture how TCP resources are used as a potential indicator of a pathway to success for those people who improve or do not worsen following TCP.
The voices of caregivers have not frequently been included in previous research. When caregiver burden is considered, little detail is provided in how this burden is measured, for example, when comparing two models of care e.g., ‘discharge planning’ versus ‘standard hospital discharge’ (Allen et al., Reference Allen, Hutchinson, Brown and Livingston2014). One study in Australia explored the perspectives of family caregivers involved in providing ‘family-assisted therapy’ as part of TCP (Lawler et al., Reference Lawler, Taylor and Shields2015). This scarcity of the voices of caregivers is a concern, as there is already an expectation that adult child and older spousal caregivers will be required to expedite discharge from hospital to home. There is a risk of poor understanding of the care demands on caregivers and how such caregivers perceive the resources they are offered to meet these demands. Future research or practice initiatives should specifically record and evaluate caregiver responses to the included components of Comm-TCP, i.e., allied health training at home, type of communication with providers, types and usability of equipment and technology, and confidence with use, etc.
Findings from our study indicate that older people, with little cognitive difficulty, can direct support and therapy services to address their own needs. These older people prioritised hygiene and walking goals, often not requiring significant time (4–12 weeks) to make decisions about how that support (equipment and/or people) was provided. This finding suggests that timely introduction, or cessation, of social supports are needed with some consumers (with little functional disability), perhaps by ascertaining confidence of older people for key task completion. Future evaluations of community programmes should perhaps consider different streams of support that could be flexibly adjusted to individual needs promptly when home.
Finally, our PCC mapping exercise has illustrated how qualitative data may be utilised to explore whether a programme adheres to PCC principles. We acknowledge that this assessment is not conclusive evidence; however, through this mapping exercise, we endeavoured to link qualitative data on Comm-TCP to evidence-informed theoretical constructs. In our view this is an important departure from previous studies, as we attempted to show whether Comm-TCP was delivered with PCC constructs endorsed by health networks (Jo Delaney, Reference Jo Delaney2018). Furthermore, when evaluating TCPs there is little consideration of whether a PCC approach is implemented. A review by Allen et al. (Reference Allen, Hutchinson, Brown and Livingston2014) highlighted that PCC indicators were only reported in 50% of their included twelve studies. Future research should consider grounding of a study design in the theoretical model purported to underpin the ‘model of care’ being evaluated. Use of this approach would enable identification of any gaps to key components within that ‘model of care’, as for example ‘engagement’ was identified as missing in both our participant groups. Further, recent research illustrates how a newly co-designed communication tool has potential to facilitate conversations between nursing staff, older people, health professionals and transitional care needs (Allen et al., Reference Allen, Hutchinson, Brown and Livingston2022). This tool example might enable documentation of concrete evidence for consumer engagement with TCP services.
Limitations and future research directions
This was a study conducted pragmatically by clinician researchers whilst also involved in their own clinical workload. This duality of roles may have meant potential participants were missed due to conflicting time demands. Most interviews were conducted prior to the onset of the Covid-19 pandemic; however, the last interview may have been influenced somewhat by hospital discharge pressures in 2021. Future research should examine the confidence consumers have with an older person remaining at home following hospital admission. If having confidence is implicated in fully realising new long-term care arrangements, then confidence-building should be targeted by TCP clinicians.
Conclusions and implications for practice and policy
There will continue to be demand on community-based programmes as populations age. The challenge for researchers and clinicians in care of older people is to ensure that existing programmes truly adapt flexibly to older person and caregiver needs. Consumers of Comm-TCP continue to identify essential mobility-related and continence care equipment, knowledgeable healthcare staff, and access to support workers when discharged home. However, it is still unknown how consumers acquire confidence in their ability to remain at home following hospital.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/S1463423626101716.
Acknowledgements
Our study group would like to acknowledge the participation and time of the older people and caregivers enrolled in the Community-based TCP, Western Health, and Western Health Office for Research for support of this work. We acknowledge Ms K. Watson’s contribution to the data collection and analysis and Ms S. Day for her invaluable comments on the manuscript. We also acknowledge the support of TCP management and clinicians without whose support this work would not have been possible.
Funding statement
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Competing interests
None.
Ethical standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional guidelines on human experimentation (The National Statement on Ethical Conduct in Human Research 2007 (updated 2018). https://www.nhmrc.gov.au/about-us/publications/national-statement-ethical-conduct-human-research-2023) and with the Helsinki Declaration of 1975, as revised in 2008. Written informed consent was obtained from all older adult and caregiver participants.


 Open access

