Introduction
Tuberculosis (TB) is the second leading infectious cause of death worldwide; up to one-third of the world's population is infected.Reference Newlands, Bailey, Johnson and Newlands1 The incidence of TB in the UK is generally believed to be increasing. Indeed, the prevalence of TB in the UK is currently at its highest point since 1987.Reference Kruijshaar, French, Anderson and Abubakar2 However, between 2005 and 2006 there was no actual increase in the UK overall, and the annual incidence remained at 14 per 100 000 population.Reference Kruijshaar, French, Anderson and Abubakar2 The incidence in Scotland is lower than that in England, Wales and Northern Ireland. However, the incidence of TB in Scotland is unevenly distributed, with the Greater Glasgow and Clyde region contributing the majority of reported cases (46.6 per cent) within Scotland in 2006.Reference Kruijshaar, French, Anderson and Abubakar2
Tuberculosis is relatively rare in the head and neck. Its most common manifestation in this region is cervical lymphadenopathy, frequently involving the posterior triangle and in particular the supraclavicular region.Reference Nalini and Vinayak3 Laryngeal TB is now rare and makes up less than 1 per cent of all TB cases.Reference Nalini and Vinayak3 Laryngeal TB can involve any part of the larynx and its appearance is varied.Reference Newlands, Bailey, Johnson and Newlands1 Tuberculosis can also involve the salivary glands, tonsil, nasal cavity and ear.Reference Newlands, Bailey, Johnson and Newlands1
Several investigative and diagnostic tests for TB are available. Ninety-eight per cent of patients with cervical lymphadenitis secondary to TB will have a positive tuberculin sensitivity skin test (known as the Mantoux test).Reference Newlands, Bailey, Johnson and Newlands1 Fine needle aspiration (FNA) cytology is quoted in many studies as a useful test for evaluating tuberculous lymphadenitis. However, there are limitations when acid-fast bacilli are not found in smears, and subsequent culture of Mycobacterium tuberculosis takes six to eight weeks. Nucleic acid amplification techniques can identify mycobacterial DNA or RNA from aspirates, and have better positive and negative predictive values than direct microscopy.Reference Newlands, Bailey, Johnson and Newlands1 However, these techniques are expensive and time-consuming.
The current study aimed to review how suspected cases of head and neck TB presenting in the Greater Glasgow and Clyde Health Board were diagnosed, and in particular which diagnostic methods were most accurate.
Materials and methods
We retrospectively reviewed the data of all cases of TB notified to the Greater Glasgow and Clyde Health Board from February 2000 to October 2007. This information was obtained from the Enhanced Surveillance of Mycobacterial Infections system, a clinical surveillance database for TB in Scotland established by Health Protection Scotland in 2000. We included all cases of TB with a head and neck presentation. Local access to radiology, pathology and microbiology departments was required to verify database information.
We looked specifically at which diagnostic investigations were used, i.e. FNA, core biopsy or lymph node excision biopsy. We recorded whether radiological guidance was used during FNA. All core biopsies were performed within a radiology department, using high frequency linear probe ultrasound scanning and an Achieve needle using a ‘no-throw’ technique. After written consent was obtained, two biopsies were taken using a 16 G needle under local anaesthetic. Patients were observed for 30 minutes post-biopsy, prior to leaving the department. In all cases, we evaluated whether the diagnosis was achieved by histological or cytological analysis, by microbiological culture, or by both.
This was a retrospective review and did not involve any alteration of investigation, management or clinical outcome, so no specific ethical approval was required. The database of notified TB cases was accessed with the permission of Health Protection Scotland, for the purpose of this article.
Our figures were derived from this database, which recorded all notified Scottish cases of TB. Therefore, because we only had information regarding true positives and false negatives, sensitivity calculations were used to evaluate and compare the different diagnostic tests used for head and neck tuberculous lymphadenopathy.
Results and analysis
There were 1298 new cases of TB notified in Greater Glasgow within the seven-year study period. The male to female ratio for these cases was 2:1 (62.2 per cent male, 37.6 per cent female and 0.2 per cent unknown). The median age of patients diagnosed with Mycobacterium tuberculosis infection was 46 years (range, 2 months to 103 years). A total of 856 cases were diagnosed with pulmonary TB (66 per cent), while the remaining 442 cases were non-pulmonary.
Of the 1298 new cases of TB, 148 (11 per cent) presented with signs and symptoms related to the head and neck. Within this group, the male to female ratio was 1:1. The average patient age was 43 years, with an age distribution of one to 90 years. Of these 148 patients, 31 per cent were born in the UK, 55 per cent were born outside the UK and in 14 per cent the birthplace was unknown. The racial distribution was 35 per cent Caucasian, 34 per cent Pakistani, 25 per cent Indian and 20 per cent Black African.
One hundred and eighteen patients had disease contained solely within the head and neck region. A further 30 patients had additional sites of involvement: 16 had pulmonary TB, two had pleural involvement, nine had intrathoracic lymphadenopathy, one had bone and joint involvement, and two had gastrointestinal involvement. The most common head and neck presentation was cervical lymphadenopathy (144 patients), followed by laryngeal TB (two patients), parotid TB (two patients) One of the patients with tuberculous cervical lymphadenopathy also had tonsillar TB (Table I).
Data for patients with head and neck TB

Pts = patients; TB = tuberculosis
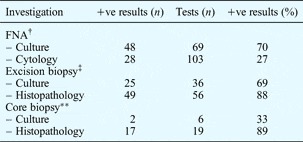
In the 144 patients with cervical tuberculous lymphadenopathy, the most commonly used investigation in head and neck presentation cases was FNA (119 patients), followed by lymph node excision biopsy (57 patients) and core biopsy (19 patients). Core biopsy and excision biopsy had a similar overall diagnostic sensitivity (95 and 91 per cent, respectively), while FNA had a lower overall sensitivity of 53 per cent. There was a statistically significant difference between the sensitivity results for FNA versus core biopsy (p = 0.0003, Fisher's exact test) and FNA versus excision biopsy (p < 0.0001, Fisher's exact test). There was no statistically significant difference between the sensitivity results for core biopsy and excision biopsy (p = 1, Fisher's exact test).
Microbiological culture of FNA samples had a higher diagnostic sensitivity, of 70 per cent, while culture of lymph node biopsies had a sensitivity of 69 per cent and culture of core biopsies had a sensitivity of only 33 per cent. Cytological examination of FNA samples had a sensitivity of only 27 per cent, while histopathological examination of excision biopsies had a sensitivity of 88 per cent, and histopathological examination of core biopsies had a sensitivity of 89 per cent.
Of the 119 FNA procedures performed, 103 samples were sent for cytological examination but only 69 samples were sent for microbiological culture. The diagnostic sensitivity of FNA culture was higher than that of FNA cytology (being 70 and 27 per cent, respectively).
However, lymph node excision biopsy and core biopsy samples showed a higher diagnostic sensitivity for histological examination than for microbiological culture (Table II). Of the 56 lymph node excision biopsies performed, all were sent for histopathology and 36 (64 per cent) were sent for culture. Similarly, all 19 core biopsy samples were sent for histopathology and six (32 per cent) were sent for culture.
Diagnostic test results*

* For Mycobacterium tuberculosis lymphadenitis. †n=119 procedures; ‡n = 56 procedures; **n = 19 procedures. +ve = positive; FNA = fine needle aspiration
Ultrasound guidance was used for FNA in only 26 of 119 cases. Ultrasound-guided FNA had a sensitivity of 50 per cent, versus 54 per cent for non-ultrasound-guided FNA.
Forty-one patients were diagnosed by positive culture alone (28 per cent) and 52 by histopathological diagnosis alone (36 per cent). The requirement for a positive histopathological diagnosis was granulomatous lymphadenitis which was positive for acid-fast bacilli, or caseating granulomas. Thirty-six patients (25 per cent) had their TB diagnosis confirmed by both microbiology and histopathology or cytology. Acid-fast bacilli were found in the smears of 25 per cent of patients. In 5 per cent of patients, it was unclear how the diagnosis of TB had been confirmed. Results were unavailable for 6 per cent of patients.
Discussion
The majority of patients with TB of the head and neck have cervical lymph node involvement. Clinicians should be aware of TB lymphadenitis as a differential diagnosis in patients presenting with head and neck lymphadenopathy. Risk factors such as immunosuppression, TB exposure history and ethnic origin should be considered. Clinicians should be alerted by clinical manifestations of TB such as constitutional or respiratory symptoms. Specific features of the cervical nodes should also raise clinical suspicion of TB, such as posterior triangle and supraclavicular location, lack of tenderness, and discharging sinuses.
Our data showed that FNA was the commonest initial diagnostic investigation in patients with head and neck lymphadenopathy. However, we found a low diagnostic sensitivity for FNA (53 per cent) in the investigation of tuberculous lymphadenitis. The sensitivity of FNA was increased by sending the FNA sample for microbiological culture. The sensitivity of FNA was not increased by the addition of ultrasound guidance (being 50 per cent with ultrasound guidance versus 54 per cent without). However, it is difficult to draw conclusions from this, as only a small numbers of patients (26) received ultrasound-guided FNA.
As expected, lymph node excision biopsy had a higher diagnostic sensitivity (91 per cent) than FNA, as the former provides more tissue for both histopathological and microbiological analysis. However, our data showed that core biopsy performed under ultrasound guidance had a comparable diagnostic sensitivity (95 per cent).
All samples taken for the investigation of TB should be sent for both histopathological and microbiological analysis. However, if this is not possible and there is limited sample material available, then our data suggest that FNA should be sent preferentially for acid-fast bacilli testing and culture. Similarly, lymph node excision biopsies and core biopsies should be sent for histopathology, in order to maximise the diagnostic yield from a small sample.
There are ever-increasing demands on ENT surgeons to perform lymph node excisions in cases in which TB is suspected but other, simpler methods have been unable to confirm the diagnosis. Such procedures consume valuable operating theatre time and carry a risk of significant patient morbidity, not least the risk of general anaesthetic complications particularly in frail or immunocompromised patients. Lymph node excision is also associated with complications, including infection, scarring and nerve injury.Reference Ammari, Bani Hani and Ghariebeh4 It is well recognised that excisional or incisional biopsies may result in a longer-term discharging sinus.Reference Baek, Kim, Ko and Chu5
It has been demonstrated that the diagnostic sensitivity of core biopsy is equivalent to that of lymph node excision biopsy. Ultrasound-guided core biopsy should be capable of accurately sampling the abnormal area (which will be highlighted ultrasonically), and the core of tissue obtained appears to be sufficient for a positive diagnosis. Furthermore, ultrasound-guided core biopsy has been shown to have a low incidence of complications.Reference Kim, Kim, Kim, Yang, Park and Park6, Reference Song, Cheong, Kee, Lee, Sohn and Kim7
The current study focussed on an area of clinical head and neck TB presentation which has previously seen only limited research. Tuberculous patients with extra-pulmonary TB, including head and neck tuberculous lymphadenopathy, are often the most challenging diagnostically. The current study included a large number of patients with head and neck TB (148); therefore, we can draw from it reasonable conclusions on the best method for the investigation and diagnosis of TB within the head and neck.
Ours was a retrospective study and therefore had limitations regarding data quality, which was reliant upon the accuracy and completeness of TB notifications, and upon the microbiological, radiological and histopathological information recorded.
All patients included in our study had a confirmed diagnosis of TB. The study did not include patients presenting with head and neck lymphadenopathy in whom TB was excluded and other pathology found.
Our study found a lower diagnostic sensitivity for FNA, compared with many other studies. Only one retrospective study of 99 cases of tuberculous lymphadenitis found a similar FNA sensitivity, of 46 per cent; this same study found a sensitivity for lymph node excision biopsy of 97 per cent.Reference Memish, Mah, Mahmood, Bannatyne and Khan8 Another study reported a series of 1349 FNA biopsies from the head and neck region of 1193 patients, and found a diagnostic specificity for FNA of 93 per cent, and a sensitivity of 77 per cent in diagnosing TB-related granulomatous lymphadenopathy.Reference Lau, Wei, Hsu and Engzell9 A further study showed that the diagnosis of tuberculous lymphadenitis could be improved further, to 90 per cent specificity and 84 per cent sensitivity, by the combined use of FNA and tuberculin skin testing (Figure 1).Reference Lau, Wei, Kwan and Yew10
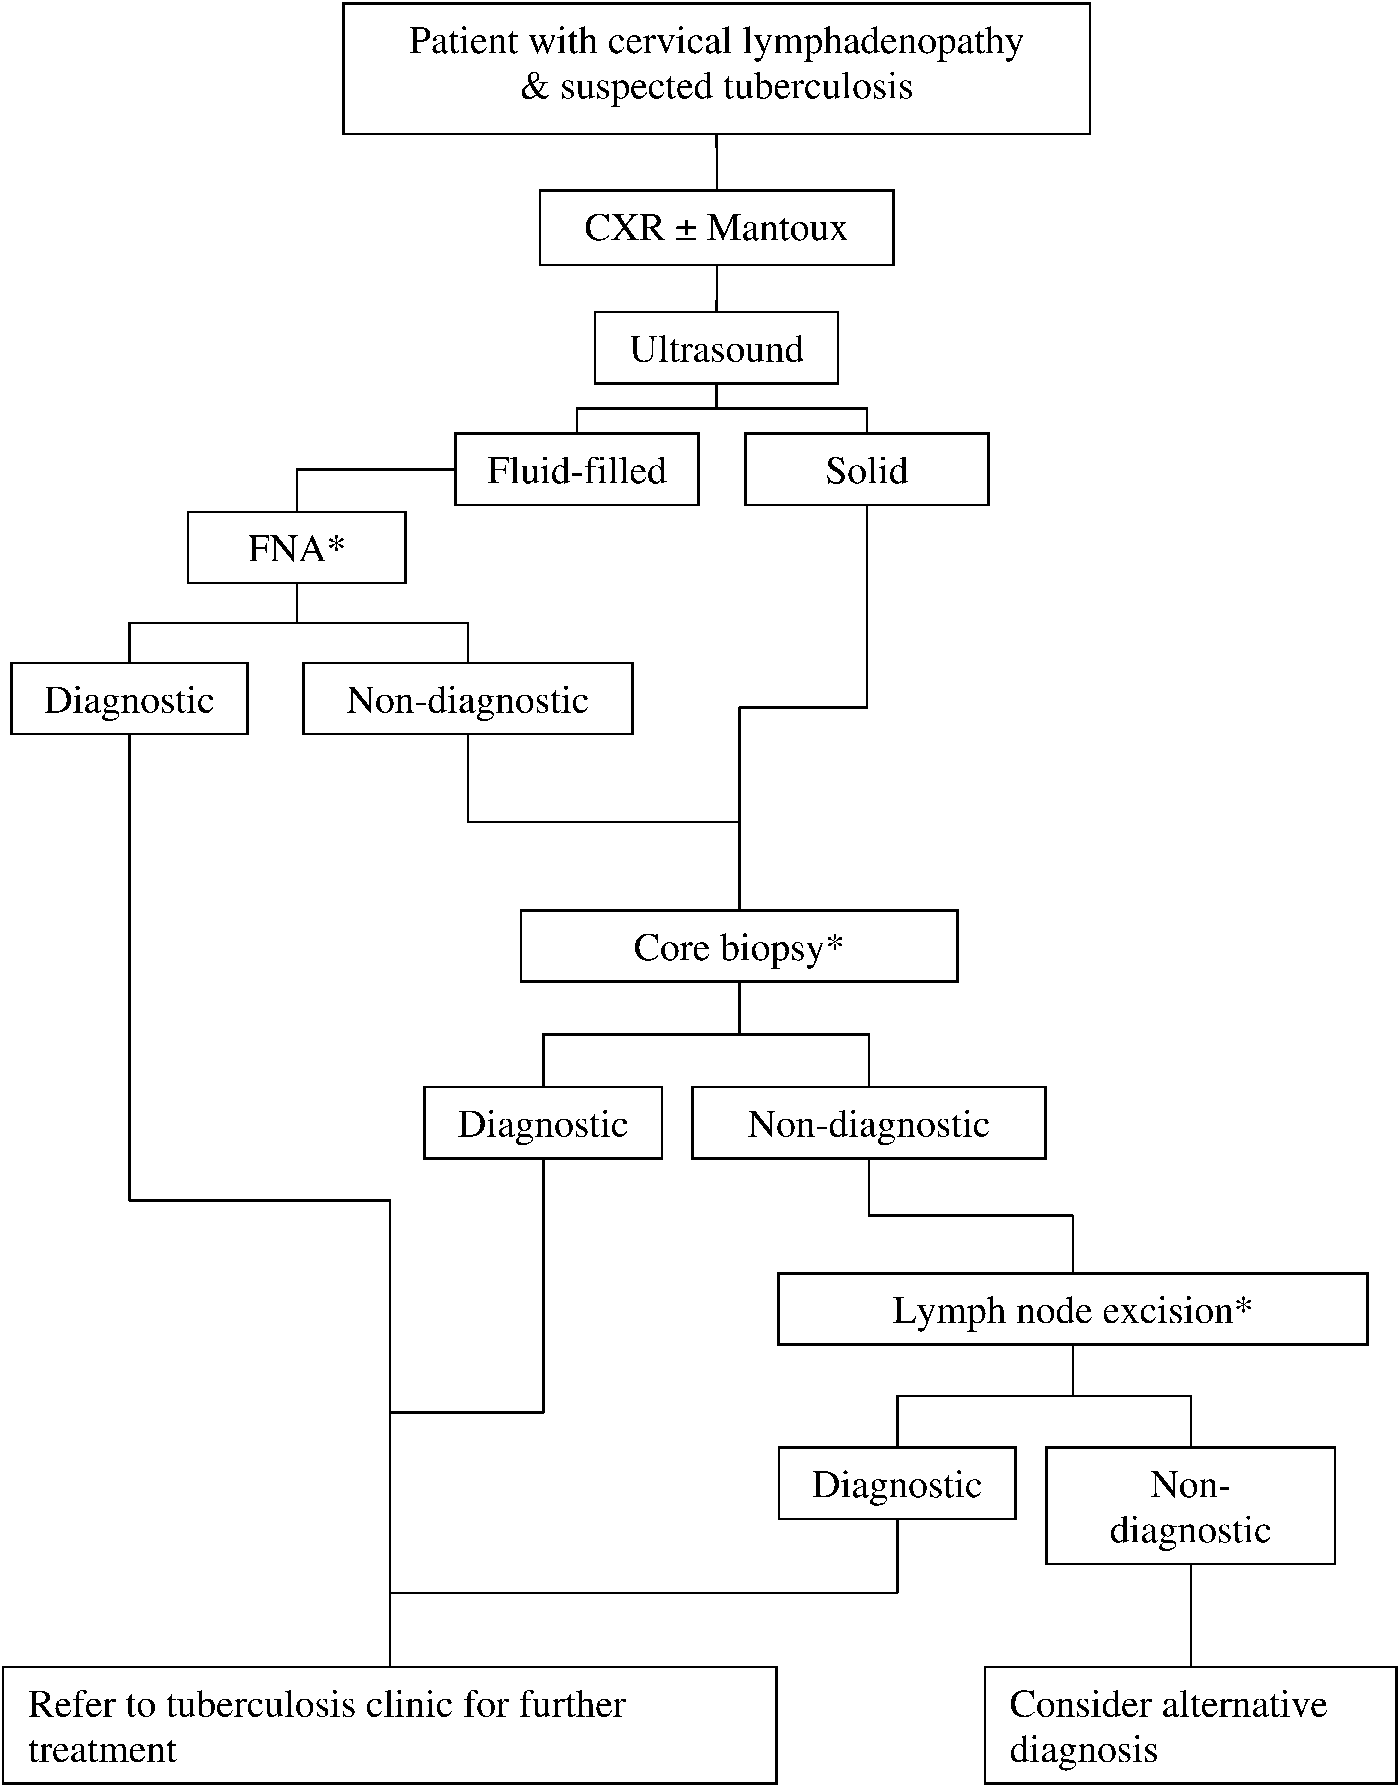
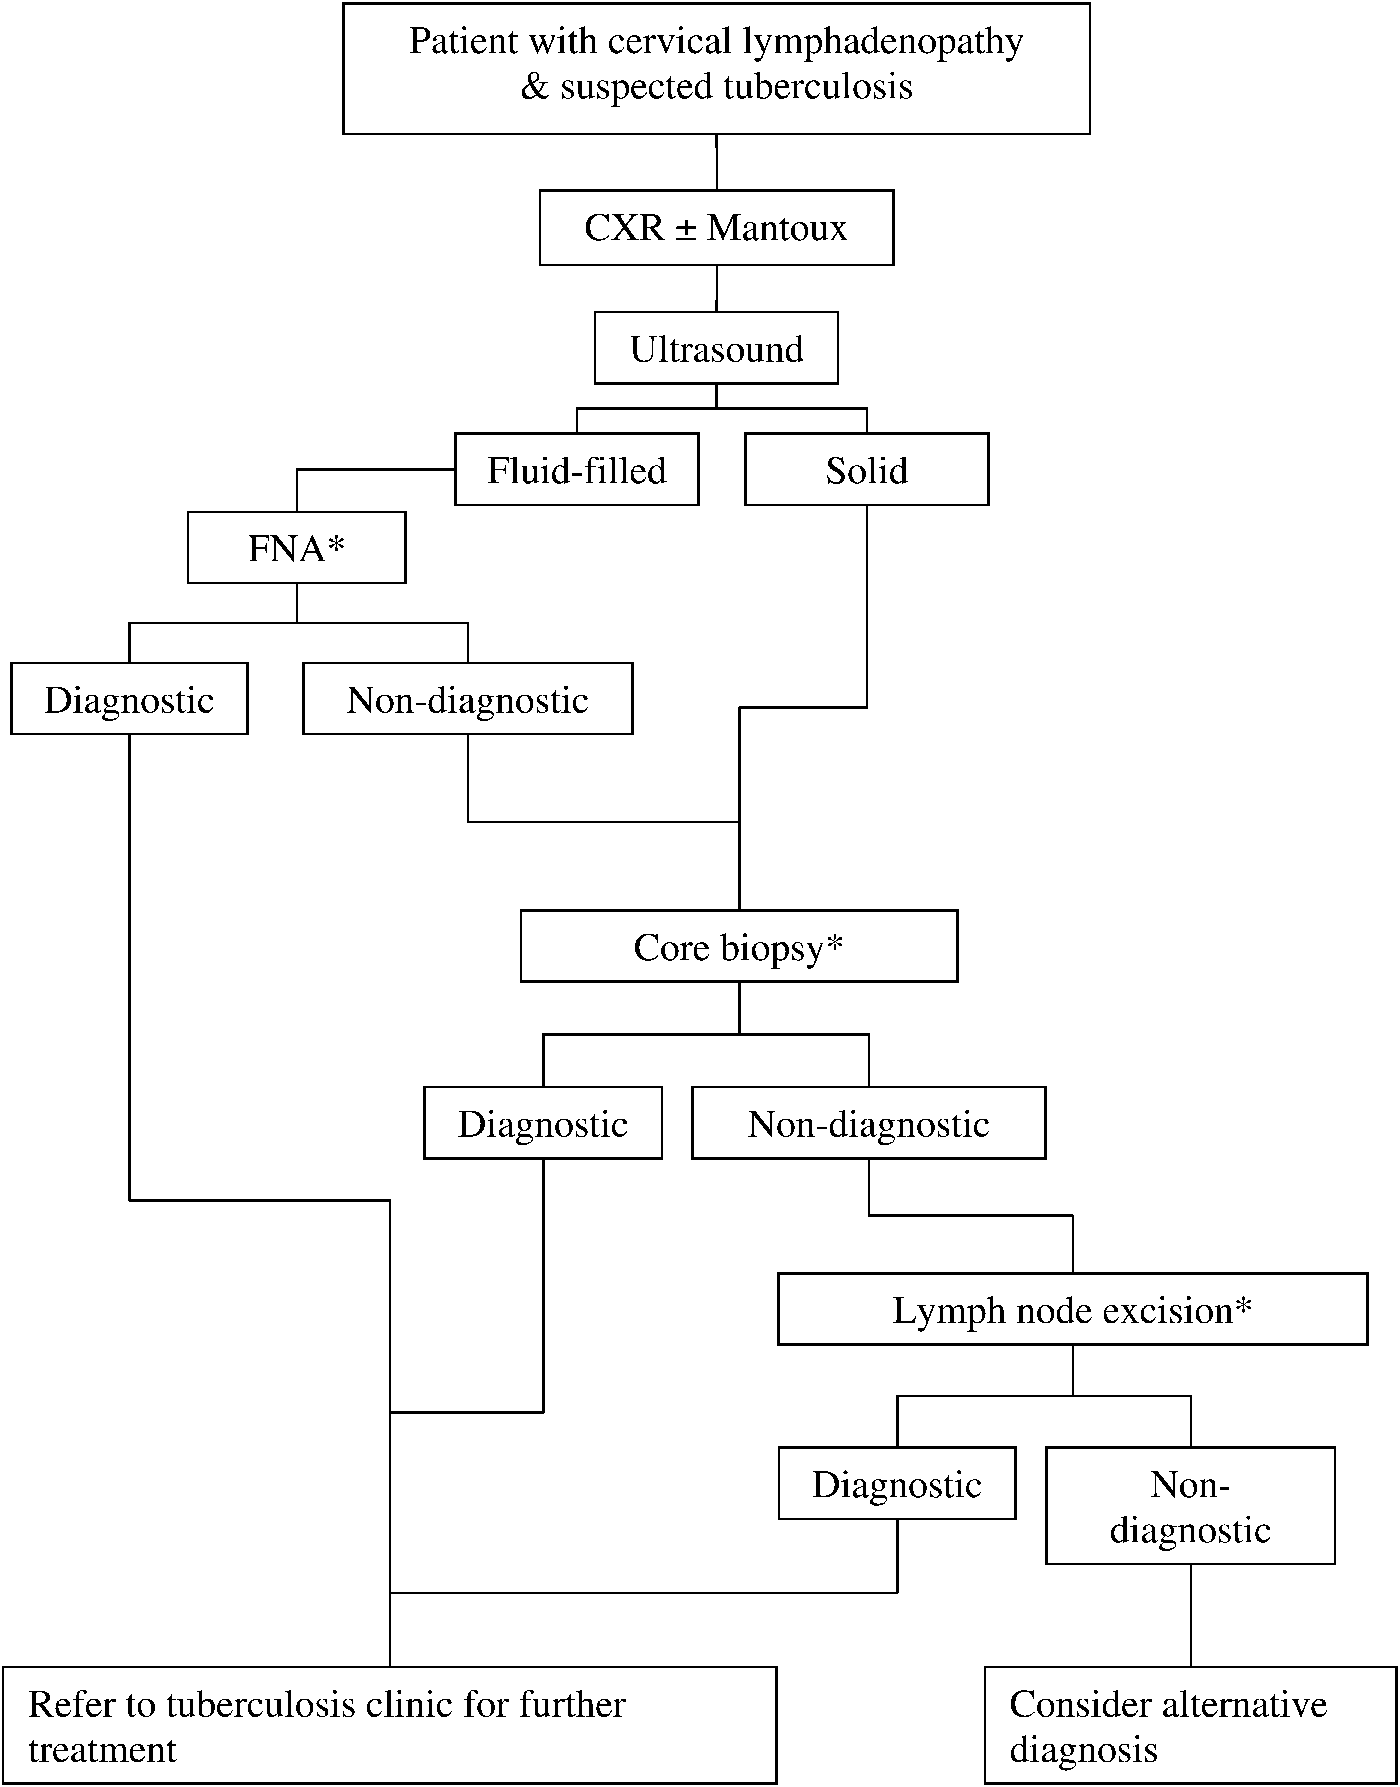
All patients with suspected Tuberculous cervical lymphadenopathy should be investigated primarily with chest x-ray and Mantoux testing. Ultrasound can then be used to determine if the lymph nodes are solid or fluid filled. FNA should be performed on fluid filled nodes and core biopsy used to investigate solid lymph nodes. All samples obtained should be sent for both microbiology and cytology/histopathology. If core biopsy is non-diagnostic then lymph node excision should be performed. *Samples sent for microbiology and cytology or histopathology. CXR = chest X-ray; FNA = fine needle aspiration
The majority of studies have found FNA to have a sensitivity of 70–85 per cent.Reference Nalini and Vinayak3, Reference Ammari, Bani Hani and Ghariebeh4 One of the reasons for this variability may be the level of clinical suspicion of TB. In our study, the overall low diagnostic sensitivity of FNA was related to the type of analysis the samples were sent for. The majority of FNA samples (87 per cent) were sent for cytology rather than for culture (58 per cent), in order to exclude malignancy. We found that FNA samples sent for culture had a much higher diagnostic sensitivity for TB than those sent for cytology.
• Cervical lymphadenopathy is the most common manifestation of tuberculosis (TB) in the head and neck
• The majority of 2006 Scottish TB cases (46.6 per cent) occurred in Greater Glasgow and Clyde
• This study found equivalent sensitivities for core biopsy and lymph node excision biopsy (95 and 91 per cent, respectively), but a lower sensitivity for fine needle aspiration (53 per cent), for the diagnosis of head and neck TB
• Fine needle aspiration is a useful investigation for fluctuant cervical lymph nodes suspicious for TB, but core biopsy should be used for solid nodes
Our study found a prevalence of acid-fast bacilli on smear testing of 25 per cent, which is comparable to other studies' findings (i.e. approximately 20 per cent).Reference Al-Serhani11 One study suggested that histological specimens provided the most reliable indicator of mycobacterial infection.Reference Manolidis, Frenkiel, Yoskovitch and Black12 Although the definitive diagnosis is based on culture, treatment is often commenced based on histological examination. This is because isolation of mycobacterial infection has a low sensitivity, and also because the process takes a long time.Reference Baek, Kim, Ko and Chu5
Conclusion
With the ever-expanding role of radiologically guided investigations, many patients with suspected head and neck TB could be referred directly to the radiology department for FNA of a fluctuant lymph node, or core biopsy in the case of a solid node. Specimens should be sent for both histopathology and microbiological analysis. Patients who cannot be diagnosed by these methods should then be referred to the ENT department.