


Introduction
Evidence has been adduced to support the hypothesis that mammalian (including human) sex ratios (proportions male) at birth are causally associated with the hormone levels of both parents around the time of conception (James, Reference James1996, Reference James2004, Reference James2008a, Reference Jamesb). Almost all this evidence is correlational in nature and so is susceptible to alternative interpretations. However for ethical reasons, direct endocrine experimentation cannot be undertaken on human beings for the purpose of testing its effect on offspring SR. So the present note will continue the practice of commenting on the implications of recent sex ratio findings for this hypothesis. Only if, and when, it seems that the hypothesis is capable of accommodating all the available empirical data, will it become established. In that sense, the present paper continues a process of ‘testing’ the hypothesis. Variables to be discussed here include ‘sociosexual orientation’, female genital cutting, the sexes of prior sibs, finger length ratios, the autism spectrum disorder, parental occupation and maternal eating disorders. It would be very helpful if readers were to communicate data that apparently contradict the hypothesis.
Variables testing hypothesis
‘Sociosexual orientation’
The generalized Trivers–Willard hypothesis (gTWH) proposes that parents who possess any heritable trait that increases male reproductive success at a greater rate than female reproductive success in a given environment will have a higher-than-expected offspring SR (Kanazawa & Apari, Reference Kanazawa and Apari2009). These authors plausibly suggested that one heritable trait that increases the reproductive success of sons more than that of daughters is what they call ‘unrestricted sociosexual orientation’ (measured by number of sexual partners, frequency of sex, and attitudes toward relationship commitment and sexual exclusivity). Accordingly they predicted that unrestricted parents would produce offspring with a higher SR than restricted parents. And (following Gangestad & Simpson, Reference Gangestad and Simpson1990) they presented data that confirmed their prediction. The purpose here is to show that this finding is accommodated by my hormonal hypothesis of sex determination.
It will be seen that the definition of unrestricted sociosexual orientation is similar to that of ‘sensation-seeking’, which has been defined as ‘hedonistic pursuit of pleasure through extraverted activities including social drinking, parties, sex and gambling’ (Mealey, Reference Mealey1995). It was originally reported that sensation-seeking correlates with gonadal hormone levels (testosterone in men and oestrogen in women) (Daitzman & Zuckerman, Reference Daitzman and Zuckerman1980; Zuckerman, Reference Zuckerman1994). This has been confirmed in two large samples of men (Dabbs & Morris, Reference Dabbs and Morris1990; Bogaert & Fisher, Reference Bogaert and Fisher1995), and in a large sample of adolescent girls (Vermeersch et al., Reference Vermeersch, T'Sjoen, Kaufman and Vincke2008). Accordingly it seems reasonable to propose that people of ‘unrestricted sociosexual orientation’ have high gonadal hormone levels. If that were so, then the findings of Kanazawa & Aparo (Reference Kanazawa and Apari2009) would be explained by my hypothesis that high parental levels of testosterone (in men or women) and oestrogen (in women) around the time of conception are associated with subsequent births of sons (James, Reference James1996, Reference James2004, Reference James2008a, Reference Jamesb).
Female genital cutting
Female genital cutting (FGC) is otherwise known as ‘female genital mutilation’ or ‘female circumcision’. Martin & Williams (Reference Martin and Williams2008) reported on 413,384 births in 22 African countries. In nine of these countries, the FGC rate is 0%, and among the other thirteen, prevalence rates range from less than 10% to over 90%. These authors reported that FGC is associated with increases in offspring SR (odds ratio 1.019 : 95% CI 1.007–1.032). Stewart et al. (Reference Stewart, Morison and White2002) studied 2188 married women in the Central African Republic and (after adjusting for confounders) reported that FGC has no appreciable effect on coital frequency. However, Behrendt & Moritz (Reference Behrendt and Moritz2005) described 23 FGC Senegalese women and 24 controls. Most of the operations had occurred when the subjects were aged 5–10 years. Their mean age at interview was 22.9 years (viz about 15 years after the operation on the average). In no case of FGC had analgesics or narcotics been used. All but one FGC subject remembered the day as traumatizing. Ninety per cent of them described feelings of intense fear, horror and severe pain. For 78% of them the procedure was performed unexpectedly and without preliminary explanation. About 80% of the FGC women met criteria for affective or anxiety disorders. In contrast, only one subject among the non-FGC controls fulfilled the diagnostic criteria of affective disorder. Cases, as contrasted with controls, showed a significantly higher percentage of post-traumatic stress syndrome.
In female mammals (including humans), the major source of androgens is the adrenals. These respond to stress of many sorts, e.g. infectious disease, psychotic disorder, surgical trauma and strenuous exercise (Kemper, Reference Kemper1990; Powell et al., Reference Powell, Lovallo, Matthews, Meyer, Baum and Stone2002; Swaab et al., Reference Swaab, Bao and Lucassen2005). So it seems reasonable to propose that (at least in some women) the stress of genital cutting causes a long-term increase in adrenal androgens, which in turn are responsible for the excess of sons reportedly born to these women. The point is testable. (And indeed, a long-term increase in adrenal androgens in FGC women would be interpretable as a long-term detrimental effect of the operation.) It will be noted that the data relating offspring SR to FGC seem to be at variance with the predictions of the hypothesis of Trivers & Willard (Reference Trivers and Willard1973). However, if the present speculation is correct, it illustrates how that hypothesis is subject to hormonal constraints, as suggested in James (2006).
The sex(es) of prior sibs
Garenne (Reference Garenne2009) studied the variation of SR of a current birth by the sex(es) of the prior sibs. He used a sample of 2 million births from sub-Saharan Africa. He noted that for families with only sons, the SR (proportion male) of a current birth increased (roughly monotonically) from 0.511 for the first birth to 0.520 for the eighth birth. For families with only daughters, the SR of a current birth declined from 0.511 for the first birth to 0.485 for the eighth birth. It will be noted that this result is not symmetrical for males and females: the decline is sharper for females than is the increase for males. A similar feature had been noted in the data of Malinvaud (Reference Malinvaud1955). This author suggested that his data were fairly well fitted by the linear relationship
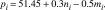
where pi is the probability estimate (measured as a percentage) that a present pregnancy will yield a boy, and ni is the number of pre-existing boys and mi is the number of pre-existing girls. In an attempt to partition the variance of p into Lexis and Poisson constituents, I suggested that Malinvaud's formula might be re-interpreted in the following words (James, Reference James1975):
(1) the probability of having a boy at each successive pregnancy declines by 0.1% as a direct effect of parity: in view of my hypothesis that coital rate influences sex ratio, I should simply interpret this decline as due to the overall decline in coital rate within each couple … and
(2) the estimate of the probability of having a boy at the next pregnancy is augmented by 0.4% for each pre-existing boy and diminished by the same amount for each pre-existing girl.
On the basis of this formulation I estimated the Lexis variance (Vb) of p between couples at about 0.002. However, though that estimate is close to those of Edwards (Reference Edwards1958) and Pickles et al. (Reference Pickles, Crouchley and Davies1982), it now seems an underestimate. It depends (as apparently did Edwards' estimate) on the assumption that the Poisson variance (V w) of p within couples is (in the terminology of James (Reference James2000a)) solely ‘systematic’ (as exemplified by a birth order effect) and without a ‘chaotic’ component. However, such a chaotic component is shown by the variation of p with the time of formation of the zygote within the fruitful cycle (James, Reference James2000b). Hence, as suggested above, my estimate (James, Reference James1975) of the Lexis variance in Malinvaud's (Reference Malinvaud1955) data now seems too low because I underestimated the Poisson variance. This judgment is fortified by Garenne's (Reference Garenne2009) analysis. He found that he could fit the data with an asymmetric log-gamma function. This suggested a substantial overall variance V, in p. In principle, p may be subject to Markov, Lexis and Poisson variation (Edwards, Reference Edwards1960). However, I have suggested that empirical evidence for Markov variation is not strong: moreover there seems no compelling biological ground for hypothesizing its existence (James, Reference James2000a). If we make the simplifying assumption that it does not exist, then the total variance V t is given by

where V b is the Lexis variance between parents in p and V w is the Poisson variance within parents in p.
Garenne's (Reference Garenne2009) result suggests that previous estimates of these Poisson and Lexis variances were too low (a suspicion offered in James, Reference James2000a). Moreover, this suggestion is strengthened by Garenne's (in press) report of a similar result on European populations. I have adduced evidence to suggest that both the Lexis and Poisson variances may be accommodated by the hormonal hypothesis of sex ratio determination (James, Reference James2009a).
Manning's finger length ratio (2D:4D)
Manning's R is defined as the ratio of the lengths of the 2nd and 4th digits (2D:4D). It was reported that in men, R correlates significantly and negatively with testosterone levels (Manning et al., Reference Manning, Scutt, Wilson and Lewis-Jones1998). So in accordance with my hypothesis (that high levels of parental testosterone are associated with sons) I predicted that in men, R would correlate negatively with offspring SR (James, Reference James2001). The prediction was significantly confirmed by Manning et al. (Reference Manning, Martin, Trivers and Soler2002). However, more recently, Helle & Lilley (Reference Helle and Lilley2008) reported that they could not detect such a phenomenon in respect of 244 contemporary post-reproductive Finnish women. What can be the explanation for this?
It has been suggested that Manning's R (as well as being negatively correlated with adult testosterone) is positively correlated with adult oestrogen levels (Manning, Reference Manning, Martin, Trivers and Soler2002; McIntyre et al., Reference McIntyre, Chapman, Lipson and Ellison2007). Moreover, I have hypothesized that (in women at any rate) high levels of oestrogen are associated with the production of sons (James, Reference James1996, Reference James2004, Reference James2008a, Reference Jamesb). So it would seem unwise to make a confident prediction on the relationship between women's R and their offspring sex ratio (because it is not known which parental hormone – oestrogen or testosterone – has the stronger association with offspring sex).
However, there are two grounds that jointly suggest that one may predict a relationship between women's R and offspring SR (proportion male). These are: (1) Manning & Fink (Reference Manning and Fink2008) reported highly significant negative and positive correlations between R and fertility for, respectively, very large samples of men and women; and (2) there is also a highly significant association between fertility (family size) and offspring sex ratio. This is exemplified in the sexes of the 4,794,304 children born within 998,760 sibships in Geissler's data for Saxony in 1876–85 reproduced in Edwards (Reference Edwards1958). In these data, the sex ratio increases steadily from 0.5138 for sibships of size 2 to 0.5192 for sibships of size 12. Similar data were published by Schutzenberger (Reference Schutzenberger1950) in respect of French births. [In parenthesis, it is worth noting that this positive association between human fertility and offspring sex ratio exists in spite of the well-established negative correlations between sex ratio and birth order and (probably) parental age (James, Reference James1987). It is also noteworthy that these sex ratio data constitute further evidence in favour of the influential hypothesis of Trivers & Willard (Reference Trivers and Willard1973). Highly fertile parents, to a slight but significant extent, preferentially produce sons.]
Thus there are grounds for supposing that R and SR are each independently associated with fertility: and that therefore there may be a correlation between R and SR, secondary to correlations of each with fertility. If this were correct, then (as shown in the Appendix), the expected correlations between R and SR would be negative in men (as reported by Manning et al., Reference Manning, Martin, Trivers and Soler2002) and positive in women. Accordingly I here hypothesize that in women, R and SR correlate positively.
It is becoming increasingly clear that in regard to R, standard errors of measurement are large in comparison with suspected effect size (Manning, Reference Manning2002; Voracek et al., Reference Voracek, Manning and Dressler2007).
And in sex ratio, any effect size may be suspected of being small. So to test the present hypothesis, only the results of very large samples would be expected to be persuasive. It would be useful if offspring sex ratios and R values were available in a sample comparable in size to that of the BBC Internet Study. Unfortunately respondents in that study were not questioned about the sexes of their children (Reimers, Reference Reimers2007).
The autism spectrum syndrome
Baron-Cohen et al. (Reference Baron-Cohen, Knickmeyer and Belmonte2005) hypothesized that high maternal intrauterine testosterone concentrations are causally associated with autism. If this were true, then in accordance with my hypothesis, it would explain the male excess among autistic probands; and I predicted (on the basis of both hypotheses) that they would also have a statistical excess of brothers (James, Reference James2008c). In that paper I noted that there are a number of neurodevelopmental disorders that show some behavioural overlap, which are thought to be of multifactorial threshold origin and which occur more frequently in boys than girls. Since genome investigations suggest possible genetic overlap among these (Smalley et al., Reference Smalley, Loo, Yang and Cantor2005), data were pooled on the sexes of sibs of probands with reading disorder (RD), attention deficit hyperactivity disorder (ADHD) and autism spectrum disorder (ASD). Contrasted with an expected US live birth sex ratio of 0.512, the pooled data showed a highly significant excess of brothers (χ2=9.97, p<0.002). More recently, this result has been confirmed by Mouridsen et al. (in press). These two results simultaneously strengthen both my hypothesis and that of Baron-Cohen.
Parental occupation
Baron-Cohen's work was also the inspiration for research by Kanazawa & Vandermassen (Reference Kanazawa and Vandermassen2005). Baron-Cohen (Reference Baron-Cohen2003) described two psychological dimensions: systemizing (on which autistic people score highly), ‘S’; and empathizing, ‘E’. There is substantial variation in scores on these dimensions. Men's mean S exceeds women's mean S: and women's mean E exceeds men's mean E. In his Figure 8 (p. 151), Baron-Cohen portrays these dimensions as orthogonal. But elsewhere (pp. 174–175) he questions whether they are independent. This doubt was later shown to be justified: Baron-Cohen and his colleagues have since provided evidence that fetal testosterone levels are at least partially associated with (responsible for?) scores on both traits. Fetal testosterone concentrations (assessed at routine amniocentesis) reportedly correlate positively with postnatal scores on autism scales (Auyeung et al., 2009), and negatively with children's empathy scores (Chapman et al., Reference Chapman, Baron-Cohen, Auyeung, Knickmeyer, Taylor and Hackett2006). There is also evidence that prenatal testosterone levels correlate positively with adult testosterone levels in women (Inqudomnukul et al., Reference Inqudomnukul, Baron-Cohen, Wheelwright and Knickmeyer2007) and in female Rhesus monkeys (Eisner et al., Reference Eisner, Barnett, Dumesic and Abbott2002); and in men (Sorenson et al., Reference Sorenson, Meier and Campbell1993; Manning et al., Reference Manning, Scutt, Wilson and Lewis-Jones1998). Lastly it has been reported that administration of testosterone to women reduces their empathizing behaviour (Hermans et al., Reference Hermans, Putnam and Van Honk2006).
The relevance of this excursus may now become apparent. Kanazawa & Vandermassen (Reference Kanazawa and Vandermassen2005) reported that engineers (systemizers) have significantly more sons, and nurses (empathizers) more daughters than controls. Viewed in this context, these data may be interpreted as supporting my hypothesis: I suggest that Baron-Cohen's systemizers have higher offspring sex ratios than his empathizers because they have higher prenatal and (more relevantly) postnatal testosterone levels on the average.
It is worth noting that Kanazawa & Vandermassen's (Reference Kanazawa and Vandermassen2005) result confirmed earlier work of Bernstein. In a series of papers this author presented evidence that offspring sex ratios varied positively with the ‘masculinity’ of the parents' occupations (Bernstein, Reference Bernstein1951, Reference Bernstein1981; Bernstein & Martinez-Gustin, Reference Bernstein and Martinez-Gustin1961). ‘Masculinity’ of an occupation was defined by her as the proportion of men in its employment force. It is also notable that the ranking of occupations on this scale was strikingly concordant with the ranking of occupations by the ‘androgenicity’ of the behaviour of their employees devised by Terman & Miles (Reference Terman and Miles1936). I suggest that parents (of both sexes) may be ranked by ‘masculinity’ of occupation, and that their testosterone levels correlate positively with the ‘masculinity’ of their occupation or ‘androgenicity’ of their behaviour (nursing and engineering included). Subsequent workers have categorized occupations by the testosterone levels of their male (Dabbs et al., Reference Dabbs, de la Rue and Williams1990) and female (Purifoy & Koopmans, Reference Purifoy and Koopmans1979) practitioners; these latter data give some support to my suggestion. Indeed, I should like to re-iterate Bernstein's suggestion that offspring sex ratios correlate positively with the ‘masculinity’ or ‘androgenicity’ (defined as above) of the parental occupations, and I should like to hypothesize that this correlation is mediated by parental testosterone levels. In this context, it may be noted that some systemizing occupations (e.g. engineering, surgery, architecture) require a high degree of visuo-spatial ability, which in turn is facilitated by high testosterone levels in men (Hooven et al., Reference Hooven, Chabris, Ellison and Kossleyn2004; Thilers et al., Reference Thilers, MacDonald and Herlitz2006; Martin et al., Reference Martin, Wittert and Burns2007) and women (Hausmann et al., Reference Hausmann, Slabbekoorn, Van Goozen, Cohen-Kettenis and Gunturkun2000; Gooren & Giltay, Reference Gooren and Giltay2008). It should be emphasized that some forms of deleterious occupational exposure affect offspring sex ratio (James, Reference James2006b): the above hypothesis is intended only to refer to occupations free from such exposures.
Maternal eating disorders
Bulik et al. (Reference Bulik, Holle, Gendall, Lie, Hoffman and Mo2008) reported that women with anorexia and bulimia have low offspring sex ratios. In conformity with my hypothesis (that low maternal oestrogen levels are associated with the subsequent births of daughters), women with anorexia (Brambilla et al., Reference Brambilla, Monteleone, Bortolotti, Dalle, Todisco and Favoro2003) and bulimia (Edler et al., Reference Edler, Lipson and Keel2007) reportedly have low oestrogen levels. I drew attention to this (James, Reference James2009b); and Bulik et al. (Reference Bulik, Torgersen, Reichborn-Kjennerud, Gendall and Von Holle2009) strengthened my claim by reporting that the low offspring sex ratios of their patients was not a consequence of endocrine treatment to facilitate conception: of their 37 anorexic patients, only one had had such treatment.
Further research
Further research is suggested above. Here that research is summarized.
The variation of p with the sex(es) of prior sibs
It would be useful if the meaning of the parameters of the log-gamma distribution could be interpreted in the light of Garenne's (Reference Garenne2009, in press) successful fit to sex ratio data. In particular, does the variance there estimated equal V t=(V w+V b) as defined above? If so, an attempt should be made to estimate (V b−V w). This would presumably be given by the variance of the distribution of the sexes of the first two sibs in sibships of all sizes. Then, V w and V b could be individually estimated from their sum and difference.
Female genital cutting
Are the androgen levels of FGT women high, as hypothesized above?
Manning's R
Do women's R values correlate positively with their offspring SR, as hypothesized above?
Parental occupation
Do offspring sex ratios correlate positively with ‘masculinity’ of parental occupation, the correlation being mediated by testosterone levels?
Concluding remarks on the congruity of three hypotheses
It is worth noting how evidence on the three sets of hypotheses (Baron-Cohen's (B), James' (J) and Manning's (M)) is mutually supportive. Several deductions have been drawn, each of which is dependent on a combination of two of these hypotheses. I have noted how two such deductions have been confirmed (one based on B and J in the ‘autism spectrum syndrome’ section; and one on J and M in the ‘Manning's finger length ratio’ section above). These two results strengthen all three hypotheses. A third deduction (based on B and M) relates to the values of Manning's R in autistic probands and their relatives. These values of R are reportedly strikingly and significantly low in contrast with expected population values (Manning et al., Reference Manning, Baron-Cohen, Wheelwright and Sanders2001). This result strengthens the hypotheses of both Baron-Cohen and Manning. A fourth deduction (based on B and M) relates values of Manning's R to empathizing and systemizing scores. In male students, a high (female-typical) R score was reportedly associated with an enhanced tendency to empathize and a reduced tendency to systemize (Von Horn, in press). This result also simultaneously strengthens the hypotheses of both Baron-Cohen and Manning.
Acknowledgments
The author is grateful to Dr M. Garenne (Institut Pasteur, Paris), Dr S. Helle (University of Turku, Finland), Dr S. Kanazawa (London School of Economics) and Professor J. F. Martin (Arizona State University) for sending copies of their papers.
Appendix
A potential explanation of the data of Manning & Fink (Reference Manning and Fink2008): the basis for a prediction
These authors reported highly significant negative and positive correlations between Manning's R (finger length ratio) and fertility (number of children) in, respectively, very large samples of men and women. Here I suggest an explanation of these correlations.
Let the finger length ratio be denoted by R, adult hormone concentrations by H, and fertility by F. Let us assume that the association between R and F is secondary to associations of both with H. The standard formula for the partial correlation between R and F, eliminating the effect of hormone concentrations, is
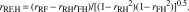
whence it follows that if (as assumed above) the partial correlation is zero, then

So the sign of r RF is dependent on the signs of the two correlations on the right-hand side of the equation. If these are both of the same sign, r RF will be positive; otherwise, r RF will be negative. The cases of the two sexes will be treated separately.
For men, the relevant hormone is testosterone. Accordingly the subscript H will be replaced by T. The correlations r RT and r FT are respectively negative and positive (see notes 1 and 2 below). Whence r RF is negative (as reported by Manning & Fink, Reference Manning and Fink2008).
For women, the relevant hormone is oestrogen. Accordingly the subscript H will be replaced by E. The correlations r RE and r FE are both positive (see notes 3 and 4 below). Whence r RF is positive (as reported by Manning & Fink, Reference Manning and Fink2008).
Notes to Appendix
1. It is assumed here that the negative correlation between R and adult testosterone levels in men reported by Manning et al. (Reference Manning, Scutt, Wilson and Lewis-Jones1998), Manning et al. (Reference Manning, Wood, Vang, Walton, Bundred, van Heyningen and Lewis-Jones2004) and Manning (Reference Manning2002) is veridical.
2. Testosterone in men is positively associated with a number of components of fecundability (the probability of conception in a month at risk), e.g. coital rate (Potter & Millman, Reference Potter and Millman1986; Mantzoras et al., Reference Mantzoras, Georgiadis and Trichopoulos1995) and sperm quality (Zalata, 1995). So in the absence of direct contradictory evidence, one would expect a positive correlation between men's testosterone levels and offspring number.
3. The correlation between R and E (adult oestrogen level in women) is taken to be positive as reported by McIntyre et al. (Reference McIntyre, Chapman, Lipson and Ellison2007).
4. The correlation between F and E in women is taken as positive because:
i. High oestrogen concentrations are associated with short cycles (Harlow et al., Reference Harlow, Baird, Weinberg and Wilcox2000; Windham et al., Reference Windham, Elkin, Fenster, Waller, Anderson and Mitchell2002).
ii. High oestrogen concentrations are associated with early menarche (Emaus et al., Reference Emaus, Espetvedt, Veirod, Ballard-Barbash, Furberg and Ellison2008).
iii. Oestrogen levels in women are positively associated with the duration of the fertile interval (that period during the woman's cycle in which the probability of conception is non-zero) (Burger, Reference Burger1989).


