Introduction
In the patients with large dural defects of the anterior and ventral skull base, there is a significant risk of post-operative cerebrospinal fluid (CSF) leak. Advances in surgical technique, instrumentation and intra-operative image guidance have made reconstruction of even large dural defects possible. Reconstruction with vascularised tissue is desirable to facilitate rapid healing, especially in irradiated patients.
The Hadad–Bassagasteguy flap, a vascular pedicled flap of the nasal septum mucoperiosteum and mucoperichondrium based on the posterior septal artery (branch of the sphenopalatine artery), was first developed at the National University of Rosario, Argentina, for the reconstruction of ventral skull base dural defects.Reference Hadad, Bassagasteguy, Carrau, Mataza, Kassam and Snyderman1 It is increasingly becoming a ‘workhorse’ for reconstruction in extended endonasal skull base surgery.
Endoscopic endonasal repair of traumatic CSF leaks with the posterior nasoseptal flap has a success rate of approximately 95 per cent, comparable to that of traditional approaches.Reference Hadad, Bassagasteguy, Carrau, Mataza, Kassam and Snyderman1 Fortes et al. used the Hadad–Bassagasteguy flap and reported a 5 per cent incidence of CSF leak, which is similar to the rate after open craniotomy.Reference Fortes, Carrau, Snyderman, Prevedello, Vescan and Mintz2 A posterior nasoseptal flap preserves the possibility of raising a Hadad–Bassagasteguy nasoseptal flap if needed; therefore, it is indicated when a CSF leak is possible but not probable.
Materials and methods
Study design and sampling
This prospective, non-randomised study was conducted in the Departments of Otorhinolaryngology and Neurosurgery at Bombay Hospital and Institute of Medical Sciences, Mumbai, India, from January 2013 to January 2017. Patients were selected from these departments, irrespective of gender, or urban or rural residence. We identified patients who underwent skull base surgery via an endoscopic endonasal approach where the posterior nasoseptal flap was harvested early during the procedure.
The study, conducted in a prospective manner, involved 100 patients with a CSF leak due to a skull base defect following endonasal skull base surgery. Post-operative CSF leak reconstruction was carried out with vascularised tissue to facilitate rapid healing. The design was similar to that of the studies by Hadad et al. and Kassam et al., which also used a posterior nasoseptal flap.Reference Hadad, Bassagasteguy, Carrau, Mataza, Kassam and Snyderman1,Reference Kassam, Thomas, Carrau, Snyderman, Vescan and Prevedello4
The study included all patients who underwent an endoscopic approach for resection of skull base pathologies, who had a significant risk of having a CSF leak on pre-operative assessment, and who experienced a traumatic high-flow CSF leak intra-operatively, when large skull base defects were being repaired using a posterior nasoseptal flap. Patients with nasoseptal injury due to trauma, previous surgery, or tumours infiltrating the nasal septum, pterygoid fossa or sphenoid sinus anterior wall, and patients aged less than 18 years, were excluded.
Data collection technique and tools
All patients who presented with impaired vision, hemianopsia, headache, nausea and vomiting, oculomotor paralysis, hypopituitarism, polydipsia, polyuria, amenorrhoea, or galactorrhoea underwent a complete pre-operative out-patient evaluation by a neurosurgeon, rhinological surgeon, endocrinologist and neuro-ophthalmologist when indicated.
The clinical diagnosis was established after taking a detailed history and conducting a clinical examination that included a systemic examination and local ENT examination. Assessment of the nose included anterior rhinoscopy, posterior rhinoscopy and paranasal sinus examination. Investigation of all patients included an electrocardiogram, complete haemogram, coagulation profile, liver profile, and assessment of serum creatinine, human immunodeficiency virus types 1 and 2, hepatitis B surface antigen, and blood sugar. Patients also underwent endocrine function evaluation, visual field and visual acuity examinations, and radiological evaluation.
In the radiological evaluation, axial, sagittal and coronal computed tomography sections are essential for a pre-operative review of the approach, including bony landmarks and relationships, extent of sinus and skull base pneumatisation, and areas of dehiscence with potential for injury. Gadolinium contrast enhanced magnetic resonance imaging (MRI) was conducted in all the patients, for detailed pre-operative assessment of intracranial content and extent. This revealed macroadenomas (maximum diameter of more than 1 cm) and small non-secretory tumours (less than 1 cm), termed microadenomas. Serial MRI scans can be used to monitor for progressive enlargement of microadenomas, before proceeding to surgery.
Written consent was obtained from each patient prior to surgery. All patients were operated on under general anaesthesia.
Posterior nasoseptal flap harvesting
A posterior nasoseptal flap is a Hadad–Bassagasteguy nasoseptal flap that involves elevating the pedicle of the Hadad–Bassagasteguy nasoseptal flap. The posterior nasoseptal flap was harvested at the beginning of the operation if a high-flow CSF leak was anticipated, and was placed in the nasopharynx for protection during the case.
The use of a vascular pedicle flap has become the preferred means of skull base reconstruction. The most commonly used technique is a vascular flap of the nasal septum mucoperiosteum and mucoperichondrium; the flap is pedicled on the nasoseptal artery, a branch of the posterior septal artery, which is one of the terminal branches of the internal maxillary artery.
The nasal cavity was decongested with oxymetazoline (0.05 per cent). The inferior, middle and superior turbinates were out-fractured to allow visualisation of the sphenoid anterior wall. This was conducted bilaterally to facilitate a bimanual technique, which allows the nasoseptal flap to take on one side, with a reverse flap on other side. The flap was designed according to the size and shape of the anticipated defect.
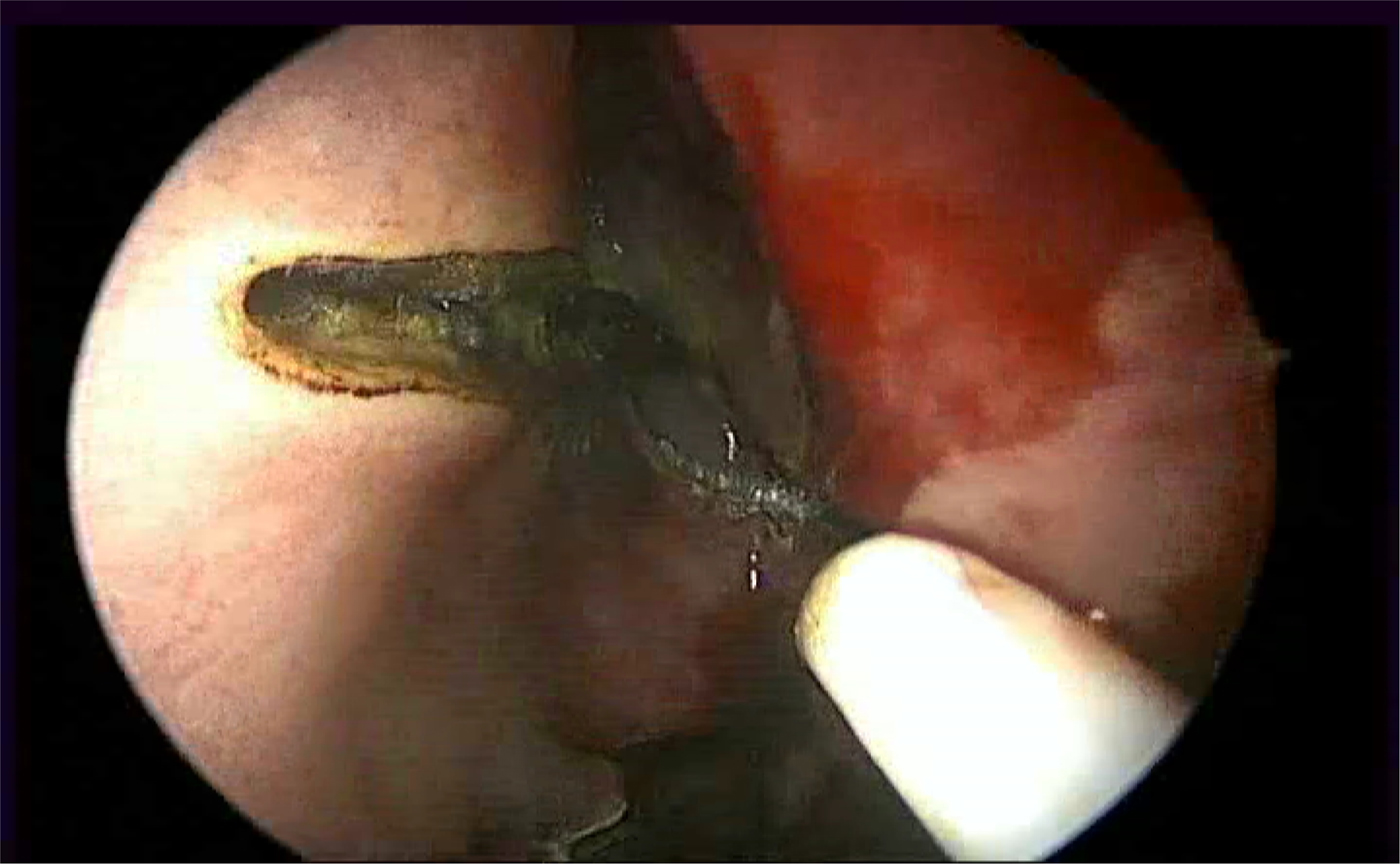
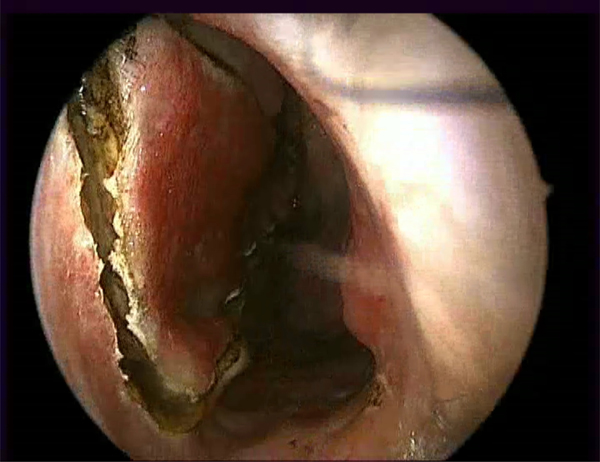
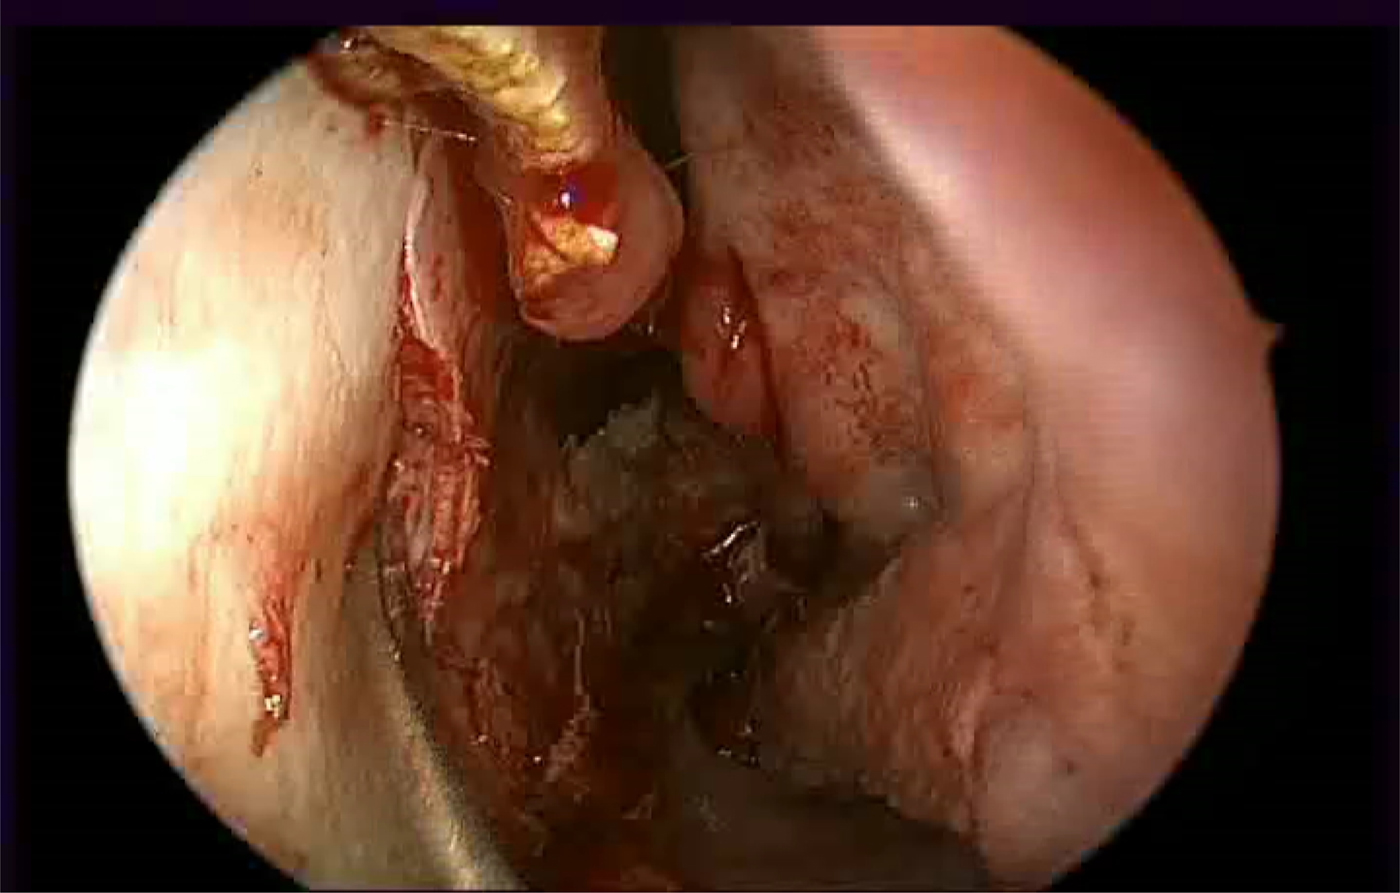
Two parallel incisions were made following the axial plane of the septum. A superior incision was made at the level of the sphenoid ostium up to the level of the anterior end of the middle turbinate, and then curved superiorly. In cases of a CSF leak, a standard Hadad–Bassagasteguy nasoseptal flap can be harvested by extending the incisions coming anteriorly to the mucocutaneous junction inferiorly to join the inferior horizontal line of incision. Inferior incision starts laterally just above the Eustachian tube opening, and continues along, just above the choana, to the septum. It then proceeds anteriorly along the floor of the nose to join the anterior vertical incision, allowing elevation of this Hadad–Bassagasteguy flap. The flap was elevated anteriorly with a freer elevator. Elevation of the flap from the anterior face of the sphenoid sinus was completed with preservation of a posterior lateral vascular pedicle. The technique was repeated bilaterally. Wide sphenoidotomy and posterior septectomy were subsequently performed.
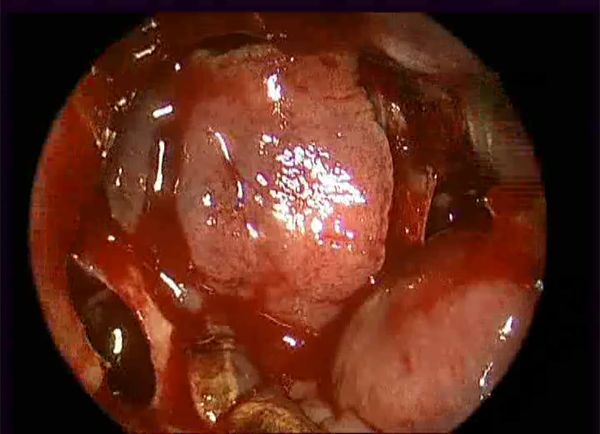
A Hadad–Bassagasteguy flap thus elevated can cover defects from the frontal recess to the clivus. A reverse flap was harvested on the other side, to cover the bare cartilage. Once harvested, the flap was displaced into the nasopharynx until the pathology was removed.
After the skull base approach and tumour resection, the subsequent skull base defect was prepared by denuding approximately 1 cm of mucosa around the bony defect to prevent delayed mucocele formation from trapped paranasal sinus mucosa. The sphenoid sinus was also completely denuded of mucosa in the transsellar and transplanum transtuberculum repairs, to avoid potential sphenoid sinus mucocele formation. This step additionally optimises flap adherence to the native bone, and prevents residual intervening mucosa from causing delayed flap dehiscence.
If there was no intra-operative CSF leak, at the end of pituitary surgery, the nasoseptal flap was translocated posteriorly to cover any denuded bone at the floor of the sphenoid sinus. In cases of a CSF leak, a standard Hadad–Bassagasteguy nasoseptal flap was harvested by extending the incisions. Fat harvested from the thigh or abdomen was used to assist in the repair, if required. Fibrin glue or other biological glue was used to help secure the flap, and nasal packing was utilised.
Figures 1–4 show the commencement of the incision, the harvesting of the flap, the continuation of the nasoseptal flap dissection from the underlying septal cartilage and the repositioning of the flap.
Starting the incision.

Harvesting the flap.

Continuing to dissect the nasoseptal flap from the underlying septal cartilage.

Repositioning of the flap.

Data analysis
Data analyses were performed using Microsoft Office Excel® 2007 spreadsheet software. Data were stored in an Excel file for descriptive statistical evaluation. The minimum, maximum, and mean and standard deviation values were recorded for the descriptive analysis of various parameters.
Results
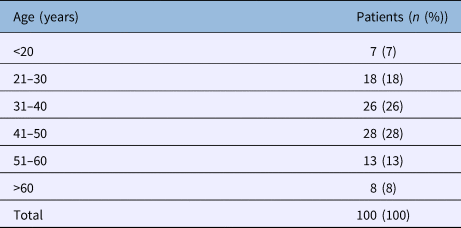
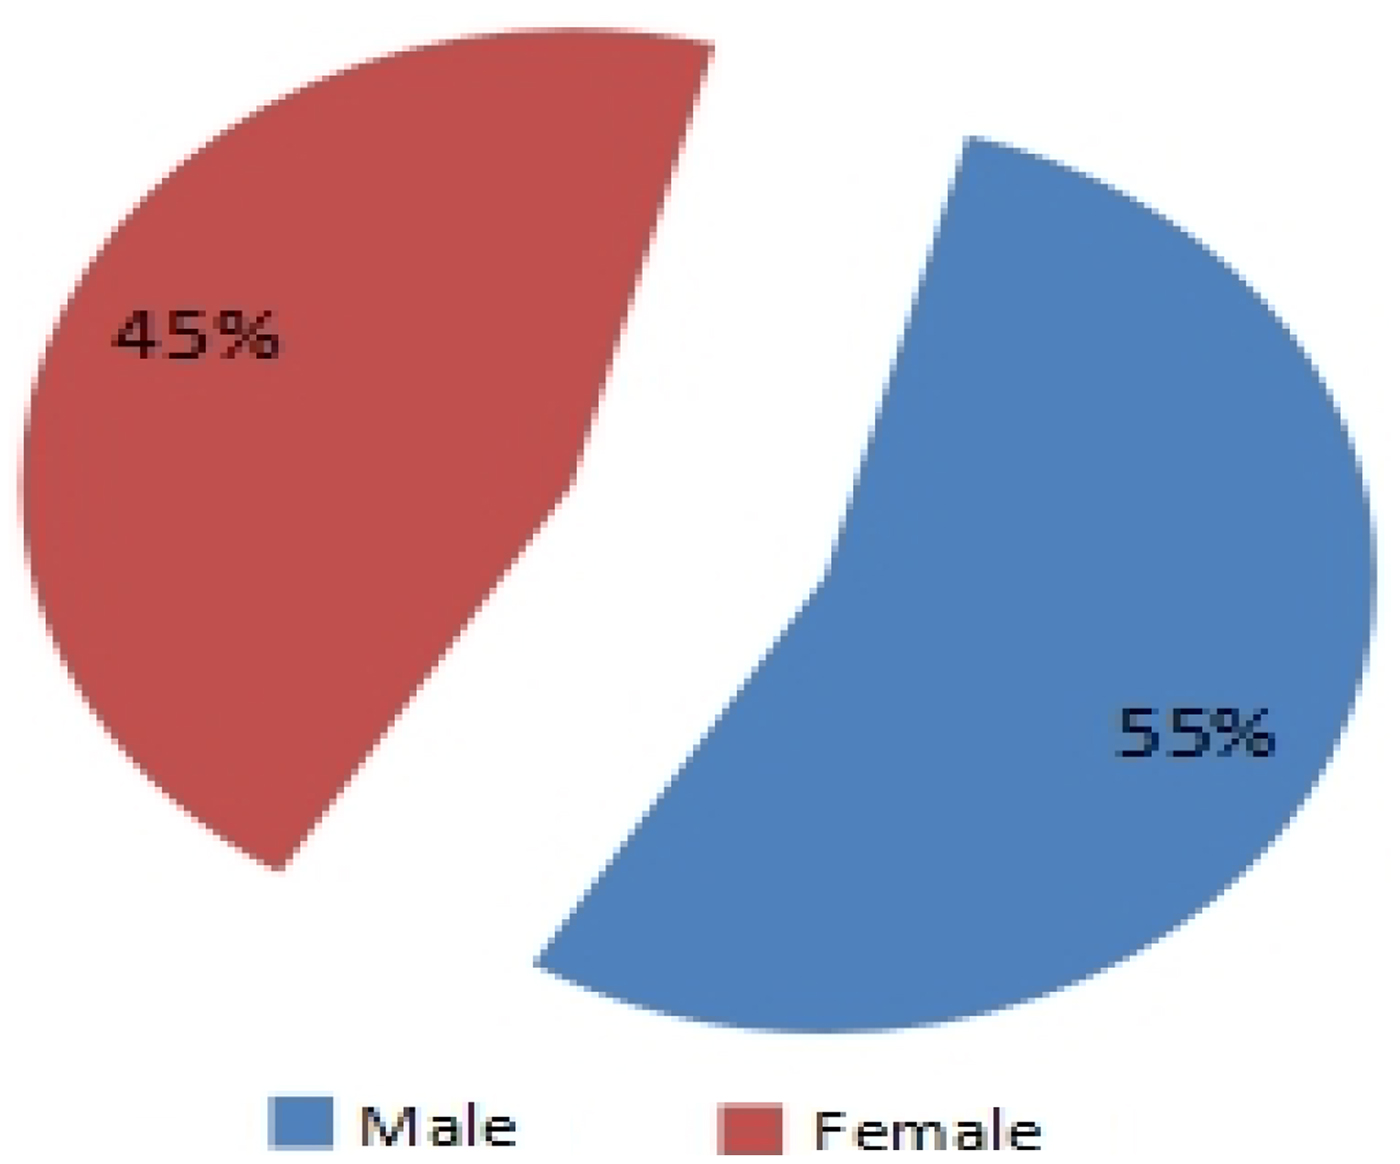
A total of 100 patients underwent posterior nasoseptal flap reconstruction for skull base defects as part of the endonasal skull base surgery. The mean age of the study subjects was 41.8 ± 13.8 years (Table 1), with a near-equal number of males and females (Figure 5).
Distribution of patients based on age

Mean age (± standard deviation) of patients was 41.8 ± 13.8 years.
Gender distribution of the patients.

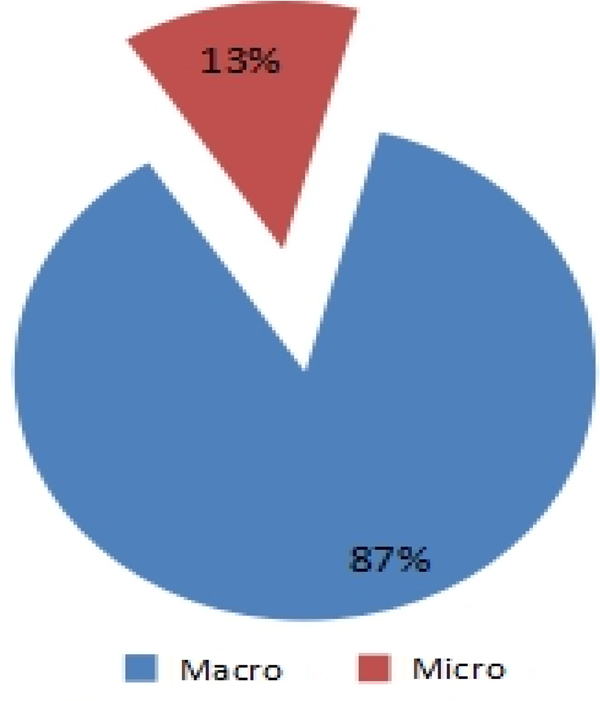
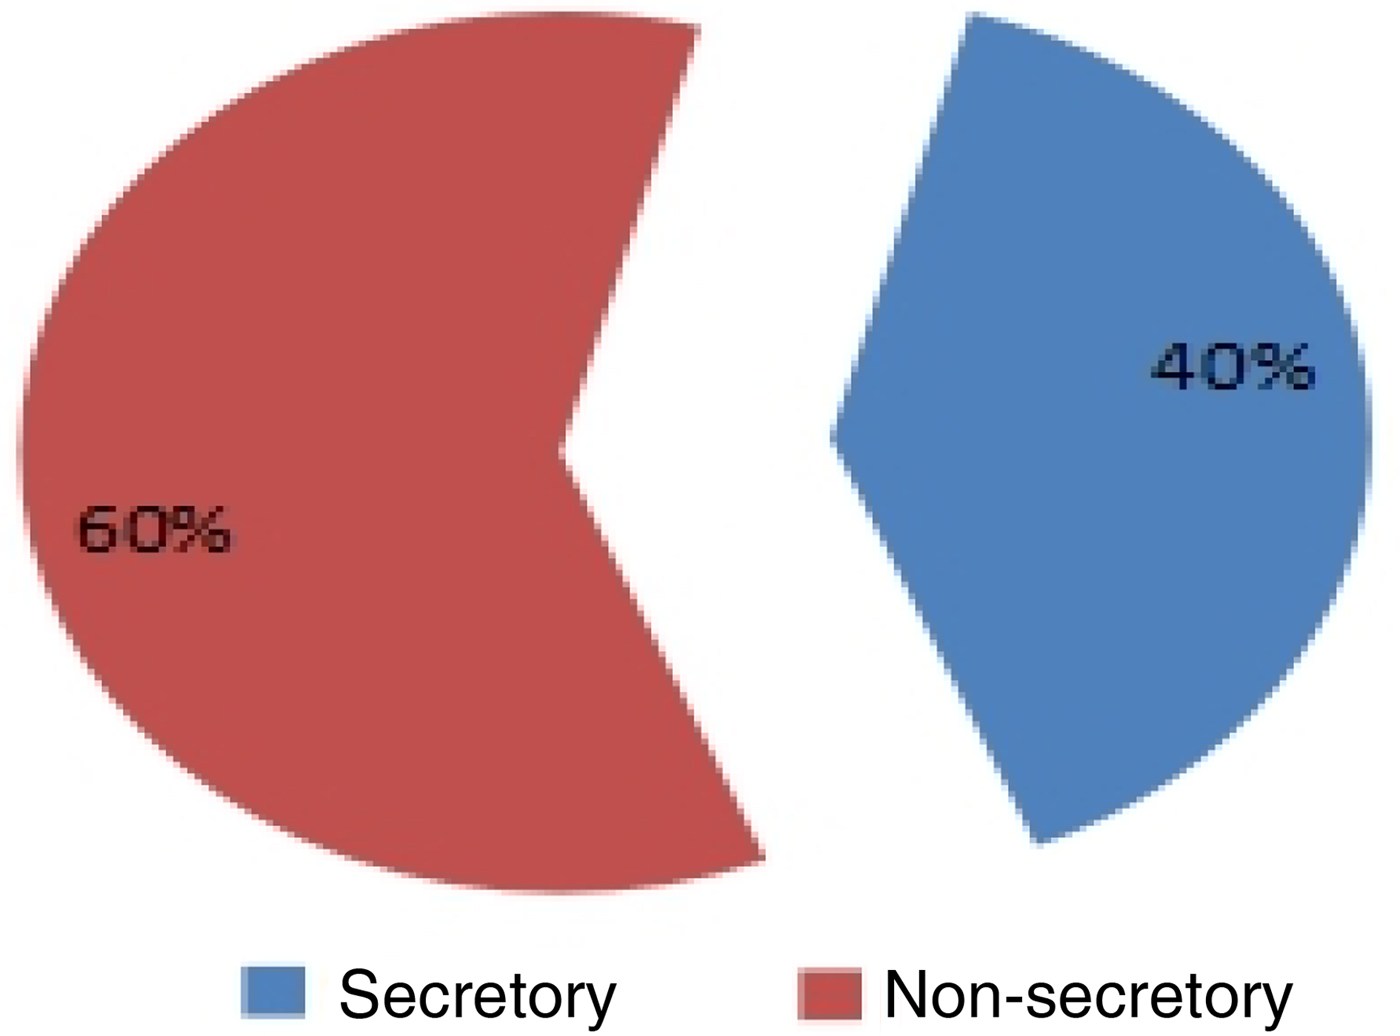
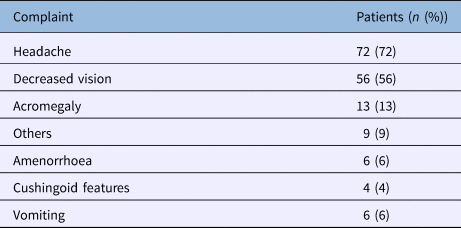
Eighty-seven patients had macro defects of the skull base, while 13 had micro defects (Figure 6). Non-secretary lesions were present in 60 patients, while secretary lesions were present in 40 patients (Figure 7). Headache was the most common presenting complaint (72 per cent), followed by decreased vision (56 per cent) and acromegaly (13 per cent) (Table 2).
Distribution of defect type (macro or micro defect) amongst the patients.

Distribution of lesion type (secretory vs non-secretory) amongst the patients.

Distribution of presenting complaints amongst patients

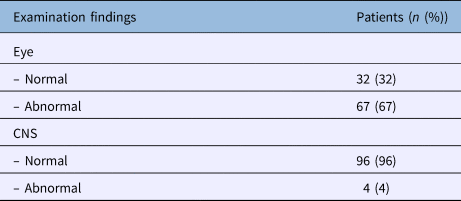
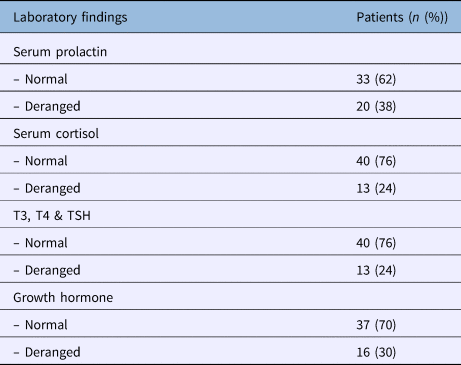
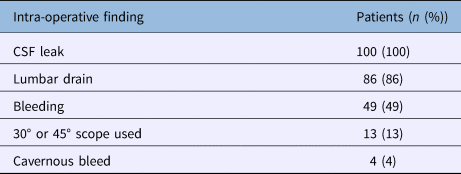
Tables 3–5 describe the examination findings, hormone levels and intra-operative findings.
Distribution of examination findings amongst patients

CNS = central nervous system
Distribution of various hormone levels amongst patients

T3 = triiodothyronine; T4 = thyroxine; TSH = thyroid-stimulating hormone
Distribution of intra-operative findings amongst patients

CSF = cerebrospinal fluid
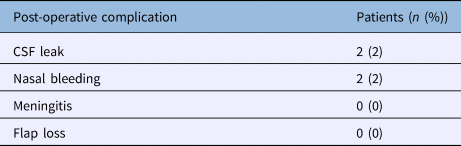
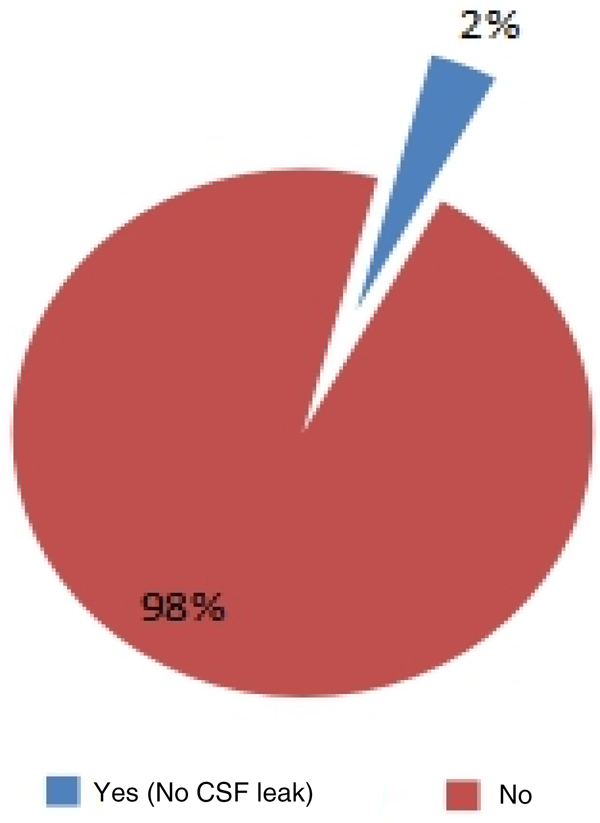
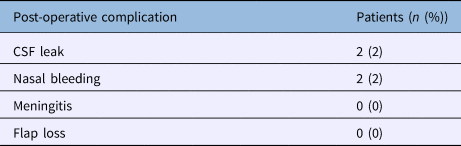
After posterior nasoseptal flap reconstruction, post-operative CSF leak was observed in two patients, giving a failure rate of 2 per cent (Table 6 and Figure 8). In the first patient, the leak resulted from straining and was observed on the 3rd post-operative day. The leak was repaired with the help of fascia lata graft. In the second patient, the leak was observed on the 2nd post-operative day. A lumbar drain was inserted and complete bed rest was advised; the leak subsequently stopped.
Distribution of post-operative complications amongst patients
CSF = cerebrospinal fluid
Distribution of post-operative cerebrospinal fluid (CSF) leaks (presence or absence) amongst the patients.

Discussion
The advantages of reconstructive techniques for the closure of surgically induced defects of the skull base enabled important progress in endonasal skull base surgery. The ultimate goals of reconstruction techniques in the skull base region include: the stable separation between the nose and the cranial cavity, the protection of neurovascular structures, the conservation or reconstruction of cosmoses, the preservation or reconstitution of function, and the avoidance of dead spaces. In this respect, the separation of the nasal and cranial cavities is of utmost importance, because it prevents post-operative CSF leaks, pneumocephalus and intracranial infections, and protects cranial nerves and large vessels from infection and trauma. The effects of post-operative radiotherapy also have to be considered.
Although a number of different techniques have been used successfully to endoscopically treat CSF leaks that occur after trauma, iatrogenic injury or in spontaneous rhinoliquorrhoea, these methods have proven inadequate for the reconstruction of large defects in extended endonasal skull base surgery.Reference Stammberger, Lund and Gleeson5–Reference Schick and Draf8
As a neuro-endoscope is utilised, especially after an endoscopic endonasal approach, the incidence of complications, such as CSF leak, infection and encephalocele formation, is high. Carrabba et al. reported that the incidence of CSF leak was 24 per cent after an endoscopic endonasal approach.Reference Carrabba, Dehdashti and Gentili9 Therefore, skull base defect reconstruction is of paramount importance to prevent a CSF leak after endoscopic endonasal surgery.Reference El-Banhawy, El-Dien, Zolfakar, Halaka and Ayad10,Reference El-Banhawy, Halaka, Altuwaijri, Ayad and El- Sharnoby11 In patients with large dural defects of the anterior and ventral skull base, there is a significant risk of a post-operative CSF leak after reconstruction.
Reconstruction with vascularised tissue is desirable, to facilitate rapid healing, especially in irradiated patients. The Hadad–Bassagasteguy flap, a neurovascular pedicled flap of nasal septum mucoperiosteum and mucoperichondrium based on the nasoseptal artery, was first developed at the National University of Rosario, Argentina, for the reconstruction of ventral skull base dural defects.Reference El-Banhawy, Halaka, Altuwaijri, Ayad and El- Sharnoby11
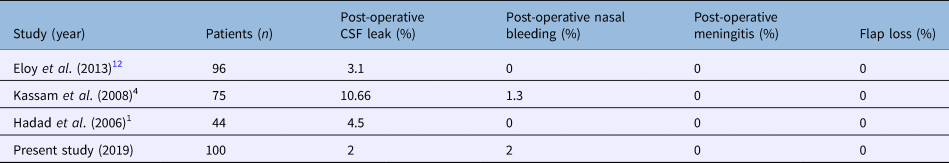
It was not until local vascularised flaps, in particular the Hadad–Bassagasteguy flap,Reference Locatelli, Rampa, Acchiardi, Bignami, De Bernardi and Castelnuovo6 were developed that the rate of post-operative CSF leaks, even after expanded skull base resections, could be reduced to below 5 per cent.Reference Eloy, Patel, Shula, Choudhary and Liu12 In the landmark study that introduced the Hadad–Bassagasteguy flap, Hadad et al. reported a post-operative leak rate of 4.5 per cent, without any partial or complete flap loss.Reference Hadad, Bassagasteguy, Carrau, Mataza, Kassam and Snyderman1 Recently, Eloy et al. reported a post-operative CSF leak rate of 3.1 per cent in a study of 96 skull base defects with high-flow CSF leaks that included 47 sellar defects (including 2 revision cases: 1 recurrence and 1 residual tumour) (Table 7).Reference Eloy, Patel, Shula, Choudhary and Liu12
Presenting outcome profile of posterior nasoseptal flap in previous studies

CSF = cerebrospinal fluid
A post-operative CSF leak rate of 2 per cent (2 out of 100) was observed in our study following the posterior nasoseptal flap repair of 100 sellar defects, with the use of an external lumbar drain in 86 per cent of cases. This is in line with the published results of post-operative CSF leak rates after posterior nasoseptal flap repair. The relatively higher rate (10.66 per cent) of post-operative CSF leaks observed by Kassam et al. was predominantly found in those patients who required intra-arachnoidal dissection, and the authors partly attributed it to their initial experience with the technique.Reference Kassam, Thomas, Carrau, Snyderman, Vescan and Prevedello4
All of the 100 patients in our study had sellar defects; 13 had macro sellar defects and 87 had micro sellar defects. A substantial, non-traumatised and well-perfused flap is essential for the efficacy of the repair technique. Early harvesting of the flap (before resection) is meant to ensure the quality of the flap and thereby the repair. Like most of the previously published studies, we also employed the pre-harvesting approach in all of our patients. Although the exact size of the expected skull base and dural defect is unknown, a good estimation can be obtained by carefully reviewing the pre-operative imaging scans. Early harvesting of the posterior nasoseptal flap allows a maximally sized flap that can be tucked into the nasopharynx or maxillary sinus, away from inadvertent trauma during the approach and tumour resection. A maximally sized posterior nasoseptal flap that has not been compromised by trauma, with a well-preserved vascular pedicle, may provide the most robust closure. This is even more important in cases where the approach used to access a lesion may involve sacrificing a portion of the posterior nasoseptal flap.Reference Eloy, Patel, Shula, Choudhary and Liu12
Disruption of the surgical barrier between a relatively septic nasal cavity and a highly aseptic arachnoid cavity is inherent in transnasal approaches to the anterior cranial fossa, as is the risk of iatrogenic meningitis. There will also be an inherent risk of olfactory dysfunctions in such surgery. In addition, as with all other surgical procedures, post-operative bleeding, especially in an area of compromised access, remains a possibility. Though rare, such complications are real with endoscopic nasal approaches to the skull base. The true incidence of these complications is unknown given the relatively smaller sample size of the relevant published studies to date. Like most of the reported studies, we observed very few cases of post-operative meningitis or nasal bleeding, even in those cases that had intra-operative bleeding from a cavernous injury (2 out of 100).
Kassam et al. reported post-operative bleeding in 1 out of 75 patients.Reference Kassam, Thomas, Carrau, Snyderman, Vescan and Prevedello4 Xuejian reported a single death due to post-operative meningitis out of 20 patients investigated.Reference Xuejian, Fan, Xiaobiao, Yong, Ye and Tao13 The latter study, however, did not specify the kind of mucosal vascular flap used in that particular patient. None of our patients had significant post-operative nasal synechiae, nasal obstruction or significant nasal crusting.
Bernal-Sprekelsen et al. conducted a retrospective study of 54 patients who underwent advanced skull base surgery (with large defects (greater than 20 mm)) and 62 patients with CSF leaks of a different origin (with small (2–10 mm) and mid-sized (11–20 mm) defects).Reference Bernal-Sprekelsen, Rioja, Enseñat, Enriquez, Viscovich and Agredo-Lemos14 Large defects were reconstructed with a nasoseptal pedicled flap positioned on fat and fascia lata. A lumbar drain was used. In those with small or mid-sized CSF leaks of another origin, intrathecal fluorescein was applied before the surgery to identify the defect; fascia lata in an underlay position was used for reconstruction, covered with mucoperiosteum of either the middle or inferior turbinate. The success rates after the first surgical reconstruction were 91 per cent for large skull base defects and 98 per cent for small or mid-sized skull base defects. After rescue surgery, the closure rate reached 100 per cent. The authors concluded that endoscopic surgery for closure of any type of skull base defect is the ‘gold standard’. Defect size does not seem to have a significant effect on success rate. Fascia lata and mucoperiosteum of the turbinate allow two-layer reconstruction of small and mid-sized defects. For larger skull base defects, a combination of fat, fascia lata and nasoseptal pedicle flaps enable successful reconstruction.Reference Bernal-Sprekelsen, Rioja, Enseñat, Enriquez, Viscovich and Agredo-Lemos14
Some recently published reports have also highlighted the olfactory dysfunction associated with Hadad–Bassagasteguy flap reconstruction. Rotenberg et al. reported a decrease in mean University Of Pennsylvania Smell Identification Test scores, from 37.2 (normosmic) pre-operatively to 30.8 (hyposmic) post-operatively.Reference Rotenberg, Saunders and Duggal15 These decreased scores persisted even after complete healing at six months post-surgery. The authors hypothesised that olfactory impairment resulted from use of the Hadad–Bassagasteguy flap. They recommend that the possibility of permanent olfactory changes be included when providing routine patient counselling and obtaining consent for this procedure. They also advised that Hadad–Bassagasteguy flaps be raised judiciously during trans-sphenoidal endoscopic procedures.Reference Rotenberg, Saunders and Duggal15 We regret not including such evaluation in our study.
• The efficacy of a posterior nasoseptal flap in endonasal reconstruction of anterior skull base defects was studied prospectively in 100 patients
• The post-operative cerebrospinal fluid (CSF) leak rate was 2 per cent
• Posterior nasoseptal flap use has decreased the incidence of post-operative CSF leaks after an endoscopic endonasal approach
• Posterior nasoseptal flap use for anterior skull base reconstruction in high-flow intra-operative CSF leak patients has prevented post-operative CSF leaks
• The technique can be applied to a wide patient range regarding age, defect size and diagnosis, making it a versatile choice
• Post-operative meningitis and post-procedure nasal bleeding are uncommon
The limitations of the current study include the lack of evaluation of pre- and post-operative olfactory status. In addition, the study did not have a control group. Lastly, the study focused on a single institution only. Consequently, a multi-institutional study, and prospective, randomised controlled, double-blinded studies, would be ideal to validate our results.
Conclusion
Endonasal reconstruction of anterior skull base defects using a posterior nasoseptal flap is associated with very high rates of post-operative CSF leak. Hence, endoscopic endonasal skull base reconstruction using a nasoseptal flap seems to be useful and reliable for ventral skull base defects, following an endoscopic endonasal approach, as compared with our previous single-layer reconstruction using free fat grafts or fascia lata.
Competing interests
None declared