Introduction
Right ventricular outflow tract infective endocarditis in children accounts for only 5–10% of infective endocarditis in children with CHDs. Reference Shmueli, Thomas, Flint, Setia, Janjic and Siegel1 Right ventricular outflow tract infective endocarditis occurs mainly in patients with an exogenous surgical conduit Reference Patel, Iserin, Bonnet and Boudjemline2–Reference Lin, Hsieh, Chen, Huang and Cheng6{Knirsch, 2011 #383}. Clinical manifestations of infective endocarditis include fever, fatigue, dyspnoea, cough, chest pain, and congestive heart failure. Reference Yuan7 The diagnosis is formulated from clinical, microbiological, and echocardiographic findings, using the recently (2023) revised Duke criteria. Reference Li, Sexton and Mick8–Reference Fowler, Durack and Selton-Suty10 Right ventricular outflow tract infective endocarditis might be difficult to diagnose since downstream vascular phenomena and pulmonary emboli, representing minor Duke criteria, may be clinically occult due to filtration by the pulmonary circulation and are less relevant for diagnosing right-sided endocarditis. Reference McElhinney11 In addition, a predisposing factor is present in all patients with repaired CHD and does not provide, therefore, further differentiation for any febrile episode. Reference McElhinney11 Moreover, in right ventricular outflow tract conduit, there is difficulty in visualisation of vegetations within the valved conduit by transthoracic as well as by transesophageal echocardiography. Reference Cheung, Vejlstrup and Ihlemann5 Positron emission tomography and computed tomography (PET-CT) is especially useful in prosthetic valve endocarditis; however, it is expensive and cumbersome, involving radiation exposure and sedation in children, and therefore, its use in this population is limited. Reference Mahmood, Kendi and Ajmal12
We examined the added diagnostic value of an increase in right ventricular outflow tract pressure gradient as assessed by Doppler-echocardiography on establishing the diagnosis of suspected infective endocarditis in children who underwent surgical right ventricular outflow tract reconstruction.
Methods
This cohort study included patients admitted between 2003 and 2020 to a tertiary, university-affiliated, children’s medical centre. Inclusion criteria were: age under 21 years old, presence of an exogenous conduit in the right ventricular outflow tract, and a diagnosis of infective endocarditis based on the modified Duke criteria, subdivided into possible and definite diagnoses. Reference Li, Sexton and Mick8–Reference Fowler, Durack and Selton-Suty10 During the study period, updates were made to the Duke criteria. We analysed our data using the 2023 revised Duke criteria. Reference Fowler, Durack and Selton-Suty10
Patients with infective endocarditis following right ventricular outflow tract exogenous surgical conduit insertion meeting these inclusion criteria were included.
The control group included patients with a conduit and a febrile illness due to another diagnosis. Reference Fowler, Durack and Selton-Suty10 Of note, in this study, we chose to document the number of infective endocarditis or non-infective endocarditis febrile episodes, rather than only the number of patients affected, because each episode represents a distinct clinical event.
Patients following transcatheter pulmonary valve insertion (e.g. Melody valve) were excluded, as this study focuses on surgically inserted exogenous conduits. Reviewing the literature, we noticed that Melody valve raises the risk for infective endocarditis more than external conduit, and we were concerned that this might cause a bias in the results. Reference Abdelghani, Nassif and Blom13
The study group included one patient with a pulmonary artery stent, as it represents foreign material in the right ventricular outflow tract, which may similarly serve as a nidus for infection, and therefore shares the same clinical relevance regarding susceptibility to endocarditis in the presence of bacteraemia.
Clinical, laboratory, microbiology, and echocardiographic findings, including right ventricular outflow tract calculated pressure gradient, were retrieved from the patients’ files. The study was approved by the institutional review board.
Microbiology
Each isolate was identified using the VITEK 2 system (bioMérieux, https://www.biomerieux.com) or MALDI Biotyper System (Bruker, https://www.bruker.com), in accordance with the manufacturers’ instructions for bacteria identification. Antimicrobial-susceptibility profiles of the isolates were determined by the disk diffusion method (Oxoid, https://www.oxoid.com), Etest (bioMérieux), or VITEK 2 as needed and interpreted based on the Clinical and Laboratory Standards Institute criteria. Reference Wayne14 Serological tests for Coxiella burnetii were conducted at the Israel National Institute for Biological Research, the national central laboratory for diagnosis of Coxiella burnetii, using indirect immunofluorescent assays. Reference Keysary, Amram and Keren15
Echocardiography
The echocardiography scans were reviewed by a senior paediatric cardiologist, and the peak right ventricular outflow tract gradient was obtained from the image with the best angle of insonation, usually from the subcostal view. The maximal pressure gradient across the right ventricular outflow tract was recorded from a routine study in the 3–6 months preceding infective endocarditis, during the acute illness, and following resolution of symptoms. The pressure gradient across the right ventricular outflow tract was calculated from the maximal Doppler velocity measured using the simplified Bernoulli equation. An elevation in the gradient was defined as a ≥ 15 mmHg increase in the baseline right ventricular outflow tract pressure gradient compared to the previous examination. Reference Abdelghani, Nassif and Blom13
Statistical analysis
Continuous variables were analysed by their median and Interquartile range (IQR). Differences in continuous variables between groups were compared using paired t-tests or Mann-Whitney U tests, and Pearson chi-square tests for categorical variables. p values 0.05 > were considered significant. Statistical analyses were performed with IBM SPSS Statistics. Version 27 and R statistical software.
Results
Patient population
The study included 26 febrile episodes with a surgically inserted valved conduit in the right ventricular outflow tract evaluated during an acute febrile illness: 11 diagnosed as with infective endocarditis and a control group of 15 febrile non-infective endocarditis episodes. In the control group, two patients each had two separate episodes of fever at different times. Each febrile episode was included separately. In both instances, the episodes were evaluated and determined not to be IE, based on Duke’s criteria.
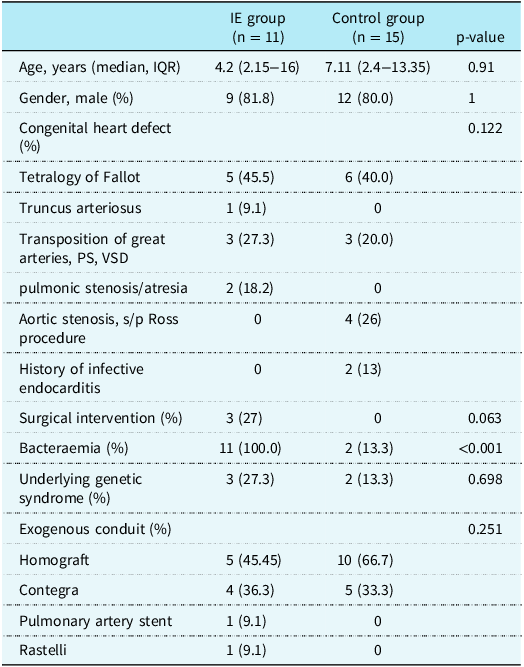
Data regarding the patients’ demographic characteristics, type of CHDs, and type of conduit surgically inserted are detailed in Table 1.
Patient’s characteristics

a PS, pulmonic stenosis; VSD, ventricular-septal defect. ** Mann-Whitney U test; Fisher’s exact test.
Patients in the control group were diagnosed as follows: two pericarditis, two bacteraemia, one pneumonia, one cellulitis, one periapical abscess, and eight viral illnesses. Of note, one patient in the infective endocarditis group had a pulmonary artery stent. No differences were found between the groups regarding mean age at the febrile illness, gender, and the type of surgical valved conduit (Table 1).
Three patients in the control group with five episodes of non-infective endocarditis febrile illness had previous episodes of IE: one patient had a viral illness (resolved without antibiotics) and a separate episode of pneumonia, both occurring 1–2 years after their infective endocarditis; another patient had pneumonia one year after their previous infective endocarditis; a third patient experienced a viral illness two months post-infective endocarditis, which resolved without antibiotic treatment; and one episode, occurring two years after infective endocarditis, was diagnosed as acute pericarditis, resolving following colchicine and ibuprofen treatment, confirming that none of the patients had active infective endocarditis at the time of their inclusion in the control group.
The infective endocarditis group included one patient with a pulmonary artery stent considered as an exogenous conduit, as it represents foreign material in the right ventricular outflow tract, which may similarly serve as a nidus for infection, and therefore shares the same clinical relevance regarding susceptibility to endocarditis in the presence of bacteraemia.
Laboratory
There was no statistically significant difference between the groups in the following parameters: leukocytes count (infective endocarditis group 10.20 × 10⁹/L, IQR 8.28–14.04; vs. control group, 8.88 × 10⁹/L, IQR 7.32–13.19, p = 0.646), creatinine levels (infective endocarditis group 0.44 mg/dL, IQR 0.28–0.58; vs. control group 0.36 mg/dL, IQR 0.30–0.58, p = 0.830).
Haemoglobin levels differed significantly between the groups; in the infective endocarditis group, haemoglobin levels were 9.90 gr/dL (IQR 9.50–10.50), compared with the control group 11.40 gr/dL (IQR 10.75–12.40), p = 0.015. Plateles levels also differed significantly (p = 0.009) with platelet levels of 158 × 109/L (IQR 102–273) in the infective endocarditis group, and 327 × 109/L (IQR 253–364) in the control.
C-reactive protein levels trended higher in the infective endocarditis group (10 mg/dL IQR 2.64–13.30 vs. 2.59 mg/dL, IQR 0.86–6.24, respectively, p = 0.061); however, its lack of specificity and the overlap in interquartile ranges limits its utility as a marker to differentiate infective endocarditis from other febrile illnesses.
Microbiology
Various bacteria were identified in the blood of all patients with infective endocarditis, compared with only 13% (2/15) of patients in the control group.
In patients with infective endocarditis, the identified bacteria were as follows: Kingella kingae (3 patients), Staphylococcus aureus (2 patients), Coagulase-Negative Staphylococci (2 patients), Staphylococcus lugdunensis (2 patients), and Streptococcus mutans, Aggregatibacter aphrophilus, Streptococcus mitis, Coxiella Brunetti in one patient each. Two patients were positive for two bacteria (one for both Kingella Kingae and Coxiella Brunetti, and another for both Staphylococcus aureus and Coagulase-Negative Staphylococci). In the control group, only two patients had positive blood cultures, and the identified bacteria were Streptococcus pneumoniae and Kingella kingae.
Treatment
All patients in the infective endocarditis group were treated with antibiotics. Three patients in the infective endocarditis group underwent surgical intervention following their episode of infective endocarditis. One patient required ventricular outflow tract replacement one month after diagnosis. Another underwent pacemaker lead extraction due to failure of medical treatment, four months after infective endocarditis diagnosis. The third patient underwent surgical lobectomy of the lung two months after the diagnosis of infective endocarditis, and a redo homograft procedure was performed six years after the infective endocarditis episode, for reasons unrelated to active infection.
As of 2025, one patient in the infective endocarditis group died from an arrhythmia during gastrostomy insertion, 10 months following the infective endocarditis diagnosis. In the control group, five patients were treated with antibiotics with no surgical intervention.
None of the control group patients (including patients with bacteraemia) fulfilled the criteria for endocarditis or were managed/treated as such.
Echocardiographic findings
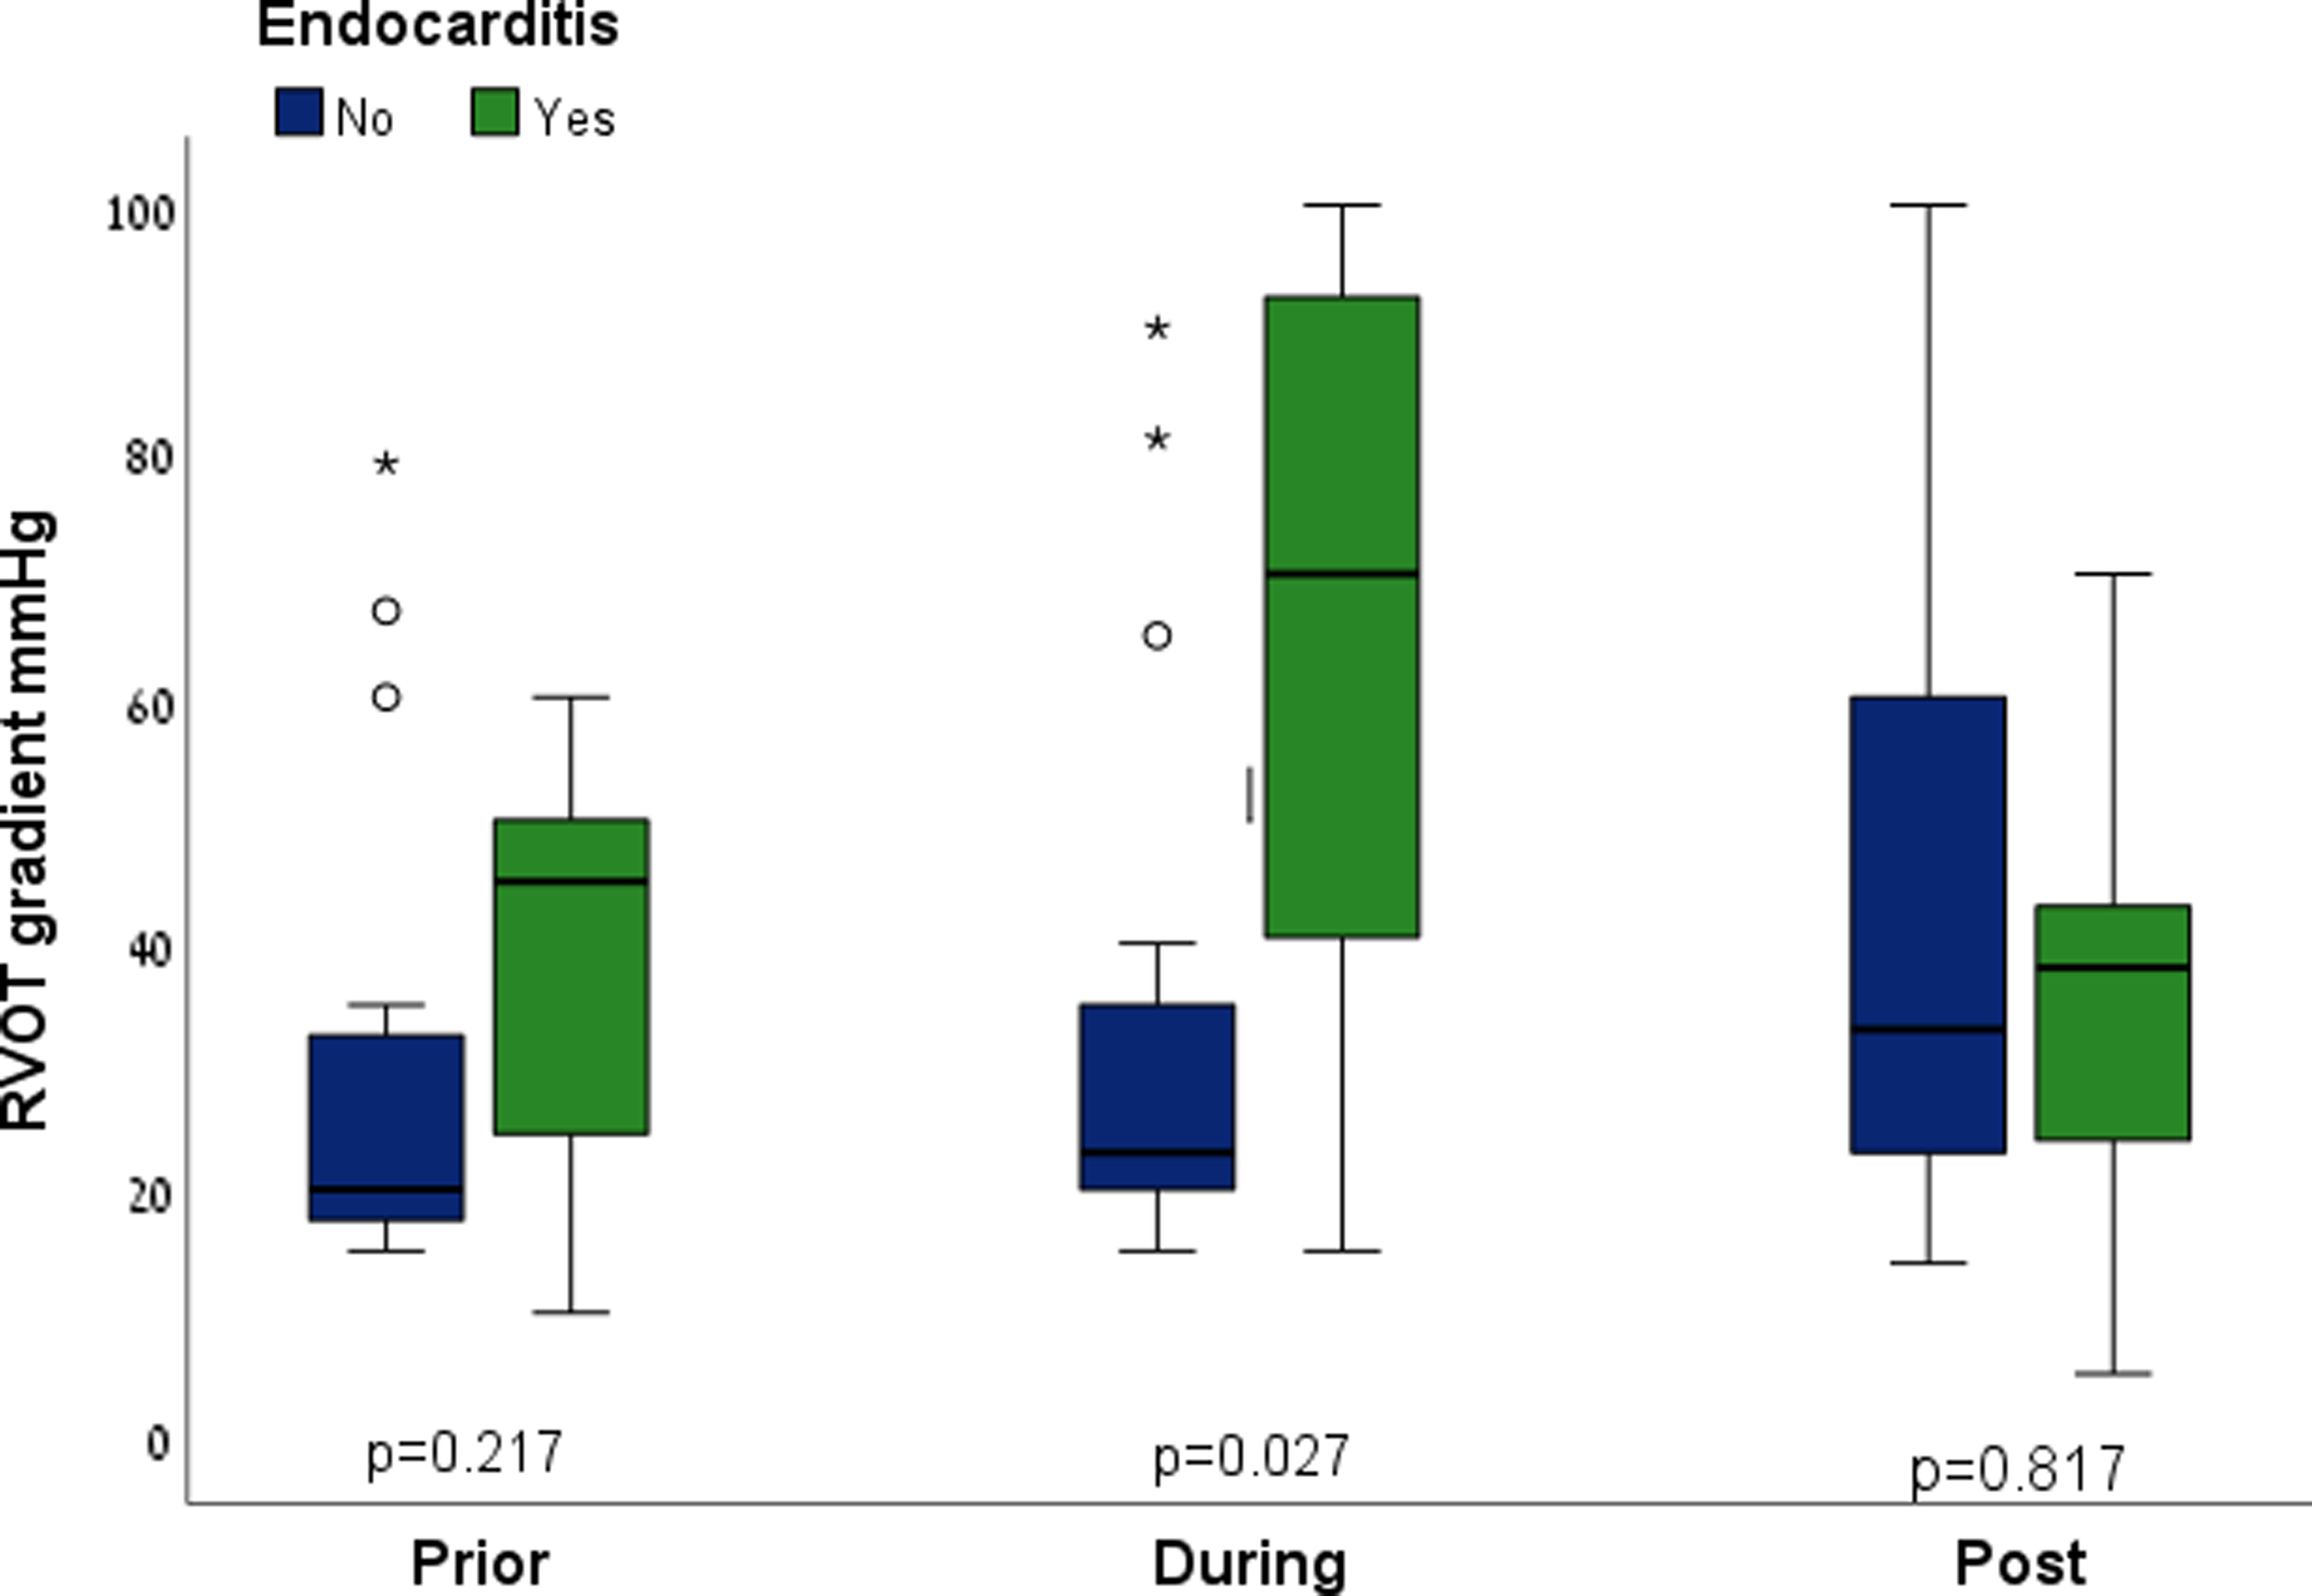
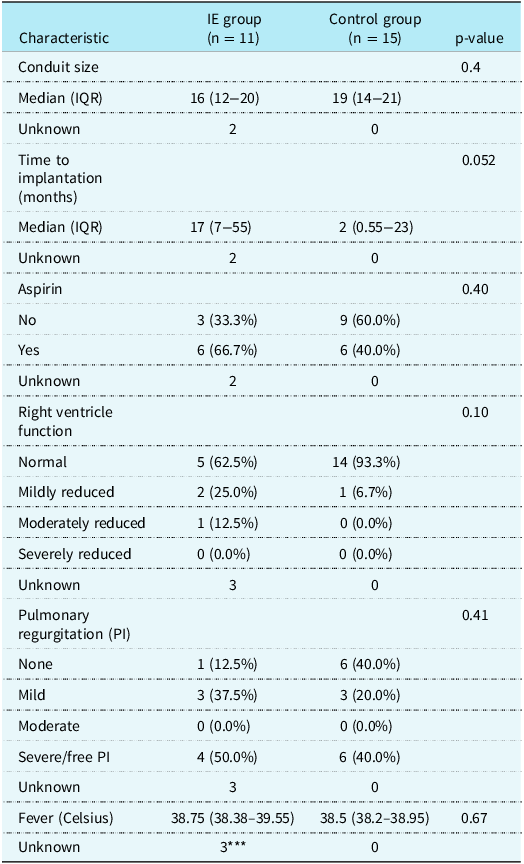
Patients’ right ventricular function and echocardiography characteristics are depicted in Table 2. The right ventricular outflow tract gradient on admission was moderately-severe elevated in 7/11 (64%) of the patients with infective endocarditis, compared with mild elevation in the control group (1/15). The peak right ventricular outflow tract gradient during the 6 months before diagnosis was 45 (IQR 24.75–50) mmHg in patients with infective endocarditis, and 20 (IQR 18.25–32.5) mmHg in the control group (p = 0.524). At the time of diagnosis, the peak right ventricular outflow tract gradient was 70 (IQR 42.75–92.2 = 5) mmHg in the infective endocarditis group compared with 23 (IQR 20–35) mmHg in the control group (p = 0.035) (Figure 1).
Peak right ventricular outflow tract pressure gradient in patients in the infective endocarditis group (n = 13), compared with patients in the control group (n = 15), in median and IQR. Prior and during, infective endocarditis group n = 11, control group n = 15; post, infective endocarditis group n = 8 (3 surgically treated patients are excluded), control group n = 15.

Patients’ clinical and echocardiography characteristics

* n (%) Median (IQR). ** Mann Whitney U test, Fisher’s exact test. *** Right ventricular function was marked as ‘unknown in three IE patients due to incomplete or non-quantifiable documentation in the echocardiography reports.
There was no difference in the peak right ventricular outflow tract pressure gradient between study groups 3–6 months following the febrile illness; peak 38 (IQR 22–46) mmHg in patients with infective endocarditis, versus 33 (IQR 23–60) mmHg in patients in the control group (p = 0.342).
When examining the sub-group of patients with infective endocarditis requiring surgical intervention (n = 3), the peak right ventricular outflow tract pressure gradient during 6 months prior to diagnosis was 50 (IQR 47.5–55) mmHg, versus 30 (IQR 23–50) mmHg in the conservatively treated patients in the infective endocarditis group (no surgical intervention, n = 8). At the time of diagnosis, the peak right ventricular outflow tract gradient was 100 (IQR 92.5–100) mmHg in patients requiring surgical intervention, compared with 57.5 (32–70.35) mmHg in the conservatively treated patients in the infective endocarditis group. The above sub-groups were too small for further statistical analysis.
Time to diagnosis
In the infective endocarditis group upon admission, based on Duke’s criteria, Reference Fowler, Durack and Selton-Suty10 18% (2/11) patients had a definite diagnosis of infective endocarditis, 45% (5/11) had a possible diagnosis, and 36% (4/11) did not meet the criteria for infective endocarditis. Reference Li, Sexton and Mick8,Reference Prendergast9 If right ventricular outflow tract pressure gradient were to be considered as a major criterion (alongside the existing echocardiography criteria), upon admission, 45% (5/11) patients had a definite diagnosis of infective endocarditis and 45% (5/11) of the patients had a possible diagnosis of infective endocarditis, one patient did not have a diagnosis. A week after admission, 64% (7/11) of patients in the infective endocarditis group had a definite diagnosis, and 27% (4/11) had a possible diagnosis, following a positive blood culture result and serology tests. When considering right ventricular outflow tract pressure gradient as a major criterion, 10/11 patients had a definite diagnosis of infective endocarditis and one patient had a possible diagnosis.
A total of three patients required surgery; of those, one had a possible infective endocarditis diagnosis on admission (patient #10), and two did not meet Duke criteria (patients #2, #9). A week following admission, two patients had a definite diagnosis (patients #2, #10), and one patient had a possible diagnosis (patient #9). When adding right ventricular outflow tract pressure gradient as a Duke’s criteria, upon admission, patients #2 and #9 had a possible diagnosis, and patient #10 had a definite diagnosis. A week following admission, all had a definite diagnosis for infective endocarditis.
Likelihood ratio analysis
The likelihood ratio analysis for a definite diagnosis based on the Duke criteria alone shows a sensitivity of 18% and a specificity of 93.33%, resulting in a positive likelihood ratio of 2.70. When the peak right ventricular outflow tract pressure gradient is included as a major criterion, the sensitivity increases to 45% while maintaining the same specificity of 93.33%. This adjustment results in a higher positive likelihood ratio of 6.7, indicating a significant improvement in the diagnostic power for identifying infective endocarditis.
Discussion
In 2023, the Duke-International Society for Cardiovascular Infectious Diseases revised the criteria for infective endocarditis and published an update to the modified Duke criteria. Reference Fowler, Durack and Selton-Suty10 Their main conclusions were that the original structure for differentiating definite, possible, and rejected infective endocarditis based on major and minor clinical criteria should remain unchanged. One new domain, surgical, was added to the two previous domains (microbiologic and imaging), comprising the clinical criteria. Reference Fowler, Durack and Selton-Suty10
This supports the notion that criteria ought to serve as a living document that is continually refreshed based on evidence-based research. Building upon this concept, in this study, we evaluated the added value of assessing peak right ventricular outflow tract pressure gradient to diagnose infective endocarditis in patients with right ventricular outflow tract valved conduit. We found that taking into consideration the increased peak right ventricular outflow tract pressure gradient during a febrile episode may establish the diagnosis earlier, and probably at admission.
In our paediatric cohort, 64% of the patients with infective endocarditis showed an elevation in their right ventricular outflow tract pressure gradient, ranging from 19 to 76 mmHg (Figure 1). This observation was unrelated to patient age, gender, or to a particular bacterium. A systematic review, Abdelghani et al., suggested that right ventricular outflow tract pressure gradient can assist in the diagnosis of right-sided infective endocarditis in adult patients with Melody valve implantation. Reference Abdelghani, Nassif and Blom13 They defined a new or progressive right ventricular outflow tract obstruction as a ≥ 15 mmHg increase in right ventricular outflow tract pressure gradient on the first echo-Doppler evaluation after infective endocarditis onset, compared with the latest study before infective endocarditis. Reference Abdelghani, Nassif and Blom13
A valved conduit is a predisposing factor that is present in patients with CHDs who underwent surgical right ventricular outflow tract reconstruction, and does not provide additional differentiation for any febrile episode. Reference McElhinney11 While endocarditis rates are lower in certain procedures (e.g in patent ductus arteriosus closure devices like ADOII and Piccolo), Reference Bruckheimer, Steiner and Barak-Corren16 the right ventricular outflow tract’s unique flow dynamics and surgical complexity may increase infection risk, supporting the need for adjunctive diagnostic markers such as right ventricular outflow tract gradient.
Positive blood cultures (a major Duke criteria) take 48 hours to 5 days to cultivate and analyse and are negative in 2 to 40% of cases of endocarditis. Reference Murdoch, Corey and Hoen17–Reference Chela, Vasudevan, Rojas-Moreno and Naqvi19 Although a bacterial aetiology was eventually detected in all our patients in the infective endocarditis group; however, adding an increase in right ventricular outflow tract pressure gradient as a criterion on admission led to an earlier diagnosis in all patients and was definite in 45% compared to 18% based on current Duke’s criteria. A total of 36% who had no confirmed diagnosis upon admission based on current Duke’s criteria were re-categorised with either possible or definite diagnosis, enabling earlier treatment initiation and closer monitoring. One patient had no confirmed diagnosis, even when considering it as a criterion.
It is of note that severe obstruction in the conduit can cause right ventricular dysfunction, and when this is severe, the pressure gradient may be underestimated due to the poor function. Since in our cohort the systolic function was normal in all of the patients, there was no bias in pressure gradient underestimation.
Most patients in our cohort in the infective endocarditis group responded to antibiotic treatment. Only 3/11 (27%) patients required surgical intervention, all of which could have been diagnosed earlier if right ventricular outflow tract pressure gradient was considered a major Duke’s criteria, alongside the existing echocardiography criteria. Liang et al. showed that although in most patients with infective endocarditis, antibiotic treatment is sufficient, in the subset of patients requiring surgical intervention, early surgery is associated with lower in-hospital and long-term mortality. Therefore, early diagnosis could hasten recovery and prevent mortality. Reference McElhinney, Benson, Eicken, Kreutzer, Padera and Zahn3,Reference Liang, Song, Liu, Yang, Tang and Li20 Change in the course of infective endocarditis prognosis depends on the rapid establishment of targeted therapy, which in turn is only possible when an early diagnosis is attained. Reference Nishiguchi, Nishino, Kitagawa and Tokuda21
Our study results are in line with previously reported studies suggesting that the right ventricular outflow tract pressure gradient may be considered as a major Duke criterion in patients with exogenous conduit. Reference Abdelghani, Nassif and Blom13,Reference Bos, De Wolf and Cools22 To the best of our knowledge, previous studies did not differentiate between surgical and percutaneous valves to the right outlet. In this study, we present 11 patients with infective endocarditis and surgically inserted grafts (Xenografts or Contegra).
Although this is one of the largest studies in the field, the number of cases is still a limitation. Nonetheless, it had sufficient power to demonstrate clinical findings that were statistically significant. In the control group, only 1 out of 15 patients (6.6%) exhibited an increased gradient of ≥ 15 mmHg with Fisher’s 95% CI of 0.17% to 31.95%, substantially lower than the proportion of 7 out of 11 (63.6%) among endocarditis patients.
Anaemia may affect pressure gradient, as haemoglobin levels are inversely related to stroke volume, and cardiac output increases when the haemoglobin levels are below 7 gr/dL. In our study, patients with infective endocarditis had lower haemoglobin concentration compared with the control. However, in both groups, median haemoglobin levels were above 9 gr/dL (infective endocarditis group 9.9 gr/dL (IQR 9.5– 10.5), control group 11.4 gr/dL (IQR 10.7N12.4). The difference between the groups might indicate disease severity, as all patients in the infective endocarditis group had confirmed bacterial infection compared with only two patients in the control. Reference Barrett-Connor23 Fever and somatic growth are factors that can also influence the right ventricular outflow tract pressure gradient, yet there were no differences between the groups in the patients’ age, and all patients had a fever during the time of evaluation.
Of note, the infective endocarditis group had higher baseline right ventricular outflow tract gradient compared with the control. This could be caused by high turbulence lesions that are a risk factor for infective endocarditis. Reference Steckelberg and Wilson24
Furthermore, the heterogeneous nature of the control group poses challenges in direct comparison. However, the inclusion of various non-infective endocarditis conditions reflects the common clinical scenario where patients may present with febrile episodes of varying aetiologies.
There was a higher incidence of males in our study, possibly due to evidence indicating that males are significantly more likely to be born with severe CHDs, while females are more commonly born with milder CHD subtypes. Reference Pugnaloni, Felici, Corno, Marino, Versacci and Putotto25
In addition, we did not include, in the study, patients with reduced right systolic function. Incorporating the right ventricular outflow tract pressure gradient as a major Duke criterion, alongside the existing echocardiography criteria, could enhance the sensitivity of infective endocarditis diagnosis; however, it might also increase its false positive rate. Nevertheless, we showed that in our control group, only one patient had an elevated right ventricular outflow tract pressure gradient during a non-infective endocarditis febrile episode. Furthermore, even after considering elevated right ventricular outflow tract as a major criterion in this patient, he did not meet the criteria for definite infective endocarditis.
Although additional diagnostic methods like PET-CT and intracardiac echocardiography (additional Duke criteria) can be beneficial for adults, their use in children is limited due to invasiveness, radiation exposure, and the risks associated with sedation. In contrast, echocardiography is non-invasive, painless, and does not require sedation.
To the best of our knowledge, this is the first study to examine the right ventricular outflow tract pressure gradient as a criterion for infective endocarditis in the paediatric patients with surgical right ventricular outflow tract. Infectious endocarditis entails high morbidity and mortality. Adding a criterion that enables the physician to establish an earlier diagnosis, and consequently prompts treatment, is essential. A larger-scale study is necessary for further validation.
Data availability statement
Data available within the article or by request of the authors.
Acknowledgements
None.
Financial support
None.
Competing interests
None.