Significant outcomes
∙ Regardless of gender, unipolar or bipolar depression, lower levels of total and LDL cholesterol, and total lipids were shown in depressed patients with suicidal thoughts, tendencies and attempts, compared with those without such behaviours.
Limitations
∙ Cross-sectional character of the study.
∙ Some studies did not confirm an association between cholesterol level and suicidal behaviour.
Introduction
The evidence for a possible association between low levels of lipids (particularly cholesterol) and increased suicidality dates back 3 decades when the issue of lowering cholesterol levels became a popular topic in cardiology. Results from projects such as the Lipid Research Clinics and Helsinki Heart Study suggested that a reduction in cholesterol level from a low-fat diet and cholesterol-lowering drugs did not decrease total mortality. In an experimental (interventional) group, a significant increase in mortality was observed owing to suicide and violent behaviour, compared with the control group.
The first meta-analysis of this issue, covering six randomised studies on primary prevention of ischaemic heart disease, included nearly 25 000 men. Muldoon et al. (Reference Muldoon, Manuck and Matthews1) showed that, in the group of subjects with a 10% reduction in total cholesterol, there were 28 fewer deaths because of ischaemic heart disease, and 29 more deaths because of suicide, violence and accidents. Overall, the reduction was associated with a twofold increase in death risk owing to suicide, violence and accidents.
Of the numerous subsequent meta-analyses, dealing with cholesterol and suicidal behaviour Lester (Reference Lester2) seems to be most informative. For predicting future suicidal behaviour, a significant tendency was observed for those with low cholesterol levels to have a higher suicide rate in follow-up. For the past suicide attempts, there was a correlation between low cholesterol level and suicidal thoughts and violent methods of attempted suicide. However, in cholesterol-lowering studies, the association with higher suicidality did not reach statistical significance.
A meta-analysis by Zhang (Reference ZHANG3) including various study designs suggests that cholesterol-lowering interventions may result in a reduction of mortality from all causes. However, in both cross-sectional and case–control studies, there was an association between low cholesterol level and suicidal ideation and attempts in depressed patients. In long-term (>10 years) cohort studies, an association between low cholesterol and suicidality was observed only during the early years of follow-up.
In a series of experimental and review papers, De Berardis et al. (Reference de Berardis, Serroni and Campanella4–Reference de Berardis, Marni and Piersanti6) attempted to find a balance of research on this issue conducted until 2011. They found a majority of studies suggesting a relationship between low serum cholesterol and suicide; however, some papers failed to show such a relationship.
Clinical studies on depressed patients published since 2013 have brought conflicting results. Papadopoulou et al. (Reference Papadopolou, Markianos, Christodoulou and Lykouras7) compared total cholesterol levels in 51 affective patients on admission with a psychiatric clinic after a suicide attempt and with total cholesterol levels when patients returned to their normal activities. Although total cholesterol increased in follow-up, its levels were significantly lower in suicide attempters than in matched controls on both assessments. No differences were observed between violent and non-violent attempters; however, total cholesterol levels correlated negatively with aggression score. Korean authors did not find differences in total cholesterol level between patients hospitalised for mood disorders, who subsequently died of suicide and those who did not (Reference Park, Yi, Lim and Hong8). However, in their subsequent study, they found a negative correlation between suicidal ideation and triglyceride levels (Reference Park, Lee and Lee9). Recently, Baek et al. (Reference Baek, Kang and Fava10) showed that, among patients with major depressive disorder, recent suicide attempters had significantly lower triglyceride and higher HDL cholesterol levels compared with the remaining patients.
Aims of the study
The aim of the present study was to investigate whether lipid levels [total cholesterol, low density lipoprotein (LDL) cholesterol, low density lipoprotein (HDL) cholesterol, triglycerides and total lipids] can make state-dependent markers of suicidal behaviour in Polish patients with mood disorder recently admitted to a psychiatric hospital because of an acute depressive episode.
Subjects and methods
Patients
A total of 223 patients, consecutively admitted to the inpatient clinic, of the Department of Adult Psychiatry, Poznan University of Medical Sciences, because of an acute depressive episode, from September 2005 to June 2006, were recruited into the study. There were 73 male patients (mean age 45±15 years, duration of illness 8±9 years), and 150 female patients (mean age 49±13 years, duration of illness 8±8 years). Exclusion criteria for the study included severe somatic illness, drug and/or alcohol abuse/dependence, mental retardation, comorbid eating disorder, using low-fat diet or lipid-lowering drugs, or hormonal therapy.
In 171 patients (53 male, 118 female), major unipolar depression was diagnosed, and 52 patients were diagnosed with bipolar depression. Consensus diagnosis by at least two psychiatrists was made for each patient, according to DSM-IV criteria (Reference First, Spitzer, Gibbon and Williams11).
Methods
Clinical assessment
A semi-structured questionnaire was used for demographic data, duration of illness, psychiatric and suicidal family history, as well as psychiatric and somatic treatment during the 3 months before admission. The main purpose of the interview was to establish an occurrence of any suicidal thoughts, suicidal tendencies and/or suicidal attempts during the 3 months before admission. The interview with all patients studied was conducted by the same psychiatrist (B.A.), using the same set of questions, within the 1st week of admission.
Laboratory measures
Fasting blood was drawn at 08:00 a.m. within 24–72 h of admission. Laboratory measures included serum concentration of following lipids: total cholesterol, LDL cholesterol, HDL cholesterol, triglycerides and total lipids.
The study was approved by the Bioethics Committee, Poznan University of Medical Sciences, and all patients gave their informed consent after the nature of the procedures had been fully explained to them.
Statistical methods
Calculations were performed using the Statistica version 7.1 statistical package. Distribution of the results was tested using the Shapiro–Wilk test. As the results were normally distributed, parametric statistical tests were used. Comparisons of two groups (with and without suicidal behaviour) were made by non-paired Student’s t-test. Statistical significance was set at p<0.05.
Results
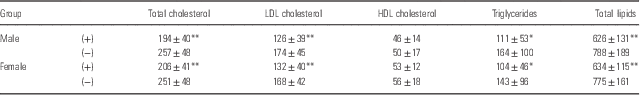
Suicidal thoughts were reported by 51% of the depressed men and by 39% of the depressed women. Concentrations of total cholesterol, LDL cholesterol, triglycerides and total lipids were significantly lower in depressed patients with suicidal thoughts compared with the remaining patients. This was demonstrated both in male and female patients. No relationship with HDL cholesterol was found (Table 1).
Lipid levels in depressive patients with (+) and without (−) suicidal thoughts in recent 3 months
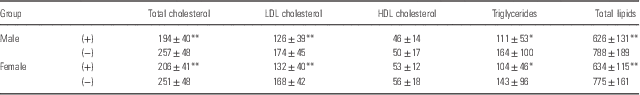
HDL, high density lipoprotein; LDL, low density lipoprotein.
Values are expressed as mg/dl (mean±SD).
Concentrations significantly lower in patients with suicidal thoughts.
**p<0.001, *p<0.01.
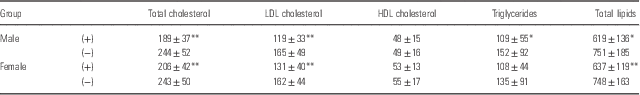
Suicidal tendencies were reported by 34% of the depressed men and by 25% of the depressed women. Concentrations of total cholesterol, LDL cholesterol and total lipids were significantly lower in depressed patients with suicidal thoughts compared with the remaining patients. In addition, in male patients with suicidal plans, significantly lower triglyceride levels were found. No relationship with HDL cholesterol was observed (Table 2).
Lipid levels in depressive patients with (+) and without (−) suicidal tendencies in recent 3 months
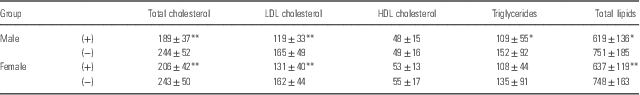
HDL, high density lipoprotein; LDL, low density lipoprotein.
Values are expressed as mg/dl (mean±SD).
Concentrations significantly lower in patients with suicidal tendencies.
**p<0.001, *p<0.01.
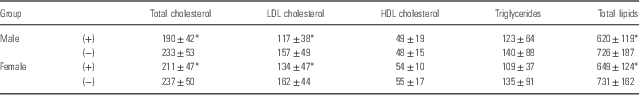
Of the total number of depressed men, 19% have made a suicidal attempt during 3 months before admission, as well as 13% of the depressed women. Concentrations of total cholesterol, LDL cholesterol and total lipids were significantly lower in depressed patients who had a suicidal attempt during the 3 months before admission, compared with the remaining patients. No relationship with HDL cholesterol was observed (Table 3).
Lipid levels in depressive patients with (+) and without (−) suicidal attempt in recent 3 months
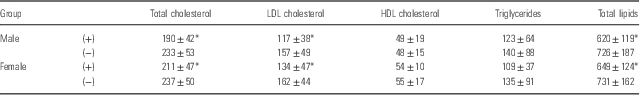
HDL, high density lipoprotein; LDL, low density lipoprotein.
Values are expressed as mg/dl (mean±SD).
Concentrations significantly lower in patients with suicidal attempts.
*p<0.05.
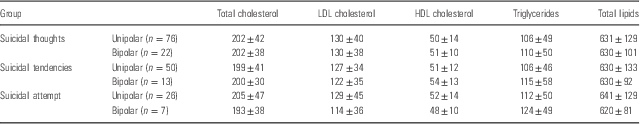
Table 4 compares lipid levels between patients with unipolar and bipolar depression having suicidal thoughts, suicidal tendencies and after suicidal attempt.
Comparison of lipid levels between patients with unipolar and bipolar depression having suicidal thoughts, suicidal tendencies and after suicidal attempt
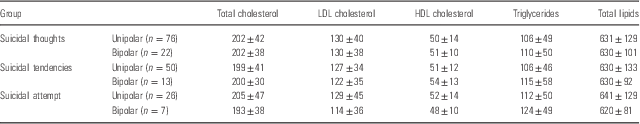
HDL, high density lipoprotein; LDL, low density lipoprotein.
Values are expressed as mg/dl (mean±SD).
No difference between unipolar and bipolar depressed patients.
The results of comparison reveal no differences in concentrations of total cholesterol, LDL cholesterol, HDL cholesterol, triglycerides, and total lipids between unipolar and bipolar depressed patients showing suicidal thoughts, suicidal tendencies and making suicidal attempt during the 3 months before admission.
Discussion
The main finding of our study is that some elements of lipid profile (total cholesterol, LDL cholesterol and total lipids) can provide a state-dependent marker of suicidal behaviour in Polish depressive patients recently admitted to a psychiatric hospital. These findings may corroborate the results of a previous Polish study by Rabe-Jabłońska and Poprawska (Reference Rabe-Jablońska and Poprawska12), who observed acute depression episode patients exhibiting suicidal behaviour had lower levels of total and LDL cholesterol. Our results correspond to the majority of meta-analyses performed since 1990s (Reference Muldoon, Manuck and Matthews1–Reference ZHANG3,Reference de Berardis, Marni and Piersanti6) and to a number of individual studies, including those performed in recent decades (Reference Brunner, Bronisch, Pfister, Jacobi, Höfler and Wittchen13–Reference Ruljancic, Mihanovic and Cepelak16).
In addition, an association of suicidal behaviour in our study was documented by low level of total lipids and, in some instances, also low levels of triglycerides. Recent research (Reference Park, Lee and Lee9,Reference Baek, Kang and Fava10) also reported low levels of triglycerides associated with suicidality. However, our study found no association between HDL cholesterol and any of the suicidal parameters studied, thus contradicting the results recently obtained by Baek et al. (Reference Baek, Kang and Fava10).
The main neurobiological mechanism explaining a connection between low cholesterol and suicidal behaviour is the cholesterol–serotonin impulsivity model (Reference Engelberg17). Low cholesterol is associated with a decreased activity of serotonergic system, reflected by low levels of serotonin and its main metabolite, 5-hydroxyindolacetic acid (5-HIAA), in serum and cerebrospinal fluid (CSF). In suicide attempters, lower concentration of 5-HIAA was found in CSF, and its connection with low serum cholesterol was established (Reference Ringo, Lindley, Faull and Faustman18,Reference Hibbeln, Umhau, George, Shoaf, Linnoila and Salem19).
A disturbance of serotonin system related to low cholesterol may be connected with depression. Such a link between low cholesterol and depression has been demonstrated by Morgan et al. (Reference Morgan, Palinkas, Barrett-Connor and Wingard20) in elderly men, as well as between low cholesterol and intensity of depression in the Polish study (Reference Rabe-Jablońska and Poprawska12). Recently, Indian investigators found significantly lower levels of LDL cholesterol and triglycerides in depressive patients compared with the healthy control group (Reference Patra, Khandelwal, Chadda and Ramakrishnan21). An association between serotonin and cholesterol may have some genetic background because subjects with s allele of serotonin transporter gene polymorphism, which has been linked to depression, have lower LDL cholesterol (Reference Fischer, Gruenblatt, Pietschmann and Tragl22). A recent review points to a relationship between the use of cholesterol-lowering statins and the appearance of depression (Reference You, Lu, Zhao, Hu and Zhang23).
Aselius et al. (Reference Aselius, Nordström and Jokinen24), investigated an association between exposure to violence during childhood, level of cholesterol and adult violence in suicide attempters. The correlation between exposure to violence as a child and adult violence was significant in patients with serum cholesterol below median values in this population.
Recently, Freemantle et al. (Reference Freemantle, Chen, Cruceanu, Mechawar and Turecki25), analysed brain oxysterol levels, which are enzymatic oxidation products of cholesterol, in the prefrontal cortex of suicide victims. Their results show a significant increase in 24-hydroxysterol, reflecting a higher turnover of cholesterol. They suggest that this metabolic process may be responsible for reduction in central and peripheral cholesterol in these subjects. These authors also found altered phospholipid levels connected with increased activity of cholesteryl ester hydrolase, which may impair inhibitory neurotransmission in the prefrontal cortex of subjects with violent suicides (Reference Freemantle, Mechawar and Turecki26).
The limitations of our study include its cross-sectional nature and a lack of a healthy control group. In addition, the association between low cholesterol and suicidal behaviour was not confirmed in a number of studies. Several research studies on the Asian population were unable to find such an association (Reference Park, Yi, Lim and Hong8,Reference Tsai, Kuo, Chen and Lee27,Reference Huang28). In their research involving 193 current suicide attempters hospitalised in Lexington, de Leon et al. (Reference de Leon, Mallory, Maw, Susce, Perez-Rodriguez and Baca-Garcia29) found that low cholesterol levels were not associated with increased suicide risk but with a decreased risk in men. They suggest that regional or ethnic differences may exist with respect to this phenomenon.
The strength of our study may reflect the large number of patients studied, including both unipolar and bipolar depression, specifically focusing on suicidality, and measuring both total, LDL and HDL cholesterol, and triglycerides and total lipids.
In conclusion, the results of our study add to a majority of research showing the association between suicidal behaviour and low levels of total and LDL cholesterol. In addition, we found that such an association may also apply to low total lipids, and in some instances, to low triglycerides.
Acknowledgements
B.A. performed clinical assessment of the patients and made statistical analysis. J.K.R. designed the study and wrote the final version of the manuscript.
Financial Support
The study was supported by research funds from the Department of Adult Psychiatry, Poznan University of Medical Sciences.
Conflicts of Interest
None.
Ethical Standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.