Introduction
Tobacco use continues to be a major contributor to preventable morbidity and mortality, being strongly linked to a growing list of health conditions, including several forms of cancer, and cardiovascular and respiratory diseases (Fiore et al., Reference Fiore, Jaen, Baker, Bailey, Benowitz and Curry2008). Unfortunately, successful smoking cessation continues to be challenging, despite the availability of smoking cessation medications and behavioural counselling techniques (Cahill, Stevens, Perera, & Lancaster, Reference Cahill, Stevens, Perera and Lancaster2013). Medications such as varenicline (Champix®/Chantix®), the most effective agent available for smoking cessation (Cahill, Lindson-Hawley, Thomas, Fanshawe, & Lancaster, Reference Cahill, Lindson-Hawley, Thomas, Fanshawe and Lancaster2016), have several clinical issues impacting on their effectiveness, such as causing intolerable adverse effects leading to premature therapy discontinuation, poor adherence and a resurgence of cravings and withdrawal symptoms after therapy has been completed (Balmford, Borland, Hammond, & Cummings, Reference Balmford, Borland, Hammond and Cummings2011; Catz et al., Reference Catz, Jack, McClure, Javitz, Deprey and Zbikowski2011; Drovandi, Chen, & Glass, Reference Drovandi, Chen and Glass2016; Liberman et al., Reference Liberman, Lichtenfeld, Galaznik, Mastey, Harnett and Zou2013; Rigotti et al., Reference Rigotti, Pipe, Benowitz, Arteaga, Garza and Tonstad2010).
Modifications to the varenicline regimen through changes in daily dosing may address these problems as suggested by a recent systematic review (Drovandi, Teague, Glass, & Malau-Aduli, Reference Drovandi, Teague, Glass and Malau-Aduli2017). Modifications trialled and warranting further study include the use of an extended duration of pre-quit varenicline therapy (Hajek, McRobbie, Myers, Stapleton, & Dhangi, Reference Hajek, McRobbie, Myers, Stapleton and Dhangi2011; Hawk et al., Reference Hawk, Ashare, Lohnes, Schlienz, Rhodes and Tiffany2012), and an extended duration of varenicline therapy (Tonstad et al., Reference Tonstad, Tǿnnesen, Hajek, Williams, Billing and Reeves2006; Williams, Reeves, Billing, Pennington, & Gong, Reference Williams, Reeves, Billing, Pennington and Gong2007). These modifications were theorised to reduce the frequency and severity of adverse events at the beginning of therapy, and the long-term risk of relapse at the end of treatment. A modification yet to be tested is a step-down period at the end of varenicline therapy, potentially reducing the short-term risk of relapse at the end of treatment, which has been encountered in some clinical trials (Rigotti et al., Reference Rigotti, Pipe, Benowitz, Arteaga, Garza and Tonstad2010; Tonstad et al., Reference Tonstad, Tǿnnesen, Hajek, Williams, Billing and Reeves2006).
This protocol was developed to evaluate changes in the effectiveness and tolerability of varenicline, when it is introduced more slowly over a period of 4 weeks, and ceased over a period of 2 weeks. It is proposed that the use of extended ‘step-up’ therapy will reduce the frequency and severity of adverse events, which are usually more prominent at the beginning of therapy (Tonstad et al., Reference Tonstad, Tǿnnesen, Hajek, Williams, Billing and Reeves2006; Williams et al., Reference Williams, Reeves, Billing, Pennington and Gong2007), and the use of ‘step-down’ therapy will reduce the likelihood of recurring cravings and withdrawal symptoms due to a sudden drop in dopamine levels from the removal of varenicline (Coe et al., Reference Coe, Brooks, Vetelino, Wirtz, Arnold and Huang2005).
Methods
This protocol has been registered with the Australian New Zealand Clinical Trials Registry (ACTRN12616000802404p), and was developed to comply with the Helsinki Declaration of 1975 (revised in 2008) and Australian Guidelines on the development of ethical research. Ethical approval was given by the James Cook University's Human Research Ethics Committee (approval number H6748). This article for the study protocol follows the Standard Protocol Items: Recommendations for Interventional Trials (SPIRIT) checklist (Chan et al., Reference Chan, Tetzlaff, Altman, Laupacis, Gøtzsche and Krleža-Jerić2013).
Study Design
A randomised, double-blinded, placebo-controlled trial will consist of three treatment groups with different dosing schedules: two intervention groups (step-up and step-down varenicline therapies) and a placebo-matched control group. This community-based single-site trial will require participants to adhere to a treatment duration of 16-weeks and a follow-up duration of 12-weeks, and attend scheduled clinic visits at James Cook University's Health Clinic in Townsville, Australia.
Participant Eligibility and Recruitment
Eligible participants are required to be at least 18 years old and motivated to quit smoking, have a Fagerström Test for Nicotine Dependence (FTND) score of at least 5.0, indicate their intention to comply with scheduled clinic visits, have no history of major or uncontrolled depressive or other psychiatric disorders, and use appropriate hormonal contraception if a woman of childbearing age. Participants are ineligible if they have a history of a suicide attempt or any suicidal behaviours in the previous 2 years, have a severe or uncontrolled major depressive, psychiatric or cardiovascular disorder, have a current psychosis, have concomitant substance abuse disorders, have used varenicline within the previous 6 months, or do not agree to abstain from non-cigarette tobacco products during the intervention and follow-up periods.
Participants will be recruited from pharmacies, general practitioner clinics and newspaper advertisements in Townsville, Australia. Potential participants may view, self-assess and complete an expression of interest flyer at these locations, which include preliminary eligibility questions, and the contact details of the principal investigator to facilitate a baseline visit with the potential participant. Final eligibility and further information and consent documents will be provided during the baseline visit to ensure the eligibility and safety of participants.
Treatment Groups and Interventions
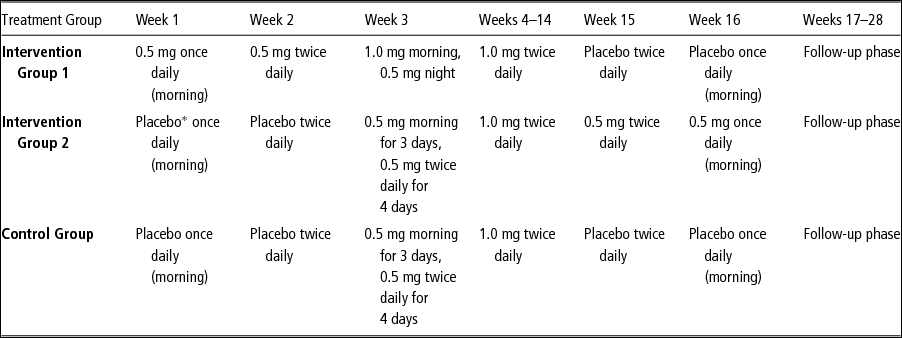
The dose regimens for all the treatment groups are detailed in Table 1. Intervention group 1 (step-up) will be assigned to take 0.5 mg once daily for 7 days, 0.5 mg twice daily for 7 days, 0.5 mg once daily plus 1.0 mg once daily for 7 days, 1.0 mg twice daily for 11 weeks, then 2 weeks of placebo tablets matched to the step-down intervention group. Intervention group 2 (step-down) will be assigned to take 2 weeks of placebo tablets matched to the step-up intervention group, followed by 0.5 mg once daily for 3 days, 0.5 mg twice daily for 4 days, 1.0 mg twice daily for 11 weeks, then 0.5 mg twice daily for 7 days, then 0.5 mg once daily for 7 days. The control group will be assigned to take 2 weeks of placebo tablets matched to the step-up intervention group, followed by 0.5 mg once daily for 3 days, 0.5 mg twice daily for 4 days, 1.0 mg twice daily for 11 weeks, then 2 weeks of placebo tablets matched to the step-down intervention group. The medication provided will be supplied in a dose administration aid (DAA) to avoid dosing confusion, maintain treatment blinding and to serve as a mechanism for monitoring participant adherence (Haywood & Glass, Reference Haywood and Glass2016).
Varenicline dosing schedules for the three treatment regimens

*Only 0.5 mg-tablet matching placebos will used during the study.
Eligible participants will be randomly assigned a participant identifier number (PIN), each of which is linked through a computer-generated randomisation sequence to a treatment group. Treatment allocations will be sealed in individual envelopes, and a research associate who is not involved in the study will be responsible for affixing PINs to each DAA to ensure continued double-blinding. However, a participant's allocated treatment can be revealed prior to completion of the study, if the participant experiences a life-threatening or other severe event.
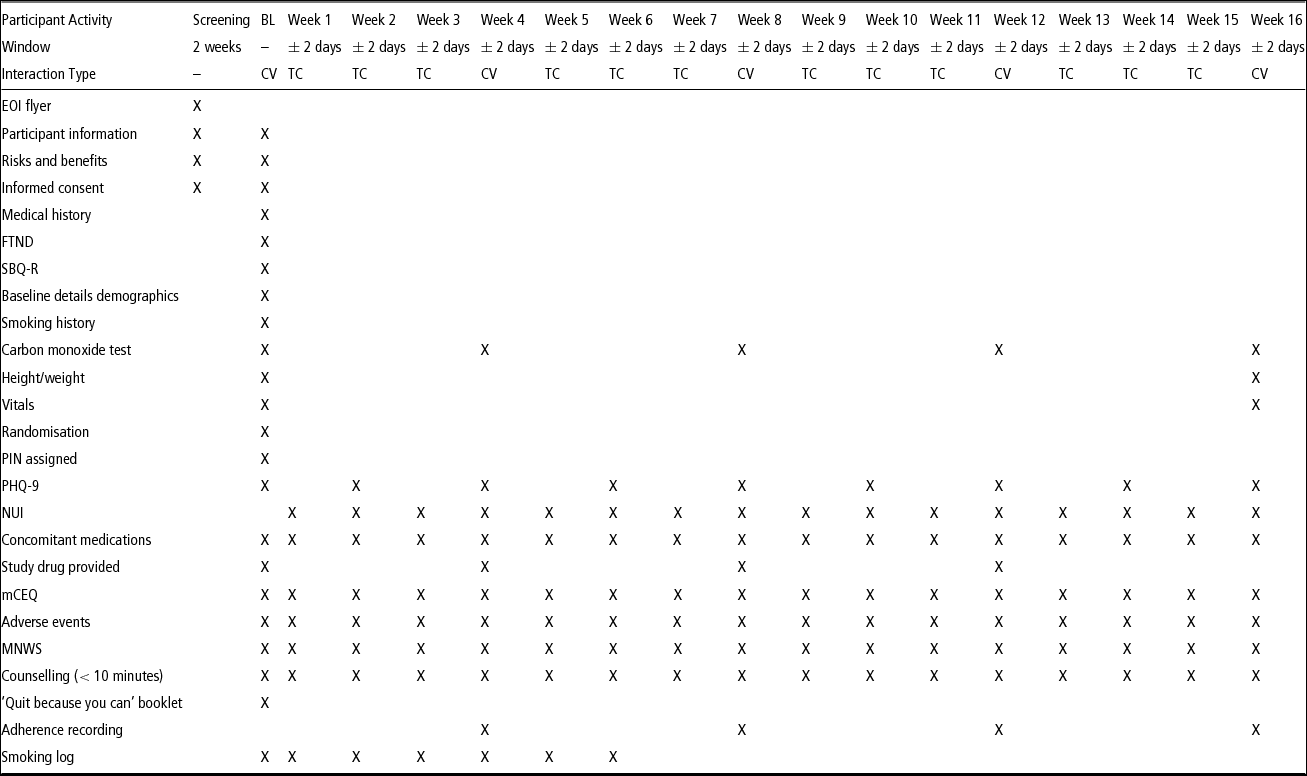
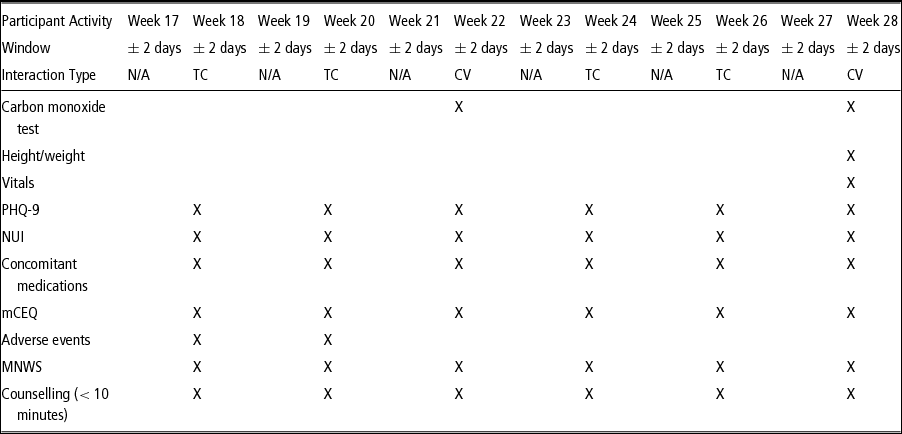
Interventions for eligible participants for the duration of the trial, including data collection tools are detailed in Tables 2 and 3 for the treatment and follow-up periods, respectively. Participants will be contacted weekly during the treatment phase, and fortnightly during the follow-up phase through a combination of telephone calls and face to face clinic visits. These scheduled interactions will gather data on participant health indicators (both physical and mental), concomitant medication load, adverse events, cravings and withdrawal symptoms experienced, and recent smoking habits. Participants will receive a booklet on smoking cessation during the baseline visit, and up to 10 minutes of individualised counselling on techniques for smoking cessation during each intervention, and be recommended to set a quit date between weeks 4 and 6 of treatment.
Schedule of procedures between the principal investigator and study participants during the treatment period

BL: Baseline CV: Clinic Visit TC: Telephone Call EOI: Expression of Interest FTND: Fagerström Test for Nicotine Dependence SBQ-R: Suicide Behaviours Questionnaire Revised PIN: Participant Identifier Number PHQ-9: Patient Health Questionnaire-9 NUI: Nicotine Use Inventory mCEQ: Modified cigarette evaluation questionnaire MNWS: Minnesota Nicotine Withdrawal Scale.
Schedule of procedures between the principal investigator and participants during the follow-up period.

CV: Clinic Visit TC: Telephone Call PHQ-9: Patient Health Questionnaire-9 NUI: Nicotine Use Inventory mCEQ: Modified cigarette evaluation questionnaire MNWS: Minnesota Nicotine Withdrawal Scale.
Study Outcomes
Primary outcomes to be assessed during this trial are comparisons of biochemically confirmed continuous abstinence rates, 7-day point prevalence abstinence rates, and the frequency, severity and duration of adverse events, cravings and withdrawal symptoms. These primary outcomes will determine if step-up or step-down varenicline dosing has positive effects as measured by improved smoking cessation rates, and reduced adverse events, cravings or withdrawal symptoms during cessation attempts. Secondary outcome measures include adherence to the study medication throughout treatment, and changes in smoking satisfaction and reward.
Data Collection and Management
During the interventional and follow-up periods, as detailed in Tables 2 and 3, respectively, data for the primary and secondary outcomes will be initially collected from participants on a weekly basis, with monthly face to face clinic visits being interspersed by telephone calls. Continuous and 7-day point prevalence abstinence rates will be assessed by multiple methods, including the Nicotine Use Inventory (NUI), a personal smoking log and biochemically confirmed using a Micro+ Smokerlyzer device. The NUI will be administered during scheduled telephone and clinic visits by the principal investigator, querying the participants’ use of cigarettes or any other nicotine-containing products. The smoking log will be used daily by participants to track their exposure to nicotine throughout the treatment and follow-up periods, and reported abstinence to be confirmed during clinic visits using a Micro+ Smokerlyzer device, with a cut-off reading of < 10 ppm considered as being abstinent. All adverse events, including serious and non-serious, will be recorded on case report forms on a per-participant basis, to be reported to the principal investigator, and causality determined during the scheduled telephone and face to face clinic visits. Participants will be encouraged to log adverse events daily as they occur, ensuring to note changes in severity or apparent cause if they persist over several days, will be coded using MedDRA, and followed-up until cessation of the event. Concerning or unusual adverse events will be reported immediately to the principal investigator, with events considered to be serious or unexpected to also be reported to Pfizer Inc., the approving ethics committee, and the Adverse Drug Reaction unit of the Therapeutic Goods Administration. Physical health will be assessed at the commencement and cessation of treatment, and at the completion of the follow-up period, and include recording of participant height, weight and vital signs (blood pressure, respiratory rate and heart rate). Mental health will be assessed initially using the Suicide Behaviours Questionnaire Revised (SBQ-R) (Osman et al., Reference Osman, Bagge, Guitierrez, Konick, Kooper and Barrios2001), and monitored fortnightly using the Patient Health Questionnaire-9 (PHQ-9) (Kroenke, Spitzer, & Williams, Reference Kroenke, Spitzer and Williams2001). The 9-item version of the Minnesota Nicotine Withdrawal Scale (MNWS) (Hughes & Hatsukami, Reference Hughes and Hatsukami1986) will be used to assess weekly changes in cravings and withdrawal symptoms, using a 5-point Likert scale ranging from 0 (not at all) to 5 (extreme). The MNWS will be self-administered by participants on a daily basis, and reported to the principal investigator during phone calls and clinic visits.
Medication adherence checks will be done by the principal investigator during the treatment period clinic visits, by counting remaining tablets in returned DAAs. Changes in smoking satisfaction and reward will be assessed by the principal investigator using the Modified Cigarette Evaluation Questionnaire (mCEQ) (Cappelleri et al., Reference Cappelleri, Bushmakin, Baker, Merikle, Olufade and Gilbert2007), a 12-item questionnaire rating on a 7-point scale from one (not at all) to seven (extremely) the common experiences normally received by smoking. All data collection will be performed by the principal investigator only, who will personally enter all data into a master excel spreadsheet, which will be stored on a password-protected computer in the office of the principal investigator. PINs will be used in this spreadsheet to ensure confidentiality.
Sample Size and Statistical Analyses
Using GPOWER v3.1, it was determined that to detect a moderate effect size with 80% power, a total of 119 completers are required for statistical power for the primary endpoint of the study, being the biochemically confirmed continuous abstinence rate for participants in each treatment group. To ensure statistical power is achieved, up to 201 participants will be enrolled to accommodate up to 40% participant withdrawal from treatment and loss to follow-up as demonstrated by similarly designed smoking cessation trials (Hajek et al., Reference Hajek, McRobbie, Myers, Stapleton and Dhangi2011; Hawk et al., Reference Hawk, Ashare, Lohnes, Schlienz, Rhodes and Tiffany2012; Rigotti et al., Reference Rigotti, Pipe, Benowitz, Arteaga, Garza and Tonstad2010). Intention to treat analysis will include univariate and multivariate analysis of the factors associated with abstinence post-quit date. Analysis will occur after the final participant has completed their end-of-study clinic visit, whereupon blinding will be removed.
Data analysis will include assessing biochemically confirmed continuous abstinence rates, and the presence of, and numerical scale of severity of adverse events, cravings and withdrawal symptoms, for smokers or non-smokers. Quantitative data will be subjected to multivariate analysis in SPSS (v23) to establish relationship between categorical and continuous variables. Logistic regression will be used to assess the effect of the treatment regimens on smoking cessation. Odds ratios (OR) will be used to compare the relative odds of occurrence of smoking cessation, between the active and control groups. The 95% confidence intervals (CI) will be used to estimate the precision of the OR. Survival analysis (via cox regression) will be used to measure more precise and absolute estimates of when smoking cessation occurs. A survival probability estimate will also be calculated using the Kaplan–Meier method. Survival curves and a non-parametric statistical log rank test will be used to determine significant differences between the groups. The severity of adverse events, cravings and withdrawal symptoms will be compared between the three groups, using a General Linear Model (GLM) in SPSS (v23). Significance levels were set at 0.05 and a medium effect size as reported by Cohen (Reference Cohen1988) will be calculated to determine the magnitude of statistically significant relationships. No interim analyses are planned for this study.
Study Monitoring
Adverse event-recording documents will be provided both electronically and as hard-copies during clinic visits, and when additionally requested. Participants who experience intolerable adverse events or worsening of concomitant medical conditions may have their dose temporarily reduced or withdrawn, with recommencing of the standard dose at the discretion of the participant, principal investigator and medical advisor. Participants may also have treatment permanently withdrawn if their participation places them at an excessive risk of harm (including changes in behaviour or mood), or demonstrate an inability to comply with the study protocol. Participants will be encouraged to log adverse events daily, which will be regularly monitored by the principal investigator to track event progression and ensure the resolution of events.
Ethics and Dissemination
This research has been approved by the James Cook University Human Research Ethics Committee (approval number H6748), with amendments to the protocol submitted to the committee and to Pfizer Inc. as they occur. The principal investigator will be responsible for gaining informed consent from participants and will maintain patient confidentiality during clinic visits and phone calls. Advisors to the principal investigator will only have access to de-identified data from participants. Results for this research will largely be disseminated through publication in peer-reviewed journals. The approving ethics committee, Pfizer Inc., and the supplier of the DAA (Webstercare) will be provided with detailed reports on the outcomes of the research, and participants will be offered a report of the research if desired.
Acknowledgements
The authors would like to acknowledge Webstercare for their provision of Webster-paks® to be used during the study, and JCU Health for offering their clinic for the principal investigator to conduct clinic visits with participants.
Financial Support
The principal investigator has received financial support through an Australian Government Research Training Program Scholarship and James Cook University for the conduct of postgraduate research. The study medication and placebo tablets are being sought through Pfizer Inc.
Conflict of Interest
None reported. Pfizer Inc. support the academic freedom of researches and do not intend to contribute to, or modify results or publications resulting from the data collected during this research.
Ethical Standards
The authors assert that all procedures contributing to this work comply with the ethical standards of relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.