




No CrossRef data available.
Article contents
Spontaneous closure of atrial septal defects within the oval fossa
Published online by Cambridge University Press: 20 January 2005
Abstract
Objectives: To estimate the incidence and timing of spontaneous closure of atrial septal defects within the oval fossa, to study the modalities for diagnosis, and predict the need for therapeutic intervention. Methods: We reviewed retrospectively the medical records of patients with isolated atrial septal defects within the oval fossa, so-called “secundum defects”, diagnosed between January 1990 and February 2003. Based on the initial echocardiographic evaluation, we divided defects into small ones measuring from 3 to 5 mm, medium ones from 5 to 8 mm, and large ones greater than 8 mm. Results: We identified 121 patients, 50 (41.3%) of whom had failed to thrive, and 14 (11.6%) had congestive heart failure. At a mean of 44.9 ± 22.1 months following diagnosis, with a range from 12 to 102 months, the defects had closed spontaneously in 31 patients (25.6%). Of 22 patients having small defects, spontaneous closure occurred in 18 (82%) at a mean age of 18.9 ± 10.2 months. Of 27 patients with defects of medium size, 12 (44%) either experienced spontaneous closure, or else the defect effectively became a patent oval foramen, at a mean age of 51.2 ± 32.2 months. Only 1 (1.4%) of the 72 patients with a defect larger than 8 mm in size underwent spontaneous closure. The defects increased in size in 8 patients (6.6%). Intervention was necessary in 76 patients (63%) at a mean age of 75.5 ± 15.2 months. Conclusion: The initial size of a defect within the oval fossa at diagnosis is the best predictor of its natural history. Some defects increase in size with growth, irrespective of their initial size.
Information
- Type
- Original Article
- Information
- Copyright
- © 2004 Cambridge University Press
An atrial septal defect within the oval fossa is a relatively common congenital cardiac anomaly that, in contrast to most malformations, can be considered nearly completely correctable.1 Little, however, is known about the natural history of such defects, despite the significant attention they have recently received. There are increasing reports of infants who present with congestive heart failure in the setting of an isolated defects,2–5 or whose defects increase in size in relation to the growth of the infant.6, 7 Spontaneous closure of such defects, nonetheless, even in symptomatic infants,2, 8–10 or in those beyond the age of 5-years,11 is well reported. With these aspects in mind, we evaluated retrospectively a cohort of patients to estimate the incidence and timing of spontaneous closure of atrial septal defects within the oval fossa, to study the modalities for diagnosis, and to predict the need and timing for therapeutic intervention.
Methods
We studied 121 consecutive patients with isolated so-called “secundum” atrial septal defects, in reality those located within the confines of the oval fossa, diagnosed between January 1990 and February 2003. The patients had been referred for evaluation of a heart murmur, heart failure, or because of cardiomegaly or chest pain. The criterions for inclusion were:
- The presence of an atrial septal defect with a minimal size of 3 mm. We excluded those having smaller defects because, according to Radzik et al.,12 such defects are better described as probe patency of the oval foramen.
- The absence of other significant cardiac anomalies, albeit that we included those with mitral valvar prolapse in the absence of mitral regurgitation.
We reviewed the medical records, the 12-lead electrocardiograms, and the chest radiographs, as well as the echocardiograms, of all patients. We noted the age and weight at diagnosis and on follow-up, the associated syndromes, the presence or absence of symptoms and the final outcome in terms of spontaneous closure versus persistence of the defects and the eventual need for intervention. We measured the cardiothoracic ratio on the chest radiographs, taking a ratio between 0.5 and 0.6 as evidence of mild cardiomegaly, between 0.6 and 0.75 as moderate cardiomegaly, and severe when greater than 0.75. The 12-lead electrocardiograms were reviewed for rhythm, frontal QRS-axis, PR-interval and right ventricular conduction delay. We analysed the initial and subsequent echocardiograms, all performed using a 5.0 MHz transducer (Vingmed CFM 800 super Vision). The maximal size of the defect was measured from the subcostal long and short axes, and the longest end-systolic measurement was taken. We used the same view as taken during the initial mea-surement for follow-up in each patient. Left-to-right shunting was confirmed by colour Doppler echocardiography. When available, we measured the right ventricular size on M-mode parasternal long axis recordings, comparing our findings with reference values,13 otherwise we assessed subjectively the presence of right ventricular dilation. The pattern of motion of the ventricular septum was evaluated using both cross-sectional and M-mode recordings.
Patients were evaluated clinically and echocardiographically at intervals ranging between 1 and 12 months, according to their clinical state. All patients with defects not documented to have been repaired or closed spontaneously had an echocardiogram performed in January 2003 by a “blinded” cardiologist as a final follow-up.
Classification
We divided the patients into groups, as proposed by Radzik and colleagues,12 into those with small defects, measuring from 3 to 5 mm, those with defects of medium size measuring from 5 to 8 mm, and those with large defects greater than 8 mm.
Statistical analysis
Statistical analysis was performed using SPSS 10.0 for windows. Data are expressed as mean plus or minus the standard deviation, and the range. Mean values were compared using independent t-test, and one-way ANOVA. A Kaplan-Meier survival function was used to produce a graphical representation of the closure of the defects as a function of time for the different groups. A probability less than 0.05 was deemed to be significant.
Results
We included a total of 121 patients for analysis. Of these, 74 (61.2 %) were females, giving a ratio of females to males of 1.6 to 1. There were 22 patients (18.2%) having small defects measuring from 3 to 5 mm, 27 patients (22.3%) with defects of medium size, measuring from 5 to 8 mm, and 72 (59.5%) having large defects greater than 8 mm in size. Of those with small defects, 59% were male, whereas 65.6 % of those with medium and large defects were female.
Age and weight at diagnosis
The mean age at diagnosis was 23.0 ± 24.3 months, with a range from 1 day to 11 years. The mean age at diagnosis differed significantly depending on the initial size of the defect, being 3.3 months for patients with small defects, compared to 32.5 months for patients with a large defect (p < 0.001 – Table 1). The mean age at diagnosis for patients with heart failure was 14 ± 17.9 months, with a range from 2 months to 61 months, with 79% presenting during the first year of life.
Table 1. Showing the relation between the size of the defect and the mean age at diagnosis.

The body weight at the time of diagnosis was below the 5th percentile in 50 patients (41.3%), with 3 patients (6%) having small or medium-sized defects being below the 5th percentile at the time of diagnosis, as compared to 47 patients (65.3%) with large defects (p < 0.001 – Fig. 1).

Figure 1. The centiles for weight at the time of diagnosis of our 121 patients. Note that the distribution is skewed toward the lower centiles.
Patients with medium and large defects, measuring greater than 5 mm, and who experienced spontaneous closure, were significantly younger, at a mean age of 9.2 months, at the time of diagnosis, with a minority (13%) having subnormal body weight, as compared to those with defects of the same size that remained unchanged. The patients making up the latter group were diagnosed at a mean age of 30.5 months, with the majority (56%) having a body weight less than normal at the time of diagnosis (p value ≤ 0.001 and 0.002 respectively).
Associated anomalies
Down’s syndrome was found in 19 patients (15.7%), but only one had Holt-Oram syndrome. In 4 patients (3.3%) there was associated prolapse of the mitral valve.
Clinical presentation
We found that 14 patients (11.6%) presented with congestive heart failure, and all except one had defects larger in size than 8 mm. The remaining 107 patients (88.4%) were detected while investigating an incidental heart murmur, or else were referred because of cardiomegaly or chest pain. A history of mild exercise intolerance was obtained retrospectively in 15 patients (12.4%). All of these also had large defects, and were older than 4 years at diagnosis.
Those with small defects
All patients were asymptomatic, with 20 (91%), including 8 with Down’s syndrome, detected during the investigation of asymptomatic cardiac murmurs. Of the other 2 patients, one was detected during evaluation of supraventricular tachycardia due to atrioventricular nodal re-entry, and the other was an infant of a diabetic mother.
Those with defects of medium size
Of these patients, 23 (85.2%), including 7 with Down’s syndrome, had been referred with an asymptomatic cardiac murmur, with 3 patients being diagnosed incidentally during investigation of chronic chest pain, one of whom had associated mitral valvar prolapse, and only 1 patient presenting with congestive heart failure.
Those with large defects
The mean size of the defects was 14.8 ± 5.3 mm, with a range from 8 to 28 mm. Of the patients making up this group, 4 had Down’s syndrome, and one had Holt-Oram syndrome. Congestive heart failure had been the presenting feature in 13 (18.1%), with 54 patients being detected during investigation of a heart murmur (75%), 2 presenting with cardiomegaly (2.8%), 2 with recurrent chest pain (2.8%), and the final one having supraventricular tachycardia, not of the type expected from atrial overload.
Electrocardiogram
Electrocardiographic abnormalities were documented in 109 patients (90%). Normal sinus rhythm was observed in all but two patients (1.7%); who presented with atrioventricular nodal reentry. The mean frontal QRS-axis was to the right in 67 patients (55.4%), (+100° to +180°). First-degree atrioventricular block was documented in 12 patients (9.9%), and delay of right ventricular conduction was seen in 107 patients (88.4%).
An abnormal electrocardiogram was found in 15 of 22 patients (68.2%) with small defects, and of these, 5 (22.7%) had right-axis deviation, 13 (59%) had right ventricular conduction delay, while all had a normal PR-interval.
Similar abnormalities were found in 23 patients (85.2%) with defects of medium size, with 7 (25.9%) having right axis deviation, 4 (14.8%) first degree heart block, and 23 (85.2%) right ventricular conduction delay.
The electrocardiogram was abnormal in 71 of the patients (98.6%) with large defects, with 55 (76.4%) having right axis deviation, 8 (11.1%) first degree heart block, and 71 (98.6%) right ventricular conduction delay.
Chest radiographs
Cardiomegaly was found in 53 patients (44%), with mild changes seen in 2 patients (9%) with small defects, and mild-to-moderate changes in 7 (26%) with defects of medium size. In 44 (61%) of those with larger defects, there was mild-to-severe cardiomegaly. The presence of cardiomegaly on chest radiograph was always associated with echocardiographic evidence of right-heart dilation.
Echocardiographic findings
Right heart dilation was found in 83 patients (68.6%). This was associated with flattened or paradoxical motion of the ventricular septum in 75 patients (62%). Signs of right heart volume overload were found in 2 patients (9%) with small defects, 10 (37%) with medium defects, and 71 (98.6%) with large defects. We found signs of volume overload in all patients with a defect measuring more than 6 mm who were diagnosed after, or followed-up until, the age of 5 years. Absence of dilation of the right heart on echocardiography was always associated with normal cardiac size on chest radiographs, while the presence of mild dilation was associated with an increased cardiothoracic ratio in two-fifths of cases. Moderate or severe dilation was always associated with radiographic evidence of cardiomegaly (p < 0.001).
Pulmonary arterial hypertension
Pulmonary arterial pressures greater than 30 mmHg were found in 8 patients (6.6%); 6 being male and 2 female, with the mean size of the defect being 15.5 ± 6.7 mm, with a range from 9 to 28 mm. The mean age at diagnosis was 17.6 ± 20.9 months, with a range from 2 to 61 months, with 5 patients (62.5%) being below the age of 1 year at the time of diagnosis. The body weight at diagnosis was below the 5th centile in 6 patients (75%). Only one had Down’s syndrome, and all had signs of congestive heart failure. Cardiomegaly and signs of right heart volume overload were also present in all patients.
Follow-up and outcome
Small defects: At a mean period of follow-up of 21.3 ± 13.4 months, with a range from 4 to 56 months, the defect had closed spontaneously in 18 patients (81.8%). In 2 patients (9.1%), the defects remained at their original size, while in another 2 (9.1%), the defects had increased in size from 3 and 4 to 8 and 10 mm, respectively. The defects were closed surgically in the last 2 patients, at ages of 60 and 61 months, respectively.
Defects of medium size
At a mean period of follow-up of 45.5 ± 21.1 months, with a range from 12 to 102 months, the defects had closed spontaneously in 8 patients (29.6%), while in 4 (14.8%), the defects had decreased in size, effectively becoming patent oval foramens. In 1 patient (3.7%), the defect decreased in size from 7 to 4 mm. This was the only patient who presented with symptoms and signs of heart failure and he is still undergoing follow-up. In 11 patients (40.7%), the defects remained at their original size. Of these, 4 were referred for closure, while 7 are still undergoing follow-up. In 3 patients (11.1%), the defects had increased their sizes from 6, 6, and 7 to 10, 12, and 16 mm, respectively.
Intervention was considered in 7 patients (26%), and was achieved surgically in 4, with the others having transcatheter closure. Radiological evidence of cardiomegaly, as well as echocardiographic evidence of progressive right ventricular volume overload, was seen in 6 of these patients, including the three in whom the size of the defect had increased. Elective intervention was offered to the seventh patient, whose defect measured 7 mm, despite the absence of symptoms, normal weight gain, and only mild volume overload, because there had been no change in the size of the defect at the age of 5 years after follow-up of 55 months.
Large defects
At a mean follow-up of 55.1 ± 17.5 months, with a range from 20 to 99 months, only 1 patient had experienced spontaneous closure (1.4%), the defect in this patient measuring 8 mm. In another patient, the defect had decreased in size from 9 to 4 mm. In 67 patients (93%), the defects did not change in size, but in 3 (4.2%), the defects increased from 11, 14, and 16 to 20, 20, and 22 mm, respectively.
Intervention was considered in a total of 67 patients (93%), including the 8 with elevated pulmonary arterial pressures. All did well except one, who died during attempted surgical closure. This was a 4-month old infant weighing 2.9 kg, with a defect measuring 12 mm, intractable cardiac failure, and elevated pulmonary arterial pressures. We are still following 4 patients (5.6%), one because of a progressive decrease in the size of the defect, and 3 who will probably be candidates for elective intervention, but who currently are asymptomatic and thriving, with only signs of mild volume overload. The outcomes for the patients with defects of different size are shown in Table 2.
Table 2. Summarizes the outcome of 121 patients with defects of different sizes.

Indications for intervention
Intervention was considered in a total of 76 patients (63%), including 11 patients (16.4%) with indications for early intervention. These were the uncontrolled symptoms of cardiac failure associated with failure to grow and signs of volume overload despite aggressive medical treatment. In the other cases, intervention was considered mainly because of the presence of right heart volume overload, an increase in the size of the defect, or as an elective procedure prior to the age for schooling in those with large defects that showed no evidence of a spontaneous decrease in size.
Age at intervention
The mean age for those having early intervention was 16.6 ± 6.2 months, with a range from 4 to 24 months, otherwise the mean age at intervention was 75.5 ± 15.2 months.
Spontaneous closure
Spontaneous closure occurred in a total of 31 patients, giving an overall incidence of 25.6%. The mean age at spontaneous closure for patients with small defects was 18.9 months, with a range from 6 to 55 months, with 94% of the closures documented before the age of 2 years. The mean age at spontaneous closure for patients with defects of medium size was 51.2 months, with a range from 15 to 137 months, with 92% of closures documented before the age of 6 years (Table 3). The timing of spontaneous closure differed significantly according to the sizes of the defects (p = 0.005). The probability of spontaneous closure as a function of time in relation to initial size of the defect is shown in Figure 2. Since only one patient with a large defect experienced spontaneous closure, this patient was not included in the analysis. The presence or absence of cardiac failure did not influence the incidence of spontaneous closure, (p = 0.33), nor were there differences in the incidence and timing of spontaneous closure (p > 0.05) between the genders for those with defects of the same size. Spontaneous closure occurred in 10 (52.6%) of 19 patients with Down’s syndrome, with no statistical difference in their incidence and timing of spontaneous closure (p > 0.05) compared to chromosomally normal patients with defects of the same size.
Table 3. The mean age at spontaneous closure, and the period of follow-up for patients with defects of different sizes.


Figure 2. Kaplan-Meier curve showing the proportion of defects remaining open as a function of time according to their initial size for patients with small and medium defects.
Growth-related increase in the size of defects
An increase in the size of the defect was documented in 8 patients (6.6%); 2 initially having small defect, 3 having defects of medium size, and 3 with large defects. The sizes increased at a rate of 1.9 mm per year, with a range of 0.5 to 3 mm per year. All these patients were candidates for intervention.
Discussion
We have collected data retrospectively from a large series of patients with so-called isolated secundum atrial septal defects, in other words those with the defects confined within the oval fossa. The patients formed a group with a wide age range, with defects of variable sizes, and with follow-up of long duration. The mean period of follow-up, however, was shorter for those with small defects, since the majority of these underwent spontaneous closure before the age of 2 years (Table 3).
We found a significant relation between the initial size of the defect and the age at diagnosis; larger defects, compared to the smaller ones, were found in older patients. It has been postulated that an atrial septal defect is usually small in infancy, growing large enough to produce symptoms only later in life.1 Because of this, it is argued that, at an older age, when most of the smaller defects have closed spontaneously, others that had escaped initial clinical detection would have increased the sizes of their defects, with increased left-to-right shunting and obvious abnormalities in the physical examination, thus permitting their detection as larger defects. In our study, an increase in the size of the defect was confirmed in only 8 (6.6%) patients. McMahon et al.,6 in contrast, found that the defects increased in size in two-thirds of their patients, and they endorsed the concept that small defects, initially believed to be hemodynamically insignificant, could grow into major defects. The continuous shunting through the defects, the intrinsically compliant nature of the atrial septum,6 and the stretching in the opposite direction to the short axis of the elliptoid shape of the defect,7 are proposed as mechanisms to explain the growth of defects.
While patients with defects in the oval fossa are typically held to be asymptomatic in childhood, infants are often symptomatic.3–5, 14–19 Our data supports this belief, with almost nine-tenths of our patients being asymptomatic, while four-fifths of those presenting in cardiac failure did so at ages lower than 1 year.
We noted a body weight less than the fifth centile at the time of diagnosis in two-fifths of our patients, with a significant statistical relation to the size of the defect at diagnosis, suggesting that the more hemodynamically significant the defect, the greater is the risk of having a subnormal body weight. Even after excluding patients with congestive cardiac failure, the size of the defect was found to be an independent risk factor for failure to thrive (p < 0.001).
The incidence and severity of the abnormalities seen in electrocardiograms, chest radiographs and echocardiograms correlated positively with the increased size of the defects (p < 0.001). Almost all patients (98.6%) with large defects had signs of right ventricular conduction delay and right heart volume overload on their electrocardiograms and echocardiograms, respectively. The detection of right sided dilation by chest radiography correlated well with that found on echocardiogram, with the apparent ability of the echocardiogram to detect mild dilation that was not visualized on chest radiography.
First degree atrioventricular block has been reported to occur in between one-tenth and one-third of patients with defects in the oval fossa.1 We found this feature in one-tenth of our patients.
Spontaneous closure of atrial septal defects confirmed by echocardiography has been reported to range from one-sixth20 to nine-tenths.21 The wide range of reported incidence is probably due to the wide variation in sizes of the defects among the different studies. Our study showed an overall incidence of spontaneous closure in one-quarter. This is expected, since three-fifths of our cohort had large defects, with an average size of almost 15 mm. Those with small defects, measuring less than 5 mm, had a high chance, over four-fifths, of spontaneous closure, compared to a very low chance, only just over 1%, for those with defects larger than 8 mm. Those with defects of medium size had an unpredictable course, with two-fifths of patients experiencing spontaneous closure at a mean age near 4-years, with this event occurring before the age of 6 years in nine-tenths of this cohort. We had the chance to document spontaneous closure in patients with defects measuring 7 and 8 mm at ages of 137 and 101 months, respectively, because the parents refused intervention. The defects decreased gradually in size until complete closure was confirmed echocardiographically by multiple studies in both patients.
Radzik and colleagues12 limited their study to those diagnosed before the age of 3 months, with the majority (77%) of their group having small defects. We studied a group with broader age range, and three-fifths of our patients had large defects. Despite these differences in age, sex, and the size of the defects, our study endorsed that of Radzik and colleagues12 in showing that the classical female predominance is observed only for defects of medium or large size, specifically those measuring greater than 5 mm, and that the incidence and timing of spontaneous closure is highly correlated with the size of the defect at diagnosis.
Other factors that influenced the incidence of spontaneous closure in our patients were the weight and age of the patient at diagnosis. A normal body weight at diagnosis was associated with a higher rate of spontaneous closure (p = 0.002). Moreover, younger patients at diagnosis had a higher rate of spontaneous closure (p < 0.001). This finding has previously been reported by Cockerham et al.,22 and by Mody,10 both of whom reported an increased likelihood of spontaneous closure in children diagnosed before the age of 2 years.
We documented Down’s syndrome in 16% of our patients, albeit that having the syndrome did not predict the incidence and timing of spontaneous closure.
If untreated, atrial septal defects may cause a variety of complications. These include the eventual development of pulmonary hypertension, atrial arrhythmias, and paradoxical embolisation, with infarction of organs.23 Those with persistent defects permitting a ratio of pulmonary to systemic flows of more than 1.5 should undergo therapeutic closure before school age, or whenever the diagnosis is made if later.24 There is no obvious advantage in delaying the repair beyond this age, for the long-standing volume overload of the right heart causes irreversible changes that contribute to the subsequent complications.25 Since cardiac catheterization is rarely indicated, echocardiographic evidence of right ventricular volume overload is usually taken as an evidence of a significant shunt, and hence an indication for intervention. This was the main reason behind intervention in our series. Earlier intervention is indicated if there is marked cardiomegaly, failure to thrive, or congestive cardiac failure.1
In the light of our experience, we now propose the following strategy for the management of atrial septal defect in our institution, permitting us to inform the parents about our expectation and plan once we know the size of the defect.
- Patients with small defects measuring from 3 to 5 mm are followed periodically using echocardiography to document either the greater chance of spontaneous closure or the minimal risk of an increase in the size of the defect.
- Patients with defects of medium size, between 5 and 8 mm, are followed by echocardiography on a yearly basis until the age of 5 years. Those showing no evidence of a spontaneous decrease in the size of the defect are planned electively for intervention before the age of 6 years. A longer period of conservative follow-up may be allowed for those showing a progressive decrease in the size of the defect.
- Patients with defects of 8 mm or larger are planned electively for intervention prior to commencing school at the age of 4 years, or earlier if indicated, to avoid the inevitable risk of volume overload that is associated with their very low chance of spontaneous closure.
- Early intervention is considered in a patient with a defect of any size should evidence develop of uncontrolled cardiac failure, failure to thrive, progressive increase in the size of the defect, or significant right heart volume overload.
Based on our results, and experience, we now employ a prognostic scoring system devised by Azhari and Shihata, using a number of selected clinical and diagnostic criterions (Table 4). This will help to decide upon the management and predict the need, and timing, of intervention in patients with isolated atrial septal defects in the oval fossa. Patients will be scored at each follow-up evaluation. When there is an increase or a decrease in the size of the defect, the new size will be scored, and one point will be added or deducted from the total score for the documented increase or decrease in size. Patients with score of 3 or less will be followed conservatively, while those with a score of 4 are planned for elective intervention prior to starting school at the age of 4 years. Those with score of 5 or more are candidates for intervention at an earlier age, with the higher the score the more urgent the need for intervention.
Table 4. The proposed prognostic score devised by Azhari and Shihata for patients with atrial septal defects within the oval fossa.

Acknowledgement
We are grateful to Dr. Ziad R. Bulbul, Head of the Section of Pediatric Cardiology at King Faisal Specialist Hospital and Research Center, Riyadh, and Dr. Raja Al-Radadi, for their valuable contributions to this manuscript.
References
Beerman LB, Zuberbuhler JR. Atrial septal defect. In: Anderson RH, Macartney FJ, Shinebourne EA, Tynan M (eds). Paediatric Cardiology. Churchill Livingstone, Edinburgh, 1987, pp 541.
Hoffman JIE, Rudolph AM, Danilowicz D. Left to right atrial shunts in infants. Am J Cardiol 1972; 30: 868–875.Google Scholar
Hunt CE, Lucas RV. Symptomatic atrial septal defect in infancy. Circulation 1973; 47: 1042–1048.Google Scholar
Dimich I, Steinfeld L, Park SC. Symptomatic atrial septal defect in infants. Am Heart J 1973; 85: 601–604.Google Scholar
Toews WH, Nora JJ, Wolfe RR. Presentation of atrial septal defect in infancy. JAMA 1975; 234: 1250–1251.Google Scholar
McMahon CJ, Feltes TF, Fraley JK, Bricker JT, Grifka RG, Tortoriello TA, Blake R, Bezold LI. Natural history of growth of secundum atrial septal defects and implications for transcatheter closure. Heart 2002; 87: 256–259.Google Scholar
Helgason H, Jonsdottir G. Spontaneous closure of atrial septal defects. Pediatr Cardiol 1999; 20: 195–199.Google Scholar
Timmis GC, Gordon S, Reed JO. Spontaneous closure of an atrial septal defect. JAMA 1966; 196: 137–139.Google Scholar
Hartmann AF Jr, Elliott LP. Spontaneous physiologic closure of an atrial septal defect after infancy. Am J Cardiol 1967; 19: 290–292.Google Scholar
Mody MR. Serial hemodynamic observations in secundum atrial septal defect with special reference to spontaneous closure. Am J Cardiol 1973; 32: 978–981.Google Scholar
Brassard M, Fouron JC, van Doesburg N, Mercier LA, De Guise P. Outcome of children with atrial septal defect considered too small for surgical closure. Am J Cardiol 1999; 83: 1552–1555.Google Scholar
Radzik D, Davignon A, van Doesburg N, Fournier A, Marchand T, Ducharme G. Predictive factors for spontaneous closure of atrial septal defects diagnosed in the first 3 months of life. J Am Coll Cardiol 1993; 22: 851–853.Google Scholar
Roge CL, Silverman NH, Hart PA, Ray RM. Cardiac structure growth pattern determined by echocardiography. Circulation 1978; 57: 285–290.Google Scholar
Mahoney LT, Truesdell SC, Krzmarzick TR, Lauer RM. Atrial septal defects that present in infancy. AJDC 1986; 140: 1115–1118.Google Scholar
Hastreiter AR, Wennemark JR, Miller RA. Secundum atrial septal defects with congestive heart failure during infancy and early childhood. Am Heart J 1962; 64: 467–472.Google Scholar
Nakamura FF, Hauck AJ, Nadas AS. Atrial septal defect in infants. Pediatrics 1964; 34: 101–106.Google Scholar
Ainger LE, Page JW. Ostium secundum atrial septal defects and congestive heart failure in infancy. Am J Cardiol 1965; 15: 380–385.Google Scholar
Weinberg M, Miller RA, Hastreiter AR. Congestive heart failure in children with atrial septal defect. J Thorac Cardiovasc Surg 1966; 51: 81–87.Google Scholar
Ghisla RP, Hannon DW, Meyer RA, Kaplan S. Spontaneous closure of isolated secundum atrial septal defects in infants: an echocardiographic study. Am Heart J 1985; 109: 1327–1333.Google Scholar
Fukazawa M, Fukushige J, Ueda K. Atrial septal defects in neonates with reference to spontaneous closure. Am Heart J 1988; 116: 123–127.Google Scholar
Cockerham JT, Martin TC, Gutierrez FR, Hartmann AF, Goldring D, Strauss AW. Spontaneous closure of secundum atrial septal defect in infants and young children. Am J Cardiol 1983; 52: 1267–1271.Google Scholar
Craig RJ, Selzer A. Natural history and prognosis of atrial septal defect. Circulation 1968; 37: 805–815.Google Scholar
Kirklin JW, Barratt-Boyes BG. Cardiac Surgery, 2nd edn. Churchill Livingstone, Edinburgh, 1993, pp 609–644.
Porter CJ, Feldt RH, Edward WD, Seward JB, Schaff HV. Atrial Septal Defect. In: Moss AJ, Adams FH (eds). Heart Disease in Infants, Children, and Adolescents Including the Fetus and Young Adults, 5th edn. Williams and Wilkins, Baltimore, 1995, pp 687.

Table 1.

The centiles for weight at the time of diagnosis of our 121 patients. Note that the distribution is skewed toward the lower centiles.
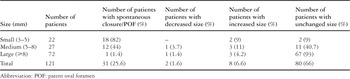
Table 2.

Table 3.

Kaplan-Meier curve showing the proportion of defects remaining open as a function of time according to their initial size for patients with small and medium defects.
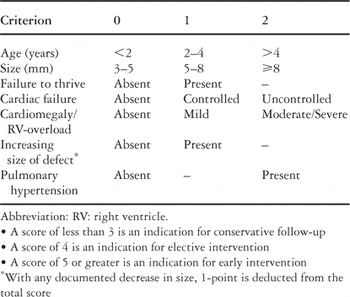
Table 4.
 You have
Access
- 24
- Cited by