Introduction
Bipolar disorder (BD) is characterized by mood regulation impairment, oscillating between persistently elevated or irritable mood and sustained periods of depressed mood (APA, 2013). Even between episodes, individuals with BD remain seriously symptomatic (Joffe et al. Reference Joffe, MacQueen, Marriott and Trevor Young2004) and exhibit significant mood lability (Aas et al. Reference Aas, Pedersen, Henry, Bjella, Bellivier, Leboyer, Kahn, Cohen, Gard, Aminoff, Lagerberg, Andreassen, Melle and Etain2014). Though sleep disturbances are among the most prominent correlates of mood episodes and inadequate recovery in BD (Harvey, Reference Harvey2008), it remains unclear how specific aspects of sleep physiology may relate to negative and positive mood dysregulation.
Disrupted sleep homeostasis is a hypothesized contributor to sleep and mood impairments in affective disorders (Borbely & Wirz-Justice, Reference Borbely and Wirz-Justice1982). Sleep homeostasis is a physiological sleep regulatory process defined by increasing pressure to sleep during extended wakefulness, followed by dissipating sleep intensity across the sleep period (Borbely et al. Reference Borbely, Daan, Wirz-Justice and Deboer2016). The amount of slow wave activity (SWA; EEG power density 0.75–4.75 Hz) during non-rapid eye movement (NREM) sleep is the best-characterized marker of sleep intensity (Borbely et al. Reference Borbely, Daan, Wirz-Justice and Deboer2016). The S-deficiency hypothesis of depression proposes that deficient build-up of sleep pressure and reduced sleep intensity (SWA) may produce or sustain depressed mood (Borbely & Wirz-Justice, Reference Borbely and Wirz-Justice1982). In accord with this hypothesis, SWA deficits and reduced visually-staged slow-wave sleep (SWS; NREM stage 3 and 4) are generally observed in unipolar depression relative to controls (See Armitage, Reference Armitage2007 for review). Moreover, selective SWS deprivation can have an antidepressant effect among unipolar depressed patients (Landsness et al. Reference Landsness, Goldstein, Peterson, Tononi and Benca2011; Cheng et al. Reference Cheng, Goldschmied, Casement, Kim, Hoffmann, Armitage and Deldin2015), which may be due to a ‘resetting’ of waking sleep pressure and greater SWA rebound the next night (Landsness et al. Reference Landsness, Goldstein, Peterson, Tononi and Benca2011). While the precise mechanisms linking SWA and depressed mood remain to be delineated, research suggests that increased sleep intensity may facilitate cortical plasticity in brain regions supporting a host of cognitive-affective processes implicated in affective disorders (Huber et al. Reference Huber, Maatta, Esser, Sarasso, Ferrarelli, Watson, Ferreri, Peterson and Tononi2008; Tononi, Reference Tononi2009).
SWA has been less extensively studied in BD. Only one study in bipolar depression (n = 8 per group) has measured SWA, reporting no differences relative to matched controls (Mendelson et al. Reference Mendelson, Sack, James, Martin, Wagner, Garnett, Milton and Wehr1987). However, studies assessing visually-staged sleep indicate lower SWS in bipolar depression relative to healthy adults, at levels akin to unipolar depression (Gillin et al. Reference Gillin, Duncan, Pettigrew, Frankel and Snyder1979; Linkowski et al. Reference Linkowski, Kerkhofs, Rielaert and Mendlewicz1986; Fossion et al. Reference Fossion, Staner, Dramaix, Kempenaers, Kerkhofs, Hubain, Verbanck, Mendlewicz and Linkowski1998; Asaad et al. Reference Asaad, Sabry, Rabie and El-Rassas2016). While no studies to date have selectively deprived SWS in bipolar depression, sleep deprivation also has antidepressant effects in bipolar depression and can induce (hypo)mania in a subset of cases (Benedetti & Colombo, Reference Benedetti and Colombo2011). SWS deficits in (hypo)mania may be comparable with depression (Linkowski et al. Reference Linkowski, Kerkhofs, Rielaert and Mendlewicz1986; Asaad et al. Reference Asaad, Sabry, Rabie and El-Rassas2016), though findings are inconsistent (Hudson et al. Reference Hudson, Lipinski, Frankenburg, Grochocinski and Kupfer1988). While altered SWS has not been observed in interepisode BD (Sitaram et al. Reference Sitaram, Nurnberger, Gershon and Gillin1982; Knowles et al. Reference Knowles, Cairns, MacLean, Delva, Prowse, Waldron and Letemendia1986; Eidelman et al. Reference Eidelman, Talbot, Gruber, Hairston and Harvey2010), one study reported that higher baseline SWS predicted greater mania symptom severity at 3-month follow-up (Eidelman et al. Reference Eidelman, Talbot, Gruber, Hairston and Harvey2010).
Overall, there is some support for SWS deficits in bipolar depression and (hypo)mania. This raises the possibility that BD patients, like their unipolar depressed counterparts, may be vulnerable to mood-related changes in sleep intensity. Initial prospective findings in interepisode BD, along with the well-documented antidepressant response to sleep deprivation, suggest that altered sleep intensity could play a role in generating or sustaining mood disturbance in BD. However, whether waking mood affects sleep intensity remains unclear. Initial experimental work in healthy adults suggests that pre-sleep affect may alter SWS (Talamini et al. Reference Talamini, Bringmann, de Boer and Hofman2013). Among those with affective disorders, who are more vulnerable to mood regulation impairments, it is important to disambiguate whether acute change in waking mood produces SWA deficits and/or whether deficient SWA maintains mood disturbances overnight. The interepisode phase of BD provides unique opportunity to experimentally probe such relationships.
The aim of the present study was to examine whether adults with interepisode BD experience experimentally-induced mood disruptions in SWA, and whether deficient SWA is related to impaired overnight mood regulation. This study involved further analysis of an existing dataset (Talbot et al. Reference Talbot, Hairston, Eidelman, Gruber and Harvey2009; Eidelman et al. Reference Eidelman, Talbot, Gruber, Hairston and Harvey2010). Adults with interepisode BD and healthy adult controls spent four nights in the sleep laboratory: one screening night, one neutral (baseline) mood induction night, one negative (sad) mood induction night, and one positive (happy) mood induction night. The first aim was to assess whether interepisode bipolar patients and healthy adults exhibited an overnight reduction in negative and positive mood following the sad and happy mood inductions, respectively. Due to documented mood regulation deficits in interepisode BD (e.g., Aas et al. Reference Aas, Pedersen, Henry, Bjella, Bellivier, Leboyer, Kahn, Cohen, Gard, Aminoff, Lagerberg, Andreassen, Melle and Etain2014), it was hypothesized that the bipolar group would exhibit a smaller overnight change in mood. The second aim was to evaluate the effects of the sad and happy mood inductions on SWA relative to baseline. Based on evidence of reduced SWA in depression and (hypo)mania, we predicted that SWA would be lower after both mood inductions relative to baseline in the bipolar group, but not in the control group. The final aim was to assess associations between SWA and overnight changes in mood on the sad and happy induction nights. We predicted that lower SWA would be associated with impaired overnight mood regulation in bipolar patients.
Methods
Participants
Participants included: 20 adults with interepisode DSM-IV-TR bipolar disorder type I (BD) and 23 healthy adult controls (CTL) with no history of psychiatric or sleep disorders. Participants were drawn from a larger protocol, results from which have been described in previous reports (e.g., Talbot et al. Reference Talbot, Hairston, Eidelman, Gruber and Harvey2009; Eidelman et al. Reference Eidelman, Talbot, Gruber, Hairston and Harvey2010). All procedures contributing to this work comply with the ethical standards of relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008. Inclusion criteria for all participants were: (a) negative for narcolepsy, sleep apnea (AHI > 5), restless leg syndrome or periodic limb movement disorder (PLMA > 15) on the basis of polysomnography; (b) met criteria for interepisode symptom cutoffs based on prior research (Chengappa et al. Reference Chengappa, Baker, Shao, Yatham, Tohen, Gershon and Kupfer2003; Thompson et al. Reference Thompson, Gallagher, Hughes, Watson, Gray, Ferrier and Young2005): a score of ⩽7 on the Young Mania Rating Scale (YMRS; Young et al. Reference Young, Biggs, Ziegler and Meyer1978) and a score of ⩽11 on the Inventory of Depressive Symptomatology-Clinician Rated (ISD-C; Rush et al. Reference Rush, Gullion, Basco, Jarrett and Trivedi1996); (c) had no history of severe head trauma, stroke, neurological disease, or severe medical illness. BD were included if they: (a) met DSM-IV-TR bipolar I disorder (American Psychiatric Association, 2000); (b) did not meet criteria for substance or alcohol abuse or dependence in the past 3 months; (c) were under the care of a psychiatrist. CTL could not meet DSM-IV-TR criteria for any lifetime Axis I disorder.
In order to be included in the present analysis, participants had to meet criteria for BD type I, and complete the baseline (neutral mood induction) and at least one mood induction (sad or happy) sleep recording. From the original sample (BD n = 28; CTL n = 28), four BD participants had BD type II. Additional participants were excluded on the basis of poor quality sleep recording/excessive EEG artifact on the baseline night (BD = 2; CTL = 4) or both mood induction nights (BD = 2, CTL = 1). For the sad induction night, additional participants were lost to dropout (BD = 1) or poor quality recordings (BD = 2; CTL = 2), leading to a total of 17 BD and 21 CTL participants for sad night analyses. Similarly, for the happy induction night additional participants were lost to dropout (BD = 1; CTL = 1) or poor quality recordings (BD = 3; CTL = 1), leading to a total of 16 BD and 21 CTL participants for happy night analyses.
Clinical functioning measures
Structured clinical interview for DSM-IV (SCID; First et al. Reference First, Spitzer, Gibbons and Williams1997)
DSM-IV-TR Axis I diagnoses were confirmed using the SCID.
Manic and depressive symptoms
Current symptoms of mania were measured using the 11-item, clinician rated Young Mania Rating Scale (YMRS; Young et al. Reference Young, Biggs, Ziegler and Meyer1978). Current symptoms of depression were assessed using the 30-item, clinician-rated Inventory of Depressive Symptomatology (IDS-C; Rush et al. Reference Rush, Gullion, Basco, Jarrett and Trivedi1996). YMRS (⩽7) and IDS-C (⩽11) scores were used to confirm current interepisode status (i.e., neither currently manic nor depressed) for both groups.
Illness course
BD course characteristics were assessed using a validated charting procedure (National Institute of Mental Health retrospective Life-Charting Methodology; Denicoff et al. Reference Denicoff, Smith-Jackson, Disney, Suddath, Leverich and Post1997; Leverich & Post, Reference Leverich and Post1997). Age of BD onset, illness duration, and the number of lifetime manic and depressive episodes were derived.
Medication tracking and dosage
Medication name and dosage were recorded at each visit. Medication effects were examined using an approach developed for neuroimaging research (Phillips et al. Reference Phillips, Travis, Fagiolini and Kupfer2008). Each medication was re-categorized by medication class, and dose was categorized as 0 (no medication), 1 (low), or 2 (high) based on published parameters and chlorpromazine-equivalent mean effective daily doses (Sackeim, Reference Sackeim2001; Davis & Chen, Reference Davis and Chen2004). A composite measure of medication load was created for each participant by summing across dosage strength codes and classes (Almeida et al. Reference Almeida, Akkal, Hassel, Travis, Banihashemi, Kerr, Kupfer and Phillips2009).
Sleep measures
Duke structured interview for sleep disorders (DSISD; Edinger et al. Reference Edinger, Bonnet, Bootzin, Doghramji, Dorsey, Espie, Jamieson, McCall, Morin and Stepanski2004)
The DSISD is a semi-structured interview that assesses research diagnostic criteria for sleep disorders; it has good reliability and validity (Edinger et al. Reference Edinger, Wyatt, Olsen, Stechuchak, Carney, Chiang, Krystal, Lineberger, Means and Radtke2009).
Polysomnography (PSG)
Sleep was recorded using overnight PSG with a Compumedics 802 Siesta system (Compumedics, Charlotte, NC). PSG involves the continuous and simultaneous recording of EEG, electrooculogram (EOG), and electromyogram (EMG) to score sleep. Recording channels included four EEG derivations (C3/A2, C4/A1, O1/A2, O2/A1), two EOG leads, and two submental EMG sensors. On the first overnight visit, heart rate, blood oxygen, nasal and oral air flow, thoracic and abdominal effort, and leg motion were monitored. PSG data were staged in 30-second epochs using standard Rechtscaffen & Kales criteria (Rechtschaffen, Reference Rechtschaffen1968).
Power spectral analysis
Sleep EEG analyses were performed offline in MATLAB R2011b (Mathworks, Natick, MA) and EEGLAB11 (http://sccn.ucsd.edu/eeglab/). Power spectral analysis was carried out in accordance with published methods (van der Helm et al. Reference van der Helm, Yao, Dutt, Rao, Saletin and Walker2011). EEG channels were re-referenced to the average of the left and right mastoid (A1, A2), run through high-pass (0.5 Hz) and low-pass (55 Hz) Finite Impulse Response (FIR) filtering, and split into 5-second epochs. EEG recordings were visually inspected for 5-second epochs containing muscle, cardiac and eye-movement artifacts; artifact-laden epochs were manually rejected. Power spectral density (μV2/Hz) was calculated using a Fast Fourier Transform (FFT) on each hamming-windowed 5-second epoch at 128 Hz, yielding a frequency resolution of 0.2 Hz. FFT results were sorted according to sleep stage and averaged across NREM (stages 2–4). NREM SWA was defined as integrated power in the 0.75–4.75 Hz range. Relative SWA (expressed as a percentage) was derived by dividing SWA by the integrated power of the entire spectrum. For each night, values ±3.0 standard deviations were Winsorized (<1% of all data). Relative SWA derived from the central EEG derivation C4 was used for hypothesis testing.
Mood ratings
Affect grid
The affect grid (Russell et al. Reference Russell, Weiss and Mendelsohn1989) is a self-report rating of pleasure on the horizontal axis (–4 = extremely unpleasant, 0 = neutral, 4 = extremely pleasant) and arousal on the vertical axis (–4 = extremely low arousal, 0 = neutral, 4 = extremely high arousal); it has adequate reliability and validity (Russell et al. Reference Russell, Weiss and Mendelsohn1989).
Mood induction
The mood induction technique was adapted from well-validated procedures (Albersnagel, Reference Albersnagel1988; Eich et al. Reference Eich, Macaulay and Ryan1994; Stein et al. Reference Stein, Goldman and Del Boca2000; Williams et al. Reference Williams, Healy, Eade, Windle, Cowen, Green and Durlach2002) that combine continuous music with autobiographical recall. For the happy and sad mood inductions, participants were told that they would listen to a selection of music to assist them in developing a happy (or sad) mood, and then were then instructed to try hard to develop an intense mood state by concentrating on ideas and images that make them feel happy (or sad). For the neutral induction, participants were asked to focus on neutral topics (e.g., directions to a familiar place or the layout of furniture at home) while listening to the classical music. See Supplementary methods regarding music selection.
Procedure
At the first laboratory visit, participants completed written informed consent. Participants were then administered the SCID, DSISD, YMRS, IDS-C, and life chart to assess diagnostic status, symptom severity, and clinical course. Eligible participants were provided with an instruction sheet for the day prior to subsequent overnight laboratory visits; these included: (1) restrict caffeine intake to <2 cups coffee (or equivalent) before noon and (2) refrain from taking over-the-counter medications.
For all overnight visits, participants arrived at the laboratory 2 hours prior to their habitual bedtime. Overnight visit eligibility was then assessed by a clinician, including compliance with overnight instructions, medication use, and interepisode status using the YMRS and IDS-C. If YMRS or IDS-C scores exceeded interepisode cut-offs, a safety assessment was completed before the participant was sent home (without completing the overnight). Overnight visits were each approximately 2 weeks apart; some participants did not complete all visits (see Supplementary procedures for details).
At the first overnight, participants underwent full clinical polysomnography to assess for sleep disorders (e.g., sleep apnea, PLMD). At the three subsequent overnight visits, mood inductions were administered. A neutral mood induction was administered at the second overnight visit, and then the order of the happy and sad inductions was counterbalanced between the third and fourth overnight visits. In order to reduce demand effects, participants were told that they were engaging in two different experiments at these visits, a music study and a sleep study.
At each mood induction overnight visit (neutral, sad, happy), PSG equipment was first attached, followed by the mood induction administration in a private room. During mood inductions, participants rated their current affect, pleasure, and arousal at baseline, and every 5 min thereafter, using a computerized version of the Affect Grid. The neutral mood induction was 15 min for all participants and there was no mood cut-off at the end. Affect Grid mood thresholds of at least -3 (pleasure) for the sad induction and +3 (pleasure) for the happy induction were set based on previous methods (Eich et al. Reference Eich, Macaulay and Ryan1994). Mood inductions ended at these thresholds, or at 40 min after the start of the induction. The final Affect Grid of the mood induction was used as the pre-sleep (post-induction) measure. Immediately after the mood induction, participants were escorted to the laboratory bedroom and allowed to sleep. Participants were awakened at the time they requested (approx. 9:00 am at the latest). To mitigate the effects of sleep inertia upon morning mood reports, participants completed the Affect Grid roughly 20 min after awakening. Participants were debriefed at the end of their last visit.
Analytic approach
Analyses were conducted in SPSS 20.0 (IBM Corporation, Somers, NY, 2012). Affect Grid pleasantness ratings were used to evaluate mood just prior to each mood induction (pre-induction), at the end of each mood induction (post-induction) and the morning following the mood induction (morning). A 2 (Group; BD v. CTL) × 3 (Time; pre-induction, post-induction, morning) repeated-measures analysis of variance (ANOVA) was conducted for each the sad and happy mood inductions. Overnight mood change was evaluated using a difference score (morning – post-induction affect grid pleasantness rating).
The effect of pre-sleep sad and happy mood inductions on SWA was examined using a series of 2 (Night; neutral v. sad or happy mood induction) × 2 (Group; BD v. CTL) repeated-measures ANOVA models. The neutral mood induction was used as a baseline night. As a few individuals did not complete both the happy and sad mood induction overnights, separate ANOVAs compared each mood induction (sad, happy) to baseline, to maximize statistical power.
In each group, spearman's rho correlation analyses evaluated whether SWA on the sad or happy mood induction nights was associated with overnight mood change (morning – post-induction affect grid pleasantness ratings) that same night.
On an exploratory basis, we conducted an analysis with sleep architecture variables paralleling the main sleep aims. Exploratory spearman rho correlations were also conducted to examine effects of illness course characteristics (see Supplemental results), pre-sleep arousal, and medication load on SWA. The significance level was set at p < 0.05 (two-sided) for all analyses.
Results
Baseline demographic and clinical characteristics
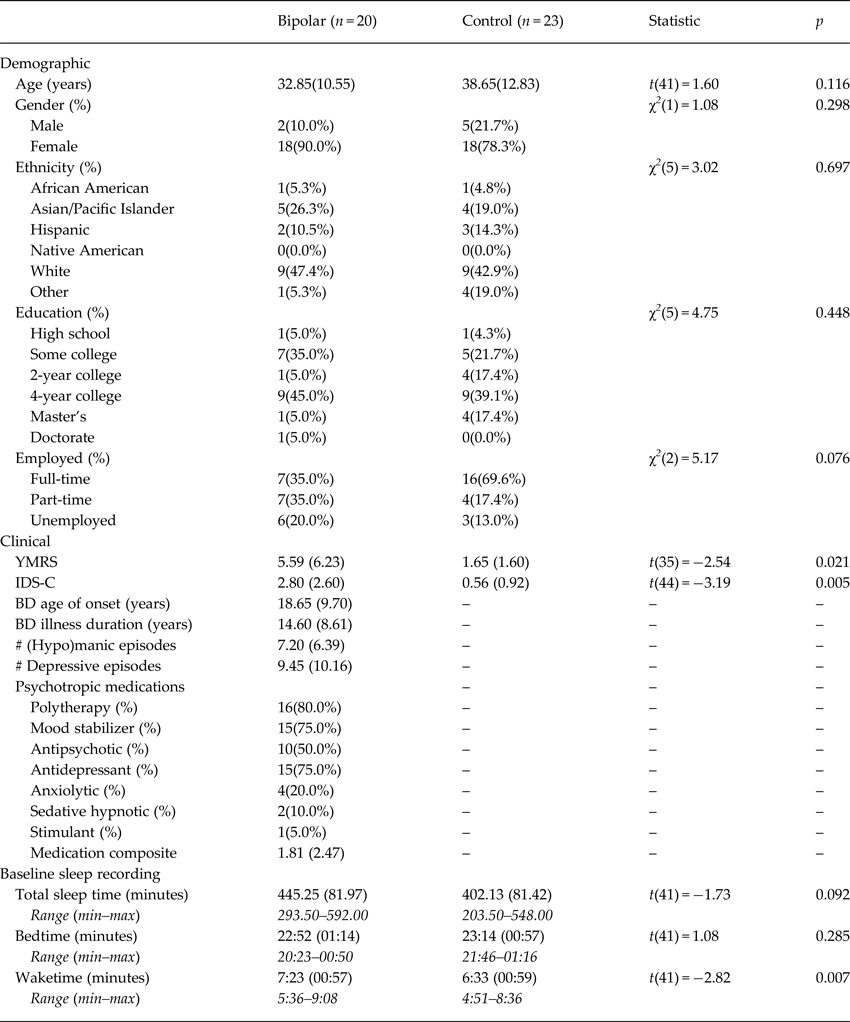
The two groups did not significantly differ on any sociodemographic characteristics (Table 1). While BD exhibited significantly higher baseline manic and depressive symptoms (ps < 0.05), scores were well below established interepisode cut-offs. Baseline (neutral induction night) bedtime and sleep duration sleep did not significantly differ between groups, though waketime was later in BD than CTL (p < 0.05). Spearman correlation analyses assessed whether age, sex, depressive or manic symptoms scores were meaningfully associated with any mood or sleep EEG outcomes. No significant correlations emerged; therefore, these variables were not included as covariates in subsequent analyses.
Sociodemographic and clinical characteristics by diagnostic group

Note. Mean values are displayed with standard deviations in parentheses where applicable; BD, bipolar disorder; YMRS, young mania rating scale; IDS-C, inventory of depressive symptoms-clinician rated.
Sad mood induction
Overnight mood regulation
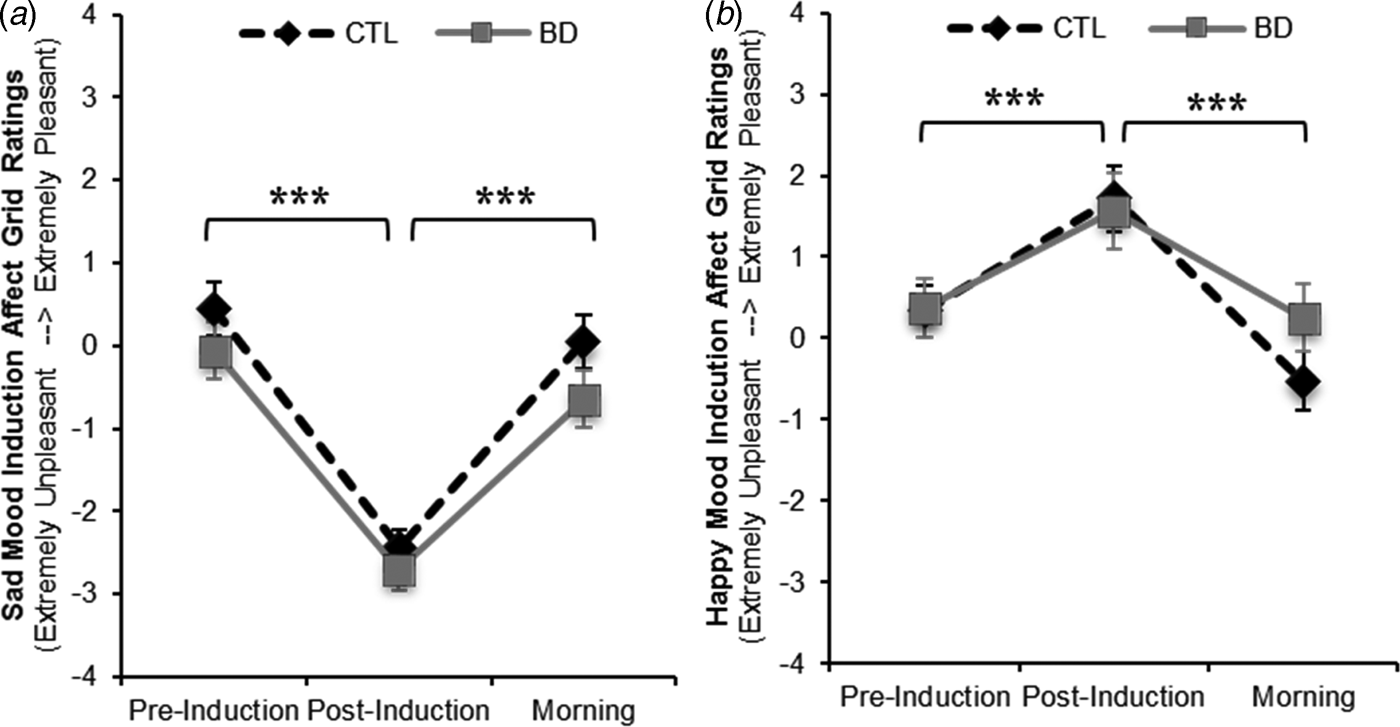
There was neither a significant main effect of Group, F(1,36) = 2.61, p = 0.115, nor a significant Group × Time interaction effect, F(1,36) = 0.44, p = 0.513, on affect grid mood ratings across the sad mood induction overnight (Fig. 1a ). However, there was a significant main effect of Time, F(1, 36) = 92.70, p < 0.001. Posthoc paired samples t tests confirmed a significant increase in negative mood from pre- to post-mood induction, t(36) = 9.68, p < 0.001, and a significant overnight decrease in negative mood from post-induction to morning, t(36) = −8.15, p < 0.001.
Affect grid pleasantness ratings for BD and CTL groups on the (a) sad mood induction and (b) happy mood induction nights, assessed at the beginning of the mood induction (Pre-Induction), at the end of the mood induction (Post-Induction) and upon awakening the following morning (Morning). BD, bipolar disorder group (sad night N = 17; happy night N = 16); CTL, healthy control group (sad night N = 21; happy night N = 21); *p < 0.05, **p < 0.01, ***p < 0.001.

Mood induction effects on SWA
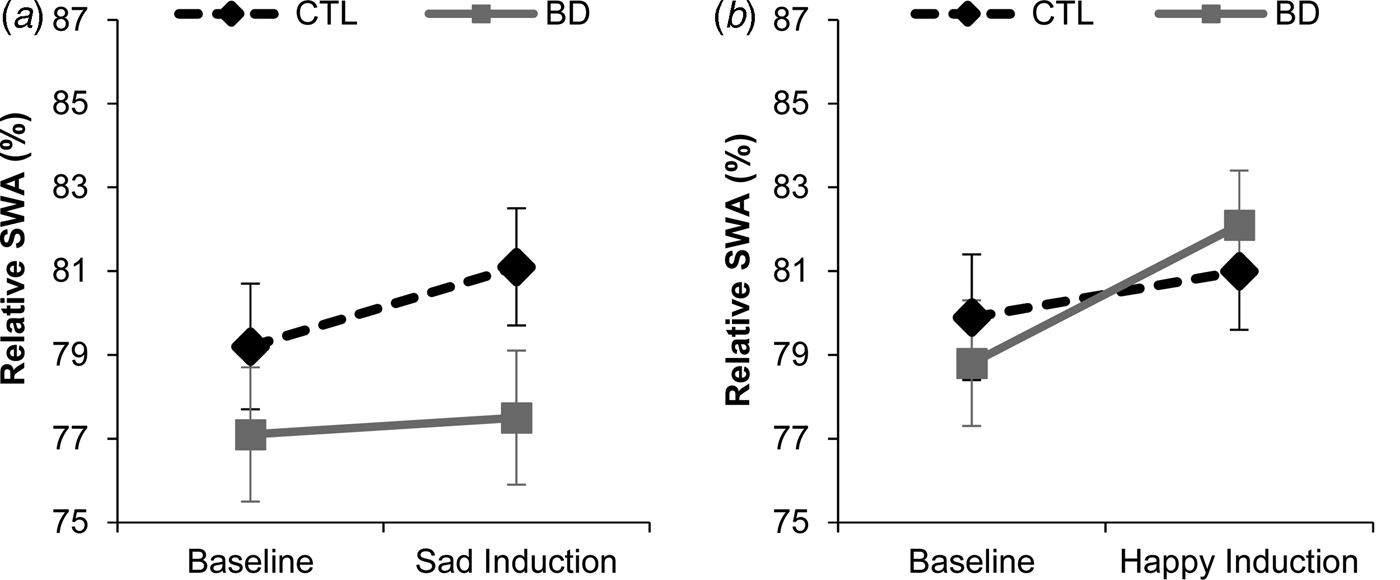
Figure 2a illustrates SWA means on the baseline and sad mood induction overnights. There were no significant effects SWA across Group, F(1,36) = 2.27, p = 0.140, Night, F(1,36) = 1.13 p = 0.295, or Group × Night, F(1,36) = 0.42, p = 0.520.
Mean relative slow wave activity (SWA) on the baseline night relative to the (a) sad mood induction and (b) happy mood induction nights. Baseline night was the neutral mood induction night. Baseline night means differ slightly between the sad and happy mood induction analysis since a few individuals did not participate in both mood induction nights. BD, bipolar disorder group (sad night N = 17; happy night N = 16); CTL, healthy control group (sad night N = 21; happy night N = 21); *p < 0.05, **p < 0.01, ***p < 0.001.

SWA-overnight mood regulation associations
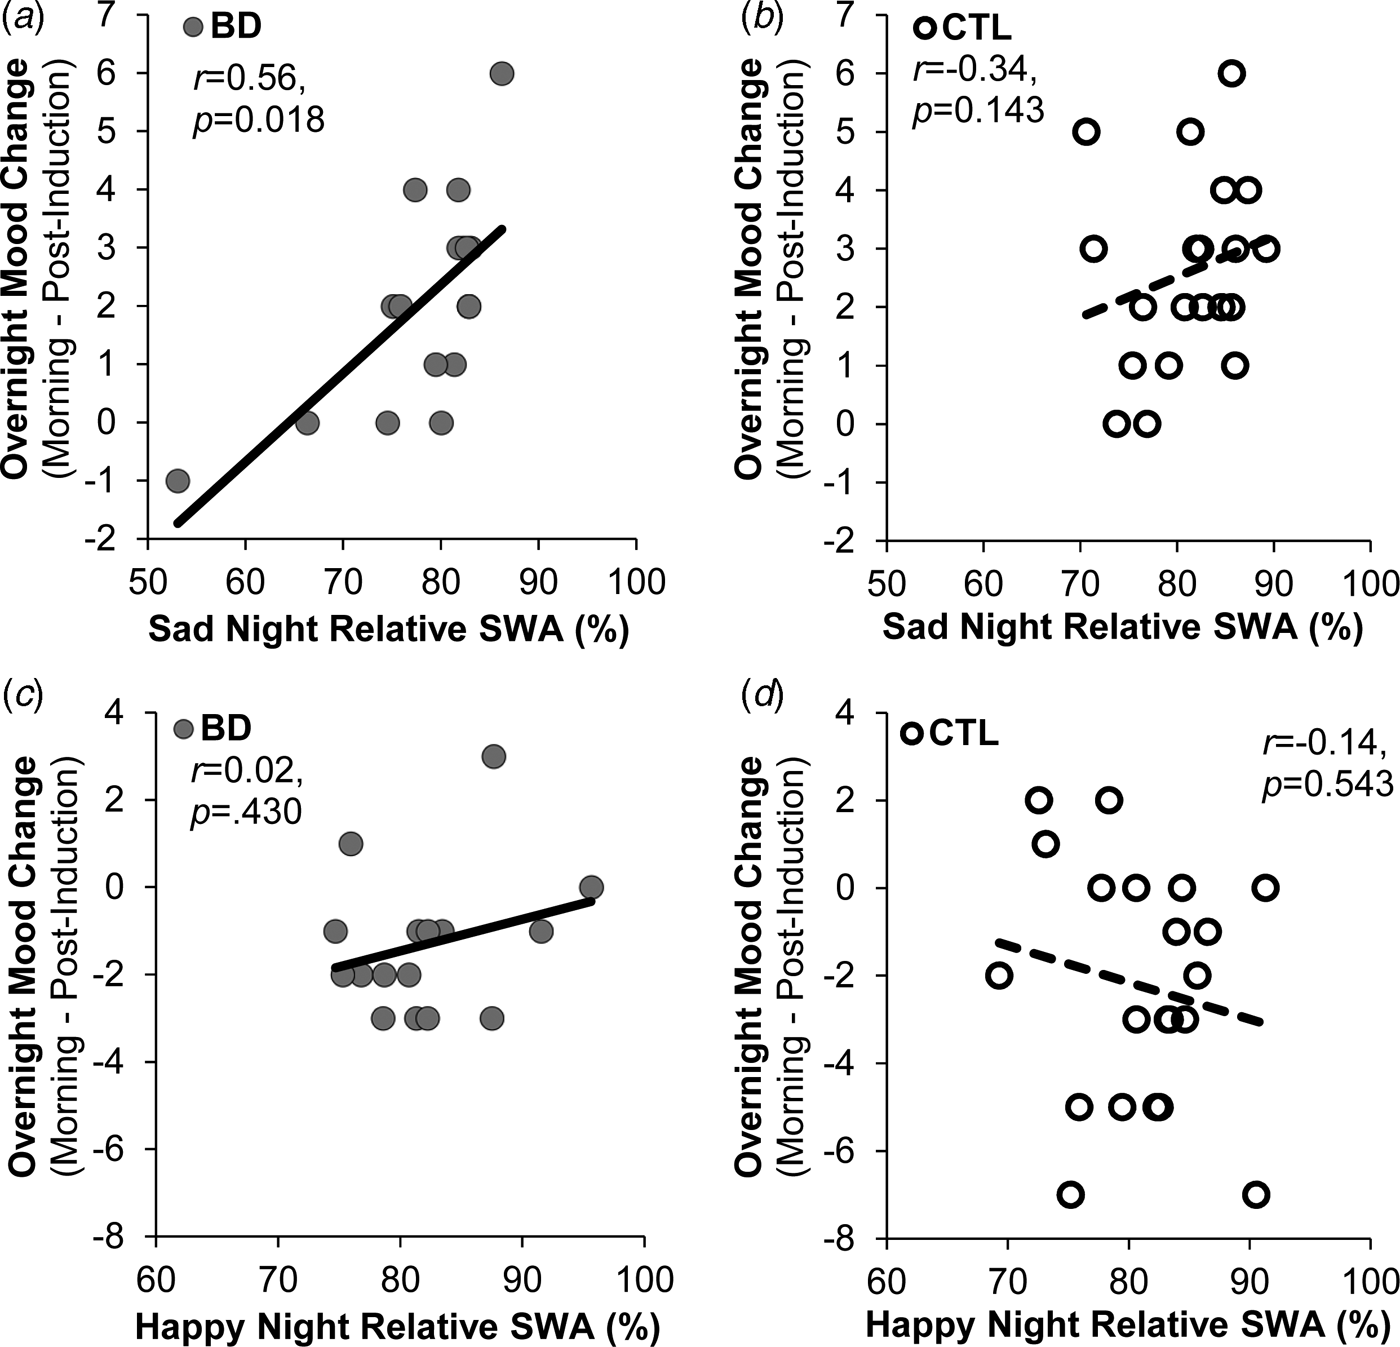
Sad mood induction night SWA positively correlated with overnight mood change on the affect grid (r = 0.56, p = 0.018; Fig. 3a ) in BD such that higher SWA was related to greater improvement in negative mood; this association was not observed in CTL (r = 0.34, p = 0.143; Fig. 3b ).
Overnight mood change on the affect grid pleasantness ratings plotted as a function of SWA for BD and CTL groups on the sad mood induction night (a, b) and happy mood induction night (c, d). BD, bipolar disorder group (sad night N = 17; happy night N = 16); CTL, healthy control group (sad night N = 21; happy night N = 21).

Happy mood induction
Overnight mood regulation
There was neither a significant main effect of Group, F(1, 41) = 0.32, p = 0.575, nor a significant Group × Time interaction effect, F(1,35) = 0.92, p = 0.343, on mood ratings across the happy mood induction overnight (Fig. 1b ). There was a significant main effect of Time, F(1, 35) = 27.61, p < 0.001. Posthoc paired samples t tests confirmed a significant increase in positive mood from pre- to post-mood induction, t(36) = −4.79, p < 0.001, and a significant overnight reduction in positive mood from post-induction to morning, t(36) = 4.80, p < 0.001.
Mood induction effects on SWA
Figure 2b shows SWA on the baseline and happy mood induction overnights. There was a significant main effect of Night, F(1,35) = 5.64, p = 0.023, whereby SWA increased on the happy mood induction night relative to baseline in both groups. Effects of Group, F(1,35) = 0.00, p = 0.996, and Group × Night, F(1,35) = 1.25, p = 0.271, were non-significant.
Sleep architecture
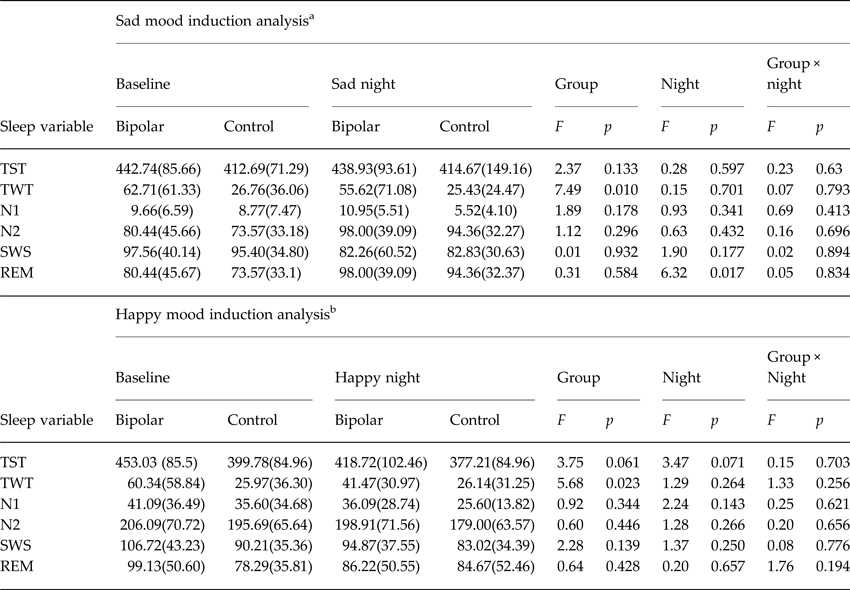
Table 2 reports results from repeated measures ANOVAs evaluating sleep architecture variables (TST, TWT, N1, N2, SWS, REM) on the neutral v. happy or sad induction nights. Baseline night means differ slightly between the sad and happy mood induction nights since a few individuals did not participate in both mood nights and a repeated measures analysis of variance excludes a participant if there is missing data on any of the observation points. Baseline sleep architecture has been described in previous reports from the full sample (Talbot et al. Reference Talbot, Hairston, Eidelman, Gruber and Harvey2009; Eidelman et al. Reference Eidelman, Talbot, Gruber, Hairston and Harvey2010). There were no significant effects of Group, Night or Group × Night for TST, N1, N2, or SWS (all p > 0.05). There was a Group effect for TWT, such that BD had greater TWT than CTL at baseline relative to both the sad night and happy nights (both p < 0.05). There was a main effect of Night for sad night REM sleep relative to baseline, such that both groups had greater REM relative to baseline (p < 0.05). Sleep architecture variables did not correlate with overnight mood change on the sad or happy nights (all p > 0.05) with the exception of SWS. Paralleling SWA findings, sad night SWS was positively correlated with overnight negative mood change in BD (r = 0.61, p = 0.009), but not CTL (r = −0.27, p = 0.259).
Sleep architecture on the mood induction nights

Note. Mean (standard deviation) are presented. Units are minutes for all variables. TST, total sleep time; TWT, total wake time; N1, NREM stage 1; N2, NREM stage 2; SWS, slow wave sleep or NREM Stages 3 and 4.
a Bipolar n = 17, Control n = 21.
b Bipolar n = 16, Control n = 21.
Pre-sleep arousal ratings
No significant differences were observed between BD and CTL on post-induction affect grid arousal ratings for the sad (−1.41 v.. −1.55; t(35) = −0.23, p = 0.822) and happy mood induction nights (−0.81 v. −0.33; t(35) = −0.61, p = 0.543). Post-induction arousal ratings did not correlate with SWA on the mood induction nights for either group (ps > 0.05).
Medication effects
In BD, medication load did not significantly differ between baseline v. the sad (4.29 v. 4.12; F(1,16) = 1.31, p = 0.269) and happy mood induction nights (4.44 v. 4.38; F(1,15) = 0.14, p = 0.718). Medication load and SWA were not significantly correlated on the baseline and sad mood induction nights (ps > 0.05). Higher medication load correlated with lower happy night SWA at a trend level (r = −0.45, p = 0.083).
Discussion
This study tested relationships between overnight mood regulation impairment, sleep intensity (indexed by SWA), and interepisode BD diagnosis. Findings included that: (1) overnight mood regulation in interepisode BD did not significantly differ from healthy adults, (2) inducing a positive mood state prior to sleep increased SWA relative to baseline across all participants, and (3) lower SWA was associated with attenuated overnight regulation of negative mood, but not positive mood, in bipolar patients.
Taking findings from the sad mood induction first, the prediction that the bipolar group would exhibit impaired overnight mood regulation was not supported. Both the bipolar and control groups exhibited intact overnight mood regulation, with negative mood prior to sleep generally regularizing to a neutral rating by the morning. This is consistent with previous research indicating that negative mood typically improves overnight in healthy adults (Cartwright et al. Reference Cartwright, Luten, Young, Mercer and Bears1998, Reference Cartwright, Baehr, Kirkby, Pandi-Perumal and Kabat2003). Impaired mood regulation in interepisode BD might only be evident after shorter spans of time during waking hours, though to our knowledge this question has not yet been systematically investigated. The present findings indicate that overnight mood regulation capabilities in interepisode BD may generally be comparable with healthy adults.
The sad mood induction did not have differential effects on SWA across the two groups. However, lower SWA on the sad mood induction night was related to attenuated overnight improvement in negative mood for bipolar patients only. This coheres with predictions of the S-deficiency hypothesis (Borbély, Reference Borbély1982), which proposes that deficient SWA may sustain depressed mood. Exploratory sleep architecture analyses further support this notion; lower sad night SWS also correlated with impaired overnight negative mood regulation in BD. A lack of correlation with REM sleep and other NREM stages suggest a specific role for sleep intensity (SWA/SWS) in overnight regulation of negative mood, consistent with prior reports (Cheng et al. Reference Cheng, Goldschmied, Casement, Kim, Hoffmann, Armitage and Deldin2015). These results raise the possibility that slow-wave deficits in BD might sustain negative mood overnight.
Predictions for the happy mood induction night were generally not supported. On average, positive mood state prior to sleep decreased to a neutral rating by morning for both groups, thus the bipolar group did not exhibit impaired overnight mood regulation relative to controls. Also contrary to our hypothesis, both groups exhibited increased SWA following the happy mood induction. Positive affect has previously been observed to be beneficial for sleep quality and efficiency in some studies (Steptoe et al. Reference Steptoe, O'Donnell, Marmot and Wardle2008; Ong et al. Reference Ong, Exner-Cortens, Riffin, Steptoe, Zautra and Almeida2013), though this is the first study to our knowledge that has explored the effects of positive mood on SWA. Finally, there was no significant association between SWA and overnight change in positive mood. The absence of a statistically significant relationship between SWA and overnight change in positive mood, in the presence of both positive mood-induced SWA changes and a reduction in positive mood from night to morning, raises the possibility that SWA may not be driving overnight change in positive mood. Perhaps overnight changes in positive v. negative mood are driven by different sleep-wake regulatory mechanisms. Tightly controlled forced desynchrony and constant routine protocols have determined that there is a circadian pattern in positive affect (Boivin et al. Reference Boivin, Czeisler, Dijk, Duffy, Folkard, Minors, Totterdell and Waterhouse1997; Murray et al. Reference Murray, Allen and Trinder2002), while there is less evidence for a clear 24-hr rhythm in negative affect (Boivin et al. Reference Boivin, Czeisler, Dijk, Duffy, Folkard, Minors, Totterdell and Waterhouse1997). Thus, overnight change in positive mood may primarily be modulated by circadian, rather than homeostatic, factors.
Overall, these results may indicate differing associations between mood state and SWA. Though sad mood did not induce changes in SWA, lower SWA correlated with attenuated overnight improvement in negative mood in BD, adding to existing literature supporting the relevance of sleep homeostatic mechanisms for negative mood regulation. There was greater inter-individual variation in sad night SWA among BD (Fig. 3A , B ). Inter-individual differences in vulnerability to SWA disruption, and its impact on negative mood, may be linked to genetic susceptibility to affective disorders. For example, PER3 polymorphisms more prevalent in affective disorders are also related to inter-individual differences in homeostatic sleep pressure (Artioli et al. Reference Artioli, Lorenzi, Pirovano, Serretti, Benedetti, Catalano and Smeraldi2007; Dallaspezia et al. Reference Dallaspezia, Locatelli, Lorenzi, Pirovano, Colombo and Benedetti2016). Conversely, the happy mood induction led to increased SWA relative to baseline in both groups, but SWA was uncorrelated with overnight change in positive mood. Effects of positive mood on central and peripheral physiology (Shiota et al. Reference Shiota, Neufeld, Yeung, Moser and Perea2011; Admon & Pizzagalli, Reference Admon and Pizzagalli2015) may acutely bolster SWA, separate from circadian mechanisms proposed to govern 24-hr fluctuation in positive mood. Relevant to depression, and other psychiatric conditions with SWA deficiencies (e.g., schizophrenia; Hoffmann et al. Reference Hoffmann, Hendrickse, Rush and Armitage2000), increasing pre-sleep positive mood may be means of enhancing SWA, as an alternative to sleep deprivation. However, further work is necessary to delineate the potentially distinct physiological mechanisms underpinning links between negative and positive mood with SWA.
While a key strength of this study is its unique combination of experimental mood manipulation with repeated within-subject PSG sleep assessments in BD, several limitations merit consideration. Only central sleep EEG derivations were analyzed. SWA deficits can be more pronounced in prefrontal and frontal areas (Werth et al. Reference Werth, Achermann and Borbely1997; Plante et al. Reference Plante, Landsness, Peterson, Goldstein, Riedner, Wanger, Guokas, Tononi and Benca2012), thus future studies of sleep in BD would benefit from utilizing hdEEG to explore topographic hypotheses. Sex differences in SWA are sometimes observed in unipolar depression, with some reports observing greater SWA in females (e.g., Plante et al. Reference Plante, Landsness, Peterson, Goldstein, Riedner, Wanger, Guokas, Tononi and Benca2012). While sex differences in SWA were not observed here, this may be due to the predominantly female sample and resulting lack of power to detect sex effects. Prior sleep and wakefulness also impact SWA (Borbély & Achermann, Reference Borbély, Achermann, Kryger, Roth and Dement2000). As this study was not initially designed to assess SWA, participants were not instructed to keep a regular sleep-wake schedule before sleep monitoring; future studies should address this design limitation. This was a medicated sample of bipolar participants. Though medication load was not significantly associated with overnight mood change, medication could be affecting sleep physiology. Because this study was conducted across a span of several months, an unmedicated sample would be unfeasible and unsafe. More broadly, research on severe mental illness would be seriously hindered and lack generalizability if done in only medication-free samples (Phillips et al. Reference Phillips, Travis, Fagiolini and Kupfer2008). The present findings remain clinically important given that the vast majority of BD patients are medicated.
In summary, the present findings provide preliminary support for a relationship between mood and sleep intensity (indexed by SWA) in interepisode BD. Lower SWA was associated with impaired overnight regulation of pre-sleep negative mood in BD, but not in controls. Pre-sleep positive mood increased SWA in both groups relative to baseline, though SWA was not related to overnight change in positive mood. The present findings suggest a potential interplay between mood and sleep intensity that may carry relevance for the management of mood dysregulation and sleep-wake disturbances in interepisode BD.
Supplementary Material
The supplementary material for this article can be found at https://doi.org/10.1017/S0033291717001581.
Acknowledgements
This research was supported by National Institute of Mental Health (A.S., grant numbers K01MH111953, T32MH089919, T32MH018269), (A.H., R34MH080958), (M.W., R01MH9353).
Conflict of interest
None.