Introduction
Outbreaks of pneumonia caused by Legionella species are a well-recognized public threat, with transmission usually occurring through the inhalation of aerosolized droplets from contaminated water sources, such as cooling towers and showers. Reference Diederen1 Transmission via aspiration has rarely been reported. Reference Blatt, Parkinson and Pace2–Reference Mohamed, Zielinski and Diedhiou4 Point-of-use cold water dispensers (PCWDs) can utilize several purification systems to improve the quality and taste of drinking water supplied by public water systems. Activated carbon water filters are widely used to improve taste and odor by removing chlorine and organic compounds. Reference Wu, Cao, Tong, Finkelstein and Hoek5 Chlorine, among other compounds, plays a significant role in providing safe and clean water by disinfecting pathogens, including Legionella species. Reference Martin, Harrison and Proctor6
We present the investigation of hospital-acquired Legionella infection in our institute’s hematology department.
Patient 1
An 80-year-old woman was diagnosed as having diffuse large B-cell lymphoma (DLBCL) two years earlier. She initially underwent six cycles of R-CHOP (Rituximab, Methotrexate, Procarbazine, and Vincristine) chemotherapy, achieving remission. Following relapse began treatment with lenalidomide, tafasitamab, and intermittent corticosteroid therapy.
She was admitted to the hematology ward due to generalized weakness, difficulty in oral hydration, and hypercalcemia (16.1 mg/dl), which were managed with hydration and steroid therapy. On the tenth day, she developed fever of up to 39.3°C, respiratory symptoms, and hypoxemia requiring oxygen support. Her pancytopenia worsened (Hb 9.1 g/dl, WBC 1.02 * 10^3/UL, PLT 109 * 10^3/Ul) and elevated CRP (35.3 mg/dl). Chest imaging revealed diffuse left alveolar infiltrates. A nasal PCR multiplex assay identified Legionella pneumophilia, and pneumonia resolved following treatment with azithromycin.
Patient 2
Shortly after the first patient, a second patient, a 69-year-old man, was diagnosed as having DLBCL just days before his current admission. He began treatment with R-CHOP, complicated by tumor lysis syndrome requiring dialysis. Nine days after admission, he developed fever (38.1 °C), respiratory symptoms, and hypoxemia, necessitating noninvasive respiratory support. Chest imaging revealed bilateral infiltrates. He also had worsening pancytopenia (Hb 7.8 g/dl, WBC 0.16 * 10^3/Ul, PLT 11 * 10^3/Ul) and elevated CRP (28.34 mg/dl). Blood cultures were negative, and a nasal PCR multiplex assay identified Legionella pneumophila. The patient required intensive care, was treated with azithromycin, responded well to therapy, and was discharged after prolonged hospitalization.
Epidemiological investigation
In response to these events which occurred 10 days apart, an epidemiological investigation was conducted. An extensive number of samples were collected from different water sources throughout the ward, including shower heads, water taps, and air-conditioning conduits, and we also sampled the family lounge which is physically outside of the ward. Moreover, patients and their families were questioned about their exposures during their stay, revealing the extensive use of the PCWD located in the family lounge by both patients for drinking cold water as this was the only such device on the floor. The investigation also revealed that the first patient was unable to ambulate during her hospitalization; therefore, she did not enter the lounge herself; however, her family routinely brought her cold water from the PCWD in the patient lounge as the water “tasted better.”
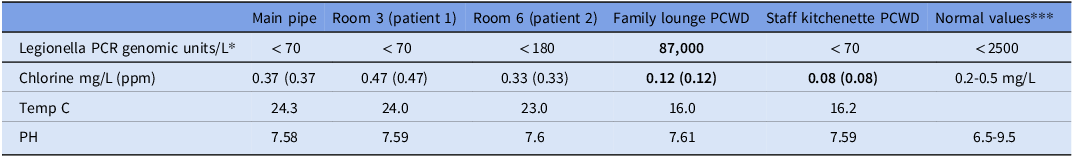
Samples were tested for Legionella PCR genomic units/L (equivalent to colony-forming units), water temperature, pH, and chlorine levels. We found that all water samples were within the acceptable range of PCR genomic units (<2,500), 7 except for the family lounge PCWD sample. In addition, we found acceptable chlorine levels in all samples except for those in the PCWD (Table 1). In Table 1, we provide the results for the patient’s rooms (3 and 6) and the main pipe of both PCWD in the ward. All other samples collected from the ward were normal. Additionally, samples were collected from the central source of hot water for the building and the floor, as well as from the central source of two other departments located in different buildings.
The results of water sampling in the hematologic ward during the investigation are presented

* Genomic units (GUs) are equivalent to colony-forming units (CFUs).
**Specimens were analyzed in an outside lab authorized by the Ministry of Health according to ISO/IEC 17025 using the BIOTECON Diagnostics dedicated Legionella kit.
***Normal values provided by the correlates with the public health regulations provided by the Ministry of Health. 10
Following the identification of Legionella in PCWD, we used genomic sequencing to compare the Legionella samples identified in PCWD and patient samples. The sample closely matched the nasal sample taken from patient number two (six out of seven genes were consistent with Legionella pneumophila serogroup 1, strain 1). Owing to the corruption of patient 1’s sample, we were unable to perform genomic sequencing for patient 1. The PCWD was connected to the main cold-water line, and water passed through a carbon-based filter and was then held in a 5-liter water reservoir that was cooled to 16 °C and dispensed cold water upon demand via a nozzle. Maintenance records revealed that the device was several years old; however, the carbon-based water filter device was changed regularly every 6 months according to the manufacturer’s instructions, and the cold-water reservoir was never drained or disinfected, as these were not part of the routine maintenance of the device.
Discussion
This report describes a cluster of nosocomial Legionella pneumophila pneumonia in two immunocompromised hematology patients traced to a PCWD in a family lounge. The evidence suggests that infection probably occurred via microaspiration while drinking rather than by the aerosolized route. Legionella pneumophila is a well-recognized pathogen in healthcare settings because of its ability to colonize and persist in water systems. Healthcare-associated infections usually occur when susceptible individuals inhale aerosolized particles containing bacteria. Reference Ashbolt8 However, these reports, as well as others, highlight that aspiration during drinking may serve as an underappreciated route of transmission, especially in high-risk patients. Reference Blatt, Parkinson and Pace2,Reference Bencini, Yzerman, Koornstra, Nolte, den Boer and Bruin9 In our cluster, both patients had significant risk factors for aspiration (advanced age, hematologic malignancy, chemotherapy, and altered sensorium or oral intake), which likely facilitated infection through this route.
Environmental investigation identified a markedly elevated Legionella load and reduced chlorine concentration in the implicated dispenser compared to all other water sources in the ward. The PCWD utilized an activated carbon filter changed every 6 months, as recommended by the manufacturer, which improved taste but also reduced residual chlorine. Its cold-water reservoir was never disinfected or drained, creating a favorable environment for bacterial proliferation. These findings underscore the potential for certain water purification systems, particularly those that store water for prolonged periods at suboptimal temperatures, to become reservoirs for Legionella, even in situations where regular maintenance is performed as recommended by the manufacturer.
This cluster calls for the re-evaluation of infection prevention strategies in high-risk hospital settings. In addition to established measures targeting aerosol-generating devices, routine monitoring of water quality, including chlorine levels and microbial contamination, should be extended to all PCWD. Hospital policies should ensure that devices serving immunocompromised populations utilize purification technologies that do not compromise their microbiological safety.
In Israel, as in other developed countries, there are no specific guidelines for the maintenance of PCWD in hospitals and high-risk populations. As a result of the investigation, all PCWD were removed from high-risk wards, and bottled water was provided pending the installation of a safer PCWD that does not reduce chlorine levels in the water.
Our investigation is limited by the matching of genotype to a single patient and the small number of patients. Nonetheless, the strong epidemiological link, environmental findings, and genotyping provide compelling evidence of a common source of infection in this outbreak.
In conclusion, aspiration of contaminated drinking water from PCWD represents an underappreciated risk factor for nosocomial Legionella infection in vulnerable patient populations. Regular surveillance and provision of appropriate water quality for high-risk patients are critical, and hospitals should be aware of the potential harms of using PCWD devices.
Acknowledgments
None.
Financial support
No funding or sponsorship was received for the publication of this study.
Competing interests
All authors declare no COI.