Introduction
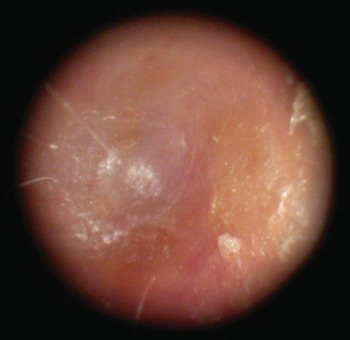
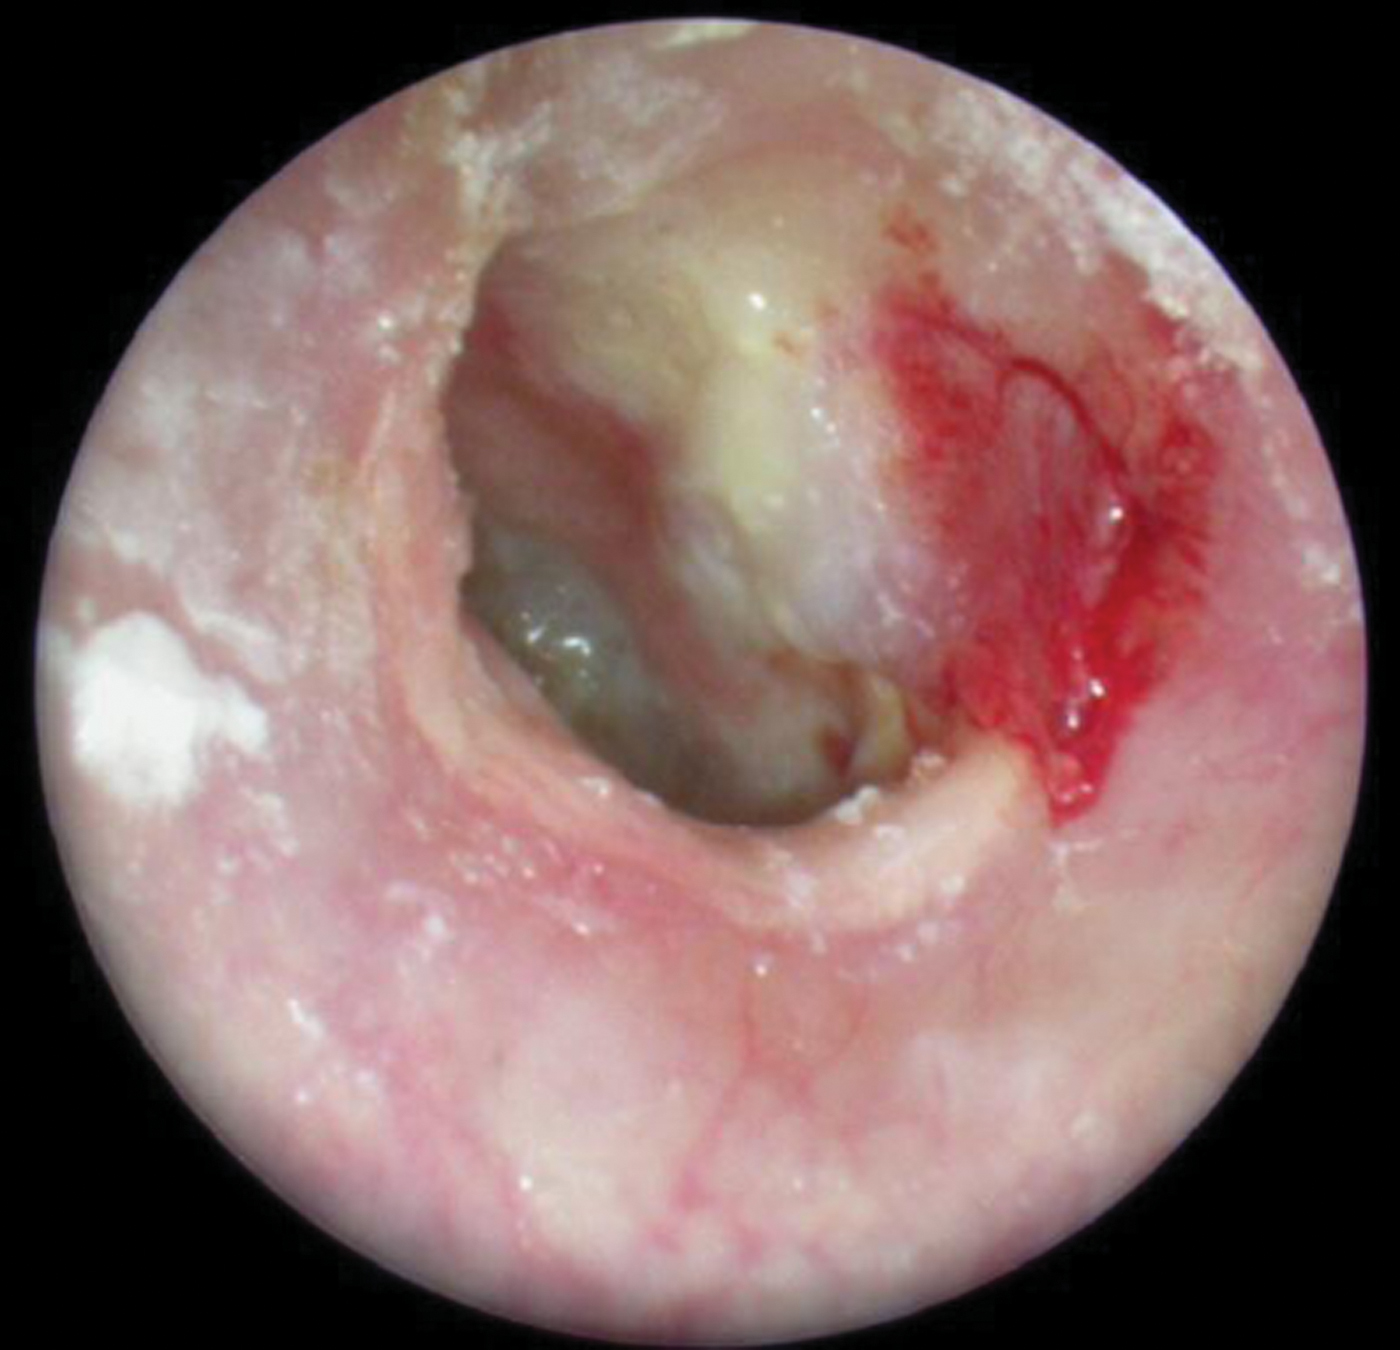
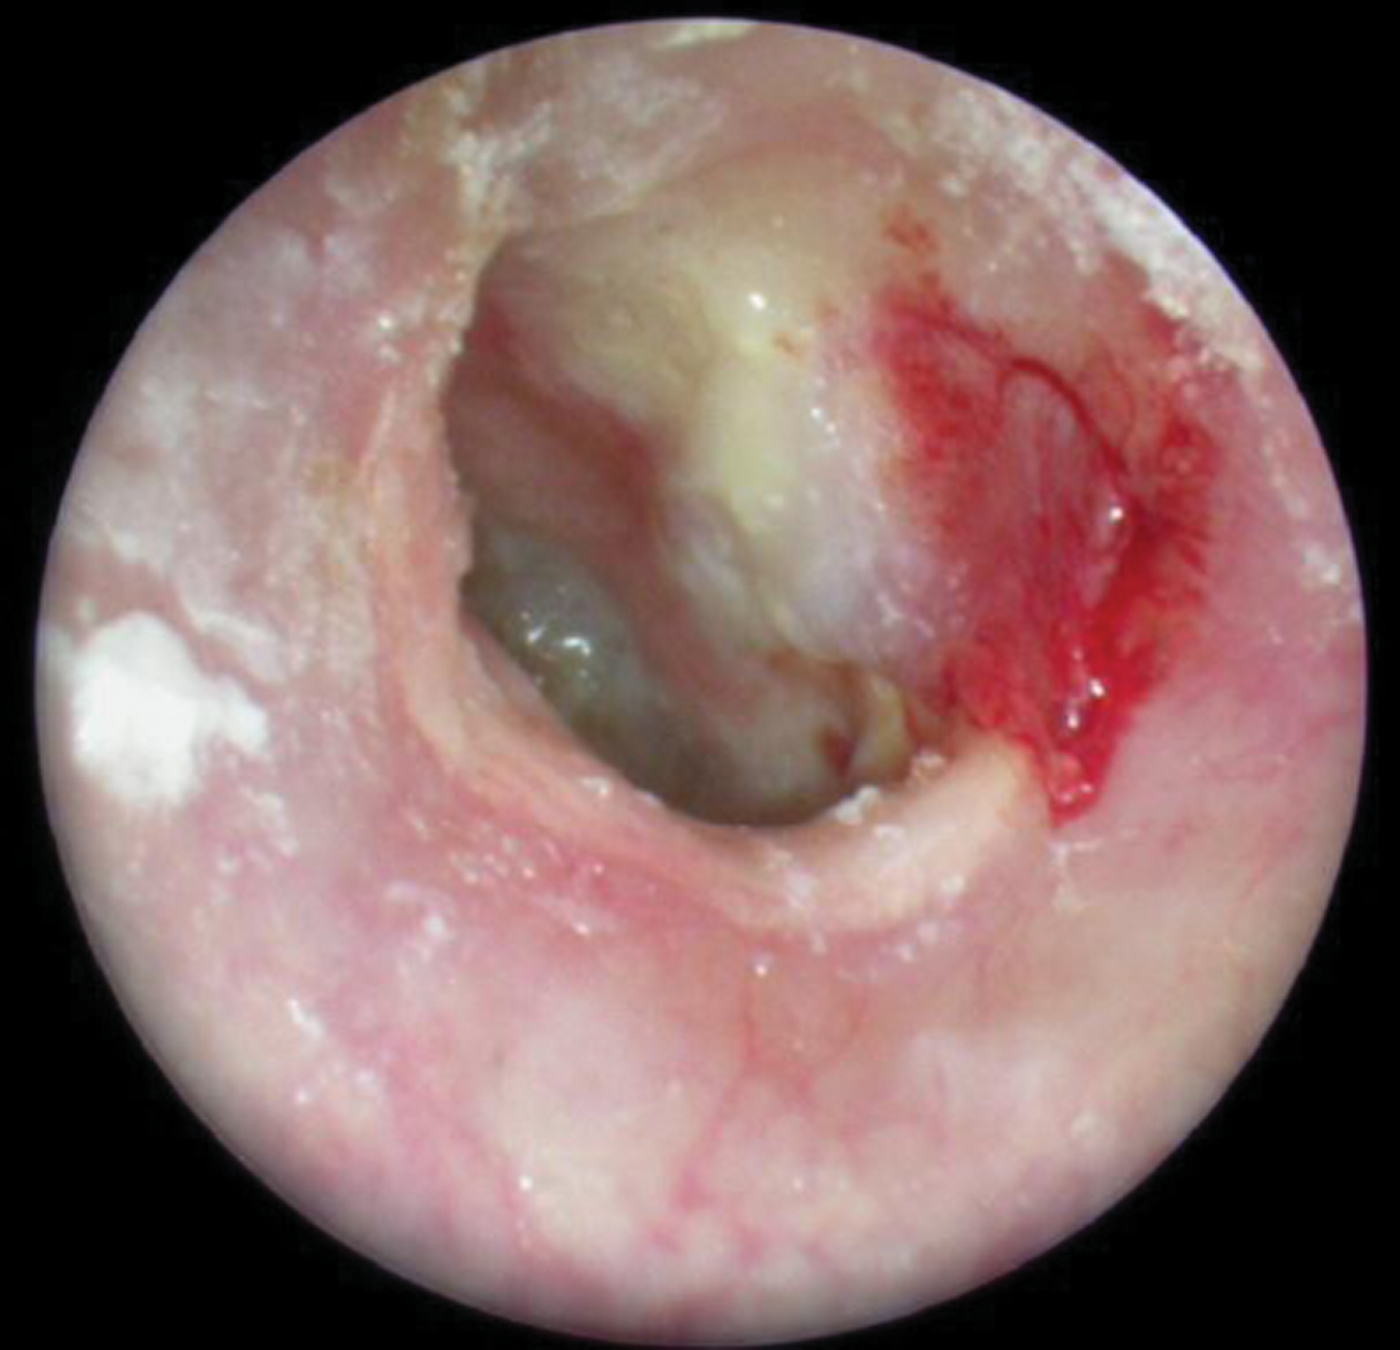
Chronic obliterative otitis externa is an uncommon clinicopathological entity with an estimated incidence of 0.6 per 100 000.Reference Becker and Tos1 It is characterised by chronic inflammation of the external auditory canal leading to irreversible subepithelial fibrosis and narrowing of the lumen.Reference Roland2 Frequently, the condition becomes refractory to out-patient medical treatment, with increasing stenosis of the canal leading to a conductive hearing loss (Figure 1).
Endoscopic view of blind-ending ear canal secondary to obliterative otitis externa.

Canalplasty aims to widen or restore patency to the ear canal. Over the years, a multitude of different techniques have been described in the literature with variable degrees of success.Reference Selesnick, Nguyen and Eisenman3
We present here a series of canalplasties carried out by the senior author with split-skin grafting of the denuded canal and great emphasis on meticulous after-care.
Materials and methods
Patients
Case notes were examined for all patients with a diagnosis of chronic obliterative otitis externa and an operative code for canalplasty with split-skin grafting, who were under the care of the lead author between 2000 and 2008. Patients with osteomata, exostoses or simple meatoplasty were excluded, leaving a total of 14 patients (8 male and 6 female) and 16 ears (8 left and 8 right). All patients underwent pre-operative computed tomography scanning to exclude significant middle-ear pathology.
The operations were all carried out by the lead, senior author, at the Radcliffe Infirmary or the John Radcliffe Hospital, Oxford. No specific ethical considerations were involved as this procedure was established practice for the condition studied.
Outcome measures
The two principal outcome measures studied were the Glasgow Benefit Inventory and the difference between pre- and post-operative audiometric hearing thresholds. The number of visits to the aural care service was also recorded as a measure of post-operative morbidity; comparison with pre-operative visits was not possible because several of the patients were tertiary referrals from other departments.
The Glasgow Benefit Inventory is a validated, post-intervention questionnaire designed to assess changes in quality of life of a patient following an operation or intervention.Reference Robinson, Gatehouse and Browning4 The questionnaire comprises 18 questions with a total score of between −100 (maximal negative effect) and +100 (maximal benefit), and may be split into subscales of general benefit, social support and physical health. In our study, questionnaires were completed during a telephone interview of the patient conducted by an independent assessor blinded to any other procedural or follow-up details.
The pure tone average hearing threshold (at 0.5, 1, 2 and 4 kHz) was calculated for each ear prior to and following each operation, and any hearing change calculated. A calibrated audiometer was used, following procedures recommended by the British Society of Audiology.
Operative technique
The operative ear was prepared with aqueous povidone-iodine solution, and the postauricular skin infiltrated with lignocaine 2 per cent with 1:80 000 adrenaline.
A postauricular incision was made and the canal skin transected lateral to the stenotic segment, allowing circumferential flap elevation.
A generous temporalis fascia graft was then harvested for later use.
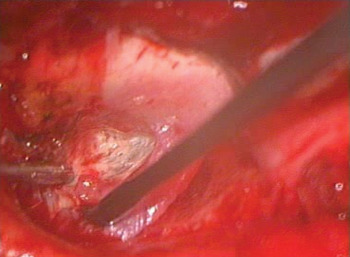
The fibrous tissue of the stenotic segment was debulked by a lateral to medial dissection off the bony canal. Eventually, the cleavage plane between the fibrous layer of the tympanic membrane and the scar tissue was reached (Figure 2).
Surgical photograph showing development of a cleavage plane between the middle fibrous layer of the tympanic membrane and the medial canal fibrosis.

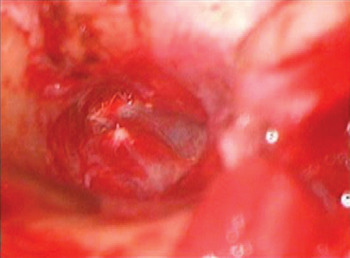
The dissection continued radially, stripping the outer squamous layer from the tympanic membrane until the umbo was freed and the scar tissue completely removed. The lateral process of the malleus and the umbo were commonly adherent to the fibrous tissue, and sharp dissection with a vitrectomy knife was often necessary to avoid perforation of the tympanic membrane. A generous bony meatoplasty was then carried out to fully expose the annulus (Figure 3).
Surgical photograph showing the denuded canal and tympanic membrane visibly free of disease.

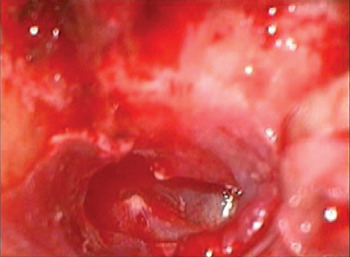
A temporalis fascial graft was placed over the exposed canal bone to facilitate skin grafting, but not over the tympanic membrane (Figure 4). A split-skin graft (0.5 mm in thickness) was harvested from the upper arm and cut into thin strips on paraffin gauze dressing before being draped longitudinally over the temporalis fascia (the gauze dressing remaining superficial). One long strip was draped superiorly along the roof of the canal to extend over the denuded tympanic membrane (Figure 5).
Surgical photograph showing placement of a generous temporalis fascia graft to cover the bony canal.

Surgical photograph showing split-skin grafts overlaying the temporalis fascia and tympanic membrane. The canal is now ready for packing.

The canal was packed with Merogel (Medtronic, Fridley, Minnesota, USA) soaked in ciprofloxacin drops, and the incision closed with absorbable sutures. Patients were generally discharged home the day after surgery, having been given a comprehensive information sheet.
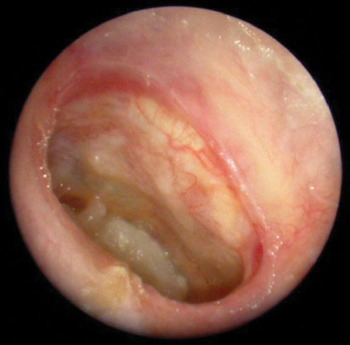
The pack was left in place for 3 weeks, with daily topical application of ciprofloxacin drops, before being removed by the aural care service. Further visits to the aural care service took place at increasing intervals, with gradual removal of the paraffin gauze dressing as the underlying grafts ‘took’ (Figure 6).
Endoscopic view 3 months after surgery.
Areas of granulation were treated topically with Triadcortyl cream (triamcinolone acetonide, neomycin sulphate, gramicidin and nystatin; Squibb, Uxbridge, UK), and recurrent fibrosis with mometasone furoate topical steroid (Elocon; Schering-Plough, Welwyn Garden City, UK). Aluminium acetate solution was also used as an astringent.
The new canal epithelium was non-migratory, so regular removal of desquamated debris was required in the long term for many patients (Figure 7).
Endoscopic view 6 months after surgery.

Results and analysis
Statistics
The normality of all variables was assessed both formally (using the Shapiro–Wilk test) and informally (looking at the data distribution on a histogram). The data did not deviate greatly from a normal distribution, and hence mean values, standard deviations and t-tests were used for comparisons and summaries.
Demographics
We studied a total of 16 operated ears (8 left and 8 right) in 14 patients (8 men and 6 women). Five patients had only incomplete stenosis of the external canal. The mean patient age at surgery was 58 years (range, 25 to 71 years) and the mean follow-up duration was 2 years 11 months (range, 3 months to 7 years). Five patients were discharged from follow up after a mean period of 2 years 7 months.
Hearing
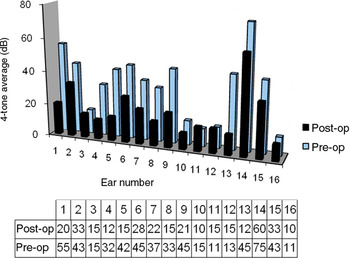
Figure 8 shows each patient's pre- and post-operative four-tone average hearing threshold. Overall, 3 months after surgery the patients' four-tone average hearing threshold had improved by a mean of 13.9 dB (95 per cent confidence interval (CI), –9.9 to 37.8 dB; t < 0.001). All 11 ears with complete stenosis showed an improvement in four-tone average hearing threshold (mean improvement, 20.2 dB; 95 per cent CI, 3.3–37.1 dB; t < 0.001). There was no significant change in hearing in the 5 ears with incomplete stenosis (t = 0.92).
Individual patients' pre-operative (pre-op) and post-operative (post-op) audiometric hearing thresholds.

Three months after surgery, the air–bone gap was below 20 dB in all operated ears.
Glasgow Benefit Inventory
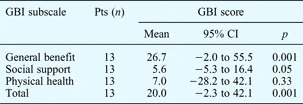
Thirteen of the 14 patients were successfully contacted for a telephone interview, by an independent agent (Table I). Glasgow Benefit Inventory scores were calculated.
Glasgow benefit inventory results

GBI = Glasgow Benefit Inventory; Pts = patients; CI = confidence interval
Two patients had a negative score, both of whom had experienced complications.
However, the overall means and their confidence intervals were strongly indicative of an overall improvement in quality of life following the procedure, with the possible exception of the physical health domain.
Aural care
The 5 patients discharged from follow up made an average 14 visits to the aural care service. The total study population had an average of 15 visits (range, 2 to 40). In those still receiving follow-up care, the mean interval between visits was 72 days.
A single patient required a myringoplasty for persistent post-operative perforation.
At the time of writing, one patient was awaiting bone-anchored hearing aid implantation after recurrent infection.
Discussion
Despite the apparent clinical simplicity of chronic obliterative otitis externa,Reference Herdman and Wright5 the literature is needlessly complicated by the proliferation of terms used in its description. It has also been described as acquired atresia of the external auditory meatus,Reference Jacobsen and Mills6 postinflammatory medial meatal fibrosis,Reference Katzke and Pohl7 postinflammatory medial canal fibrosis,Reference el-Sayed8 postinflammatory acquired atresia of the external auditory canal,Reference Bonding and Tos9 traumatic external auditory canal atresiaReference McKennan and Chole10 and simply stenosis of the external auditory canal.Reference McDonald, Facer and Clark11 There is obviously a spectrum of severity and a variety of aetiologies of the inflammatory reaction, but the underlying finding of a plug of fibrous tissue adjacent to the tympanic membrane in the medial canal is the essential feature of this clinicopathological entity.
Chronic, diffuse, low-grade infection of the external ear commonly gives rise to subepithelial infiltration of inflammatory cells and oedema. Aggressive medical management may arrest the condition at this stage,Reference Roland2 before fibrosis and irreversible stenotic change in the deep canal develop, necessitating surgical intervention for the underlying conductive hearing loss. Underlying chronic suppurative otitis media, use of a hearing aid and surgical trauma may predispose to disease progression,Reference McCary, Kryzer and Lambert12 and it has recently been shown that radiotherapy to the parotid bed may also contribute.Reference Carls, Mendenhall, Morris and Antonelli13 In our series, all patients appeared to have an infective aetiology for their canal obliteration, although the canal was still at least partially patent in 5 cases.
The first reported case series, treated by radical mastoidectomy, was published as long ago as 1950,Reference Work14 and the basic surgical principles were elucidated in 1966.Reference Paparella and Kurkjian15 Paparella and KurkjianReference Paparella and Kurkjian15 stated that excision of the fibrous plug, enlargement of both bony and cartilaginous canals, and adequate epithelial coverage of the bony canal were all essential for success. Their early adoption of staged split-skin grafting met with poor results; hence, grafting is now performed at the time of initial surgery.
Surgical exposure may be achieved via an endaural,Reference Katzke and Pohl7, Reference Tos and Bonding16 postauricularReference Cremers17, Reference Birman and Fagan18 or combined approach.Reference Parisier and Bent19 We favour the excellent exposure of bony landmarks afforded by the postauricular approach, allowing for a generous bony canalplasty. The dictum of Fisch states that the entire fibrous annulus should be visible through a speculum in one microscope position, and we believe this can be best achieved using the postauricular approach, particularly as regards the important area of the anterior tympanomeatal recess.
Complete excision of the cicatrix would appear crucial to success, but partial resection of an inferior wedge of the plug has been attempted,Reference Soliman, Fatt-Hi and Abdel Kadir20 with ‘satisfactory’ results in 80 per cent of patients after 6 weeks of stenting of the canal with a rubber tube.
Skin coverage may be achieved by meatal flaps, regional flaps and skin grafts. Proponents of local flaps suggest that the presence of appropriate apocrine and sebaceous glands and excellent vascularity are essential to maintain the unique anatomy of the region.Reference Dhooge and Vermeersch21 Contracture of the flaps in the long term will also tend to widen the canal. However, hairs and glandular elements are not present in the deep canal, and there are inherent problems with flap length and bulk. Thus, a huge variety of flaps has been reported: superiorly based preauricularReference Adkins and Osguthorpe22 or conchal bowl;Reference Wolfensberger, Hilger and Hilger23 posteriorly based;Reference Chang, Min, Kim and Koh24 both anteriorly and posteriorly based;Reference Bell25 superiorly based conchal skin;Reference Martin-Hirsch and Smelt26 inferiorly based posterior meatal;Reference Banerjee, Moir, Jervis and Narula27 and flaps based on the middle temporal artery.Reference Lavy and Fagan28
Others have suggested preservation of a skin bridge in the canal to promote healing by epithelial migration.Reference Sharp, Oakley and Padgham29, Reference Leek30 Allowing the canal to heal by secondary intentionReference Proud31 is no longer considered acceptable in terms of patient morbidity and long-term results.
It has been claimed that the cortical bone of the external canal is a very poor environment for split-skin grafting;Reference Dhooge and Vermeersch21 however, success rates of 95 per cent have been reported.Reference Spector, Sobol and Thawley32 There is a single case reportReference Moore, Moore, Yonkers and Nissen33 of successful use of a full-thickness graft in an institutionalised patient, in whom durability of the graft was a major concern. However, split-skin grafting from the inner arm gives a thin, pliable graft with excellent handling properties.Reference McCary, Kryzer and Lambert12 Preparation of the canal wall with a smoothing diamond burr and a layer of temporalis fascia appears to aid graft placement.
We believe that post-operative care is an oft-neglected component of successful surgery for chronic obliterative otitis externa. The availability of expert aural care nurses is critical to overall success, to ensure regular inspection of the healing canal and aggressive treatment of areas of granulation and graft failure. In our series, the presence of 2 patients with ongoing discharge problems skewed our results somewhat. However, our patient average of 15 visits to the aural care service prior to discharge, and the average interval of 72 days between visits, demonstrate the need for adequate provision in this respect.
In the largest similar series reported,Reference Becker and Tos1 comprising 53 ears, the recurrence rate was 11 per cent at a median follow up of 5 years, and closure of the air–bone gap to less than 20 dB was achieved in 90 per cent of patients initially (although this dropped to 61 per cent over time). Other studies have reported air–bone gap closure to less than 20 dB in 94 per cent,Reference Cremers and Smeets34 81 per centReference Tos and Balle35 and 64 per centReference Jacobsen and Mills6 of post-operative cases, although all these proportions appeared to diminish with time.
Published restenosis rates vary from 9 to 27 per centReference Becker and Tos1, Reference McDonald, Facer and Clark11, Reference Birman and Fagan18, Reference Soliman, Fatt-Hi and Abdel Kadir20, Reference Cremers and Smeets34, Reference Slattery and Saadat36 according to the technique and length of follow up. In our series, at the time of writing we had encountered only one case of restenosis, amongst the 16 ears studied (6 per cent). This occurred after a mean follow-up period of 2 years 1 month; 3 months after re-operation, the patient's air–bone gap had closed to less than 20 dB.
• Chronic obliterative otitis externa is rare
• Subepithelial fibrosis and stenosis can cause significant hearing loss
• Many surgical approaches are described; long-term outcomes are rarely reported
• Here, circumferential excision and split-skin and temporalis fascia canal grafting are described
• With meticulous after-care, improved hearing and quality of life are achievable
Our patients' Glasgow Benefit Inventory scores would appear to suggest a significant overall benefit from the described procedure, despite its requirement for intensive and prolonged follow up.
Conclusion
Chronic obliterative otitis externa is a rare condition characterised by subepithelial fibrosis and stenosis of the external ear canal. If conservative therapy fails, significant conductive hearing loss may occur.
A variety of surgical approaches have been described, but long-term success rates have rarely been reported. The described technique involves circumferential excision of the disease and split-skin and temporalis fascia grafting of the canal. Meticulous post-operative care is necessary to ensure good outcomes.
The presented findings indicate that improvements in both hearing and quality of life are achievable in this condition.