INTRODUCTION
The relationship between depressive symptoms and cognition has received increased attention in recent cognitive aging literature. Depressive symptoms are less frequent in older adults compared with younger adults (Fiske, Wetherell, & Gatz, Reference Fiske, Wetherell and Gatz2009; Hasin, Goodwin, Stinson, & Grant, Reference Hasin, Goodwin, Stinson and Grant2005). However, at higher levels of endorsement, they are linked to cognitive decline, greater functional disability, and mortality (Blazer, Reference Blazer2003; Ganguli, Snitz, Vander Bilt, & Chang, Reference Ganguli, Snitz, Vander Bilt and Chang2009; Lockwood, Alexopoulos, & van Gorp, Reference Lockwood, Alexopoulos and van Gorp2002; Wilson et al., Reference Wilson, Barnes, Mendes, Agarwal, Schneider, Bach and Bennett2002). It remains unclear whether the association of depressive symptoms and cognitive function is due to a common cause, such as underlying cerebrovascular pathology; whether depressive symptoms appear in a reaction to the onset of cognitive decline (Steffens et al., Reference Steffens, Otey, Alexopoulos, Butters, Cuthbert, Ganguli and Yesavage2006), or whether depressive symptoms simply exacerbate cognitive impairment (Horwath, Johnson, Klerman, & Weissman, Reference Horwath, Johnson, Klerman and Weissman1992; Jorm, Reference Jorm2001; Ownby, Crocco, Acevedo, John, & Loewenstein, Reference Ownby, Crocco, Acevedo, John and Loewenstein2006). Causal and temporal explanations of the relationship between depression and cognition have spurred interest in examining depressive symptoms at varying levels of severity, particularly among non-depressed people who endorse few or very mild depressive symptoms.
In depressed older adults, poorer cognition has been reported in the domains of executive functioning, verbal memory, learning, and processing speed in comparison to healthy controls (Austin, Mitchell, & Goodwin, Reference Austin, Mitchell and Goodwin2001; Boone et al., Reference Boone, Lesser, Miller, Wohl, Berman, Lee and Palmer1994; Comijs, Jonker, Beekman, & Deeg, Reference Comijs, Jonker, Beekman and Deeg2001; Nebes et al., Reference Nebes, Butters, Mulsant, Pollock, Zmuda, Houck and Reynolds2000; Stoudemire, Hill, Morris, Martino-Saltzman, & Lewison, Reference Stoudemire, Hill, Morris, Martino-Saltzman and Lewison1993). Depressive symptoms that fall below clinical diagnostic criteria are often described as subthreshold or subsyndromal (Cohen, Magai, Yaffee, & Walcott-Brown, Reference Cohen, Magai, Yaffee and Walcott-Brown2005; Pincus, Davis, & McQueen, Reference Pincus, Davis and McQueen1999) and are shown to predict cognition (Dotson, Resnick, & Zonderman, Reference Dotson, Resnick and Zonderman2008; Elderkin-Thompson et al., Reference Elderkin-Thompson, Kumar, Bilker, Dunkin, Mintz, Moberg and Gur2003; Lichtenberg, Ross, Millis, & Manning, Reference Lichtenberg, Ross, Millis and Manning1995; Ravdin, Mattis, & Lachs, Reference Ravdin, Mattis and Lachs2004). Subsyndromal and subthreshold phenomenology studies with significant or primarily African American representation have provided some cross-sectional and longitudinal evidence of depressive symptoms and cognition associations yet vary in the extent of neuropsychological measures used (Adams & Moon, 2009; Burt, Zembar, & Niederehe, 1995; Cohen et al., Reference Cohen, Magai, Yaffee and Walcott-Brown2005; Wilson, Mendes De Leon, Bennett, Bienias, & Evans, 2004).
Despite evidence of higher lifetime major depression disorder (MDD) prevalence rates among Whites in comparison to African Americans and Hispanics in epidemiological and community-based samples (Blazer, Landerman, Hays, Simonsick, & Saunders, Reference Blazer, Landerman, Hays, Simonsick and Saunders1998; Kessler et al., Reference Kessler, Berglund, Demler, Jin, Koretz and Merikangas2003), African Americans tend to have greater chronicity of depressive symptoms (Williams et al., Reference Williams, Gonzalez, Neighbors, Nesse, Abelson, Sweetman and Jackson2007). Greater chronicity of depressive symptoms coupled with higher prevalence of vascular disease among African Americans over 65 in comparison to other racial groups (Roger et al., Reference Roger, Go, Lloyd-Jones, Benjamin, Berry, Borden and Turner2012) could amplify susceptibility to cognitive decline, cognitive impairment, and dementia risk (Barnes, Alexopoulos, Lopez, Williamson, & Yaffe, Reference Barnes, Alexopoulos, Lopez, Williamson and Yaffe2006; Fillenbaum, Peterson, Welsh-Bohmer, Kukull, & Heyman, Reference Fillenbaum, Peterson, Welsh-Bohmer, Kukull and Heyman1998; Ogunniyi et al., Reference Ogunniyi, Hall, Gureje, Baiyewu, Gao, Unverzagt and Hendrie2006; Tang et al., Reference Tang, Cross, Andrews, Jacobs, Small, Bell and Mayeux2001; Unverzagt et al., Reference Unverzagt, Gao, Baiyewu, Ogunniyi, Gureje, Perkins and Hendrie2001).
It is not well established whether minimal endorsement of depressive symptoms, routinely recognized as non-clinically relevant, is related to performance in specific cognitive domains in older African Americans. Because depressive symptoms often go undetected in African Americans (Gallo, Rabins, Lyketsos, Tien, & Anthony, Reference Gallo, Rabins, Lyketsos, Tien and Anthony1997; Lebowitz et al., Reference Lebowitz, Pearson, Schneider, Reynolds, Alexopoulos, Bruce and Parmelee1997; Miller et al., Reference Miller, Malmstrom, Joshi, Andresen, Morley and Wolinsky2004), it is important to examine whether low-level endorsement of depressive symptoms is predictive of cognition among older African Americans. The aim of this study was to examine whether depressive symptoms are related to cognition in a large, cross-sectional cohort of non-demented older African Americans. Our study is unique among prior studies of African American older adults (Espiritu et al., Reference Espiritu, Rashid, Mast, Fitzgerald, Steinberg and Lichtenberg2001; Gitlin, Hauck, Dennis, & Schulz, Reference Gitlin, Hauck, Dennis and Schulz2007; Livney et al., Reference Livney, Clark, Karlawish, Cartmell, Negron, Nunez and Arnold2011; Lopez et al., Reference Lopez, Jagust, Dulberg, Becker, DeKosky, Fitzpatrick and Kuller2003; McDougall, Morgan, & Vaughan, Reference McDougall, Morgan and Vaughan2012; Rovner, Casten, & Leiby, Reference Rovner, Casten and Leiby2012) in that we examined the relationship between depressive symptoms and cognition in a large sample without significant cognitive or functional impairment and used a comprehensive neuropsychological assessment battery. We hypothesized that depressive symptoms would be independently associated with lower scores on measures of executive functioning, memory and attention.
METHODS
Individuals were recruited for a case-control study to identify genes associated with Alzheimer’s disease (AD) among African Americans. This multi-site study included research teams from Columbia University, North Carolina A&T State University, Vanderbilt University, and the University of Miami. Participants were recruited from surrounding areas of New York City, Greensboro, Miami, and Nashville. Self-reported ethnicity and race were based on U.S. Census criteria (U.S. Census Bureau, Reference Unverzagt, Gao, Baiyewu, Ogunniyi, Gureje, Perkins and Hendrie2001). All study-related procedures, including recruitment, informed consent, diagnostic, medical, neuropsychological, and neurological evaluation, were approved by the Institutional Review Boards of participating sites. Eligibility for the current study was restricted to those who were identified as non-demented and had available neuropsychological and self-reported depression data across all participating sites.
Subjects
Eligible participants were aged 60 and over, self-identified as non-Hispanic and Black or African American, and endorsed English as their primary language. Individuals with a past history of psychosis, epilepsy, electroconvulsive therapy, Parkinson’s disease, or Huntington’s disease were excluded. Older adults with a history of MDD, as determined from a medical and psychiatric history questionnaire of symptoms, clinical diagnosis, and treatment, were not excluded. Diagnoses of dementia (American Psychiatric Association, 1994), Alzheimer’s Disease (McKhann et al., Reference McKhann, Knopman, Chertkow, Hyman, Jack, Kawas and Phelps2011), vascular dementia (Roman et al., Reference Roman, Tatemichi, Erkinjuntti, Cummings, Masdeu, Garcia and Hofman1993), mild cognitive impairment (Petersen et al., Reference Petersen, Smith, Waring, Ivnik, Tangalos and Kokmen1999), and cognitive impairment (not MCI), and healthy control status were made according to standard research criteria and determined by consensus case conference that considered the information gathered from neurological, neuropsychological, medical, and functional evaluations.
A total of 1468 individuals were reviewed at consensus conference. Of those, 300 were categorized as AD, 3 were demented with undetermined etiology, and 3 were diagnosed as probable vascular dementia. Of the 1162 non-demented cases, 217 were not administered the 15-item Geriatric Depression Scale (GDS) (Yesavage Reference Yesavage, Brink, Rose, Lum, Huang, Adey and Leirer1983) due to differences in procedures across performance sites. Nevertheless, there was no significant difference across those who were and were not administered the GDS in age (M=69.42, SD=6.9 with GDS vs. M=69.40; SD=7.63 without GDS; t=.0398; p=.96), or years of school (M=13.87; SD=2.99 with GDS vs. M=13.35; SD=6.904 without GDS; t=1.718; p=.09). Of the remaining 945 participants, 1 person was excluded because they did not complete enough of the neuropsychological test battery to be able to compute at least one composite score.
Depressive symptoms were ascertained from the 15-item self-rated GDS. The yes/no response format was adapted from the original, 30-item scale and is a frequently used, reliable, and valid measure of depression symptoms in cognitively intact (Norris, Gallagher, Wilson, & Winograd, Reference Norris, Gallagher, Wilson and Winograd1987), cognitively impaired (Gerety et al., Reference Gerety, Williams, Mulrow, Cornell, Kadri, Rosenberg and Long1994), and African American (Pedraza, Dotson, Willis, Graff-Radford, & Lucas, Reference Pedraza, Dotson, Willis, Graff-Radford and Lucas2009) older adults.
Neuropsychological Evaluation
A comprehensive neuropsychological battery that evaluated memory, language, processing speed, executive functioning, and attention was administered to participants. The battery comprised the following tests: California Verbal Learning Test-2 (CVLT-II; Trials 1–5 free recall, short delayed free recall, long delayed free recall, recognition hits-false positives) (Delis, Kramer, Kaplan, & Ober, Reference Delis, Kramer, Kaplan and Ober2000); 30-item Boston Naming Test (Kaplan, Goodglass, & Weintraub, Reference Kaplan, Goodglass and Weintraub1983; Weintraub et al., Reference Weintraub, Salmon, Mercaldo, Ferris, Graff-Radford, Chui and Morris2009); Digit Symbol subtest of the Wechsler Adult Intelligence Scale – Revised (Wechsler, Reference Wechsler1997); Trail-Making Test Parts A and B (Reitan, Reference Reitan1978); Digit Span Forward and Backward (Wechsler, Reference Wechsler1997); Category Fluency Test (animal and vegetable naming) (Goodglass & Kaplan, Reference Goodglass and Kaplan1983; Morris et al., Reference Morris, Heyman, Mohs, Hughes, van Belle, Fillenbaum and Clark1989).
Exploratory and factor analysis of the neuropsychological test battery revealed five factors, and confirmatory factor analysis revealed structural and metric invariance of these factors across age, education, and diagnostic groups (Miloyan et al., in preparation). To create composite scores for each cognitive domain, Z scores were calculated and averaged from the raw neuropsychological data for each test within each factor. Domain composite scores were grouped as follows: California Verbal Learning Test-2 (CVLT-II; Trials 1–5 free recall, short delayed free recall, long delayed free recall, recognition hits-false positives) comprised the memory composite; 30-item Boston Naming Test, Letter and Category Fluency Test (animal and vegetable naming) were included in the language composite; the processing speed composite included time to complete Trail-Making Test Parts A and Digit Symbol Forward; the attention composite included Digit Span Forward and Backward; and the executive functioning score was the residual of time to complete Trails A regressed onto time to complete Trails B. For all composites, higher scores reflect better performance.
Statistical Analysis
All analyses were conducted using SPSS version 19 (IBM Corp., Amonk, NY). To compare demographics across diagnostic groups (normal control vs. cognitively impaired, not demented) analysis of variance was used for continuous variables and χ2 analysis for proportional data. We used five separate linear regression analyses to evaluate whether depressive symptoms were related to cognitive performance with each of the cognitive domains. In the unadjusted models, GDS scores were entered as a continuous predictor of cognitive test performance. The adjusted regression models included age, sex, number of years of education, and reading level WRAT-3 (WRAT-3; Wilkinson, 1993), as covariates. A value of 0 was assigned to men and a value of 1 was assigned to women for the categorical variable of sex. A heterogeneity of slopes analysis was performed to determine if the relationships between depressive symptoms and cognitive test performance differed across those with and without cognitive impairment.
RESULTS
On the GDS, 415 (44%) endorsed no symptoms, 218 (23.1%) endorsed 1 symptom, 109 (11.5%) endorsed 2 symptoms, and 202 (21.4%) endorsed 3 or more symptoms. Descriptive statistics across diagnostic categories are reported in Table 1. There was no significant difference in the proportion of women across groups. Individuals with cognitive impairment were older and endorsed more depressive symptoms compared to normal controls. Normal controls had more years of formal education compared to individuals with cognitive impairment.
Demographic characteristics of non-demented participants by diagnostic group

Note. CI=participants with mild cognitive impairment with and without memory impairment and cognitively impaired, not MCI; ns=not significant.
** p<.001.
In the unadjusted models, participants with more depressive symptomatology obtained lower scores on measures of attention, language, memory, and processing speed. Because of the skewed distribution of GDS scores, we used Spearman’s correlation to confirm these associations. Total GDS scores were negatively and significantly correlated with language (ρ=−.139; p<.001), memory (ρ=−.089; p<.001), and processing speed (ρ=−.071; p<.05) but not executive functioning (ρ=−.040; p=.220) or attention (ρ=−.065; p=.052).
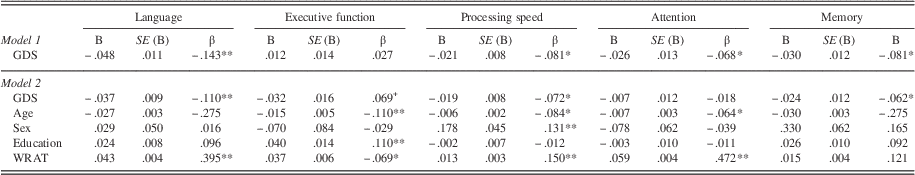
In the adjusted models, higher GDS scores were associated with lower performance on measures of language, memory, and processing speed (Table 2). The association between GDS scores and executive function approached significance (p=.05) once the covariates were included in our model. In contrast, the relationship between depressive symptoms and attention was no longer significant after accounting for the covariates. Reading level was significantly related to all domains of cognitive performance. Women obtained higher scores on all the cognitive composites than men.
Unadjusted and adjusted regression model of GDS scores and cognitive performance

Note. GDS=Geriatric Depression Scale; Edu=Education; WRAT=Wide Range Achievement Test; B=unstandardized beta; SE (B)=standard error of unstandardized beta. Model 1: Unadjusted model of main effects of GDS on cognitive performance. Model 2: Adjusted model controlling for age, sex, education, and WRAT.
*p<.05; **p<.001; +p=.05.
A heterogeneity of slopes analysis was performed to determine whether the relationship between depressive symptoms and cognition varied between diagnostic groups. The interaction between diagnostic group and GDS total score was not significant in each of the five analyses for the cognitive domains (p >.05 for all). We repeated the adjusted regression models analyses in samples stratified by cognitive impairment and found that there was not a significant relationship between depressive symptoms and cognitive test performance in any of the stratified groups (p>.05 for all).
DISCUSSION
We found that, in a large sample of non-demented older African Americans, depressive symptoms were associated with lower scores on measures of memory, language, attention, and processing speed. Attention was no longer related to depressive symptoms after adjusting for age, sex, years of education, and reading level; however, depressive symptoms remained significantly related to lower scores on measures of memory, language, and processing speed. The relationship of depressive symptoms with a measure of executive function approached significance in the context of the covariates. When we examined these relationships within subgroups divided by presence of cognitive impairment, we found the relationship between depressive symptoms and cognition was no longer significant in any domain or subgroup. This suggests that the relationship between depressive symptoms and cognitive function cannot be detected when the sample does not include the full range of cognitive function within non-demented African Americans. Our study is unique because it is the first to examine depressive symptoms as a continuous predictor of multiple cognitive domains among older non-demented, community-dwelling African Americans. Prior studies have focused on internal consistency study of the GDS self-report measure in older African Americans (Pedraza, Dotson, Willis, Graff-Radford, & Lucas, Reference Pedraza, Dotson, Willis, Graff-Radford and Lucas2009) and have included medical populations (Kane, Yochim, & Lichtenberg, Reference Kane, Yochim and Lichtenberg2010).
Consistent with prior studies of depressed and remitted depressed older adults (Bassuk, Berkman, & Wypij, Reference Bassuk, Berkman and Wypij1998; Dal Forno et al., Reference Dal Forno, Palermo, Donohue, Karagiozis, Zonderman and Kawas2005; Dufouil, Fuhrer, Dartiques, & Alperovitch, Reference Dufouil, Fuhrer, Dartigues and Alperovitch1996; Feng, Yap, & Ng, Reference Feng, Yap and Ng2013; Godin et al., Reference Godin, Dufouil, Ritchie, Dartigues, Tzourio, Peres and Alperovitch2007), we found a significant association between depressive symptoms and language, memory, attention, executive function, and processing speed. One longitudinal study of cognitively intact older women showed that baseline depressive symptoms were associated with later, accelerated declines in global cognition and memory function (Goveas et al., Reference Goveas, Espeland, Hogan, Tindle, Shih, Kotchen and Resnick2014). Cross-sectional associations of depressive symptoms and faster rate of cognitive decline have also been reported in cognitively impaired and AD diagnosed individuals (Devanand et al., Reference Devanand, Sano, Tang, Taylor, Gurland, Wilder and Mayeux1996; Geerlings et al., Reference Geerlings, Shoever, Beekman, Jonker, Deeg, Schmand and Van Tilburg2000; Yaffe, Blackwell, Gore, Sands, Reus, & Browner, Reference Yaffe, Blackwell, Gore, Sands, Reus and Browner1999; Zahodne, Devanand, & Stern, Reference Zahodne, Devanand and Stern2013). Poorer memory, language, and executive function performance in the presence of depressive symptoms may be indicative of greater AD risk within this population.
Several limitations should be noted. First, our study was a study of non-demented African American volunteers for a case-control genetic study. We were unable to compare our results to other ethnic and racial groups, and our participants are not representative of all older African Americans. Second, although the GDS has been shown to be reliable among older African Americans (Pedraza et al., Reference Pedraza, Dotson, Willis, Graff-Radford and Lucas2009), it is still a self-rated screening instrument that was not based on a structured clinical interview. Third, our findings may not generalize to broader samples with more significant depressive symptoms or more severe cognitive or functional impairment. The cross-sectional nature of our sample is a limitation in that the cause-effect associations between depressive symptoms and cognitive function could not be determined. Furthermore, we did not examine whether vascular risk factors mediated the relationship between depressive symptoms and cognition. Cardiovascular risk factors such as hypertension, diabetes mellitus, obesity, and diet have been implicated in poorer cognition among African Americans (Antonogeorgos et al., Reference Antonogeorgos, Panagiotakos, Pitsavos, Papageorgiou, Chrysohoou, Papadimitriou and Stefanadis2012; Sachs-Ericsson et al., Reference Sachs-Ericsson, Burns, Gordon, Eckel, Wonderlich, Crosby and Blazer2007; Sims, Madhere, Callender, & Campbell, Reference Sims, Madhere, Callender and Campbell2008; Wessels et al., Reference Wessels, Lane, Gao, Hall, Unverzagt and Hendrie2011) and may be a common cause of depressive symptoms and cognitive impairment among African Americans. Future work will examine the role of vascular disease within the relationship between depressive symptoms and cognition within this population.
This is the largest study of depressive symptoms and cognition using a comprehensive neuropsychological battery and a well-characterized sample of non-demented African American older adults. It is important to examine possible contributing factors that may alter the course of cognitive aging and may be potential avenues for targeted behavioral and cogniton interventions for African Americans, a group that is at higher risk than non-Hispanic Whites for the development of dementia.
ACKNOWLEDGMENTS
This research study was supported by National Institutes of Health, National Institute of Aging (grant R01 AG028786) and in part by Columbia University`s CTSA grant No.UL1TR000040 from NCATS/NIH and T32 MH020004 training grant in Late Lifespan Neuropsychiatric Disorders Program. Aspects of the data were presented at the 2013 International Neuropsychological Society’s meeting in Kona, Hawaii. The authors extend their gratitude to the research assistants and coordinators Raquel Cabo, Josina Hector, Karmen Louie, and Steven Philemond for data collection and processing assistance.