



Introduction
In 2007, the American Heart Association (Dallas, Texas USA) launched “Mission: Lifeline.” This initiative recognizes the importance of shortening the total ischemic time in patients with an acute coronary artery occlusion leading to an ST-elevation myocardial infarction (STEMI) on a 12-lead electrocardiogram (12L-ECG). Reference Rathore, Curtis and Chen1 One crucial area of improvement is the prehospital activation of the catheterization lab in percutaneous coronary intervention (PCI)-capable hospitals in order to expedite the definitive care of these patients immediately upon arrival to the emergency department (ED). Reference O’Gara, Kushner and Ascheim2 Currently, prehospital interpretation of 12L-ECGs is only within the national scope of practice of paramedics. 3-5
However, based on local staffing challenges and the Emergency Medical Services (EMS) system model in Suffolk County, New York (USA), it is possible that a paramedic is not immediately available for these patients. In such a scenario, it is common for an emergency medical technician (EMT) to attend to the patient during transport to the nearest hospital in an ambulance already equipped with a cardiac monitor. Since time-to-intervention is proven to be an independent predictor of early death, Reference O’Gara, Kushner and Ascheim2 it seems reasonable to train EMTs to use equipment already available to them. In keeping with this logic, the recently released 2019 National EMS Scope of Practice Model includes the acquisition and transmission of a 12L-ECG as an allowable skill by an EMT. 5 After a search for peer-reviewed, published literature describing EMT acquisition of 12L-ECGs, it seems that qualifying research is limited to two feasibility studies Reference Provo and Frascone6,Reference Werman, Newland and Cotton7 and an evaluation of the safety of EMTs bypassing local community hospitals for a PCI-center in rural Canada. Reference Froats, Reed and Dionne8
Therefore, the objective of this retrospective observational study was to describe the impact of EMT-acquired 12L-ECGs in Suffolk County, New York, both in terms of the diagnostic quality of the transmitted 12L-ECGs and the number of prehospital PCI-center notifications made as a result of transmitted 12L-ECGs demonstrating a STEMI.
Materials and Methods
This retrospective observational study utilized a pre-existing database to evaluate EMS calls on which an EMT performed and transmitted a 12L-ECG. This study was reviewed and approved by the Stony Brook University IRB (Stony Brook, New York USA; IRB2019-00479).
Suffolk County is a suburban-rural county in New York with a population of roughly 1.5 million, covering approximately 915 square miles. Emergency medical response is provided by 102 agencies: 69 volunteer fire departments, 27 volunteer community ambulance corps, two hospital-based ambulance services with one providing a helicopter air medical service, and four career-based commercial ambulance services. Regional medical oversight and credentialing is performed by the Suffolk County Department of Emergency Medical Services Division (SCEMS; Yaphank, New York USA). Regional online medical control direction is provided by Suffolk County Medical Control (SCMC; Yaphank, New York USA), which is run as a collaboration between the Suffolk County Department of Health Services (Great River, New York USA) and Stony Brook University Hospital.
The scope of practice for EMTs and paramedics in New York state closely resemble the United States National Scope of Practice models for EMTs (formerly EMT-Basics) and paramedics. 3-5 Briefly, EMTs complete approximately 150-200 hours of initial education and are able to perform assessments using pulse oximetry and capillary blood glucometry, as well as perform basic patient care interventions such as semi-automatic defibrillation, airway management with a bag-valve-mask or continuous positive airway pressure mask, application of tourniquets and splints, and administration of medications such as albuterol, aspirin, nitroglycerin, oxygen, naloxone, oral glucose, and epinephrine via an autoinjector.
In November 2016, the New York State Department of Health (Albany, New York USA) released a policy statement allowing EMTs to acquire and transmit 12L-ECGs as a regional option. Following the creation of a train-the-trainer program, SCEMS began to roll out the program to interested agencies. To be eligible, EMTs must complete a standardized training session including an educational presentation and skills performance tool. The agency must conduct annual refresher courses for the EMTs and agree to participate in the Regional Quality Improvement Program as part of which includes prompt review of any call involving an EMT-acquired 12L-ECG by the SCEMS Medical Director.
In the event they are the highest certified provider on scene, approved EMTs are able to acquire a 12L-ECG on patients at least 18 years old presenting with a cardiac-related complaint. The EMT then calls SCMC with brief patient presentation and notification that a 12L-ECG has been, or will be, transmitted via wireless technology. A SCMC physician interprets the 12L-ECG once it has been received and is available for real-time consultation via radio or phone with the EMT; SCMC then advises the EMT of the 12L-ECG interpretation and recommended hospital destination. Of the 11 hospitals in the county, eight are PCI-centers capable of receiving STEMI patients. In the event that the 12L-ECG is determined to be concerning, SCMC transmits it to the PCI-center’s ED and then calls to verify they received it and provide an estimated time of EMS arrival.
For this study, the pre-existing SCMC database was queried for EMS calls on which an EMT acquired a 12L-ECG from program initiation (January 2017) through December 31, 2019. No qualifying calls were excluded, though some aspects of the analysis were limited due to missing data points. Requested data points included the date of the EMS call, patient age, patient gender, time of EMS activation, time EMS arrived on scene, time EMS departed the scene, time EMS arrived at the ED, time of contact with SCMC, and time of PCI-center notification. In the event that data points within the database were missing or unusual, the original prehospital care report and the original paper form completed by the medical control operator at the time of EMT contact were reviewed. Additionally, scanned copies of the 12L-ECGs received by SCMC were requested so that a physician board-certified in Emergency Medicine and EMS could review and determine if their quality was sufficient to diagnose the presence or absence of a STEMI. The physician was presented only with the 12L-ECG and was blinded to the SCMC physician interpretation and patient outcome. Statistical analysis was limited to performing descriptive statistics on Microsoft Excel 2020 (Microsoft Corp.; Redmond, Washington USA).
Results
The database query yielded 665 calls (228 in 2017, 217 in 2018, and 220 in 2019; 41 participating agencies) on which an EMT acquired and transmitted a 12L-ECG. Of the 665, 99 had no 12L-ECG available within the database. A physician board-certified in Emergency Medicine and EMS reviewed the 566 available 12L-ECGs and determined that for 543 (96%) of them, the quality was sufficient to diagnose the presence or absence of a STEMI. In terms of patient demographics, 50% were women and the median age was 60 years old (IQR 44-74).
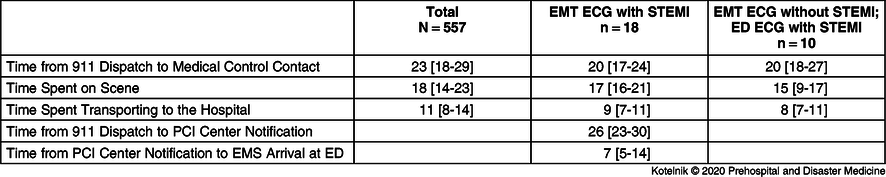
Of the 665 calls, only 557 had a full set of times available in the database. Table 1 describes the time intervals for these calls.
Description of Time Intervals for Calls with a Full-Set of Times Available

Note: Times are represented as median [interquartile range] and are reported in minutes.
Abbreviations: ECG, 12-lead electrocardiogram; ED, emergency department; EMT, emergency medical technician; STEMI, ST-elevation myocardial infarction.
Since the initiation of the county-wide program, 18 notifications were made to PCI-centers about 12L-ECGs acquired by EMTs which were concerning for STEMIs. Of the 18 notifications, three had ED diagnoses other than STEMI, which included a left bundle branch block and NSTEMI.
Of the patients on whom an EMT acquired and transmitted a 12L-ECG, 10 were noted to have a STEMI on the 12L-ECG acquired in the ED despite having a reassuring prehospital 12L-ECG. Seven of these 12L-ECGs were available in the database; the quality of all of seven were determined to be sufficient to diagnose the presence or absence of a STEMI.
No hospital destination selections were changed as a result of transmitted 12L-ECGs.
Discussion
While the cost-benefit analysis of equipping every ambulance with a cardiac monitor is beyond the scope of this paper, it seems clear that in the event a cardiac monitor is available, after a limited educational intervention, EMTs are capable of acquiring a diagnostically useful 12L-ECG and transmitting it to a remote medical control physician for interpretation. A PCI-center was pre-notified 18 times, in some cases upwards of 15 minutes prior to EMS arrival there. Although no hospital destination selections were changed following 12L-ECG interpretation, likely owing to the numerous PCI-capable centers in the county, advanced notice was provided to PCI-centers which otherwise would not have occurred until after a 12L-ECG was acquired in the ED. This is of particular benefit if the PCI team is not already in-house. Additionally, this demonstrates value in the financial and time implications for the initial and continuous training of EMTs to perform this skill.
This study is unique from the handful of previously described studies evaluating EMTs acquiring 12L-ECGs in several respects. First, this study involves over 40 different agencies transmitting 12L-ECGs to a centralized medical control location, which then notifies one of eight possible PCI-centers in the county. Other studies describe the results of one Reference Froats, Reed and Dionne8 or four Reference Provo and Frascone6 agencies, or transmission of the 12L-ECGs to a single receiving PCI-center. Reference Werman, Newland and Cotton7,Reference Froats, Reed and Dionne8 Additionally, other studies rely on the monitor’s analysis of the 12L-ECG, Reference Provo and Frascone6,Reference Froats, Reed and Dionne8 whereas this county-wide program utilizes the real-time transmission of the 12L-ECG to a physician, which although more vulnerable to technical difficulties, allows for greater interpretational nuance than most software programs. Reference Litell, Meyers and Smith9
Despite these operational challenges, this is the largest study published to date, Reference Provo and Frascone6-Reference Froats, Reed and Dionne8 and the only one which uses a single physician, blinded to patient outcome, to evaluate the diagnostic quality of the transmitted 12L-ECGs. Reference Provo and Frascone6,Reference Werman, Newland and Cotton7 Of the 12L-ECGs acquired by EMTs, 96% of those available for review were of diagnostic quality. With a median on-scene time of 18 minutes, which is similar to previous studies, Reference Werman, Newland and Cotton7 the time spent for an EMT to acquire a 12L-ECG using equipment already available seems reasonable and well worth it, especially for the 18 patients who otherwise would not have received a prehospital PCI-center activation for a concern of a STEMI.
Limitations
The most significant limitation for this study is the reliance on a pre-existing database from which information was queried. As described in the results section, not all entries were complete and not all 12L-ECGs were available for review. Drawing appropriate conclusions from such data is reliant upon correct information being initially entered into the database, with the awareness that when the data were entered, it was not known that it would be later interpreted in the context of this research study. Additionally, just under 15% of the transmitted 12L-ECGs were not available in the database for review. Given that 96% of the available ones were deemed acceptable in quality, it was suspected that the missing ones would likely be similar.
Conclusions
In the event a cardiac monitor is available, after a limited educational intervention, EMTs are capable of acquiring a diagnostically useful 12L-ECG and transmitting it to a remote medical control physician for interpretation. This allows for prehospital PCI-center activation for a concern of a STEMI in the event that a paramedic is not available to care for the patient.
Conflicts of interest
The authors have no financial conflicts of interest to disclose.



Target article
12-Lead Electrocardiograms Acquired and Transmitted by Emergency Medical Technicians are of Diagnostic Quality and Positively Impact Patient Care
Related commentaries (1)
The Effect of Prehospital ECGs on Patient Care in STEMI