Introduction
There is increasing evidence for a bi-factor model of attention deficit/hyperactivity disorder (ADHD) (Grizenko et al. Reference Grizenko, Paci and Joober2010) with two distinct factors of inattention and hyperactivity/impulsivity (Martel et al. Reference Martel, von Eye and Nigg2010). Attention is an important prerequisite for learning in the classroom and at home. In the general population, middle childhood ADHD of the inattentive subtype has been reported as a better predictor of later academic performance than hyperactivity/impulsivity (Duncan et al. Reference Duncan, Claessens, Huston, Pagani, Engel, Sexton, Japel, Dowsett, Magnuson, Klebanov, Feinstein, Brooks-Gunn and Duckworth2007).
Children born very preterm (VP; <32 weeks of gestation) and/or with very low birth weight (VLBW; <1500 g birth weight), referred to as VLBW/VP subsequently, are at a highly increased risk of cognitive impairments, behavioural problems and poor academic achievement (Aarnoudse-Moens et al. Reference Aarnoudse-Moens, Weisglas-Kuperus, van Goudoever and Oosterlaan2009; Johnson et al. Reference Johnson, Wolke, Hennessy and Marlow2011). VLBW/VP children are consistently found to display a higher prevalence of ADHD symptoms than full-term children (Aarnoudse-Moens et al. Reference Aarnoudse-Moens, Weisglas-Kuperus, van Goudoever and Oosterlaan2009), in particular of the inattentive subtype (Hack et al. Reference Hack, Hudson, Schluchter, Andreias, Drotar and Klein2009; Johnson et al. Reference Johnson, Hollis, Kochhar, Hennessy, Wolke and Marlow2010), which are only partly explained by cognitive (IQ) deficits (Anderson & Doyle, Reference Anderson and Doyle2004; Samara et al. Reference Samara, Marlow and Wolke2008). This increased risk for ADHD inattentive subtype in VLBW/VP children may result from global changes in brain anatomy, connectivity or altered development of functional architecture (Kapellou et al. Reference Kapellou, Counsell, Kennea, Dyet, Saeed, Stark, Maalouf, Duggan, Ajayi-Obe, Hajnal, Allsop, Boardman, Rutherford, Cowan and Edwards2006; Johnson et al. Reference Johnson, Hollis, Kochhar, Hennessy, Wolke and Marlow2010). Prematurity is often associated with intra-uterine growth restriction (IUGR), assessed as small for gestational age (SGA) at birth, but it remains unclear whether prematurity or IUGR/SGA constitutes the more significant predictor of attention problems (Heinonen et al. Reference Heinonen, Raikkonen, Pesonen, Andersson, Kajantie, Eriksson, Wolke and Lano2010). Both prematurity and SGA status are associated with adverse brain development including reduced brain volume (Toft et al. Reference Toft, Leth, Ring, Peitersen, Lou and Henriksen1995; Cheong et al. Reference Cheong, Hunt, Anderson, Howard, Thompson, Wang, Bear, Inder and Doyle2008). However, prematurity may have additional neurological consequences such as alterations in white matter microstructure (Dudink et al. Reference Dudink, Kerr, Paterson and Counsell2008) and cortical folding (Kapellou et al. Reference Kapellou, Counsell, Kennea, Dyet, Saeed, Stark, Maalouf, Duggan, Ajayi-Obe, Hajnal, Allsop, Boardman, Rutherford, Cowan and Edwards2006). These changes in brain development increase the likelihood of cognitive dysfunction (Mento & Bisiacchi, Reference Mento and Bisiacchi2012) and may functionally result in poorer attention and slower processing speed affecting academic attainment (Mulder et al. Reference Mulder, Pitchford and Marlow2011).
ADHD of the combined subtype is often co-morbid with conduct disorder and other externalizing behaviours (Costello et al. Reference Costello, Mustillo, Erkanli, Keeler and Angold2003; Biederman et al. Reference Biederman, Ball, Monuteaux, Kaiser and Faraone2008a, Reference Biederman, Petty, Dolan, Hughes, Mick, Monuteaux and Faraoneb) which are also predictive of schooling problems (Odgers et al. Reference Odgers, Moffitt, Broadbent, Dickson, Hancox, Harrington, Poulton, Sears, Thomson and Caspi2008). In contrast, ADHD inattentive subtype symptoms, whether in the general population (Connor et al. Reference Connor, Steeber and McBurnett2010) or in VLBW/VP children, have been found to be specific and rarely co-morbid with conduct problems (Samara et al. Reference Samara, Marlow and Wolke2008; Hack et al. Reference Hack, Hudson, Schluchter, Andreias, Drotar and Klein2009), providing further evidence for a bi-factor model of ADHD.
In summary, VLBW/VP children more often suffer from ADHD inattentive subtype as well as from cognitive impairments than full-term children. Full-term children, on the other hand, are less often diagnosed with ADHD inattentive subtype but, when they are, they may have the same limitations to cortical development that are characteristic of preterm children (Wolosin et al. Reference Wolosin, Richardson, Hennessey, Denckla and Mostofsky2009; Proal et al. Reference Proal, Reiss, Klein, Mannuzza, Gotimer, Ramos-Olazagasti, Lerch, He, Zijdenbos, Kelly, Milham and Castellanos2011). Accordingly, in the preterm and general population the combination of ADHD inattentive subtype and low cognitive abilities frequently results in academic failure (Breslau et al. Reference Breslau, Miller, Breslau, Bohnert, Lucia and Schweitzer2009, Reference Breslau, Breslau, Peterson, Miller, Lucia, Bohnert and Nigg2010; Polderman et al. Reference Polderman, Boomsma, Bartels, Verhulst and Huizink2010). This suggests an underlying neuropsychological deficit involved in attention problems (Nagy et al. Reference Nagy, Westerberg, Skare, Andersson, Lilja, Flodmark, Fernell, Holmberg, Bohm, Forssberg, Lagercrantz and Klingberg2003; Wolke, Reference Wolke, Howlin, Charman and Ghaziuddin2011) and the study of VLBW/VP children may provide an excellent model for understanding pathways to ADHD inattentive subtype and subsequent academic underachievement.
This study investigated attention problems at 6 and 8 years of age using multiple data sources and assessed academic outcome at 13 years of age in VLBW/VP and full-term children. The following questions were addressed. Are VLBW/VP children compared with full-term children at higher risk of ADHD of the inattentive subtype? Are ADHD inattentive subtype-specific symptoms, rather than hyperactivity/impulsivity, better predictors of later academic achievement? Are the pathways from attention problems and cognitive impairment to academic underachievement in VLBW/VP similar to those in full-term children?
Method
Samples
Data were collected as part of the prospective Bavarian Longitudinal Study (BLS) (Wolke & Meyer, Reference Wolke and Meyer1999b; Schneider et al. Reference Schneider, Wolke, Schlagmüller and Meyer2004), a geographically defined whole-population sample of VLBW/VP children and full-term controls in South Germany.
VLBW and/or VP children
Of 70 600 children born in South Bavaria during a 15-month period during 1985 and 1986, 682 were VLBW (birth weight <1500 g) or VP infants (<32 weeks gestation), or both. Of these VLBW/VP children, 172 died during the initial hospitalization and seven died during the first 6 years of life. Of the parents, seven did not give written consent to participate and 48 parents and their children were non-German speakers (i.e. the parents did not speak German and the children scored < − 2 s.d. on German language tests at 4 years of age). These mother–child dyads were excluded from the study as their verbal behaviour could not be coded and the cognitive assessments not administered. Of the 448 VLBW/VP survivors eligible for inclusion, 378 (84%), 396 (88%) and 339 (76%) participated at the 6 years 3 months, 8 years 5 months and 13-year assessments, respectively. Altogether, 281 (63%) VLBW/VP children had complete datasets across all four measurement points, i.e. neonatal, 6 years 3 months, 8 years 5 months and 13 years of age. A comparison of these children with those who dropped out during the course of the study did not show any differences in birth weight, gestational age, SGA status, intensity of treatment during the first 10 days of life, length of hospitalization after birth, multiple births, maternal education or family adversity (Supplementary Appendix 2). However, the participating VLBW/VP children had older mothers compared with the VLBW/VP drop-out children.
Full-term control group
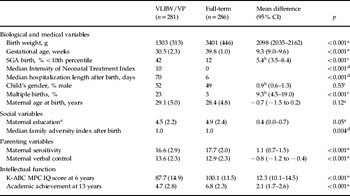
Of 936 controls (>36 weeks gestation; normal postnatal care) identified at birth from the same hospitals in Bavaria, 350 survivors (five died) were selected for the 6 years 3 months assessment to match the overall distribution of child gender, family socio-economic status (SES) and maternal age of the VLBW/VP group (see Table 1). Of the 350 recruited at birth, 307 (88%), 279 (80%) and 294 (84%) attended at 6 years 3 months, 8 years 5 months and 13 years, respectively, and 286 full-term control children (82%) had complete datasets across the four time points.
Biological, medical and social variables, parenting, and functional characteristics of the VLBW/VP and full-term control children

VLBW/VP, Very low birth weight/very preterm; CI, confidence interval; SGA, small for gestational age; K-ABC MPC IQ, Kaufman Assessment Battery for Children mental processing component of intelligence quotient.
Data are given as mean (standard deviation) unless stated otherwise.
a Two-tailed significance based on a t test.
b Odds ratio.
c Two-tailed significance based on a χ2 test.
d Two-tailed significance based on a Mann–Whitney U test.
e Minimum = 1; maximum = 11.
Procedure
Details of pre-, peri- and neonatal data have been described elsewhere (Wolke & Meyer, Reference Wolke and Meyer1999b; Gutbrod et al. Reference Gutbrod, Wolke, Söhne, Ohrt and Riegel2000) and are briefly outlined here. Participating parents were approached within 48 h of the infant's hospital admission and were included in the study once they had given written consent for their child to participate. Ethical approval was obtained from the University of Munich Children's Hospital Ethics committee. At both 6 years 3 months and 8 years 5 months, participating children and their mothers were assessed by the interdisciplinary study team for one whole day including neurological assessments (done by paediatricians), parent interviews (done by psychologists), cognitive assessments and behaviour ratings (done by psychological assistants and the whole team). (See Supplementary Appendix 1 for an overview of the instruments administered at each assessment wave.) All assessors and raters were blind to group membership. Child observations and assessments focused on the current situation at the time of assessment whereas the questions in the parent interview referred to the last 6 months.
Measures
Biological variables
Gestational age was determined from maternal reports of the last menstrual period and serial ultrasounds during pregnancy. When the estimates of these two differed by more than 2 weeks, postnatal Dubowitz scores were used (Dubowitz et al. Reference Dubowitz, Dubowitz and Goldberg1970). Birth weight was documented in the birth records. Infant risk was assessed with the Intensity of Neonatal Treatment Index (INTI) (Gutbrod et al. Reference Gutbrod, Wolke, Söhne, Ohrt and Riegel2000), which was computed from daily ratings of care level, respiratory support, feeding dependency and neurological status during initial hospitalization.
Social variables
Information was obtained by standardized interviews within the first 10 days of life. Maternal education was entered into 11 categories (i.e. 1 = no educational qualification; 5 = General Certificate of Secondary Education; 11 = doctoral degree) (Riegel et al. Reference Riegel, Ohrt, Wolke and Österlund1995). Family adversity after birth was determined by eight psychosocial variables as a composite index score [family adversity index (FAI); for example, being a single parent or having mental health problems] (Rutter & Quinton, Reference Rutter, Quinton and McGurk1977; Wolke et al. Reference Wolke, Schmid, Schreier and Meyer2009).
Parenting
At 6 years 3 months and 8 years 5 months, maternal sensitivity and verbal control behaviour was recorded during a dyadic play situation using an Etch-a-Sketch. Maternal behaviour was analysed with a standardized coding system, the ‘Assessment of Mother–Child Interaction with the Etch-a-Sketch’ (AMCIES) (Schneider et al. Reference Schneider, Houweling, Gommlich-Schneider, Klein, Nündel and Wolke2009; Jaekel et al., Reference Jaekel, Wolke and Chernovain press; D. Wolke et al. unpublished observations), by two independent experienced raters (psychologists) who were blind to group and family characteristics. Inter-rater reliabilities (intraclass correlation coefficients; ICCs) ranged from 0.75 to 0.92 for maternal sensitivity, and from 0.74 to 0.86 for verbal control (Jaekel et al., Reference Jaekel, Wolke and Chernovain press).
Cognitive assessments
At 6 years 3 months of corrected age, children's intelligence was assessed with the German version of the Kaufman Assessment Battery for Children (K-ABC; Kaufman & Kaufman, Reference Kaufman and Kaufman1983; Melchers & Preuss, Reference Melchers and Preuss1991). Cognitive assessments were carried out by trained assistant psychologists.
Attention and activity problems assessed along a continuum at both 6 years 3 months and 8 years 5 months
First, child behaviour during the K-ABC test situation was evaluated by assistant psychologists with the Tester's Rating of Child Behavior (TRCB) (Wolke et al. Reference Wolke, Skuse and Mathisen1990; Wolke & Meyer, Reference Wolke and Meyer1999a), consisting of 13 nine-point rating scales (1 = very low, 9 = very high). Guided by principal component analysis, six of 13 subscales [(1) attention, (2) robustness and endurance, (3) demandingness (recoded), (4) cooperativeness, (5) compliance, and (6) difficulty (recoded)] formed an index scale named Task Orientation (Cronbach's α = 0.90 at 6 years and α = 0.85 at 8 years). In addition, the two subscales of (1) activity and (2) intensity were combined to form an index scale of Activity (Cronbach's α = 0.63 at 6 years and α = 0.71 at 8 years). The TRCB manual including a detailed description of the 13 subscales is available from the authors. Inter-rater reliabilities of the TRCB were computed for 32 participants. ICCs ranged from 0.63 to 0.97 for the Task Orientation subscales, and from 0.88 to 0.93 for the Activity subscales.
Second, child attention across the whole assessment day was evaluated as a consensus rating by the whole research team (psychologist, assistant psychologist and paediatrician). Then, three of the above-described TRCB subscales [(1) attention, (2) robustness and endurance, (3) demandingness (recoded)] were combined to form the TEAM index scale of attention (Cronbach's α = 0.88 at 6 years and α = 0.98 at 8 years). Scores could range from 1 = very low to 9 = very high.
Third, child activity and task persistence were videotaped during a standardized dyadic play situation and evaluated with the AMCIES coding system (D. Wolke et al. unpublished observations) by two independent psychologists. ICCs ranged from 0.69 to 0.75 for child activity and task persistence at both time points (Jaekel et al., in press).
Fourth, mothers rated child attention and impulsivity in the Child Behavior Checklist (CBCL; Achenbach, Reference Achenbach1991) attention problems scale.
Diagnosis of ADHD at 6 years 3 months and 8 years 5 months
ADHD diagnoses were obtained with the structured Mannheimer Parent Interview (Esser et al. Reference Esser, Blanz, Geisel and Laucht1989), a ‘gold standard’ interview in Germany allowing for 100% concordant clinical DSM-IV diagnosis (El-Faddagh et al. Reference El-Faddagh, Laucht, Maras, Vöhringer and Schmidt2004; Esser et al. Reference Esser, Fischer, Wyschkon, Laucht and Schmidt2007) and inter-rater reliabilities of Cohen's κ = 0.71 (Esser et al. Reference Esser, Blanz, Geisel and Laucht1989). Child attention problems, hyperactivity and impulsivity were evaluated separately and the DSM-IV diagnoses of: (1) ADHD inattentive subtype; (2) ADHD hyperactive-impulsive subtype; or (3) ADHD combined subtype were made. Interviews of 106 participants were audiotaped and double-rated by two psychologists; inter-rater reliabilities of ADHD diagnoses were good (Cohen's κ = 0.80–0.89, ICCs = 0.81–0.89). In addition, CBCL (Achenbach, Reference Achenbach1991) cut-off criteria (>97th percentile) according to the German norms (Walter & Remschmidt, Reference Walter and Remschmidt1999) were used to obtain a categorical measure of child attention problems. (Supplementary Appendix 3 shows a correlation matrix of the different attention and activity measures.)
Overall Achievement Test score at 8 years 5 months
The following standard tests to assess school achievement were administered: the Zürich Reading Test (number of errors, reading speed) (Grissemann, Reference Grissemann2000); a pseudo-word reading test (Schneider et al. Reference Schneider, Wolke, Schlagmüller and Meyer2004; J. Leon-Villagra and D. Wolke, unpublished observations); spelling and writing tests (Diagnostic Spelling Test 2; Müller, Reference Müller1983); and a mathematical test (mathematics performance, arithmetic) (Stigler et al. Reference Stigler, Lee and Stevenson1990; Wolke & Leon-Villagra, Reference Wolke and Leon-Villagra1993). Performance in these tests was moderately correlated and scores were combined into an Overall Achievement Test score (Cronbach's α = 0.76).
Academic achievement at 13 years
Child academic achievement at 13 years was based on level of educational track in the German secondary school system according to the following criteria: (1) school type [special school, secondary school low-track (Hauptschule), mid-track (Realschule) or high-track (Gymnasium)]; (2) whether the child ever had repeated a class (i.e. is in age-appropriate class or not); and (3) performance within each track in the core subjects Mathematics and German (average or above versus below average). Information was obtained from end-of-year grades and parent reports of child's school and year class, and then scaled on a nine-point ranking scale (Schneider et al. Reference Schneider, Wolke, Schlagmüller and Meyer2004). The scale ranged from: 1 = received special education throughout school career; through 5 = attends Hauptschule at age-appropriate grade-level and shows average/above average performance according to end-of-year marks in the core subjects; to 9 = attends Realschule or Gymnasium at age-appropriate grade-level and shows average/above average performance.
Statistical analyses
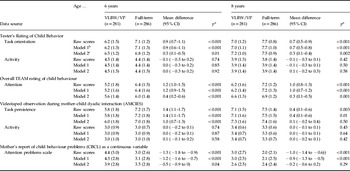
Data were analysed with SPSS 17.0 (SPSS, Inc., USA). Group comparisons of continuous attention and activity measures were carried out with Student's t tests, using raw values and then repeated adjusting for social factors (maternal education and family adversity: model 1), and additionally repeated adjusting for model 1 factors and child IQ (K-ABC: model 2, see Table 2). Group comparisons of ADHD diagnoses were carried out with χ2 tests (Table 3). All tests were two-tailed.
Multiple data source child attention and activity measures for VLBW/VP and full-term children at 6 and 8 years, comparing raw scores with scores adjusted for maternal education and family adversity at birth (model 1), and additionally child IQ at 6 years (model 2)

VLBW/VP, Very low birth weight/very preterm; IQ, intelligence quotient; CI, confidence interval; AMCIES, Assessment of Mother–Child Interaction with the Etch-a-Sketch; CBCL, Child Behavior Checklist.
Data are given as mean (standard deviation).
a Two-tailed significance based on a t test.
b Model 1 adjusted for social factors.
c Model 2 additionally adjusted for child IQ.
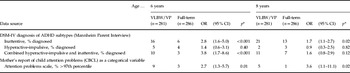
Percentages of ADHD diagnoses comparing VLBW/VP and full-term children at 6 years 3 months and 8 years 5 months of age

ADHD, Attention deficit/hyperactivity disorder; VLBW/VP, very low birth weight/very preterm; OR, odds ratio; CI, confidence interval; DSM-IV, Diagnostic and Statistical Manual of Mental Disorders, version 4; CBCL, Child Behavior Checklist.
a Two-tailed significance based on a χ2 test.
ADHD and parenting measures at 6 years 3 months and 8 years 5 months were aggregated for prediction of academic achievement at 13 years. In each case, the higher score of the respective continuous measure at 6 years 3 months and 8 years 5 months was counted (TRCB, TEAM, AMCIES, CBCL). Categorical measures were aggregated by counting diagnoses that were present at least at one of the two time points (e.g. Copeland et al. Reference Copeland, Shanahan, Miller, Costello, Angold and Maughan2010; Mannheimer Parent Interview, CBCL).
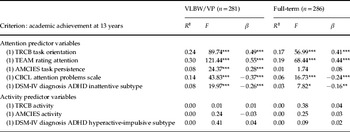
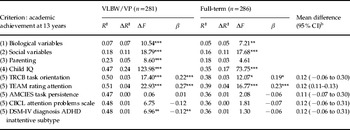
First, univariate regressions were conducted to examine the predictive value of each attention and activity measure on academic achievement for the VLBW/VP children and full-term controls (Table 4). Second, the predictive value of child attention on academic achievement was tested after controlling for biological (gestational age, INTI) and social variables (maternal education, family adversity), parenting (maternal sensitivity and verbal control) and child IQ (K-ABC, Table 5). Significance levels were adjusted for multiple testing with the D/AP (Dubey and Armitage-Parmar) procedure which takes into account the mean correlation between multiple outcome variables before performing Bonferroni correction (Sankoh et al. Reference Sankoh, Huque and Dubey1997). Third, strengths of regression coefficients in the VLBW/VP and full-term groups were compared by calculating a 95% confidence interval (CI) for the difference between proportions of explained variance (Olkin & Finn, Reference Olkin and Finn1995).
Results of univariate regressions of aggregated multiple data source attention and activity measures on VLBW/VP and full-term children's academic achievementa

VLBW/VP, Very low birth weight/very preterm; TRCB, Tester's Rating of Child Behavior; AMCIES, Assessment of Mother–Child Interaction with the Etch-a-Sketch; CBCL, Child Behavior Checklist; DSM-IV, Diagnostic and Statistical Manual of Mental Disorders, version 4; ADHD, attention deficit/hyperactivity disorder.
a α Levels were adjusted for multiple testing with the D/AP (Dubey and Armitage-Parmar) procedure and Bonferroni correction.
* p < 0.01, ** p < 0.002, *** p < 0.0002.
Results of hierarchical multivariate regressions showing individual contributions of aggregated multiple data source attention measures in predicting VLBW/VP and full-term children's academic achievement at 13 yearsa

VLBW/VP, Very low birth weight/very preterm; CI, confidence interval; IQ, intelligence quotient; TRCB, Tester's Rating of Child Behavior; AMCIES, Assessment of Mother–Child Interaction with the Etch-a-Sketch; CBCL, Child Behavior Checklist; DSM-IV, Diagnostic and Statistical Manual of Mental Disorders, version 4; ADHD, attention deficit/hyperactivity disorder.
a Each attention measure was entered separately into the prediction (step 5) after controlling for biological and social variables (steps 1 + 2), parenting (step 3) and child IQ (step 4). α Levels were adjusted for multiple testing with the D/AP (Dubey and Armitage-Parmar) procedure and Bonferroni correction.
b Regression coefficients in the VLBW/VP and full-term groups were manually compared by computing the 95% CI for the difference between proportions of explained variance (Olkin & Finn, Reference Olkin and Finn1995).
* p < 0.01, ** p < 0.002, *** p < 0.0002.
Results
Sample characteristics
The VLBW/VP children, by definition, were born at younger gestational age, had lower birth weights and higher prenatal risk scores, were more often born SGA, and hospitalized longer than full-term controls.Footnote 1Footnote † There were no group differences in child gender distribution, maternal age or education; however, among the VLBW/VP children, more were from multiple births. Mothers of VLBW/VP children had higher family adversity scores and showed less sensitive and more controlling parenting behaviour. As described before in more detail (Schneider et al. Reference Schneider, Wolke, Schlagmüller and Meyer2004), the VLBW/VP compared with full-term children in our sample had poorer scores in the K-ABC mental processing component (IQ) at age 6 and they were less academically successful at age 13 years (Table 1).
Continuous ADHD measures at 6 years 3 months and 8 years 5 months
At both 6 and 8 years, VLBW/VP children had lower scores across all attention measures independent of data source. In contrast, no differences in activity measures were found compared with the full-term control children (Table 2). When raw scores were adjusted for maternal education and family adversity (model 1), results remained the same. When scores were additionally adjusted for child IQ (model 2), however, the differences in child task persistence observed in interaction with the mother (AMCIES) and in mother ratings of attention problems (CBCL) at 8 years disappeared.
ADHD diagnoses at 6 years 3 months and 8 years 5 months
At 6 years, the VLBW/VP children were more likely to be diagnosed with ADHD inattentive and combined subtypes, but not with the hyperactive-impulsive subtype compared with full-term controls (Table 3). At 8 years of age the VLBW/VP children were still more likely to be diagnosed with ADHD inattentive subtype but not with the hyperactive-impulsive or combined subtypes. At both 6 and 8 years, VLBW/VP children more often had clinically relevant attention problems in the CBCL than full-term controls.
Prediction of adolescents’ academic achievement by middle childhood attention measures
To examine the prediction of each of the attention and activity measures on subsequent academic achievement, a set of regressions was performed for the VLBW/VP and full-term groups, separately. Table 4 shows that all of the five attention measures by different data sources significantly predicted academic achievement at 13 years in the VLBW/VP group. In contrast, none of the three activity measures predicted academic outcome. The pattern of findings for the full-term children was similar, with four out of the five attention but none of the activity measures predicting academic achievement. To ensure the robustness of these results the analyses were repeated with an alternative measure of academic attainment: the Overall Achievement Test score at age 8 years 5 months, and, in addition, with children's math school marks (subsample of ‘Hauptschüler’). The same pattern of outcome was found (see Supplementary Appendices 4 and 5).
The unique contribution of the different multiple data source attention measures in predicting academic achievement was tested by controlling for biological (step 1: gestational age, INTI) and social variables (step 2: maternal education, family adversity), parenting (step 3: maternal sensitivity and verbal control) and child IQ (step 4: K-ABC). In step 5, the TRCB Task Orientation scale and the TEAM rating of child attention individually continued to predict both VLBW/VP and full-term children's academic achievement. The predictive values of the AMCIES task persistence and CBCL attention problems scales did not reach significance after α levels had been adjusted for multiple testing whereas the diagnosis of ADHD inattentive subtype predicted VLBW/VP but not full-term children's achievement (Table 5). Comparison of regression coefficients in the VLBW/VP and full-term group with 95% CIs revealed no significant differences between proportions of explained variance across all regression functions except the one including the TEAM rating of attention, which was larger in VLBW/VP adolescents (mean difference = 0.12, 95% CI = 0.11–0.13).
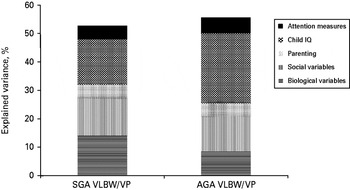
Comparison of SGA (n = 117) with appropriate-for-gestational age (AGA) (n = 164) VLBW/VP children found that SGA children had lower scores in the TRCB Task Orientation [mean = 5.97 (s.d. = 1.54) versus 6.32 (s.d. = 1.39), p < 0.05 at 6 years and 6.81 (s.d. = 1.29) versus 7.11 (s.d. = 1.13), p < 0.05 at 8 years, respectively] and TEAM ratings of attention [5.93 (s.d. = 1.51) versus 6.42 (s.d. = 1.56), p < 0.05 at 8 years]. However, SGA VLBW/VP children were not more often diagnosed with ADHD inattentive subtype than AGA VLBW/VP children. SGA VLBW/VP children had lower IQ scores at 6 years [85.44 (s.d. = 14.49) versus 90.06 (s.d. = 14.51), p < 0.05] and were less academically successful than AGA VLBW/VP adolescents [4.13 (s.d. = 2.64) versus 5.07 (s.d. = 2.87), p < 0.01, respectively]. In both groups attention measures predicted academic achievement (see Supplementary Appendix 6 for a detailed report). Finally, inclusion of biological and social variables, parenting, IQ and all attention measures in the prediction of academic achievement revealed a slightly different picture in SGA VLBW/VP compared with AGA VLBW/VP children (Fig. 1). Overall, biological, social, parenting, IQ and attention measures explained 53% of variance in SGA VLBW/VP and 56% in AGA VLBW/VP adolescents' academic achievement at 13 years. Biological variables contributed a larger amount of explained variance to SGA VLBW/VP adolescents' academic achievement (14% compared with 9%) whereas IQ contributed a larger amount of explained variance to AGA VLBW/VP adolescents' academic achievement (25% compared with 16%); however, differences between proportions of explained variance were not significant.
Unique percentage of variance explained in academic achievement at 13 years of age in small for gestational age (SGA) very low birth weight/very preterm (VLBW/VP) children (n = 117) and appropriate for gestational age (AGA) VLBW/VP children (n = 164) by biological and social variables, parenting, child intelligence quotient (IQ) and attention problems. Hyperactivity/impulsivity measures did not contribute to the prediction.

Discussion
This study investigated whether middle childhood attention problems are predictive of VLBW/VP adolescents' academic achievement. We found that independent of data source VLBW/VP children were at higher risk for specific attention problems at both 6 and 8 years but not for hyperactive/impulsive behaviour compared with full-term controls. This overall pattern did not change substantially when raw scores were adjusted for social factors and child IQ. Child attention consistently predicted academic achievement 5 to 7 years later even after controlling for biological and social variables, parenting and child IQ. In contrast, hyperactive/impulsive behaviour was not associated with poor academic achievement.
Our results confirm that VLBW/VP children are at elevated risk for attention problems, which are only partly accounted for by IQ and social factors (Anderson & Doyle, Reference Anderson and Doyle2004). Differences between VLBW/VP and full-term children were attenuated but did not disappear once adjusted for IQ. Consistent with other studies (Johnson et al. Reference Johnson, Wolke, Hennessy and Marlow2011), IQ was the best predictor of adolescents' academic achievement but attention problems explained an additional proportion of variance. Arguably, effect sizes of attention measures were small yet consistent across groups. This suggests that attention problems are detrimental for academic attainment over and above general cognitive abilities (Biederman et al. Reference Biederman, Petty, Fried, Kaiser, Dolan, Schoenfeld, Doyle, Seidman and Faraone2008c; Breslau et al. Reference Breslau, Miller, Breslau, Bohnert, Lucia and Schweitzer2009), social disadvantage and parenting (Polderman et al. Reference Polderman, Boomsma, Bartels, Verhulst and Huizink2010). The combination of ADHD inattentive subtype with cognitive impairments is frequently found in VLBW/VP children and indicates a neurodevelopmental pathway over and above social factors in explaining subsequent academic underachievement. Accordingly, as shown here, full-term children with ADHD inattentive subtype and low cognitive abilities are also at increased risk for poor academic achievement and may show similar alterations in cortical development that are characteristic of preterm children (Wolosin et al. Reference Wolosin, Richardson, Hennessey, Denckla and Mostofsky2009; Proal et al. Reference Proal, Reiss, Klein, Mannuzza, Gotimer, Ramos-Olazagasti, Lerch, He, Zijdenbos, Kelly, Milham and Castellanos2011). However, the prevalence of cognitive and attention problems is lower in full-term children. Thus, the study of VLBW/VP children may provide an excellent model for understanding the neuropsychological deficits involved in ADHD inattentive subtype and its long-term consequences for academic achievement.
Finally, IUGR may alter brain development and make an impact on cognitive abilities and attention regulation (Gutbrod et al. Reference Gutbrod, Wolke, Söhne, Ohrt and Riegel2000; Heinonen et al. Reference Heinonen, Raikkonen, Pesonen, Andersson, Kajantie, Eriksson, Wolke and Lano2010). Indeed, SGA VLBW/VP children had lower scores in the TRCB and TEAM ratings of attention but they were not diagnosed with ADHD inattentive subtype more often than AGA VLBW/VP children. This shift to increased attention difficulties after IUGR is consistent with a recent report (Heinonen et al. Reference Heinonen, Raikkonen, Pesonen, Andersson, Kajantie, Eriksson, Wolke and Lano2010). In contrast, gestation has been previously found to be a better predictor of IQ in VLBW/VP children rather than growth restriction (Gutbrod et al. Reference Gutbrod, Wolke, Söhne, Ohrt and Riegel2000). Biological factors explained slightly more variance in academic achievement of SGA VLBW/VP adolescents whereas IQ explained slightly more variance in AGA VLBW/VP adolescents' academic achievement, although this was not a significant difference. Growth restriction is associated with multiple complications in pregnancy ranging from smoking to high blood pressure leading to insufficient energy supply via the placenta (Barker, Reference Barker1998). IUGR leads to additional developmental disturbances in brain development on top of those associated with preterm birth, in particular affecting later occurring cortical growth relevant for attention control (Breslau et al. Reference Breslau, Miller, Breslau, Bohnert, Lucia and Schweitzer2009, Reference Breslau, Breslau, Peterson, Miller, Lucia, Bohnert and Nigg2010; Volpe, Reference Volpe2009). Prematurity, on the other hand, may have a more pronounced impact via neurofunctional structures (Volpe, Reference Volpe2009; Johnson et al. Reference Johnson, Hollis, Kochhar, Hennessy, Wolke and Marlow2010).
ADHD is characterized by heterogeneous aetiological subtypes and symptoms may be best understood from a developmental perspective with dynamic multiple pathway assumptions (Sonuga-Barke & Halperin, Reference Sonuga-Barke and Halperin2010). Neurobiological studies and advances in serial magnetic resonance imaging in the neonatal period provide new insights into neurological mechanisms underlying ADHD (Hintz & O'Shea, Reference Hintz and O'Shea2008). For example, ADHD inattentive subtype may indicate specific neurofunctional deficits in attentional networks in premature children (Johnson et al. Reference Johnson, Fawke, Hennessy, Rowell, Thomas, Wolke and Marlow2009) that may be attributed to persistent microstructural white matter disturbances (Nagy et al. Reference Nagy, Westerberg, Skare, Andersson, Lilja, Flodmark, Fernell, Holmberg, Bohm, Forssberg, Lagercrantz and Klingberg2003; Constable et al. Reference Constable, Ment, Vohr, Kesler, Fulbright, Lacadie, Delancy, Katz, Schneider, Schafer, Makuch and Reiss2008). At the same time, neurological problems of children diagnosed with ADHD may explain lifelong academic underattainment (Biederman et al. Reference Biederman, Petty, Fried, Kaiser, Dolan, Schoenfeld, Doyle, Seidman and Faraone2008c) and adult ADHD patients show structural abnormalities in the attention and executive function cerebral systems (Makris et al. Reference Makris, Buka, Biederman, Papadimitriou, Hodge, Valera, Brown, Bush, Monuteaux, Caviness, Kennedy and Seidman2008). Functional imaging studies that are possible during early brain development in preterm infants may shed light on the origins of later attention problems (Kapellou et al. Reference Kapellou, Counsell, Kennea, Dyet, Saeed, Stark, Maalouf, Duggan, Ajayi-Obe, Hajnal, Allsop, Boardman, Rutherford, Cowan and Edwards2006; Volpe, Reference Volpe2009; Nosarti et al. Reference Nosarti, Murray and Hack2010). If the mechanisms underlying academic underachievement are similar in VLBW/VP and the general population of children, the study of preterm children may help to understand the global pathways from early brain development and dysfunction to attention problems and academic underachievement.
In contrast, hyperactivity/impulsivity conferred no additional risk to academic attainment, as these behaviour problems may imply less severe neurological and processing impairments (Willcutt et al. Reference Willcutt, Doyle, Nigg, Faraone and Pennington2005). Thus, identifying neuropsychological subtypes might contribute to the diagnostic value of separate ADHD aetiological subtypes (Lambek et al. Reference Lambek, Tannock, Dalsgaard, Trillingsgaard, Damm and Thomsen2010).
Strengths and limitations
This is the first longitudinal study to examine ADHD subtypes and their impact on academic achievement using multiple data sources and continuous and categorical measures in VLBW/VP children. In contrast to previous studies of ADHD in VLBW/VP children that typically relied on questionnaires such as the CBCL (Bohnert & Breslau, Reference Bohnert and Breslau2008; Delobel-Ayoub et al. Reference Delobel-Ayoub, Arnaud, White-Koning, Casper, Pierrat, Garel, Burguet, Roze, Matis, Picaud, Kaminski and Larroque2009), child behaviour was evaluated on multiple measures by independent raters. Parents and teachers do not rate behavioural difficulties the same (Anderson et al. Reference Anderson and Doyle2003; Shum et al. Reference Shum, Neulinger, O'Callaghan and Mohay2008); thus data obtained from different sources substantially increases reliability and validity (Crystal et al. Reference Crystal, Ostrander, Chen and August2001). In addition, the rates of ADHD diagnoses in the full-term sample correspond with German ADHD prevalence rates (Huss et al. Reference Huss, Holling, Kurth and Schlack2008).
Furthermore, while 76% of the VLBW/VP participated in the 13-year follow-up, participation with complete datasets for the various measures of ADHD was lower across all four assessment points (63%). Those who participated did not differ in birth weight, gestation or neonatal risk from drop-outs and were originally group matched to the control children. We had to exclude non-German speaking parents and their children, as we would have needed a range of different language interpreters to code their verbal behaviour and different language versions of the same IQ test which were not available. Whereas this can be seen as a caveat of this study it has resulted in increased internal validity.
With regard to the timing of our data collection, our VLBW/VP and full-term children represent a sample without confounding therapeutic effects. During the early 1990s very few children received pharmacological treatment for ADHD in Germany (Schubert et al. Reference Schubert, Lehmkuhl, Spengler, Döpfner and von Ferber2001). Accordingly, in the present study only 1.1% of the participating VLBW/VP and 1.4% of the control children received treatment including psychotherapy or medication. Thus, our findings can be described as natural observations not confounded by treatment bias.
Theoretical and practical implications
Our study provides further evidence for the existence of different aetiological subtypes of ADHD (Coghill et al. Reference Coghill, Nigg, Rothenberger, Sonuga-Barke and Tannock2005). Martel et al. (Reference Martel, von Eye and Nigg2010) proposed to assess inattention independently from general ADHD risk as it may represent a distinct profile. We showed that the distinction in subtypes is not only reasonable in the general population but also in VLBW/VP children, with a higher occurrence of ADHD inattentive subtype in the latter.
Early identification of specific components of the disorder, especially in at-risk groups, is essential for effective prevention strategies. Compared with the DSM-IV diagnosis of ADHD inattentive subtype, the observational TRCB and TEAM ratings of child attention at 6 and 8 years most strongly predicted academic success 5 to 7 years later. This further validates the contribution of structured behavioural observations in research and clinical practice to detect ADHD-related symptoms (Huss et al. Reference Huss, Holling, Kurth and Schlack2008). Furthermore, ADHD may be accurately characterized as a dimension rather than a categorical diagnosis (Angold & Costello, Reference Angold and Costello2009; Lahey & Willcutt, Reference Lahey and Willcutt2010; Sonuga-Barke & Halperin, Reference Sonuga-Barke and Halperin2010; Krueger & Markon, Reference Krueger and Markon2011). Behaviour ratings such as the TRCB and TEAM may be implemented as sensible practice tools to identify children that may profit from early intervention. On the basis of our findings, we would recommend both the TRCB and TEAM measures of attention as two valuable alternatives: (1) the highly cost and time effective TRCB; and (2) the TEAM consensus rating combining several informants' input. Observational measures of attention during standard testing have the added advantage of detecting subclinical levels in children that are nevertheless relevant for learning and essential to reliably predict academic achievement.
In conclusion, attention is an important prerequisite for learning. In both VLBW/VP and full-term children poor attention, rather than hyperactivity/impulsivity, is an independent predictor of subsequent academic underachievement. As ADHD inattentive subtype and cognitive impairments are frequent in VLBW/VP children, their study may provide an excellent model for understanding the neurofunctional pathways from early brain development and dysfunction to attention problems and academic underachievement.
Supplementary material
For supplementary material accompanying this paper visit http://dx.doi.org/10.1017/S0033291712001031.
Acknowledgements
This study was funded by grants JUG 14 and 01 ER 0801 from the Ministry of Education and Science (BMBF) in Germany. We are grateful to all research assistants, psychologists and paediatricians who collected the data and to the parents and their children for their participation.
Declaration of Interest
None.