Increasing antibiotic resistance is a global health threat that is associated with increased mortality and increased healthcare costs. In addition, antibiotics are a common cause of severe adverse effects, including Clostridioides difficile infection (CDI).Reference Dantes, Mu and Hicks1 In some geographic locations, including South Carolina and Minnesota, community-associated CDI (CA-CDI) now represents the majority of CDI cases.Reference Lessa, Mu and Winston2,Reference Younas, Royer and Weissman3
Previous studies have reported higher incidence rates of CA-CDI in women than in men.Reference Kutty, Woods and Sena4 This cross-sectional population-based study examines whether this difference in CA-CDI rates across genders is associated with ambulatory antibiotic prescription rates.
Methods
Surveillance population and case definition
Ambulatory antibiotic prescription rates in South Carolina residents aged 18–64 years were estimated using Medicaid and State Employee Health Plan pharmacy claims. Aggregated rate data were available from January 1, 2015, to December 31, 2015. These data were estimated to represent approximately one-third of the South Carolina population in this age group. Individuals aged >64 years were not included in the study because these databases represent only a small proportion of antibiotic prescriptions in this age group.
CA-CDI cases were identified from National Healthcare Safety Network (NHSN) and South Carolina Infectious Disease and Outbreak Network (SCION) through complete enumeration of South Carolina population of the same age and study period. CDI events with missing age or gender (12% of records reported) were excluded from the study.
A CDI case was defined as a positive stool C. difficile toxin antigen or molecular assay obtained from a South Carolina resident aged 18–64 years during the study period. Only first and recurrent episodes after 8 weeks of the initial episode were included in the incidence rate analysis. CDI cases were defined as community associated, if the positive stool specimen was collected in an ambulatory setting or within 3 calendar days of hospital admission in a person with no documented overnight stay in a healthcare facility during the 12 weeks before the specimen was collected.Reference Younas, Royer and Weissman3
Of 65 laboratories in South Carolina, 40 (61%) reported using nucleic-acid amplification test (NAAT) alone for the diagnosis of CDI during the study period as previously reported.Reference Younas, Royer and Weissman3
Data collection and categorization of the cases
Laboratories in South Carolina are required to report all positive C. difficile test results directly to SCION from stool specimens collected at hospitals, nursing homes, and ambulatory settings. Healthcare facilities, including acute-care hospitals, long-term acute-care hospitals, inpatient rehabilitation facilities, and emergency departments are also mandated to report CDI cases to the NHSN as NHSN Laboratory Identification (LabID) events.
In this study, if SCION identified a CDI event that matched the NHSN LabID event date, duplicate elimination for the case was conducted using the NHSN variable for onset. The “leftover” SCION cases (ie, those that did not correspond to an NHSN event) were linked to hospital discharge billing data to determine site of acquisition of CDI.
Statistical analysis
Overall, age group–specific and gender-specific incidence rates of CDI and antibiotic prescription fill rates were calculated using US Census Bureau estimates for the population of South Carolina in 2015. Incidence rates of CA-CDI were calculated for both men and women aged 18–39 years and 40–64 years before and after adjustments for antibiotic prescription rates in the same gender and age group. Confidence intervals (CI) were used to determine statistical difference in incidence rates across genders within the same age group.
Results
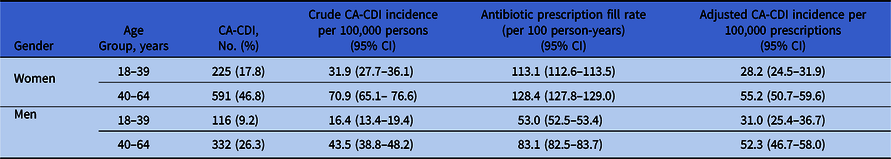
During the 12-month study period, 1,264 CA-CDI cases in South Carolina residents aged 18–64 years were identified, including 816 cases (65%) in women and 448 cases (35%) in men. The crude incidence rate of CA-CDI was higher in women than men in the two age groups: 18–39 years and 40–64 years. Similarly, antibiotic prescription rates were higher in women than men in the two respective age groups (Table 1).
Crude and Adjusted Incidence Rates of Community-Associated Clostridioides difficile Infection Across Genders and Age Groups in South Carolina in 2015

Note. CA-CDI, community-associated C. difficile infection; CI, confidence interval.
After adjustments for antibiotic prescription rates, there was no significant difference in the incidence rates of CA-CDI per 100,000 prescriptions between women and men aged 18–39 years (28.2 [95% CI, 24.5–31.9] vs 31.0 [95% CI, 25.4–36.7]) or 40–64 years old (55.2 [95% CI, 50.7–59.6] vs 52.3 [95% CI, 46.7–58.0]), respectively (Table 1).
Discussion
The results of this study offer a potential explanation for the previously reported higher incidence rates of CA-CDI in women than men.Reference Lessa, Mu and Winston2,Reference Younas, Royer and Weissman3 Comparable incidence rates of CA-CDI between women and men after adjustments for antibiotic prescription rates support the idea that higher crude incidence rate of CA-CDI in women are likely due to their higher ambulatory antibiotic prescription rates, which may be due to increased healthcare utilization by women as compared to men.Reference Schlichthrost5
Women aged 18–64 years old have higher risks of uncomplicated and complicated urinary tract infections than men.Reference Al-Hasan, Lahr and Eckel-Passow6 Although this may provide one potential explanation for the difference in healthcare utilization and antibiotic prescriptions across genders, acute respiratory infections (ARIs) remain by far the most common indication for antibiotic use in the community. A prior study in England demonstrated that overall antibiotic prescription rates for ARI were higher in women than men. However, at the time of consultation for ARI, the proportion of patients who received antibiotics was comparable between the genders.Reference Gulliford, Moore and Little7 This finding suggests that women are more likely to present to ambulatory healthcare facilities with symptoms of ARI than men. Women in this age group may be more likely than men to have an established primary healthcare provider given frequent need for screening tests (eg, mammograms, PAP smears, etc). Alternatively, men aged 18–64 years old may be more reluctant than women to seek healthcare for ARIs and other minor infections.Reference Schlichthrost5
The association between ambulatory antibiotic prescription and CA-CDI provides opportunities for ambulatory antimicrobial stewardship.Reference Chitnis, Holzbauer and Belflower8 ARI is a well-recognized source of inappropriate ambulatory antibiotic prescription.Reference Gill, Fleischut and Haas9 In addition to conventional antimicrobial stewardship efforts in patient and healthcare provider education and improving adherence with established clinical management guidelines, the use of point-of-care diagnostic tests, such as C-reactive protein, has been associated with a reduction in antibiotic prescriptions for ARIs in ambulatory settings.Reference Cals, Butler and Hopstaken10 Encouraging the use of low-risk antibiotics (eg, nitrofurantoin and fosfomycin) over agents with high-risk of CDI (eg, fluoroquinolones and cephalosporins) for acute cystitis may reduce the incidence of CA-CDI in women. Dental clinics are another area of interest; one study reported that 15% of patients with CA-CDI had been prescribed an antibiotic by a dentist within the previous 12 weeks.Reference Chitnis, Holzbauer and Belflower8
The current study has several limitations. CDI was defined based on any positive C. difficile test regardless of symptoms, and NAATs have the potential for overdiagnosis of CDI and the inability to differentiate between colonization and true infection. In this study, we may have overestimated the incidence rate of CDI because most laboratories in South Carolina (61%) used only NAAT for diagnosis.Reference Younas, Royer and Weissman3 No inferences of individual-level association between an antibiotic exposure and development of CA-CDI can be made from this cross-sectional study, and this study was not designed to determine the antibiotic appropriateness. There are also limitations associated with using the Medicaid and State Employee health plan claims for antibiotic prescribing data. These data only account for the number of prescriptions filled at a pharmacy, and they do not assess whether the patient actually took the medication as prescribed. Finally, these databases represent only 2.5% of the state population >64 years of age, which necessitated the exclusion of elderly patients from this study. The exclusion of 12% of patients with missing demographics represents is another limitation of the study.
In summary, higher crude incidence rate of CA-CDI in women are may be due to higher ambulatory antibiotic prescription rates in women as compared to men. Robust syndrome-specific ambulatory antimicrobial stewardship interventions are needed to reduce inappropriate antibiotic prescriptions and, subsequently, CA-CDI rates.
Acknowledgments
We thank the advisory board members of the Antimicrobial Stewardship Collaborative of South Carolina for facilitating this study. We also thank all healthcare facilities and clinical laboratories in South Carolina for contributing data toward this manuscript. This study was approved by the South Carolina DHEC and the South Carolina Data Oversight Council (DOC). The findings of this report are those of the authors and do not necessarily represent the official position of the South Carolina DHEC, DOC, the South Carolina Department of Health and Human Services, or the South Carolina Public Employee Benefit Authority.
Financial support
This work was supported by a federal grant (Epidemiology and Laboratory Capacity Project K2) from the Centers for Disease Control and Prevention awarded to South Carolina Department of Health and Environmental Control.
Conflicts of interest
P.B.B. served as a research advisory board member of CutisPharma, Synthetic Biologics and on Advisory board and speaker’s bureau of Melinta Therapeutics. He also received a grant from ALK Abello, Inc. All other authors report no potential conflicts of interest.