





Dear Editor,
Anhedonia is a core and clinically significant symptom of major depressive disorder (MDD) and has been proposed as a predictor of poor antidepressant response (McMakin et al., Reference McMakin, Olino, Porta, Dietz, Emslie, Clarke, Wagner, Asarnow, Ryan, Birmaher, Shamseddeen, Mayes, Kennard, Spirito, Keller, Lynch, Dickerson and Brent2012). We therefore read Uher et al. (Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026) with great pleasure, as they reported that a three-item sensory anhedonia subscale of the Snaith-Hamilton Pleasure Scale (SHAPS), comprising items relating to enjoyment of bathing, pleasant scents, and scenic beauty, predicted symptomatic improvement during escitalopram treatment in the CAN-BIND-1 cohort (Uher et al., Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026). This subscale had not previously been assessed as a standalone measure. Emphasizing the translational utility of anhedonia and its subscales, alongside their relatively straightforward clinical applicability, this work may help optimize treatment strategies for MDD. Given the importance of identifying predictors of antidepressant response, as well as the recognized need to replicate post-hoc findings, we sought to test this association in an independent cohort.
We used data from the NeuroPharm-1 study (ClinicalTrials.gov: NCT02869035), an open-label escitalopram trial in 91 unmedicated adults (71% female; median age: 24 years, range: 18–56 years) with a moderate-to-severe MDD. Patients had a mean Hamilton Depression Rating Scale (HAMD) of 22.9 (SD: 3.4), a mean total SHAPS of 7.7 (SD: 3.2; scored: 0–14, with one point per endorsed item), and a mean SHAPS sensory subscale score of 7.0 (SD: 1.8; scored: 3–12, summed across the three items).
The proposed three-item sensory subscale demonstrated acceptable internal consistency (Cronbach’s α = 0.70; inter-item r = 0.34–0.53) and the items showed moderate, homogeneous associations consistent with a unidimensional structure. Although SHAPS was originally designed as a unidimensional measure of hedonic capacity and principal component analyses in depression have broadly confirmed this structure, two- to four-factor solutions have been reported in cross-cultural populations (Fresán & Berlanga, Reference Fresán and Berlanga2013; Martino et al., Reference Martino, Santangelo, Moschella, Marino, Servidio, Augimeri, Costabile, Capoderose and Cerasa2018). Zhang et al. compared six competing factor structures and found that the four-factor model, mapping onto interest/pastimes, social interaction, sensory experience, and food/drink, provided the best fit in both nonclinical and clinical samples (Zhang et al., Reference Zhang, Zhang, Fang, He, Fan, Luo, Zhang, Xiong, Luo, Wang, Yao and Wang2021). In Spanish and Italian validations, items 6 and 12 related to scent and beautiful landscapes consistently anchored the sensory factor, supporting the proposed sensory subscale (Uher et al., Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026).
The patients in NeuroPharm-1 were treated with 10–20 mg Escitalopram. Patients with intolerable side effects or a reduction in the 6-item HAMD subscale (HAMD6) of <25% at week 4 were offered to switch to duloxetine (15 switched). Four patients were deemed nonadherent based on plasma measures at week 8. Follow-up HAMD6 scores were therefore censored for nonadherent patients and after medication switch, yielding a sample of 83 patients with 233 observations at weeks 2, 4, and 8. The outcome was HAMD6, standardized to baseline mean and SD to allow direct comparison with Uher et al.’s (Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026) standardized MADRS coefficients.
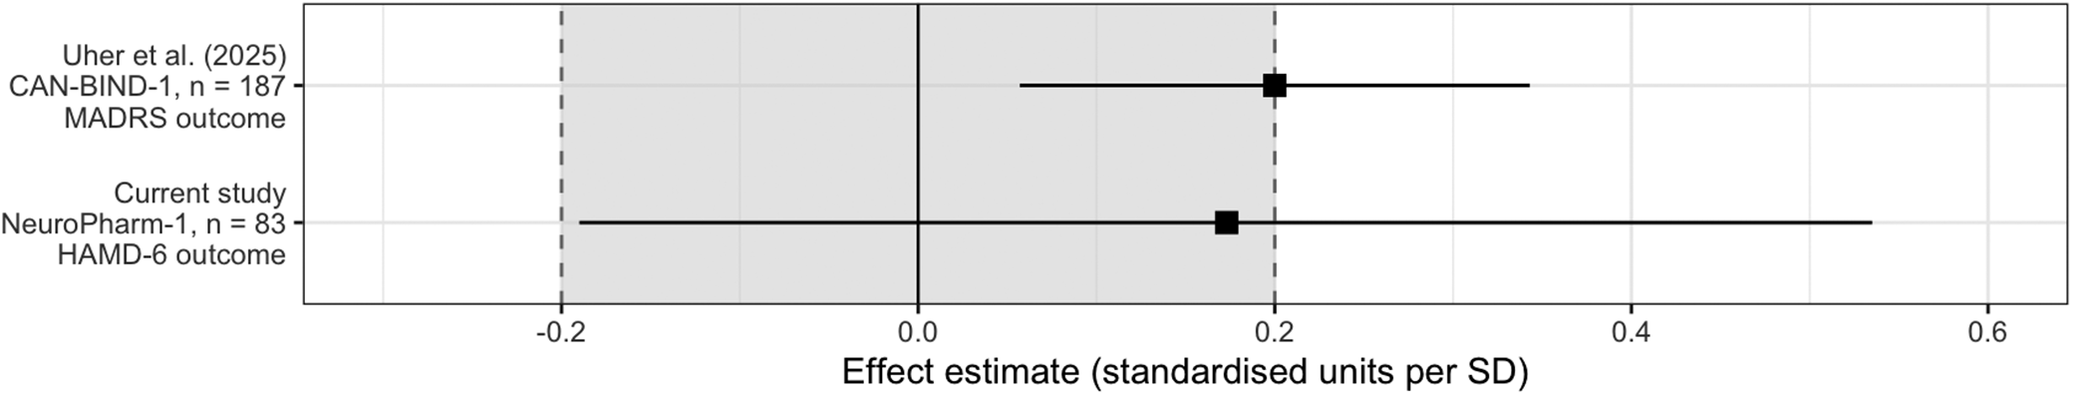
Pretreatment patients had a mean HAMD6 of 12.3 (SD: 1.7), which was significantly reduced to 5.9 (SD: 3.7) at week 8. We used a linear mixed-effects model with a random intercept for patients to regress HAMD6 trajectory on the sensory subscale, week, age, sex, and pretreatment HAMD6, replicating Uher et al.’s model structure (Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026). The SHAPS sensory subscale was not associated with treatment trajectory (β = 0.17 [−0.19; 0.54] units per SD, p = 0.35). Although similar to Uher et al.’s estimate of 0.20 units per SD, the effect was nonsignificant. Total SHAPS showed no association with outcome (β = −0.07 [−0.60; 0.47]), consistent with Uher et al.’s observation that the total score carries a smaller predictive signal than the sensory subscale. Complementary, we performed a Two-One-Sided Test for equivalence (Figure 1), defining the smallest effect size of interest as 0.20 standardized units to match that reported by Uher et al. (Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026). Equivalence was not established at this threshold: the 90% CI [−0.34, 0.68] exceeded the predefined bounds of [−0.20, 0.20], suggesting that an effect size comparable to that observed by Uher et al. remains plausible (p = 0.11 for the upper-bound test).
Effect estimates. Note: Effect estimates are standardized regression coefficients (standardized units per SD of the SHAPS sensory subscale) from linear mixed-effects models. Horizontal lines represent 95% confidence intervals. Equivalence bounds set to ±0.20, corresponding to Uher et al.’s (Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026) standardized effect size.

Figure 1. Long description
The forest plot features a horizontal x-axis labeled Effect estimate (standardised units per S D) with numerical markers at -0.2, 0.0, 0.2, 0.4, and 0.6. A vertical solid line is at 0.0, and a shaded gray region represents the equivalence zone between dashed vertical lines at -0.2 and 0.2.
* The top row is labeled Uher et al. Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026, C A N dash B I N D dash 1, n equals 187, M A D R S outcome. The data point is a black square located exactly at 0.2, with a horizontal confidence interval line extending from approximately 0.05 to 0.35.
* The bottom row is labeled Current study, NeuroPharm dash 1, n equals 83, H A M D dash 6 outcome. The data point is a black square located at approximately 0.17, with a wide horizontal confidence interval line extending from approximately -0.2 to 0.53.
These results are best interpreted as inconclusive rather than as a failure to replicate and are limited by our sample size (half of CAN-BIND-1). An adequate replication would require 150–180 patients. The sensory subscale’s internal consistency supports its use as a unidimensional measure, though its predictive validity remains to be confirmed in sufficiently powered independent samples. Nonetheless, the hedonic evaluation of pleasant scents has been observed to be enhanced by escitalopram, specifically in treatment responders (Kazour et al., Reference Kazour, Atanasova, Desmidt, Gissot, Lefevre, Camus, Belzung and El-Hage2023), whereas olfactory threshold and identification were unchanged, suggesting that sensory-specific pleasure may be a marker of improvement.
Sensory pleasure, the immediate hedonic response to stimuli such as scents, tastes, or visual beauty, is proposed as a primarily consummatory phenomenon mediated by opioidergic signaling within hedonic hotspots in the nucleus accumbens and orbitofrontal cortex, rather than by dopaminergic circuits that govern anticipatory wanting and motivation (Berridge & Kringelbach, Reference Berridge and Kringelbach2015). Although serotonergic projections from the raphe nuclei extensively innervate reward-related regions and modulate consummatory pleasure, SSRIs may paradoxically constrain hedonic reactivity by diminishing neural responses to both rewarding and aversive stimuli rather than selectively restoring positive affect (McCabe, Mishor, Cowen, & Harmer, Reference McCabe, Mishor, Cowen and Harmer2010). Consistent with serotonergic modulation of hedonic processing in depression, higher pretreatment 5-HT4-receptor levels have been linked to preserved sexual hedonic function in the same NeuroPharm cohort (Rasmussen et al., Reference Rasmussen, Larsen, Ozenne, Köhler-Forsberg, Stenbæk, Jørgensen, Giraldi and Frokjaer2023), supporting the view that differences in serotonergic architecture shape the hedonic response to SSRIs. Speculatively, patients with pronounced sensory anhedonia, for whom the world has quite literally lost its savor, may have critically reduced consummatory reward capacity, rendering serotonergic upregulation insufficient to restore hedonic experience and limiting SSRI efficacy. This could explain the differential predictive pattern reported by Uher et al. (Reference Uher, Rizvi, Quilty, Pavlova, Nunes, Foster, Lam, Milev, Müller, Taylor, Soares, Rotzinger, Kennedy and Frey2026), wherein sensory anhedonia predicted poorer response to escitalopram, while food and social anhedonia, putatively more dopaminergic in character, specifically predicted poorer response to adjunctive aripiprazole, together pointing toward the need for augmentation strategies that target dopaminergic or opioidergic pathways in patients with prominent baseline sensory anhedonia.
In conclusion, we found a consistent, though not statistically significant, estimated association between sensory anhedonia and escitalopram response in an independent MDD cohort. The confidence interval does not exclude the effect size reported by Uher et al., thus the effect, much like a pleasant scent in a crowded room, remains detectable in direction but difficult to isolate with precision. These findings neither confirm nor refute the original finding and underscore the need for an adequately powered replication to establish the utility of the sensory subscale.
Data availability statement
The data can be made available on request from the Centre for Integrated Molecular Brain Imaging (CIMBI) database (http://www.nru.dk/cimbidb) by contacting the database manager at cimbi@cimbi.dk.
Acknowledgments
The authors gratefully acknowledge investigators from the NeuroPharm-1 study.
Author contribution
Conceptualization: K.H.R.J., V.G.F., and M.B.J.; Formal analysis: K.H.R.J. and M.T.A.; Original draft: K.H.R.J. and M.T.A.; Review and editing: K.H.R.J., M.T.A., V.G.F., A.F.-D., and M.B.J.
Funding statement
The Innovation Fund Denmark (4108-00004B) supported the NeuroPharm-1 study. The Lundbeck Foundation funded K.H.R.J. (R279-2018-1145). M.T.A. was funded by Rigshospitalet (R289-A13003).
Competing interests
K.H.R.J. has given talks sponsored by H. Lundbeck; all honoraria were donated to StrongMinds.org. The other authors have nothing to disclose.

 Open access

