Introduction
Late-life depression (LLD) affects about 5–10% of individuals over the age of 60 years and is associated with reduced remission rates compared to depression in younger adults (Ismail et al., Reference Ismail, Fischer and Mccall2013; Mitchell and Subramaniam, Reference Mitchell and Subramaniam2005). Depression in older adults often presents with cognitive symptoms including executive dysfunction and memory impairment (Singh-Manoux et al., Reference Singh-Manoux2017; Wilkins et al., Reference Wilkins, Mathews and Sheline2009) that are associated with poor treatment response (Carpenter et al., Reference Carpenter2014; Tunvirachaisakul et al., Reference Tunvirachaisakul2017). Both objective cognitive impairment and subjective memory complaints increase the risk of Alzheimer’s disease (AD) and related dementias (Diniz et al., Reference Diniz, Butters, Albert, Dew and Reynolds2013; Singh-Manouxet al., Reference Singh-Manoux2017; Vega et al., Reference Vega2016). As such, the development of effective treatments targeting both mood and cognition in LLD with comorbid subjective memory complaints is urgently needed.
We conducted a 6-month double-blind randomized placebo-controlled trial to investigate the efficacy and tolerability of escitalopram combined with memantine (a cognitive enhancer) or placebo in 95 adults with geriatric depression (Lavretsky et al., Reference Lavretsky2019). Both treatment groups improved significantly in depressive symptom severity. The combination of escitalopram and memantine resulted in significantly greater improvement in executive function and delayed recall at 12 months compared to the escitalopram and placebo group. Given the 12-month latency period prior to the detection of cognitive improvement, improving prediction of which patients are likely to respond to memantine treatment has the potential to provide personalized treatment options.
Brain amyloid and tau deposits are associated with AD pathology, and positron emission tomography (PET) markers of amyloid and tau can be detected years before the diagnosis of cognitive impairment (Rosen et al., Reference Rosen, Hansson, Blennow and Zetterberg2013; Sperling et al., Reference Sperling2011). Brain amyloid imaging demonstrates slow and steady increases amyloid binding, especially in medial temporal, parietal, and frontal lobes, during the prodromal phase of AD (Cho et al., Reference Cho2016a; Palmqvist et al., Reference Palmqvist2017), which plateaus once dementia is diagnosed (Villemagne et al., Reference Villemagne2013).
Several ligands have been developed for use with PET as biomarkers that measure brain amyloid and tau deposits. In contrast to the [11C]Pittsburgh Compound-B and [18F]Florbetaben that are primarily reported to bind to amyloid but not tau (Klunk et al., Reference Klunk2004; Shin et al., Reference Shin, Lee, Kim, Kim and Cho2008), or [18F]MK-6240, a more recent tracer, which appears to mainly bind to tau (Hostetler et al., Reference Hostetler2016), 2-(1-{6-[(2-[fluorine18]fluoroethyl)(methyl)amino]-2-naphthyl}-ethylidene)malononitrile ([18F]FDDNP) and has a high binding affinity to both amyloid and tau (Murugan et al., Reference Murugan, Nordberg and Ågren2018). Binding of [18F]FDDNP in the medial temporal lobe has been associated with subjective memory complaints and objective measures of memory decline prior to the diagnosis of mild cognitive impairment (MCI) or dementia (Merrill et al., Reference Merrill2012; Small et al., Reference Small2012). [18F]FDDNP binding is increased and more widespread in later stages of dementia (Bejanin et al., Reference Bejanin2017; Palmqvist et al., Reference Palmqvist2017). Limited data are available on [18F]FDDNP binding in LLD, and no studies to date have investigated the relationship between [18F]FDDNP binding and antidepressant treatment response (Eyre et al., Reference Eyre2017; Kumar et al., Reference Kumar2011; Lavretsky et al., Reference Lavretsky2009).
In the current pilot study, we investigated whether baseline [18F]FDDNP binding can serve as a biomarker of clinical and cognitive response to escitalopram and memantine or placebo in older depressed adults. Specifically, we tested whether [18F]FDDNP binding in the medial temporal, parietal, and frontal lobes at baseline is associated with changes in mood, delayed recall performance, and executive functioning at posttreatment (i.e. 6 months) and naturalistic follow-up (12 months).
Methods
Participants
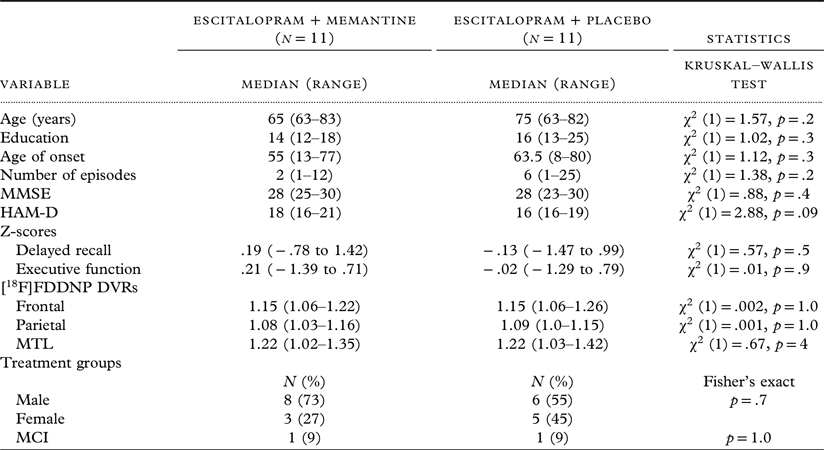
Twenty-two participants with LLD (>60 years, mean age = 72.32, standard deviation [SD = 6.92]; 14 male/8 female) who participated in the 6-month randomized controlled trial (RCT) (NCT01902004) underwent PET imaging at baseline at the University of California Los Angeles Ahmanson and Lovelace Brain Mapping Center (UCLA ALBMC) (Table 1). Of the 22 participants, 11 received escitalopram and memantine, and the remaining 11 received escitalopram and placebo. Eligibility criteria included: (1) age 60 or older, (2) diagnosis of major depressive disorder (MDD; DSM-5, American Psychiatric Association, 2013), (3) 24-item Hamilton Rating Scale for Depression (HAM-D; Hamilton, Reference Hamilton1967) score of 16 or higher, (4) absence of dementia as indicated by a Mini-Mental State Examination (MMSE; Folstein et al., Reference Folstein, Folstein and Mchugh1975) score of 23 or higher; and (5) endorsement of subjective memory complaints (affirmative response to the question, “Have you experienced memory problems over the past 6 months?” during phone screening). Exclusion criteria were (1) lifetime history of any psychiatric disorder except MDD, comorbid anxiety, or insomnia; (2) recent or current unstable medical or neurological disorders; (3) diagnosis of moderate or severe neurocognitive impairment; or (4) known allergic reaction to escitalopram or memantine. Contraindications to magnetic resonance imaging (MRI) or computer tomography (CT) scanning accompanying the PET scan further excluded potential participants, as well as refusal of the PET scan. All participants were free from cognitive enhancers at baseline. The study was approved by the Institutional Review Board at the University of California Los Angeles. Participants signed written informed consent prior to the in-person evaluation.
Patient baseline demographic, clinical test scores, and regional [18F]FDDNP binding

Diagnosis of MCI
MCI was diagnosed according to the following criteria: (1) a Clinical Dementia Rating scale score of .5 (Hughes et al., Reference Hughes, Berg, Danziger, Coben and Martin1982), indicating the stage between normal cognition and dementia; (2) subjective cognitive decline reported by the participant; (3) lack of significant functional impairment, and (4) objective impairment on neurocognitive tests. Objective impairment on neurocognitive testing was defined as scoring one SD below age- and education-specific norms on at least two screening memory tests (Hopkins Verbal Learning Test, Revised [either Total or Delayed scores] and Wechsler Memory Scale Third Edition, WMS-III, verbal paired associates [VPA] [either Total or Delayed scores]). Participants who met these criteria were classified as amnestic MCI (either single or multiple domains; Winblad et al., Reference Winblad2004).
Outcome measures
The primary outcome measure was change on the 24-item HAM-D. Composite cognitive scores representing delayed recall and executive function performance served as secondary measures. These scores were computed from the means of domain-specific tests derived from a complete neuropsychological test battery administered at baseline, posttreatment (6 months), and follow-up (12 months) (Lezac et al., Reference Lezac, Howieson and Loring2004). Our measure of delayed recall consisted of the means of the California Verbal Learning Test (Delis, Reference Delis2000) for long delayed free recall, the delayed recall score of the VPA test (Wechsler, Reference Wechsler1997), and the 30-minute delayed recall of the Rey–Osterrieth Complex Figure Test (Meyers and Meyers, Reference Meyers and Meyers1995). The executive function score was composed of the Trail-Making Test part B (time to completion; Reitan and Wolfson, Reference Reitan and Wolfson1988), the Stroop interference score (time to completion; Golden et al., Reference Golden, Marsella and Golden1975), and the raw score of the F-A-S verbal fluency test for verbal fluency (Benton et al., Reference Benton, Hamsher, Varney and Spreen1983). Raw scores were transformed to z-scores for each individual test score of interest, and subsequently averaged. For variables in which better performance was represented by lower values (e.g. Trail-Making Test), z-scores were reversed so that higher z-scores represented better performance for all measures.
Treatment protocol
Participants received a daily dose of 10 mg of escitalopram for the first month along with co-administered memantine or placebo. Within the first 4 weeks, memantine and a matched placebo dose were increased over time, starting with 5 mg a day and titrated up to 20 mg a day. The Clinical Global Impression (CGI; Guy, Reference Guy and Rush2000) scale was administered at baseline and follow-up visits to assess overall severity and improvement of depression. In cases where improvement was “minimal” or less (i.e. CGI score ≥3) at 4 weeks, the escitalopram dose was increased to 20 mg. The dose of the study drugs was lowered as needed depending on tolerability (minimum doses were 5 mg daily for memantine and 10 mg daily for escitalopram). Both participants and study staff (including the prescribing study physician) were blinded to treatment for at least 6 months (for additional details, see Lavretsky et al., Reference Lavretsky2019).
Neuroimaging protocol
A PET scan was performed for each patient at baseline. At the UCLA ALBMC, participants concomitantly underwent either an anatomical MRI or a CT scan to map [18F]FDDNP to individual neuroanatomy. A bolus of [18F]FDDNP (320–550 MBq) was injected via indwelling intravenous catheters, and subsequent 1-hour scans were performed using a Siemens-CTI system (Siemens CTI, Knoxville, TN, USA). [18F]FDDNP was prepared as described previously (Liu et al., Reference Liu2007). Decay correction and reconstruction were performed using filtered back projection (Hann filter, 5.5 mm full-width half maximum). Final images involved 63 contiguous sections with a 2.42-mm (EXACT HR+) intra-planedistance. Logan graphical analysis for determination of brain local distribution volume ratios (DVRs) was applied with the cerebellum as a reference region. High-resolution T1-weighted images were performed using either a 3T Siemens Tim Trio or Prisma system (Siemens, Erlangen, Germany) and a 32-channel head coil. The parameters, which were matched across scanners, were the following: a multi-echo MPRAGE scan 1 mm3 with isotropic voxel dimensions, 176 slices, TR = 2,150 ms, TE = 1.74, 3.6, 5.46, and 7.32 ms, TI = 1,260, FOV = 256 mm, matrix size = 256 × 256 mm, and a flip angle = 7°. Co-registration with either MRI or CT was used to reconstruct regions of interest (ROIs). Based on the existing literature on the distribution and progression of amyloid and tau (Cho et al., Reference Cho2016b; Palmqvist et al., Reference Palmqvist2017), we selected the frontal, parietal, and medial temporal lobes as ROIs (for detailed methods, see Small et al., Reference Small2006).
Statistical analysis
Due to the small sample size, nonparametric methods were used for all analyses. As recommended by Conover et al. (Conover, Reference Conover2012; Conover and Iman, Reference Conover and Iman1981), we used a rank transformation on all of the variables and then estimated standard general linear models. Changes in depressive symptoms (HAM-D) and cognitive performance (delayed recall and executive function) were examined using rank-based general linear models, with treatment group (escitalopram plus memantine vs. escitalopram plus placebo) as the predictor, controlling for baseline scores, as well as age and sex. To examine the association of baseline [18F]FDDNP binding with changes in these outcome measures, similar general linear models were estimated, with regional [18F]FDDNP binding levels, treatment group, and the interaction of treatment group with [18F]FDDNP binding as predictors. Since each ROI (frontal, parietal, and medial temporal lobe [MTL]) was examined with respect to three outcome measures (namely HAM-D, delayed recall, and executive function), we set the level of significance at p < .05/3, that is, .0167. Spearman’s correlation coefficients (r’s) are provided for all significant findings.
Results
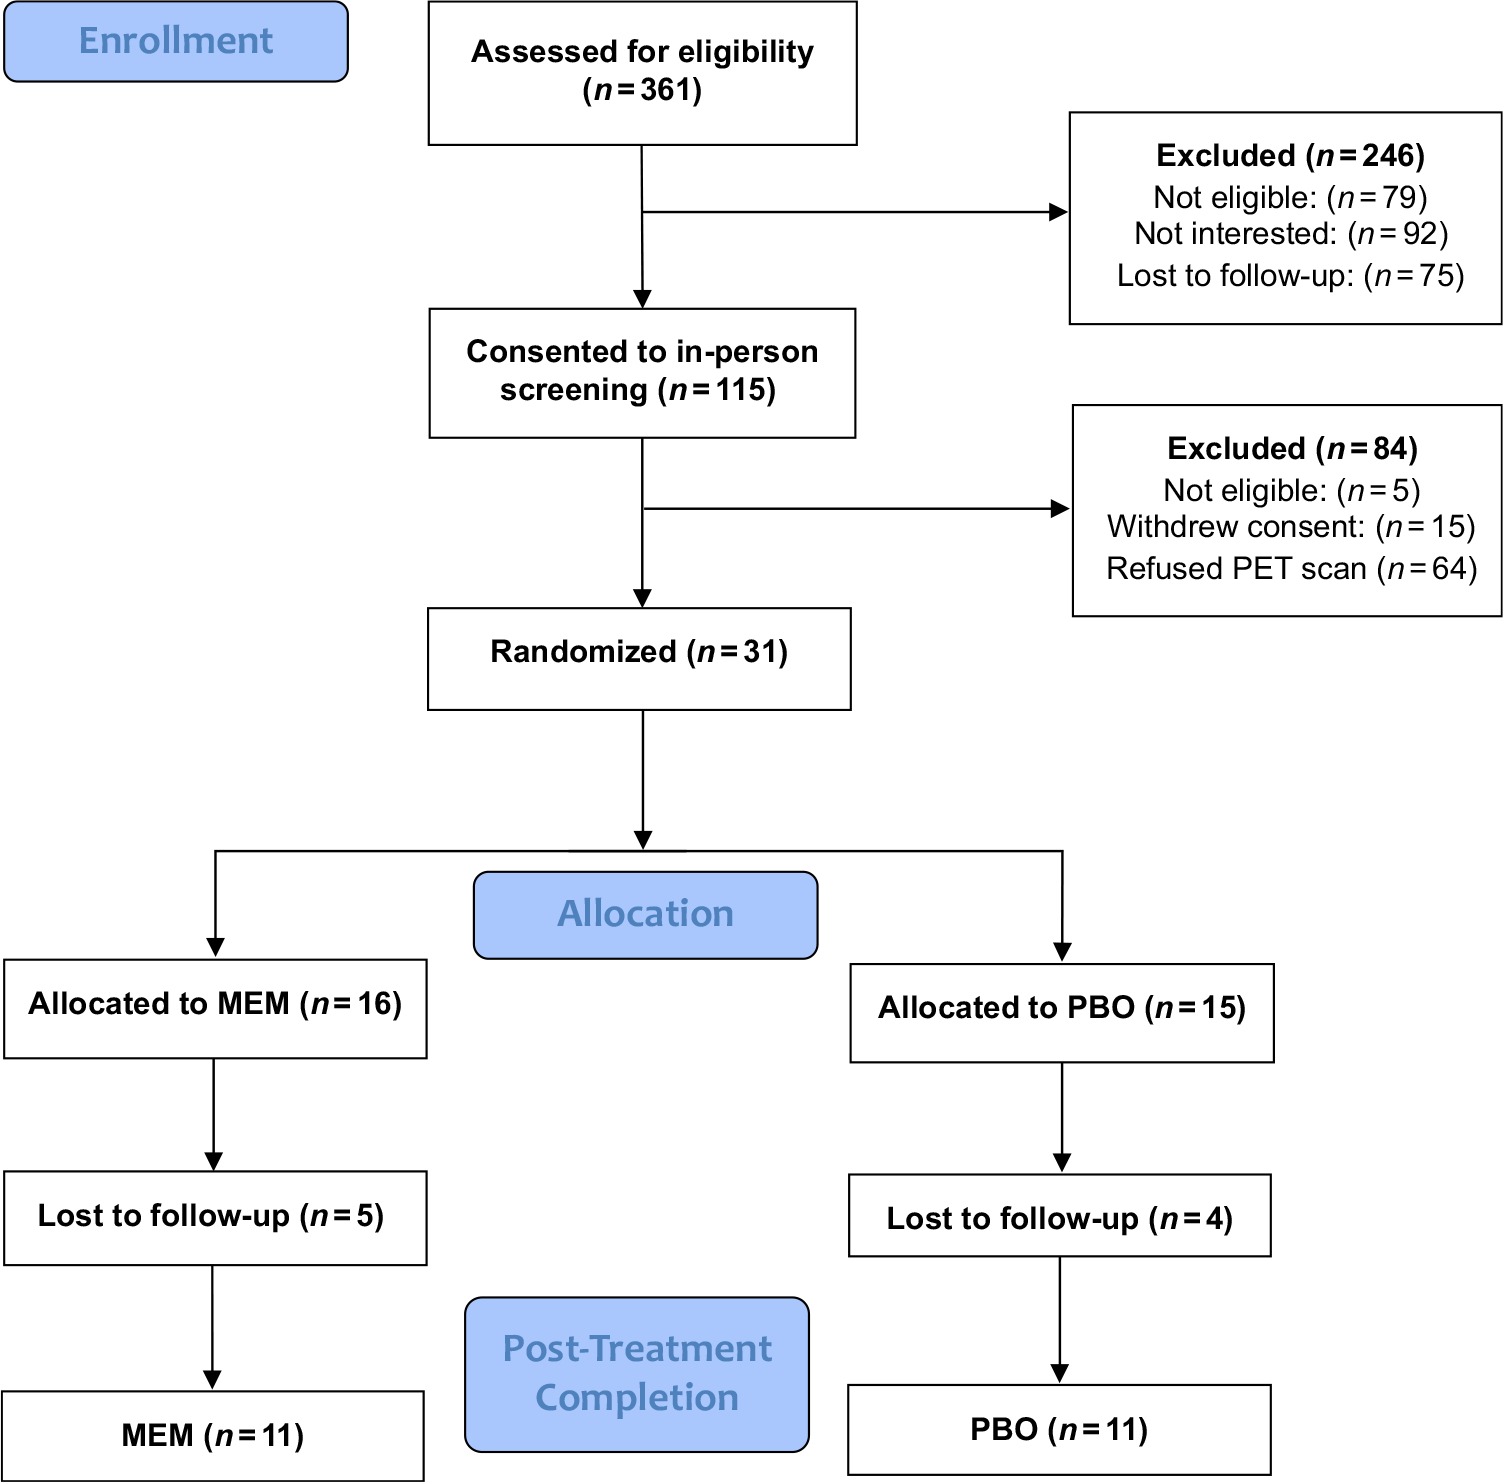
Of the 31 participants who completed baseline PET scans, 22 participants completed the 6-month follow-up and 13 completed the 12-month follow-up (please see CONSORT diagram, Figure 1). There were no differences in demographic and clinical variables at baseline between groups (Table 1). One participant in each group met criteria for MCI. The groups did not differ in the median dose of escitalopram (10 mg; range 10–20 mg). The memantine group received a median daily dose of memantine of 20 mg (range 5–20 mg). The groups did not differ in remission rates, defined as a HAM-D score of 6 or lower at follow-up(Fisher’s exact p = 1.0). Sixteen of 22 patients achieved remission at 6 months, 8 in each treatment group, and 5 per group sustained remission at 12 months. HAM-D scores improved significantly within each group from baseline to 6 months (memantine: signed rank statistic S = −33, p = .001; placebo: S = −33, p = .001), as well as from baseline to 12 months (memantine: S = −21, p = .01; placebo: S = −10.5, p = .03). Cognitive measures did not improve significantly within groups over time (S range = −12–7, p > .25; changes in scores from baseline are presented in Supplementary Table 1).
Consort diagram.

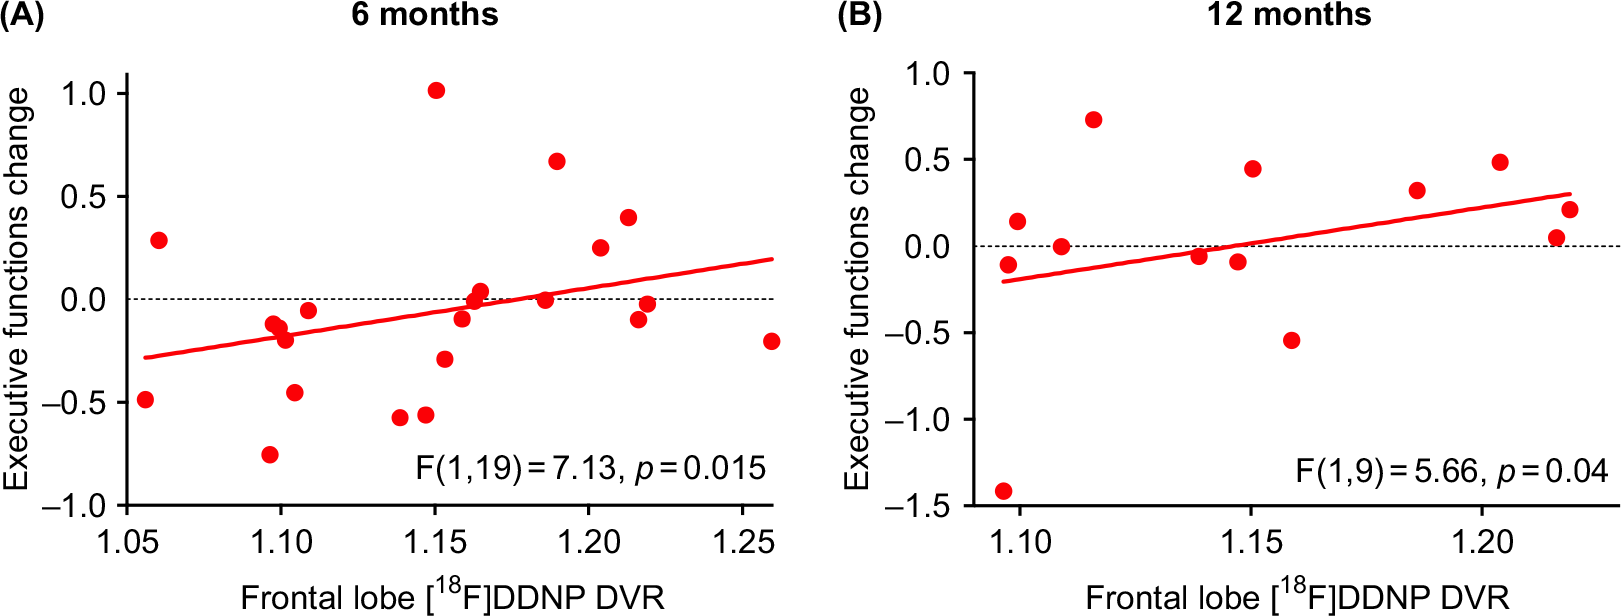
There was no between-group difference in regional [18F]FDDNP binding at baseline. Baseline [18F]FDDNP binding was not associated with change in HAM-D or change in delayed recall. However, greater frontal [18F]FDDNP binding was associated with greater improvement in executive function across groups at 6 months (F[1,19] = 7.13, p = .015, corrected p = .045, r = .53) (Figure 2A). This association was not significant at 12 months after correction for multiple comparisons (F[1,9] = 5.66, p = .04, corrected p = .12, r = .59; Figure 2B). The association of frontal [18F]FDDNP binding with change in executive function at 6 months continued to be significant, controlling for change in HAM-D in the model (F[1,18] = 7.70, p = .01). No other interaction or main effects were significant.
Higher [18F]FDDNP binding predicts improvement in executive function. (A) Frontal lobe [18F]FDDNP DVR binding was associated with improvement in executive function at 6 months across treatment groups (corrected p = .045). (B) At 12 months, this effect was no longer statistically significant after correction for multiple comparisons (corrected p = .12).

Discussion
Our study is the first to examine the role of in-vivo amyloid/tau PET binding as a biomarker of heterogeneity of antidepressant response in LLD. In this pilot study, we examined the relationship between baseline [18F]FDDNP binding and change in mood and cognition in older adults with major depression in a 6-month double-blind, placebo-controlled RCT comparing escitalopram and memantine to escitalopram and placebo with 12-month follow-up. We found that higher frontal lobe [18F]FDDNP binding at baseline was associated with greater improvement in executive function across groups at 6-month follow-up; this association was no longer significant at 12 months after correcting for multiple comparisons, possibly due to additional dropout.
In the parent RCT, we demonstrated that combined escitalopram and memantine therapy resulted in improved cognitive function at 12 months compared to escitalopram and placebo (Lavretsky et al., Reference Lavretsky2019). In this report of a smaller subsample with baseline PET imaging, we did not find group differences in cognitive or mood outcomes, which may be a consequence of reduced statistical power. However, we observed an association between increased baseline frontal lobe [18F]FDDNP binding and subsequent improvement in executive function, which may indicate improved cognitive resilience with antidepressant treatment, especially in those with greater accumulation of amyloid and tau markers at baseline. This observed association may be attributable to improvement in depressive symptoms. However, controlling for change in HAM-D score did not change the results, suggesting that the association between higher baseline binding and subsequent cognitive improvement is independent of improvement in depressive symptoms. Our findings are also consistent with studies of younger adults with MDD in which antidepressant treatment has been associated with improvement in executive function (Tian et al., Reference Tian2016; Wagner et al., Reference Wagner2018).
Previous studies suggested that [18F]FDDNP binding may serve as a biomarker of cognitive decline (Cole et al., Reference Cole2018; Jack et al., Reference Jack2013; Merrill et al., Reference Merrill2012; Small et al., Reference Small2012). The use of [18F]FDDNP in predicting clinical and cognitive outcomes in LLD is also supported by our prior studies demonstrating regionally increased [18F]FDDNP in LLD compared to healthy controls, relationships between regional [18F]FDDNP binding affinity and symptoms of depression, anxiety, and subjective memory problems, as well as a relationship between increased [18F]FDDNP binding over a 2-year period with memory decline across healthy older adults and those with MCI (Kumar et al., Reference Kumar2011; Lavretsky et al., Reference Lavretsky2009; Small et al., Reference Small2012). In our prior study, depression correlated with medial temporal lobe [18F]FDDNP binding in cognitively healthy older adults but not those with MCI (Lavretsky et al., Reference Lavretsky2009). Frontal, parietal, and medial temporal [18F]FDDNP binding at baseline has also been associated with decline in executive functions 2 years later in older adults with MCI or AD (Small et al., Reference Small2012). The same study found no associations between frontal, parietal, or medial temporal lobe [18F]FDDNP binding with changes in memory. Similar to these results, we did not find any associations between parietal and medial temporal [18F]FDDNP binding and executive functions or memory in our LLD sample. However, our results demonstrated that baseline [18F]FDDNP binding in frontal lobes at baseline was associated with improvement in executive functions over time. Because we are first to report this relationship of greater neuropathology in the frontal lobe at baseline to greater cognitive improvement, this finding will require replication. Nevertheless, our findings are suggestive that [18F]FDDNP binding may be useful for identifying those who are at greater risk for AD or related dementias and those who might derive a cognitive benefit from antidepressant treatment.
There are several limitations to this study. First, the small sample size restricted our ability to detect group differences in clinical and cognitive outcomes. Second, our sample was a fairly homogeneous group of mostly Caucasian and college-educated adults with relatively preserved cognition (only one participant per group met the criteria for MCI). Additional dropout of nine subjects from 6 to 12 months reduced the power to detect significant effects at 12 months, though the magnitude of the observed association was similar at 6 and 12 months. Although our approach was hypothesis-driven with the a priori hypothesis of previous findings of associations between the [18F]FDDNP binding in three specific ROIs with clinical and cognitive scores, our correction for multiple comparisons was lenient given the number of tests we performed. This may lead to an inflation of Type I error and should be interpreted with caution. Future studies examining the role of in-vivo PET markers of amyloid and tau will also include blood and CSF markers to fully understand the role of amyloid and tau in predicting antidepressant and cognitive response in LLD.
Despite these limitations, our findings suggest that [18F]FDDNP can serve as a biomarker to identify those candidates who are likely to experience improvement in executive functioning with antidepressant treatment. Larger trials are needed to further test the value of [18F]FDDNP binding as a biomarker of heterogeneity of treatment response in geriatric depression. Future longitudinal studies can provide more insight into the utility of [18F]FDDNP binding as a biomarker of cognitive decline in older adults with major depression by including the measures of the plasma and CSF biomarkers of tau and amyloid and, ideally, followed by postmortem neuropathological confirmation studies. Continued investigation of biomarkers of brain aging will be useful for identifying those most likely to benefit from treatments targeting both depression and cognition. Research in this area is essential to advancing the field of personalized medicine and increasing the quality of available treatments for depressed older adults at high risk of cognitive decline.
Conflicts of interest
Dr. Lavretsky reports grant funding from Allergan. Drs. Small and Barrio are co-inventors of [18F]FDDNP, which UCLA has licensed to Ceremark Pharma. They are among the co-founders of and have equity interest in Ceremark Pharma. Dr. Small also reports having served as an advisor and/or lecturer for AARP, Acadia, Activis, Allergan, Avanir, Forum, Genentech, Gerontological Society of America, Herbalife, Janssen, Lilly, Lundbeck, Novartis, Otsuka, Pfizer, Roche, and RB Health and received grant funding from The Wonderful Co. The other authors have no conflicts of interest to declare.
Source of funding
This study was funded by the National Institute of Health (R01MH097892), and partially, by the National Center for Complementary & Alternative Medicine (AT009198).
Description of authors’ roles
HL and PS conceived of the design of the study, conducted the study, and obtained funding. GS and JRB performed PET imaging and analyses. LE performed neuropsychological testing and analyses. BK-S and KN guided the neuroimaging analysis. PS and BK-S performed the statistical analyses. HL, PS, BK-S, and KTL interpreted the study findings. All authors contributed to the manuscript writing and signed-off on the submitted version.
Acknowledgments
Special thanks to Dr. Jie Liu for the synthesis of [18F]FDDNP for these studies, to Dr. KP-Wong who performed data processing and quantitative DVR analysis of the PET images, and to John Williams at the UCLA Nuclear Medicine Clinic who performed the [18F]FDDNP PET scans.
Supplementary material
To view supplementary material for this article, please visit https://doi.org/10.1017/S1041610219002047.