1. Introduction
Finding the right balance between cost containment, promoting choice and quality and preserving or enhancing equity of access to care, has been one of the major drivers of health reform in most European countries. Although the objective of universal coverage has been attained in most countries, this has not always been sufficient to ensure equity of access by need and not by ability to pay or an equitable distribution of supply. At the same time there has been increasing political pressure to re-organise delivery in order to improve the quality of publicly financed health care, particularly by reducing waiting times and giving more choice to patients. However, the nature and intensity of these problems seem to be largely determined by the basic social security model financing each country’s healthcare system.
On the one hand, it is often said that Beveridge-type, tax-based national health systems ensure more equitable access, as they are universal in coverage and tend to minimise the problems of risk selection and cost shifting by healthcare providers and insurers. Although these systems also appear to perform well in containing overall healthcare costs, they have traditionally performed less well in terms of offering choice for users and have long waiting times. Thus in recent years the major emphasis of reform in countries with these systems, such as the UK, has been to increase choice and reduce waiting times.
On the other hand, one of the hallmarks of Bismarck-type, insurance-based, systems is the plurality of providers and abundance of choice. However, the major challenge for these systems is cost containment. As a result, there has been a noticeable increase in the level of government control and regulation, which may be constraining choice and/or access. For example, both France and Germany are trying to control the ‘choice’ of providers by introducing ‘soft’ (i.e. optional) gatekeeping arrangements.
These trends could suggest that a process of convergence in healthcare systems is taking place and the difference between Beveridge and Bismarck is no longer as significant. At the same time, there may be other key contextual parameters of the health system, which need to be taken into account in addressing the specific problems in each country, such as payments to physicians for public and private patients (e.g. Flood and Haugan, Reference Flood and Haugan2010). It could be argued that these reforms have mainly involved adjustments at the margin and the more fundamental parameters, which distinguish each system remain largely intact.
Therefore, this paper focuses on three questions: Are there currently systematic differences in performance of Beveridge and Bismarck-type systems? What are the key parameters, beyond the financing base of the healthcare systems, which underlie these differences? Have recent reforms adequately addressed the observed weaknesses of each system and so eroded previous differences between them?
The paper consists of four further sections: Section 2 gives an overview of differences in performance of selected Beveridge and Bismarck systems (Denmark, England, France, Germany and Sweden); Section 3 identifies each system’s key structural parameters that may explain these differences using a common framework to describe different working practices, values and capacity underlying each system; and Section 4 reviews a number of recent reforms addressing problems with access and choice, and common to each system, with the aim of identifying organisational and political requirements for these reforms to be successful.
2. Comparison of health system performance in five countries
The principal objectives of the healthcare system in all countries are to optimise health outcomes, quality of care, ease and equity of access, subject to the constraint of containing costs. The overall performance of a health system can be measured by the extent to which these objectives are being met. Within this very broad framework, the performance of two Bismarck (Germany and France) and three Beveridge-type (Denmark, Sweden and England) systems is assessed in this section.
Performance assessment of healthcare systems is a complex task, which needs to take into account a large number of parameters simultaneously. Our aim here is not to provide a full performance assessment of each system but to review a limited set of comparable data to test the hypothesis that there are systematic differences between Bismarck and Beveridge-type systems with respect to different performance dimensions.
We select a number of different indicators for each dimension to cover different aspects of the health system and/or different segments of the population. The choice of indicators is also determined by the availability of comparable cross-country data, which is often problematic. We then calculate a score for each country and on each dimension based on their average performance rank on a scale of one to five.
2.1 Cost containment
In Figure 1, we compare the cost of resources consumed by each healthcare system with three common indicators: total healthcare expenditure, public health expenditure and total pharmaceutical expenditure, all expressed as a percentage of GDP (gross domestic product). Together, these three indicators give an idea about the opportunity cost of the resources used by the health sector within each country. In 2006, the two Bismarck-type systems, France followed by Germany, had the highest total and public healthcare expenditure as percentage of GDP. They both devoted about 11% of their GDP to the health sector. The share of public health expenditure in France is slightly higher than in Germany (9% against 8.2%). Of three Beveridge-type systems, the United Kingdom had the lowest total and public health expenditure (about 8% and 7% of GDP), but there were little differences between Denmark and Sweden (about 9% and 8% of GDP). In terms of pharmaceutical expenditures, however, the differences were more marked. The share of pharmaceutical expenditure in GDP in France (1.8%) and Germany (1.6%) was more than twice as high as in Denmark (0.8%), which had the smallest share; Sweden (1.3%) and the UK (1.2%) were in the middle.
Total, public health and pharmaceutical expenditures in five countries, 2006Source: OECD Health data, 2008.

2.2 Health outcomes
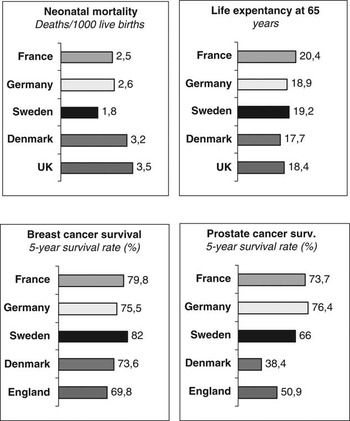
Defining a single health outcome measure combining various aspects of health status is both challenging and problematic.Footnote 1 Here, we use three commonly used health outcome indicators to cover different situations: neonatal mortality, life expectancy at age 65- and 5-year cancer survival rates for women (breast) and men (prostate) (Figure 2). In 2006, Sweden had the lowest neo-natal mortality rate and the UK the highest (1.8% and 3.5% per 1000 live births). France had the highest life expectancy at age 65 years (20.4%) and Denmark the lowest (17.7%). Sweden also had the highest five-year survival rate for breast cancer, followed closely by France, and England the lowest (82%, 80% and 70%). Germany had the highest five-year survival rate for prostate cancer and Denmark the lowest (76.4% and 38.4%). Hence, there was no clear-cut distinction in terms of these outcomes between Beveridge and Bismarck-type countries. France and Sweden consistently outperform the UK and Denmark while Germany is typically placed in between.
Health outcomes in five countries, 2006 Source: OECD Health data, 2008, relative survival rates from Eurocare-3, aged standardised, diagnosed between 1990–1994 followed up until 2000.

2.3 Responsiveness
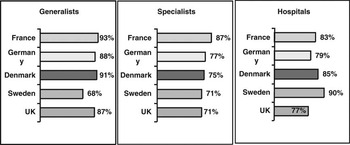
Increasingly, attention is being paid not just to improving health outcomes but also to the responsiveness of healthcare provided (OECD, 2006). This is often assessed in terms of patient’s experience with health care. Figure 3 provides the results from a recent European survey on quality of care (Eurobarometer, 2007). The question is asked on the quality of three types of care: hospital, generalist and medical and surgical specialists.Footnote 2
Responsiveness: satisfaction with the care provided. (% of persons reporting that the quality of the following are fairly or very good)Source: Eurobarometer, 2007.

The percentage of people reporting that quality of general practitioner (GP) and specialist care is fairly or very good is the highest in France, followed by Germany and Denmark closely. The picture is somewhat different for hospital care: the percentage of people reporting that quality is good is the highest in Sweden, followed by Denmark while France is in the middle just above Germany and the UK. Interpretation is problematic as peoples’ assessment of quality depends on a mixture of things including their expectations.
2.4 Access to care
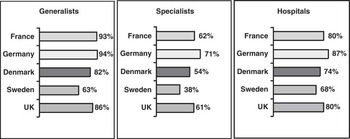
Ensuring that all segments of the population can obtain health care at the right time and place is also being seen as an important objective. Figure 4 gives the percentage of people reporting that access is fairly easy or very easy for each type of care. Sweden performs particularly poorly on this measure with one-third of the population reporting that access to generalists is difficult and with this proportion rising to two-thirds for specialist care. Germany, on the other hand, performs significantly better in terms of access to all three types of care. Surprisingly, however, the percentage of people reporting that access is difficult to hospitals and specialists is very similar in France and in the UK. It is possible that people’s expectations differ from country to country, which might explain some of these results. Nevertheless, the limited survey data available from France support the fact that access to certain types of specialist care, outside of the Parisian region, could be quite difficult because of the unequal distribution of specialists (ESPS, 2004).
Access to care: percentage of persons reporting that it is fairly or very easy to gain accessSource: Eurobarometer, 2007.

In order to obtain more objective information on the problems of access in these systems, we tried to gather information on waiting times for primary/secondary care in each country. However, it is very difficult to compare these data as the way the information is collected differs significantly between countries. The perceived wisdom is that long waiting times are a problem of Beveridge-type systems. The fact that France and Germany do not collect any data on waiting times is sometimes used to argue that this is not a problem in these counties (Scilliani and Hurst, Reference Scilliani and Hurst2003). However, at least as far as France is concerned, there are some indications that access to elective surgery in some regions could be a problem for those who are not willing to pay the extra fees asked by private providers. Moreover, data suggests that the size of the problem varies between the three countries with Beveridge-type systems, as well as over time within these countries (e.g. in England between 2001 and 2008).
2.5 Affordability
To achieve equity, ideally access to care should be determined by need and not by socio-economic status or availability of health services. One criterion to judge how fairly health care is distributed will be its financial burden for users. The Eurobarometer survey provides some information on people’s perception on affordability. Figure 5 presents the percentage of the population reporting that these services are not affordable.Footnote 3
Affordability of health care: percentages of persons reporting the following are not very/not at all affordable

In 2007, in the two Bismarck-type systems, where there is often co-payment, the percentage of the population reporting that care is not affordable was significantly higher than the Beveridge ones. In particular, one out of four people in Germany reported that hospital care was not affordable, while one out of two reported specialist care was not affordable in France. In marked contrast, only 1% of the population in Denmark reported that hospital and/or generalist care was not affordable. Paradoxically, about 13% of people in the UK reported that specialist care was not affordable even though in principle it is free at the point of delivery. This probably reflects travel/time cost for some people.
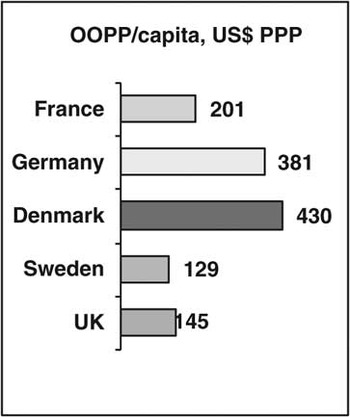
Affordability can also be compared on a more objective basis by looking at out-of-pocket expenditures (Figure 6). Despite Denmark’s well-rated access to GP and specialist care, it has the highest per capita out of pocket payments (after adjusting for differences in the cost of living). This is mainly due to co-payments for pharmaceuticals (despite exemptions) and for dentistry, physiotherapy, etc.
OOPP per capita, 2006Source: OECD Health Data 2008. Authors’ estimation for the UK based on data from the OHE and the OECD. OOPP, out-of-pocket payments.

2.6 Putting the performance pieces together
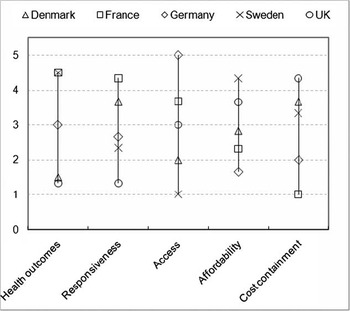
In order to provide a more synthetic picture of how countries vary across the dimensions presented here, we have constructed a simple score for each country on each of the five performance dimensions taking their average ranks on a scale of one to five for each sub-indicator. Figure 7 presents the positioning of countries on the different dimensions. We calculated the country ranks in a way that for each dimension (on the horizontal axe) the better performers get higher points, the highest point (best performance) being five. For example, concerning cost containment the UK has the highest score (best performer) and France has the worst, given their average ranking on the three indicators presented above (total, public health and pharmaceutical expenditures).
Health system performance: comparison of five countries

These comparisons illustrate systemic differences on three dimensions: the Beveridge-type appear to perform better on cost containment and affordability; and Bismarck-type systems appear to perform better on access to care (defined as availability of services when required). There appears, however, to be no clear systemic differences in performance on health outcomes and responsiveness. Sweden and France consistently perform better than the others on health outcomes, whereas France and Denmark on responsiveness.
3. Comparison of structural parameters
The previous section has highlighted a number of similarities but also significant differences within Bismarck and Beveridge systems in health performance, which need to be explained. There may be other aspects of health systems, which need to be examined simultaneously for understanding these differences in performance and for developing appropriate policy responses. This section compares the main structural differences between the Beveridge and Bismarck systems in their organisational design, which are likely to affect both their performance and resource use.
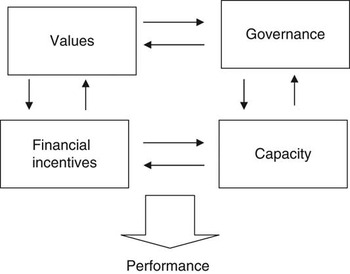
In order to conceptualise the design and structure of each country’s health system, we distinguish four broad features: the governance of the system, its underlying values, financial incentives for the providers and consumers and the capacity of the system. In reality, each of these would consist of further layers of parameters. For example, the system of governance, among other things, refers to the degree of decentralisation in decision-making, which could differ by type of service (e.g. hospital and ambulatory care in a single system).
We would also suggest that these key features are not independent of each other (Figure 8). For example, both the ‘governance’ structure and the way doctors are paid may influence capacity (in terms of doctor supply), but available capacity may also have an influence on how payment mechanisms are adjusted. This has implications for cost, quality and equity of health care as well as for health reform. For instance, copying a reform implemented in one country may not work in another country whether systemic differences exist between the two countries and may only become effective when combined, in a certain way, with other (structural) reforms of the system.
The structural features of health care system

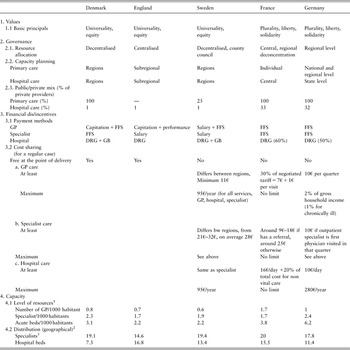
For each of the health system features, we provide below a brief review of the situation in each country in our study. Table 1 provides a summary of country-specific parameters.
Comparison of major structural parameters of health care system in five countries

GP = general practitioner; FFS = fee-for-service; DRG = activity-based payment; GB = global budget.
1Source: OECD Health data 2008.
2Coefficient of variation across regions/counties within each country. The smaller the coefficient, the more equal is the distribution of specialists and beds.
3Refers to total number of doctors for Denmark and England.
3.1 Values
The fundamental principles of Bismarck-type health systems can be summarised as plurality, solidarity and freedom (for patients to choose providers and for providers to practice where/as they want). Both in France and Germany the contributions are mainly based on the ability to pay.Footnote 4 France achieved universal coverage in 2000 with the introduction of free insurance (CMU, Couverture Maladie Universelle) for the poorest part of the population. Germany introduced mandatory health insurance in 2009; a very small fraction of the population (< 0.2%) is uninsured today.
In both countries ambulatory care delivery is based on historical principles of private practice: patients are free to choose their physicians and, in contrast to Beveridge-type systems, GPs do not have a formal gatekeeping role. In France, the only regulatory mechanism for controlling supply is the yearly quotas for limiting the number of medical students. Generalists and specialists are free to choose where they work and what they prescribe. This explains the very unequal distribution of doctors across regions, which has become a serious issue. In Germany, however, the location of physicians’ is regulated by the regional physician associations jointly with the regional sickness funds. In order to ensure equal distribution of physicians across regions, the Federal Joint Committee (GBA, Gemeinsamer Bundesausschuss, which consists of representatives of the sickness funds, physicians, hospitals and patients) determines physician/inhabitant ratios that are mandatory at the regional level.
The fundamental principle in Beveridge-type healthcare systems, on the other hand, is its universal affordable coverage; all citizens have a fundamental right to health care irrespectively of their financial contribution to the system. In all three countries healthcare systems are based upon underlying values such as equity and solidarity. In Denmark and England, health care is free for all residents with a few out-of-pocket payments exceptions, which in Denmark are almost three times higher than in England. Although patients in Sweden pay a small patient fee per visit, these payments are well regulated to control out-of-pocket expenditures (see Table 1). In Denmark the increase of private supplementary health insurance, driven by tax exemptions and waiting times, with a spread of private hospitals and clinics in the past decade might lead to greater emphasis on values such as patient choice and access (although waiting time guarantees have gradually reduced this problem). In Sweden, the supplementary private insurance has only a marginal place. In England traditionally, private insurance for elective hospital care is also a perk of executive remuneration and had the benefit of enabling those who were insured to have operations much more quickly than through the National Health Service (NHS). However, dramatic reductions in waiting times for elective care in the NHS, between 2001 and 2008, are seen as one explanation for the fall in private spending on elective surgery such as for knee and hips by about 10% between 2007 and 2008 (Trigg, Reference Trigg2008).
3.2 Governance
In broad terms governance of systems of healthcare concerns all the actions and means (policies, customs, laws and institutions), which affect the way health care is provided. Governance thus can be situated at different levels (corporate, financial and clinical). Providing a complete analysis of the governance structures and various initiatives for improving clinical governance is beyond the scope of this paper. Here we just aim to point out some major country differences in corporate governance structures.
Gatekeeping, for example, is one basic parameter, which differs across the systems studied here and affects significantly the way health care is provided. In Denmark, England and Sweden, health care has been organised around GPs as gatekeepers for the system. Gatekeeping is considered to be a mechanism of cost containment, in part because patients are not always good judges of whether they need specialist care; the evidence that specialists induce demand for costly and sometimes unnecessary procedures, and also because of an emphasis on an established primary care system to provide prevention and treatment. In contrast, in France and Germany, GPs work as ‘independent providers’ with no particular responsibility for assuring adequate use of specialist care and for assuring co-ordination of care by different providers.
Another distinguishing feature of Beveridge-type systems, in terms of governance, is that they are integrated. That means that both the provision and the financing of healthcare services are handled within one organisational system. Before 1991, the English NHS had a hierarchical integrated model. This meant that the same organisations (defined geographically) had the responsibility for meeting the needs of their populations and for running providers. Such organisations can either be funded equitably for their populations or for the performance of providers, but not both. Hence, the attraction of the model of an internal market with a purchaser–provider split in which purchasers are funded for their populations and contract with independent providers. England has tried four variations of this model in its efforts to improve provider performance: competition in the first internal market from 1991 to 1997; partnership in a ‘third way’ between 1997 and 2000; publishing performance in ‘star ratings’ between 2001 and 2005; and again an internal market from 2006 (Bevan and Robinson, Reference Bevan and Robinson2005). In contrast, the governments in Scotland, in 2003, and Wales, in 2008, have decided to abandon the purchaser–provider split and revert to integrated hierarchical organisations (NHS Scotland, 2003; Welsh Assembly Government, 2008).
A further issue is the presence or absence of central government in decisions of total funding of health care. Cost control might be easier when exercised by a central government (Tuohy, Reference Tuohy2008). In the Beveridge countries discussed here, England has a model where the decision on total NHS spending is the prerogative of national government. The UK government essentially determines spending on the NHS, but following devolution in 1998, each country (England, Northern Ireland, Wales and Scotland) has considerable latitude in determining spending on the NHS and setting priorities and styles of governance.
Denmark has recently centralised decision making regarding taxation. The expenditure level is still subject to negotiations between the national government and the regional authorities but the national government obviously has gained more direct control. In Sweden decisions on spending are ultimately made by regional authorities, but as in Denmark are subject to agreements and monitoring by the national government, which may withhold block grants. The Swedish county councils also hold a strong position by their right to levy proportional income taxes from their population.
In France and Germany financial stewardship of the system is shared between the government and the health insurance funds. In Germany, national government has limited say in decisions on expenditure by different insurers. In France, the government sets annual financial targets to limit the expenditure of health insurance funds, but these targets are never respected. The split between the supervision of healthcare expenditure and the management of healthcare provision has been highlighted as one major problem.
3.3 Public/private mix
Despite being both social insurance-based, the role and functioning of insurance funds differ significantly between France and Germany. In Germany there are two parallel insurance systems: social health insurance (SHI), covering about 88% of the total population,Footnote 4 and private health insurance covering about 10% of the population (see Flood, this issue). There are about 210 private, non-profit SHI and 52 private for-profit health insurers in Germany; although in France three public insurance schemes cover 95% of the population (and one covers 85%).
Both in France and in Germany healthcare provision rely heavily on private providers. In the ambulatory sector, physicians work in private, and in general as solo practice. Inpatient care is delivered both by public and private non-profit and for-profit hospitals. Patients choose their hospital freely between public and private providers. Private for-profit hospitals represent about one-third of all beds in both countries. In Germany, the majority of private for-profit hospitals are part of the state hospital plans and therefore adopt the same regulations as the public hospitals concerning access and payment. In France, the private providers are allowed to charge extra fees to patients but the reimbursement from public insurances is based on fixed tariffs. Private supplementary insurance policies may cover some of these fees.
Beveridge-type systems have traditionally been run by the public with few private providers (less than 1% of all beds in Denmark, England and Sweden, despite an increasing trend). GPs are salaried in Sweden, but not in Denmark. In England, the majority of GPs (approximately 85%) work as independent contractors; the rest work as salaried employees of a contractor (National Audit Office, 2008). In Denmark hospital care is mostly delivered by public hospitals owned and operated by the regions. In Sweden, in the whole healthcare sector, only about 15% of doctors and 10% of nurses work privately, but there are vast local variations in this respect. In the Stockholm region almost one-third of doctors work privately in comparison with the Northern region where the figure is only 6%. In England, there has been a recent emphasis on plurality of provision for publicly financed care with the creation of NHS foundation trusts, which enjoy greater independence from national government, and of private independent sector treatment centres to provide diagnostic and elective services, intended to create an independent sector market.
3.4 Capacity
Traditionally, there is wide choice of healthcare providers in France and Germany, and the density of physicians and hospitals per capita remains comparatively high (see Table 1). Large variations are found across countries for ratios of acute hospital beds and generalists per 1000. Germany has by far the highest ratio of acute hospital beds per 1000 (6.2): this is twice that of Denmark, almost twice that of France and almost three times that of Sweden and England. France has by far the highest ratio number of generalists per 1000 (1.7): almost twice that of Germany and almost three times that of Denmark, Sweden and England. There is less variation in the ratios of specialists per 1000: Denmark and Germany have the highest (2.4), France and England the lowest (1.7), with Sweden in the middle (1.9).
In Sweden, even if the national government has emphasised the importance of primary health care since the 1960s, the county councils have chosen to focus more heavily on hospital care. Today, the number of generalists per capita is one-third of that in France and less than 20% in Denmark. The ratio of hospital doctors to GPs in Sweden is approximately 3 : 1 today leading to an overrepresentation of specialised hospital care. Despite that the number hospital beds per capita is two-thirds of that in Denmark (e.g. 2.2 vs 3.1 per 1000 habitants).
In England, between 1997 and 2007, there were dramatic increases in staff working in the NHS: the numbers (full time equivalents) of GPs increased by 17%, and medical and dental staff in hospital and community health services rose by 53% (The Information Centre, 2008a, 2008b). Even after these dramatic increases, the ratios of specialists and GPs per capita are the lowest and second lowest of the five countries.
3.5 Financial incentives/disincentives
In France, almost all the physicians in ambulatory care, as those working in for-profit hospitals, contract with health insurance and they are paid according to a negotiated fee-for-service schedule (sector 1). Some of the physicians are authorised by the health insurance funds to charge higher fees (called sector 2), but the reimbursement to patients by public health insurance is made on the basis of the negotiated fee for sector 1. There is no official limit on these fees charged by doctors in sector 2, and the generosity of the supplementary insurance contracts for covering these extra fees varies widely. At present, 35% of specialists and 15% of generalists work in sector 2, but their distribution is very uneven. In some areas access to specialists, who do not charge extra fees (sector 1) is quite limited; this might explain why one over two people thinks that specialist care is not affordable in France (Figure 5). In France health insurance is organised according to the cost-reimbursement principle (i.e. patients pay first and get reimbursed by their insurer), whereas this is usually only the case for privately insured in Germany. The co-payment rate varies for different types of health care: from about 20% for inpatient care to between 35% and 65% for pharmaceuticals. About 85% of the population purchase supplementary insurance, which can cover these co-payments. The poorest, 7% of the population benefit from free complementary insurance.
In Germany, ambulatory care providers are also reimbursed according to a fee-for-service system. As they are mostly private for-profit providers, they have a legitimate interest in maximising their own profits. However, income maximisation is only possible to a certain extent because there are fixed budgets for general and specialist outpatient care. The attempt to introduce the same type of spending constraints in France was declared non-constitutional after long strikes and strong opposition by specialists (Or, Reference Or2002). In Germany, SHI is based on the benefit-in-kind principle (i.e. health care is free at the point of access for patients except for certain co-payments, see Table 1), and providers are directly reimbursed by sickness funds.
General practitioners in Denmark and England, and specialists in Denmark run privately owned clinics, but receive most of their income through public reimbursement based on general agreements on fees and working conditions between the various government bodies and the medical associations. Most generalists are paid a combination of capitation and fee-for-service payments. In Sweden, since the county councils run most of the health care, most of the physicians and other staff categories are salaried employees.
The increase in NHS funding in the UK in 2000 was followed in 2004 by new contracts for specialists and GPs. GPs can now withdraw from twenty-four-hour responsibility for patient care and received increases in pay from an explicit set of incentives designed to pay for performance in achieving targets set in a Quality and Outcomes Framework. Both contracts have been criticised as they resulted in paying much more for working fewer hours: the average increases in pay for specialists and GPs, who were partners, were 27% and 58%, and the reduction in the average hours they worked per week were one and seven hours (Comptroller and Auditor General, 2007, 2008).
There is a small amount of cost sharing in Sweden. Patients pay a fee at each visit in the form of a flat-rate payment with an annual cap of 95€ for the expenditure on all health services. The user fees differ between regions (see Table 1), but patients under 20-year old are exempted. Denmark has a surprisingly high level of out-of-pocket payments, which are concentrated on dental services (for citizens above 18 years), physiotherapy and pharmaceuticals. However, in both Denmark and England, there are no co-payments for primary medical care, hospital and community health services. Citizens may choose to pay out-of-pocket or for private insurance in order to gain quicker access to privately practicing specialists and private hospitals.
4. Policy responses: recent reform initiatives
The health system parameters identified in the previous section are changing, as reforms have been implemented to improve performance. In this section, we focus on two major recent reform initiatives, which may be seen as transforming the fundamental parameters of Bismarck and Beveridge systems: the introduction of ‘soft’ gate keeping in France and Germany, and the attempts to introduce more choice (including private providers) by extending waiting time guarantees in Denmark and in Sweden and by increasing the range of providers in England. In particular, we examine whether there has been some convergence in healthcare systems as a result of these reforms.
4.1 Bismarck towards Beveridge? Gatekeeping comes to France and Germany
As expected from the performance rankings above, for both France and Germany the most important policy issues are the high levels of total healthcare expenditures and costs together with concerns over quality. In France and Germany the absence of gatekeeping system is seen to result in inappropriate use and supply of health services (overuse of specialist and hospital services, duplication of treatment and inappropriate referrals), high costs and possibly lower quality of care. In this context, a non-mandatory (‘soft’) gatekeeping scheme has been introduced in Germany since 2000 and in France since 2005, in order to reduce total healthcare costs and improve system efficiency and care quality. In both countries participation in the gatekeeping scheme is voluntary both for patients and for providers.
In Germany, sickness funds and single providers can negotiate selective contracts with gatekeeping arrangements. All sickness funds are asked to set up gatekeeping programs in the next years. In France, the National Health Insurance Fund and the representative professional associations signed a national agreement introducing the ‘regular physician’ scheme set out in the healthcare reforms of 2004. Patients are asked to declare a ‘preferred doctor’ (which could be a specialist). If patients avoid ‘soft’ gatekeeping, they are penalised financially: the rate of reimbursement she/he is entitled to from the health insurance fund is reduced from 70–60% and GPs and specialists in sector 1 are entitled to charge a supplemental fee, up to 17.5% of the official rate. These financial penalties apply if an individual chooses not to register with a preferred doctor, visits a GP other than his/her preferred doctor (except in an emergency) or if the patient consults a specialist without a referral. The reimbursement schemes are so complex that health professionals and patients find it difficult to understand how the schemes work. This partly explains the high-participation rate in France, as compared with Germany, as in France, most believe that they would not be reimbursed at all if they were not to be referred by a GP. One reason for low enrollment of patients in gatekeeping programs in Germany is that this exempts them only from a low-ambulatory practice fee (10€ per calendar quarter).
In Germany, GPs receive a flat-rate premium for every patient that enrolls on their list. The amount of this payment differs between sickness funds. In France, however, there is no specific payment for ‘preferred doctors’; hence no contract is made with the doctors who are now supposed to act as gatekeepers. In Germany, gatekeeping contracts between sickness funds and GPs can include such requirements as GPs participating in training courses (e.g. on patient-oriented communication), or the use of evidence-based treatment guidelines. These contractual requirements vary between sickness funds. In France, generalists are now expected to help their patients with the coordination of treatment but they have no formal requirement to do this. However, they receive an extra payment (40€/year) for patients suffering from a list of ‘long and costly diseases’ such as cancer, diabetes, severe high-blood pressure, long-term psychiatric disease, etc. Otherwise, the payment mechanism (fee-for-service) remains the same.
Moreover, in order for GPs to be able to take on their role as gatekeepers, training and education need to be adapted to their new role. Currently, ambulatory GPs are in a rather weak position compared to specialists in both countries, despite some recent initiatives to promote general practice in medical schools. This is due to the fact that specialists have a dominant position in the majority of regional/national physician associations and have more influence in decision-making. New models of care that are promoted by the national government with the aim to strengthen general practice are thus not very popular. At the same time, at least in Germany, surveys show that patients and providers put a high value on free choice of doctors (Wasem, Reference Wasem1999).
Therefore both in France and in Germany there has been little impact from these gatekeeping schemes to date. Participation rates remain low in Germany: out of 31 million individuals who have the option to do so only 5.9 million actually enrolled with a GP (Redaktionsbüro Gesundheit, 2007). In France the majority of the population declared a ‘preferred doctor’, but there is a little visible change in consumption patterns.
4.2 Beveridge towards Bismarck? Improving choice in Denmark, Sweden and England
The main problem in English, Swedish and Danish health care has been long waiting times for access to health care and this issue has dominated the health debate since the end of the 1980s. Since the early 1990s, several attempts have been made to deal with this problem, with mixed success. Patient choice was a major parameter of these reforms.
In Denmark, in 1993, free choice of hospital for patients was introduced so that, once referred by a GP, patients could choose among all public hospitals in Denmark, and some private non-profit hospitals with the same level of specialisation (Strandberg-Larsen et al., Reference Strandberg-Larsen, Nielsen, Vallgårda, Krasnik, Vrangbæk and Mossialos2007). However, patients’ choice was limited to the hospitals that had an agreement with the region. In 2002, Denmark introduced a waiting time guarantee, called ‘extended free choice’, that extended choice to a number of private facilities and facilities abroad for patients with expected waiting times of more than two months. This appears to have had a positive impact as the average time for most waits for elective surgery has been declining since 2002: halving the time waited for cataract and orthopaedic surgery between 2000 and 2006 (from about 30–15 weeks). The extended choice scheme is mostly used for eye surgery, orthopaedic surgery, ear, nose and throat treatment and plastic surgery.
There has been limited use of both ‘free choice’ and ‘extended free choice’, perhaps because of travel costs, limited information on quality matters, traditions and patient preferences for treatment close to home (Vrangbæk et al., Reference Vrangbæk, Østergren, Okkels and Winblad2007). It does, however, seem to have improved the productivity of local providers. In Denmark, in October 2007, the waiting time guarantee was further reduced to one month. It seems that the improvement made in managing waiting times in Denmark was achieved through a combination of productivity gains and increased funding of health care.
In Sweden, the first waiting time guarantee was introduced in 1991, to assure medical care within three months for 12 procedures for which there were problems of long waits. The agreement guaranteed that patients who could not get these services in their own hospital within three months would be offered the same care at another public or private hospital with the costs to be paid by the home hospital. Around 500 million Swedish Crowns (about US $70 million) were allocated to the county councils for this guarantee, which remained in force until end of 1996 by yearly agreements, but no additional funding was provided (Hanning and Lundström, Reference Hanning and Lundström1998). This focused intervention to reduce waiting times has been effective in the short term; it helped to reduce backlogs and to improve the management of waiting lists. Nevertheless, waiting times started to go up again after 1994. Moreover, giving priorities to just 12 health conditions raised questions on the fairness and suitability of these areas as priority in the long term and the policy was abandoned in 1997 (Hanning and Winblad Spångberg, Reference Hanning and Winblad Spångberg2000).
In 2005, a new ‘national waiting time guarantee’ was agreed between the Federation of County Councils and the Swedish government to guarantee the patient a contact with a health care centre within a day, an appointment with a GP within a week, an appointment with a hospital specialist within 90 days, and a maximum waiting time of 90 days between diagnosis and treatment. However, there are no formal sanctions for providers that fail to achieve them. The only negative incentive is that a patient’s home-county has the responsibility to pay for the costs of treatment outside the county if they cannot fulfil the time limits set (Socialstyrelsen, 2010). In order to increase the effects of the waiting time guarantee, the national government recently introduced a reimbursement for clinics that are able to keep the specific time limits.
In addition to the waiting-time guarantee, several political initiatives have been taken to increase patient choice in Sweden. For instance, a national policy was introduced in 1989 and updated in 2000, which gives patients the right to choose their care-provider for primary care as well as specialist care in the whole country. In contrast to Denmark, the patients’ right to choose is not legislated. Instead the Federation of County Councils and all counties made a voluntarily agreement to introduce the patient choice policy (Fredriksson and Winblad, Reference Fredriksson and Winblad2008). However, it appears that in practice, ‘patient choice’ has not been much used by the patients, and waiting times remain a major problem in Sweden.
In the UK NHS, long waiting times have been an increasingly serious problem since it began in 1948. Indeed, some fifty years later, tackling that problem was the central manifesto commitment of the (new) Labour Government elected in 1997 (The Labour Party, 1997). The government’s initial responses, however, were not to tackle this by patient choice. Indeed, initially the government hoped that abolishing the emphasis on provider competition would lead to savings in transaction costs and hence enable the NHS to use the released resources to reduce waiting times. The government’s limited progress in tackling that problem was one of the factors contributing to the perceived crisis of the NHS in 2000 that was followed by unprecedented increases in NHS funding. From 2001–2005, the government in England introduced an analogous policy to waiting time guarantees, with targets for waiting times in a regime of ‘naming and shaming’ by ‘star ratings’, which was highly successful: in 2001, target was for patients to wait for two years from being referred by a GP to being admitted to hospital for an elective operation; in 2008, the waiting time-target for the whole pathway is only 18 weeks (Secretary of State for Health, 2000; Bevan and Hood, Reference Bevan and Hood2006; Propper et al., Reference Propper, Sutton, Whitnall and Windmeijer2008; Bevan, Reference Bevan2009). From 2002, the government re-introduced a quasi-market with a new emphasis on greater choice of specialists and hospitals based on policies in Denmark and Sweden (Secretary of State for Health, 2002). Compared to most other European countries, British people were among the most dissatisfied with their opportunities for choosing: only 30% said that these were ‘good’ or ‘very good’, compared to 73% in Spain and 70% in Switzerland (Coulter and Magee, Reference Coulter and Magee2003). Hospital market reforms have been phased into the NHS from 2002–2006 under the flag of ‘patient choice’. The cornerstone of the reform is that all patients referred for specialist care are able to use a national electronic booking system that offers patients a choice of providers for first outpatient appointment for elective care. Recent evaluation of these policies found problems in implementation (Dixon et al., Reference Dixon, Robertson and Bal2010) and no hard evidence of them yet having had a beneficial impact (Audit Commission and Healthcare Commission, 2008). Difficulties have been identified with the impact of patient choice on quality (Robertson and Torlby, Reference Robertson and Torlby2007; Bevan, Reference Bevan2008), social and geographical equity in access (Appleby et al., Reference Appleby, Harrison and Devlin2003), and the cash-limited budgets of local insurers (Bevan and Robinson, Reference Bevan and Robinson2005). In addition, using the private sector for improving choice appears to have come at a cost. To encourage entry to the hospital market, the government offered quite generous contracts to private investors including revenue guarantees for five years, irrespective of activity volume, and payments above the national tariff (Audit Commission and Healthcare Commission, 2008: p. 51).
5. Conclusions
A number of conclusions can be drawn from this comparison of the Beveridge and Bismarck systems based on the experiences of five countries.
First, on the basis of a range of comparable data, we find that there are some systematic differences in outcomes between Bismarck and Beveridge systems. In terms of cost containment and affordability, Bismarck-type systems appear to be less successful than the Beveridge type. In contrast, Beveridge-type systems appear to be less successful in terms of access, defined as availability of services when required. Yet, it should be noted that this is based on surveys of patients’ own assessments. It has not been possible to find comparable measurements of waiting times. In other performance dimensions such as health outcomes achieved and responsiveness we do not see any systematic distinction between these systems.
Second, our analysis shows that a range of structural features of health systems needs to be taken into consideration when addressing performance deficiencies. Despite their common funding principles, organisational design and governance context can differ substantially within and across Beveridge and Bismarck-type systems. In particular, we compared four broad parameters: governance; each system’s underlying values; financial incentives for providers and consumers; and system capacity. Careful consideration of these in the implementation phase may help to improve the success of any reform attempt. For example, despite both being insurance based, the structure and functioning of insurance funds differ significantly between France and Germany. The large number of sickness funds in Germany might partly explain low participation in its gatekeeping programme compared with France where three public insurance schemes cover almost all of the population.
There are also significant differences between the tax-based systems of Denmark, England and Sweden. For example, in Denmark the majority of physicians are paid a combination of per capita and fee for service while in Sweden they are mostly salaried. In England, GPs can work for a salary but about 85% are independent contractors (paid by capitation and by performance following the 2004 GP contract). These differences in parameters across countries are closely linked to the way health care is supplied and consumed and hence have a direct impact on the success of reforms introduced.
Third, within the three Beveridge countries there has been a common objective of reducing waiting times but the success varied. Denmark and Sweden both introduced, about the same time, choice of providers and waiting time guarantees. Waiting times remain a major problem in Sweden, whereas in Denmark this now seems to be less of an issue, which we suggested (in Section 3) is likely to be due to differences in terms of healthcare capacity and payment methods for doctors. In particular, the experience of Sweden suggests that choice may have a limited impact on the productivity of healthcare providers when they are paid on a salaried basis. Moreover, ‘choice’ might become a chimera when there is no real effective choice because of constraints on supply. There were dramatic reductions in long waiting times in England though demanding targets and ‘naming and shaming’ but the policy of patient choice with pluralism and expansion in supply have, so far, proved to be disappointing.
In the case of France and Germany, both countries introduced a gatekeeping scheme, ostensibly to improve quality but also to constrain demand and healthcare spending. In both countries the measure has mainly consisted of directing patients (through financial incentives) to see a generalist first. However, this was not accompanied by any serious attempt to change working practices and the underlying values of a private medical practice working on a fee-for-service basis. For example, in France, there has been no significant change in contractual arrangements with GPs to work as gatekeepers. Also, in order for GPs to act effectively as gatekeepers, specific training and education measures are required but have not been introduced.
Finally, the experience of the five countries reviewed in this paper suggests that taking a piecemeal approach to health reform is likely to be sub-optimal. Moreover, although countries of the same type may share some common problems in terms of improving healthcare performance adopting a ‘copy-and-paste’ approach to healthcare reforms without taking into account the specific structural features of each country is likely to be ineffective.
Acknowledgements
The authors thank to the members of the European Health Policy Group for their helpful comments and, in particular, Carolyn Tuohy and Claus Wendt for their valuable input. We are also grateful for comments from an anonymous referee.