Healthcare workers (HCWs) serve as a vector for methicillin-resistant Staphylococcus aureus (MRSA) transmission in institutional settings. In acute care hospitals, contact precautions (eg, single room, gown and gloves for all patient–HCW contact, patient room restriction) are used for patients colonized with MRSA to prevent transmission to other patients.Reference Siegel, Rhinehart, Jackson and Chiarello 1 The usefulness of contact precautions for MRSA-colonized residents in nursing homes has not been evaluated.Reference Trick, Weinstein and DeMarais 2 – Reference Johannessen 4 In nursing homes, infection prevention is focused on the use of standard precautions (ie, gowns and gloves for contact with blood, body fluids, skin breakdown, or mucous membranes) with all residents.Reference Johannessen 4 Unlike patients in acute care hospitals, residents are encouraged to interact with one another, eat in common areas, and share other activities. Current Centers for Disease Control and Prevention (CDC) Isolation Guidelines are vague and suggest deciding whether to implement contact precautions or to modify contact precautions for MRSA-colonized residents based on local case mix,Reference Siegel, Rhinehart, Jackson and Chiarello 1 largely due to lack of evidence.Reference Hughes, Tunney and Bradley 3
The use of standard precautions is limited by the lack of concrete guidelines regarding when to wear gowns and gloves. Detection of MRSA on HCW gowns and gloves during HCW–patient interactions facilitates the study of the risk of transmission due to different types of care.Reference Morgan, Rogawski and Thom 5 – Reference Snyder, Thom and Furuno 7 The overall goal of our research is to determine the optimal use of gowns and gloves in community-based nursing homes. Our primary objective in this study was to estimate the risk of MRSA transmission to gowns and gloves by type of care provided during HCW–resident interactions. We hypothesized that some activities, such as those involving contact with secretions (eg, draining wounds, ostomy care), pose a higher risk than others (eg, vital signs, medications). We were also interested in specific resident characteristics, such as presence of skin breakdown or stool incontinence, and their role in MRSA transmission.
METHODS
Study Design
We conducted a multicenter, prospective, observational study to estimate the frequency of and risk factors for MRSA transmission to gowns and gloves worn by HCWs when providing care to nursing home residents. During the study, HCWs wore gowns and gloves when interacting with enrolled residents. The protocol was approved by the Institutional Review Boards of the University of Maryland Baltimore and University of Michigan.
Participants
Residents from 13 non–Veterans Affairs (VA), community-based nursing homes in Maryland and Michigan were enrolled. The nursing homes ranged in size from 62 to 209 beds; 4 were not-for-profit. Eligible residents (1) had an expected length of stay of at least 1 week, (2) spoke English, and (3) consented, assented, or lacked dissent to study procedures. Eligible residents were enrolled with written informed consent from them (84%) or from their legally authorized representative (16%). HCWs were enrolled with verbal consent.
In our primary analysis, we assessed the risk of MRSA transmission when HCWs interacted with MRSA-colonized residents based on cultures on enrollment. A resident was defined as MRSA colonized if the anterior nares or perianal skin swabs grew MRSA.
We also assessed MRSA transmission rates when care was provided to residents who were not colonized with MRSA on enrollment by selecting a random sample of residents without MRSA colonization, and we cultured the gown and gloves from care interactions with these residents.
Data Collection
Using minimum data set guidelines, 8 medical records, and nursing home staff, we recorded demographic characteristics, type of long-term care (ie, rehabilitation vs residential care), recent hospitalizations, activities of daily living, case-mix index including resource utilization groups (RUG scores), current antibiotic use, skin breakdown, medical devices, and uncontrolled secretions. A resident was defined as receiving rehabilitative care or residential care based on their resource utilization group.
Cultures were obtained from the residents’ anterior nares and perianal skin using a nylon-flocked swab (Copan ESwabs; Copan Diagnostics, Inc., Murrieta, CA). HCWs were asked to wear gowns and gloves during usual care activities (eg, wound dressing) up to 28 days after resident enrollment. A research coordinator observed and recorded the type and duration of care delivered with each activity. After the activity, the coordinator swabbed the HCW’s gown and gloves as described previously.Reference Morgan, Rogawski and Thom 5 – Reference Snyder, Thom and Furuno 7 HCWs followed standard infection control practices for gown and glove use during the study. If they needed to change gowns or gloves between care activities, cultures were performed and a new observation began.
Laboratory Procedures
Specimens from residents, gowns, and gloves were cultured for MRSA at a central laboratory. Swabs from residents were vortexed, and 50 µL of Aimes media was placed on a CHROMagar Staph aureus (BD, Sparks, Maryland) and streaked to isolation. In addition, 50 µL of Amies media was placed in tryptic soy broth (TSB) with 6.5% NaCl and incubated at 37°C for 24 hours. After overnight incubation 50 µL of broth was plated on a CHROMagar Staph aureus. One swab from the double-headed swabs used for the gowns and gloves was placed into TSB with 5% NaCl, and the other was placed in brain heart infusion broth and incubated at 37°C for 24 hours. A 50-µL volume of each broth was plated separately on a CHROMagar Staph aureus. The plates were incubated at 37°C for 24 hours. Mauve-colored colonies on CHROMagar Staph aureus suspicious for S. aureus were confirmed by the detection of coagulase (Staphaurex; Remel, Lenexa, KS). Methicillin resistance was determined by oxacillin screening following Clinical and Laboratory Standards Institute (CLSI) guidelines. 9
A convenience sample of 15 MRSA isolates from residents and the 39 corresponding MRSA isolates from gown and glove contamination underwent molecular typing to assess concordance and to demonstrate that gown and glove contamination was due to transmission from the resident. Each MRSA isolate was typed by DNA sequencing analysis of a single locus, the protein A (spa) gene hypervariable region, as previously described.Reference Harmsen, Claus, Witte, Rothganger, Turnwald and Vogel 10 Spa typing was used due to its concordance with PFGE, its ease of use, reproducibility, and the advantages of unambiguous sequence analysis.Reference Strommenger, Kettlitz, Weniger, Harmsen, Friedrich and Witte 11
Data Management and Statistical Analysis
All study data were entered into a centralized relational database. Quality control was performed every 4 months via logic checks on the entirety of the database and comparison of source documentation to the database values for 10% of the participants. The association between MRSA colonization and resident characteristics was measured using the χ2 test or Fisher’s exact test for categorical variables, and the Student’s t test or the Wilcoxon rank-sum test was used for continuous variables. All statistical tests were 2-tailed, and P values <.05 were considered statistically significant. All statistical analyses were conducted using Stata 12 software (Stata Corp., College Station, TX) and SAS 9.3 (SAS Institute, Cary NC).
The risk of MRSA transmission for a particular type of care was estimated using a proportion (eg, number of glove specimens collected during a specific type of care that grew MRSA per the number of glove specimens collected during a specific type of care). Because resident–HCW interactions could include >1 type of care, we compared the risk of MRSA transmission for each type of care when it was given with another type of care to the risk when the type of care was given alone. When the risk of transmission was meaningfully different (the risk went from high to low), we separated the type of care into (1) care given with other types of care and (2) care given alone (ie, without other types of care).
Odds ratios (the odds of MRSA transmission given receiving a particular type of care divided by the odds of MRSA transmission given not receiving that care) were estimated using generalized estimating equations (GEE) with an exchangeable covariance structure. GEE adjusted for >1 observation of a type of care for a resident. Odds ratios significantly greater than 1 were considered high risk types of care and those significantly less than 1 were considered low-risk types of care. To determine whether certain resident characteristics increased the risk of transmission for a particular type of care, that variable was included in the model as a potential effect modifier.
RESULTS
Resident Characteristics
Over 25 months, 1,838 residents were screened for enrollment; 1,143 were eligible and 403 (35% of eligible) were enrolled. Of the 740 residents that were eligible but not enrolled, 564 did not consent, and for 176 the legally authorized representative (LAR) did not give consent for study participation. Two residents withdrew from the study prior to obtaining cultures, yielding a final study population of 401 residents. Of these 401 residents, 113 (28%) were colonized with MRSA. Of the MRSA-colonized residents, 62% percent were colonized only in the anterior nares, 9% were colonized only at the perianal skin, and 28% were colonized at both the anterior nares and the perianal skin.
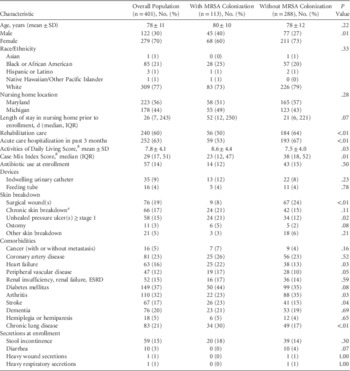
Compared with non–MRSA-colonized residents, MRSA-colonized residents were more likely to be in residential care and were more likely to have or have had a pressure ulcer, heart failure, chronic lung disease, or stroke (Table 1).
Description of Residents with Cultures (n=401) Stratified by Methicillin-Resistant Staphylococcus aureus (MRSA) Colonization Status

NOTE. ESRD, end-stage renal disease; SD, standard deviation; IQR, interquartile range.
a Chronic skin breakdown is defined as the absence of surgical wound(s) and the presence of at least one of the following: unhealed pressure ulcer (s) ≥stage 1, ostomy or other skin breakdown.
Gown and Gloves Contamination with MRSA by Type of Care
We observed a median of 7 interactions per MRSA-colonized resident (IQR, 6–11 interactions), with each interaction lasting a median of 6 minutes (IQR, 5–11 minutes). Of the interactions observed, 73% involved 1 type of care during the interaction, 13% involved 2 types of care, 7% involved 3 types of care, and 7% involved ≥4 types of care. Two types of care activities were stratified into 2 types: (1) care that occurred with other care activities and (2) care that occurred without other care activities because of substantial differences in the risk of transmission. The risk of MRSA transmission to gowns with giving medications was 18% with other care and 8% when giving medications was the only care. The risk of MRSA transmission to gowns when monitoring blood glucose was 30% with other care and 0% when it was the only care being provided.
Overall, gowns were contaminated with MRSA during 14% of 954 interactions with MRSA-colonized residents. Gloves were contaminated during 24% of 954 interactions (P<.01). Spa typing of MRSA isolates from 15 MRSA-colonized residents and 39 MRSA isolates from gowns or gloves showed that 89% were identical with the resident isolate; 8% were closely related, and the remaining 3% were discordant.
We selected a random sample of 23 residents without MRSA colonization at enrollment and cultured gowns and gloves from HCW care interactions with these residents. Of the 150 gown swabs tested from these MRSA negative residents, 8 were MRSA positive (5%). Of the 150 glove swabs tested, 8 were MRSA positive (5%). Of the random sample of residents without MRSA colonization at enrollment, 2 residents were linked to 3 positive HCW gown or glove cultures, and 10 residents were linked to a single positive gown or glove culture.
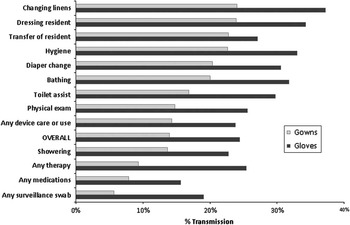
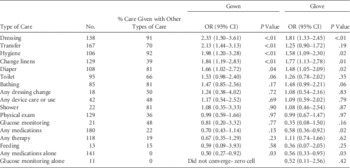
Transmission varied by type of care activity from 0% to 24% for gowns and 8% to 37% for gloves (Figure 1) demonstrating high- and low-risk activities. We identified dressing the resident, transferring the resident, providing hygiene (brushing teeth, combing hair), changing linens, and changing diapers as high-risk activities (OR>1.0, P<.05, Table 2). Giving medications and performing glucose monitoring were low-risk activities (OR<1.0, P<.05, Table 2) when they were the only type of care during the interaction. Multiple interactions with at least 1 high-risk activity were more common compared with low-risk care activities, which tended to occur as single activities (42% of interactions with at least 1 high-risk activity are bundled compared with 4% of interactions with all low-risk activities, P<.01).
MRSA transmission to gowns and gloves of healthcare workers during care of MRSA-colonized residents (n=113) by type of care provided during 954 interactions.

Odds Ratio, Odds of Gown or Glove Contamination Given Type of Care over Odds of Gown or Glove Contamination if that Type of Care Was Not GivenFootnote a

a Analysis was adjusted for clustering within individual methicillin-resistant Staphylococcus aureus (MRSA)-colonized residents.
Resident Characteristics that Increased Gown and Glove Contamination with MRSA
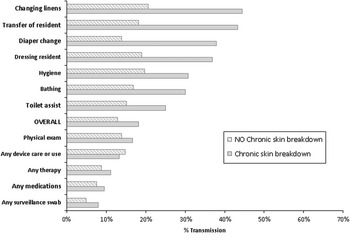
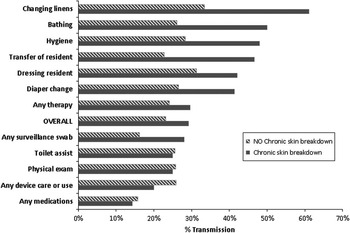
We also assessed whether resident characteristics increased the risk of transmission. We hypothesized that the presence of body secretions would increase gown and glove contamination. Diarrhea, heavy wound secretions, and heavy respiratory secretion were rare in the study population (Table 1). Thus, we assessed stool incontinence (18%) and chronic skin breakdown (21%). In residents with stool incontinence, HCW gown or glove contamination did not increase (data not shown). In residents with chronic skin breakdown, higher rates of gown and glove contamination occurred during high-risk activities. The rates of gown and glove contamination were statistically significantly different between residents with chronic skin breakdown and residents without chronic skin breakdown for transferring (P=.02), changing diapers (P = .02) and dressing (P =.05) (Figures 2 and 3).
MRSA transmission to gowns of healthcare workers during care of MRSA-colonized residents (n=113) by type of care provided and presence of chronic skin breakdown (eg, pressure ulcers) during 952 interactions.

MRSA transmission to gloves of healthcare workers during care of MRSA-colonized residents (n=113) by type of care provided and presence of chronic skin breakdown (eg, pressure ulcer) during 950 interactions.

DISCUSSION
MRSA transmission to gowns and gloves was common; 14% of gowns and 24% of gloves were contaminated with MRSA after HCW–resident interactions. Resident were confirmed as the source of MRSA by spa typing. Transmission to gloves was more common than transmission to gowns. High-risk care activities often involved >1 type of care. Residents with chronic skin breakdown were more likely to transmit MRSA during high-risk activities than residents without chronic skin breakdown.
In addition, 28% of residents were colonized with MRSA in nares and/or perianal skin. This result is similar to those of other studies over the last 10 years in the United States. Mody et alReference Mody, Kauffman, Donabedian, Zervos and Bradley 12 found a prevalence of 29% in residents without medical devices from 14 nursing homes. Huang et alReference Hudson, Reynolds and Spratt 13 found a prevalence of 26% from the anterior nares in 26 nursing homes in Orange County, California. Evans et alReference Evans, Kralovic and Simbartl 14 reported a mean admission prevalence of 29% from 133 Veterans Affairs (VA) long-term care facilities. In 6 skilled nursing facilities in Wisconsin, 22% of patients were colonized with MRSA in nares, skin of the axilla and groin, or perianal skin.Reference Crnich, Duster, Hess, Zimmerman and Drinka 15
The risk of gown and glove contamination is high when providing care to MRSA-colonized residents. This finding is consistent with uniform or clothing contamination rates reported by Garpard et alReference Gaspard, Eschbach, Gunther, Gayet, Bertrand and Talon 16 in nursing home staff. Our results suggest that the determination of when to wear gowns and gloves should be made by defining care activities with a high risk for MRSA transmission. In our study, high-risk care activities were all high-contact activities of daily living and often did not involve overt contact with body fluids, skin breakdown, or mucous membranes. This finding indicates the need to modify current CDC standards of care involving the use of gowns and gloves in this setting because under standard precautions, gowns and gloves are not recommended to be worn for what we define here as high-risk care.Reference Stone 17
Surprisingly, we found that 5% of glove and gown interactions were MRSA positive during HCW interactions with residents not colonized with MRSA. Potential sources of this MRSA include residents colonized with MRSA at anatomical sites other than the anterior nares and perianal skin, the physical environment of the resident’s room (which is often shared), the nursing home environment, the study gowns and gloves, and HCWs with MRSA colonization.Reference Strausbaugh, Jacobson, Sewell, Potter and Ward 18 Our study cohort included 2 MRSA-negative residents with 3 positive gown and glove specimens, suggesting that their MRSA colonization was not detected by enrollment cultures, possibly because these patients were colonized at other anatomical sites.Reference Mody, Kauffman, Donabedian, Zervos and Bradley 12 In prior studies in which unused gloves were cultured, they were not likely to be contaminated with MRSA prior to use.Reference Rock, Harris, Reich, Johnson and Thom 19 Our finding suggests that MRSA is ubiquitous in the nursing home environment; it also provides a context for evaluating the contamination rates in MRSA-colonized residents. Rates of contamination observed with low-risk care activities (providing medications and glucose monitoring) are similar to contamination rates observed when HCWs interacted with non-colonized residents.
The study has several limitations. The contamination of gowns and gloves of HCWs is a surrogate measure of MRSA transmission. We do not know how often MRSA transmission to HCW clothing or hands results in transmission to other residents. However, hand hygiene, glove use, and gown use typically prevent MRSA transmission to another resident. Although gown and glove contamination is a surrogate measure, it is a logical first step in the chain of transmission. A cluster-randomized trial of universal use of gowns and gloves in 20 ICUs demonstrated a 40% reduction in MRSA acquisition in the intervention units.Reference Harris, Pineles and Belton 20 A recent cluster-randomized study involving high-risk nursing home residents with indwelling medical devices showed that a multimodal strategy that included preemptive use of barrier precautions reduced new MRSA acquisitions by 22%.Reference Mody, Krein and Saint 21 Furthermore, because adherence of HCWs to recommended hand hygiene procedures has been poor (overall average 40%), hand contamination could easily lead to transmission.Reference Boyce and Pittet 22 , Reference Thompson, Dwyer, Ussery, Denman, Vacek and Schwartz 23 Because HCW participation was anonymous, we could not adjust for repeated measurements from the same staff member; however, we recruited from 13 different nursing homes; therefore, it is highly likely that a variety of HCWs participated. We did adjust for multiple observations of the same type of care on the same resident using generalized estimating equations. Consent bias may also affect study outcome measures. Residents who consented to participate in the study may differ in important ways from those who did not consent; however, we engaged legally authorized representatives in the consent process to obtain a representative sample and to limit this bias.
The study also has numerous strengths. It was a multisite, prospective study involving diverse nursing homes in 2 geographically disparate sites. Data were collected in community-based nursing homes which comprise the majority (94%) of nursing homes in the United States.Reference Harrington, Carrillo, Dowdell, Tang and Blank 24
The demographics of the study population are generally representative of the US nursing home population with regard to gender and ethnicity. Nationally, females comprise 71% of nursing home residents vs 70% in our sample.Reference Jones, Dwyer, Bercovitz and Strahan 25 Likewise, our sample was 77% non-Hispanic white, and 79% of US nursing home users are non-Hispanic white.Reference Harris-Kojetin, Sengupta, Park-Lee and Valverde 26 Finally, we identified MRSA colonization using surveillance cultures at enrollment.
To our knowledge, this is the first study to study MRSA transmission by type of care activity and resident characteristics in nursing homes. Glove contamination was significantly higher than gown contamination, reinforcing the importance of hand hygiene to prevent the transmission of MRSA and other bacteria. We identified the following high-risk care activities: dressing, transferring, providing hygiene (brushing teeth, combing hair), changing linens, and changing diapers. These data provide more concrete guidance for the use of gowns during standard precautions as well as potential modifications to contact precautions for MRSA-colonized residents. Finally, we identified chronic skin breakdown as a resident characteristic that increased the risk of MRSA transmission to both gowns and gloves (perhaps because the area of skin breakdown was colonized with MRSA). The presence of chronic skin breakdown (eg, a pressure ulcer) could be used as a marker of residents at high risk for MRSA transmission (or other MDRO transmission), as suggested in a recent editorial.Reference Stone 17 These residents could be placed on a modified form of contact precautions in which gowns and gloves are worn for high-risk types of care similar to the recent cluster-randomized study that focused on residents with medical devices.Reference Mody, Krein and Saint 21
New MRSA acquisition in nursing homes is substantial.Reference Mitchell, Shaffer and Loeb 27 , Reference Fisch, Lansing and Wang 28 Our study defines care interactions that increase the risk of transmission and suggests modifications to the current indications of gown and glove use in this setting.
Acknowledgments
We thank the staff and residents of the participating nursing homes.
Financial support. This project was supported by an AHRQ award (Grant no. 1R18HS019979-01A1). Dr. Sorkin is supported by the Baltimore Veterans Affairs (VA) Medical Center Geriatrics Research, Education, and Clinical Center; National Institute on Aging (Grant no. 5 P30 AG028747), and National Institute of Diabetes and Digestive and Kidney Diseases (Grant no. 5 P30 DK072488). Dr. Mody is supported by the Ann Arbor VA Geriatrics Research, Education, and Clinical Center, National Institute on Aging (Grant nos. R01 AG032298, R01 AG41780, and 18 HS019979) and University of Michigan Claude D. Pepper Older Americans Independence Center (Grant no. P30 AG024824).
Potential conflicts of interest. All authors report no conflicts of interest relevant to this article.