Venous thrombosis is a frequent complication of paediatric cardiac surgery, reportedly occurring in 6.7–11% of patients undergoing surgery for paediatric and CHD.Reference Manlhiot, Menjak and Brandao 1 , Reference Manlhiot, Brandao and Schwartz 2 The reported incidence is variable and the true incidence is likely much higher because investigation is rarely undertaken in the absence of clinical symptoms such as extremity swelling, chylothorax, or thromboembolism. The timing and intensity of therapy for treatment of venous thrombosis following cardiac surgery remains controversial as bleeding risks are higher in the early postoperative period.Reference Ansah, Patel, Montegna, Nicholson, Ehrlich and Petit 3 The options for treatment of venous thrombosis are surgical thrombectomy, anticoagulation alone, or anticoagulation with thrombolysis. Surgical thrombectomy is often not a feasible option because of the size of vessels in infants, risk for stenosis after intervention, risk for re-thrombosis, and repeat sternotomy. Thrombolytics are a class of medications used to induce fibrinolysis by binding to fibrin within a thrombus and converting entrapped plasminogen to plasmin; recombinant tissue plasminogen activator is the medication most commonly utilised in the literature. In children with venous thromboembolism with major vessel occlusion causing critical compromise of organs or limbs, tissue plasminogen activator administration is the preferred thrombolytic therapy.Reference Monagle, Chan and Goldenberg 4
Among the major contraindications to thrombolysis is recent intracranial or intraspinal surgery, occurring within 3 months, and recent cardiac surgery is typically considered a relative contraindication by clinicians.Reference Demaerschalk, Kleindorfer and Adeoye 5 In children with CHD, venous thromboembolism after cardiac surgery can increase morbidity, preclude candidacy for future interventions, and even lead to mortality. It is unclear whether the potential benefit of clot resolution outweighs the potential risks for bleeding. A survey of practitioners involved in the care of children with venous thromboembolism requiring thrombolytic therapy revealed wide variation in treatment approaches with regard to indication, route, dose regimen, and maximum duration of therapy.Reference Yee, Chan, Williams, Goldenberg, Massicotte and Raffini 6 Further, reports on the efficacy of tissue plasminogen activator administered to patients after cardiac surgery are limited.
The purpose of this study is to describe general safety outcomes regarding tissue plasminogen activator administration for treatment of venous thrombosis that occurs in the early postoperative period after paediatric cardiac surgery, and to describe the efficacy of tissue plasminogen activator administration with respect to thrombus resolution and improvement of chylothorax. Finally, a protocol for tissue plasminogen activator treatment of venous thrombosis that occurs in children soon after cardiac surgery will be delineated.
Materials and methods
Study population
This single-centre retrospective study reviewed the medical records of all children who had undergone cardiac surgery and received tissue plasminogen activator infusions for venous thromboses from 2011 to 2016, as identified using an electronic medication administration record. The Cincinnati Children’s Hospital Medical Center Institutional Review Board approved the study. Pertinent medical information was extracted and collated from the electronic medical records. Inclusion criteria were age less than 18 years, admission to the cardiac intensive care unit after cardiac surgery, and tissue plasminogen activator administration for venous thrombosis within 3 months of surgery. Exclusion criteria were age ⩾18 years, surgical procedure other than cardiac surgery, tissue plasminogen activator administration for an indication other than venous thrombosis – such as arterial thrombus and catheter occlusion – and tissue plasminogen activator administration later than 3 months after surgery. A total of 13 eligible patients were included in the study.
Variables and definitions
Anthropometric and demographic data, cardiac diagnosis, site of venous thrombosis, details regarding tissue plasminogen activator administration and concurrent heparin administration, blood count and laboratory values of anticoagulation, blood-product administration, chest-tube output, survival, and neurological imaging studies were tabulated. Bleeding, neurological complications, and death were attributed to tissue plasminogen activator if they occurred within 72 hours of administration completion. Bleeding was determined by chest-tube output, blood-product administration, and clinical documentation. Neurological complications were defined as clinical seizure, development of a new neurological deficit, or as a new radiological finding after initiation of treatment with tissue plasminogen activator.
Application of tissue plasminogen activator
When the decision was made to administer a tissue plasminogen activator infusion, a head ultrasound scan in infants and a detailed neurological exam in older children were utilised for screening. Concurrent anticoagulation consisting of an unfractionated heparin infusion was administered before, during, and after the administration of tissue plasminogen activator with the exception of two patients who were maintained on low-molecular weight heparin, enoxaparin, at a dose of 1.5 mg/kg with a low-molecular weight heparin level of 0.5–1 units/ml. The unfractionated heparin infusion was titrated to maintain an unfractionated heparin level of 0.1–0.3 international units/ml to mitigate the risk for bleeding. After completion of tissue plasminogen activator administration, patients were continued on anticoagulation, generally with a heparin infusion at first, and were then transitioned to low-molecular weight heparin injections for a minimum of 3 months. Platelet counts, antithrombin levels, and fibrinogen levels were monitored throughout the tissue plasminogen activator treatment course and replaced as indicated.
Statistical analysis
Anthropometric and demographic data, cardiac diagnosis, as well as details surrounding tissue plasminogen activator administration, blood-product administration, chest-tube output, survival, and neurological imaging modalities or results were tabulated and reported as the median or mean and appropriate measures of dispersion as indicated.
Results
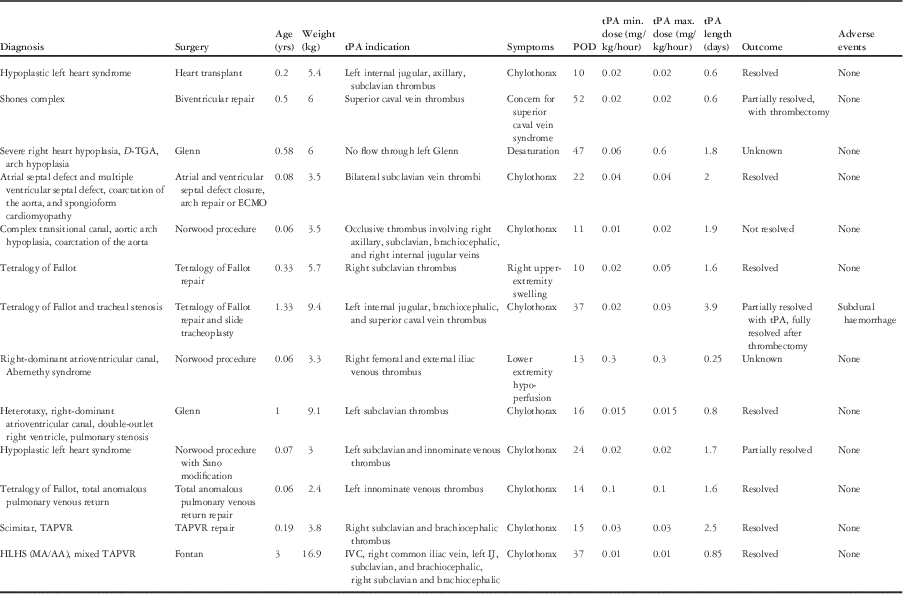
Patient characteristics are summarised in Table 1. The median age was 0.2 years with an age range of 0.057–3 years, with four patients being neonates. Consistent with their young age, the patients in this series typically weighed <5 kg. As shown in Table 2 there was diversity in congenital heart lesion and associated surgery with two patients having undergone repair of tetralogy of Fallot, two patients correction of total anomalous pulmonary venous return, one patient a Fontan procedure, two patients a cavopulmonary anastomosis, three patients a Norwood palliation, two patients complex biventricular reconstructions, and one patient having undergone a heart transplant. Of note, chylothorax was the presenting symptom of venous thrombosis in nine of 12 patients. In all, two individuals had extremity swelling, one patient had superior caval vein syndrome, and one patient had a thrombus in the cavopulmonary connection. The site of venous thrombosis varied, but it most commonly occurred in the subclavian vein. Of the 13 patients who received tissue plasminogen activator, two also underwent catheter-based mechanical thrombectomy.
Patient characteristics

IQR=interquartile range
Overview of diagnoses and tissue plasminogen activator (tPA) indication

HLHS (MA/AA)=hypoplastic left heart syndrome with mitral atresia and aortic atresia; IJ=internal jugular; IVC=inferior vena cava; POD=post-operative day; TAPVR=total anomalous pulmonary venous return; tPA=tissue plasminogen activator
Table 2 also reviews the timing, dose, and duration of tissue plasminogen activator administration in this series. Administration of tissue plasminogen activator was carried out at least 10 days postoperatively, and the treatment that occurred furthest from surgery was at 52 days post surgery. There was significant variation in dosage but, generally, tissue plasminogen activator was administered at 0.02–0.03 mg/kg/hour. A dose of 0.01 mg/kg/hour was rarely used if there was trepidation about bleeding complications for those particular patients. On the basis of previous reports stating that there is little benefit from a dose of above 0.05 mg/kg/hour, we rarely exceeded this dose. In a few cases, however, we progressed to higher doses because of lack of other feasible treatment options. The highest dose in this series was administered to the patient who had a thrombus in the cavopulmonary connection and was severely desaturated. For this patient, tissue plasminogen activator infusion was started at 0.6 mg/kg/hour and then decreased to 0.06 mg/kg/hour after 1.5 hours. The average duration of tissue plasminogen activator infusion was 37 hours, with a SD of 23.3 hours.
Efficacy
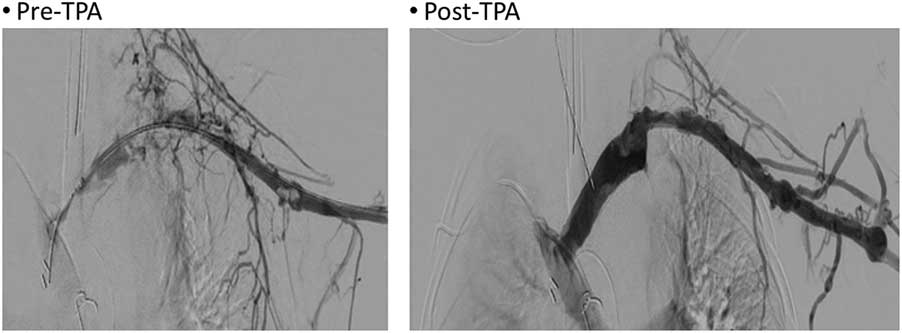
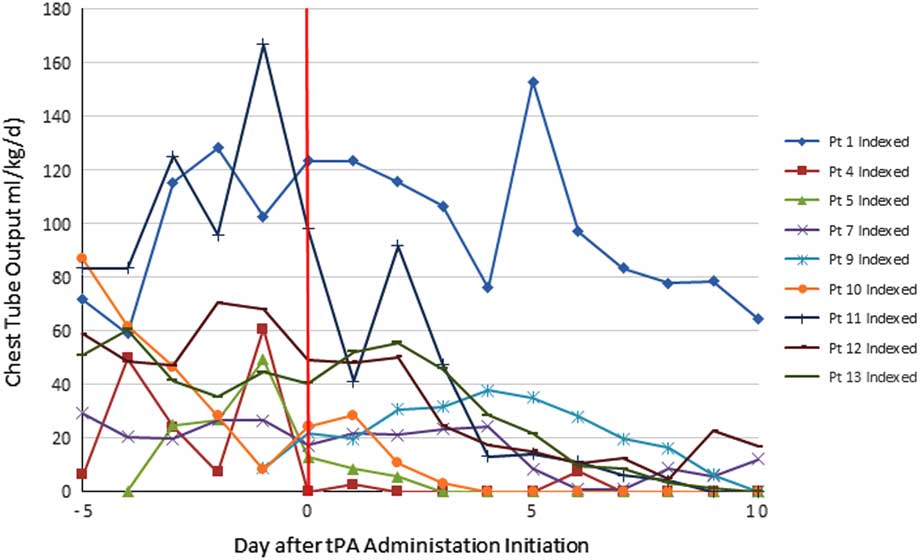
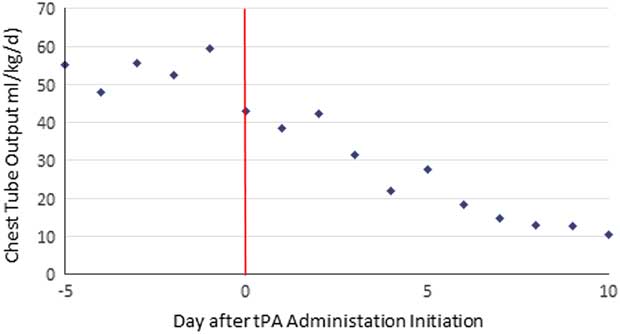
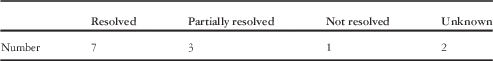
The primary modality for evaluating efficacy was ultrasound scanning. Of 13 patients, 11 underwent repeat imaging; two that did not had demonstrated significant clinical improvement. As shown in Table 3, seven patients had complete resolution of thrombus, three patients had partial resolution, and one patient had an unchanged thrombus burden. Figure 1 shows angiographic evidence of thrombus resolution in one patient. In patients with chylothorax, prompt reduction of chest-tube output occurred following thrombolysis (Figs 2 and 3). Of nine patients, seven with thrombus-associated chylothorax were able to initiate feeding and have chest tubes removed within 7 days of tissue plasminogen activator initiation. Only one of nine patients required repeated chest-tube insertion.
Angiograms demonstrating thrombus resolution for one representative patient. ( a ) Pre-tissue plasminogen activator (TPA), ( b ) post-TPA.

Scatter plot of indexed chest-tube output (ml/kg/day) from patients with chylothorax. Date of initiation of tissue plasminogen activator denoted by red line (day 0). tPA=tissue plasminogen activator.

Scatter plot of mean indexed chest-tube output (ml/kg/day) from patients with chylothorax. Date of initiation of tissue plasminogen activator denoted by red line (day 0). tPA=tissue plasminogen activator.

Impact of tissue plasminogen activator on thrombus.

Safety
No patients required surgical intervention for bleeding related to tissue plasminogen activator. Further, an increased need for transfusions was not noted, other than the need for prophylactic administration of platelets, plasma, and cryoprecipitate to maintain goals for haematological laboratory values. Of 12 patients, eight underwent follow-up head imaging. Routine head ultrasound scans were performed daily unless there was a clinical concern prompting evaluation using a CT scan. A single patient had equivocal findings on the head ultrasound scan obtained before initiation of tissue plasminogen activator; thus, a head CT scan was carried out to verify that there was no evidence of extra-axial bleeding. There was one new neurological finding within 72 hours of tissue plasminogen activator infusion, and this patient was the only one who underwent post-tissue plasminogen activator imaging by a method other than head ultrasound scanning. The patient was noted to have a subdural haematoma 1 day after tissue plasminogen activator infusion, but this was after the patient underwent cardiopulmonary resuscitation after a residual thrombus was dislodged during a mechanical thrombectomy in the interventional radiology suite. This resulted in a pulmonary embolus and subsequent aborted arrest. The same patient represented the only case of cardiac deterioration in this consecutive patient series. Given the other provoking factors, this event occurred with unknown relative contribution of tissue plasminogen activator administration.
Of 13 patients in the series, five died during hospitalisation. These mortalities occurred in high-risk, medically complex individuals: four of five with chylothorax and one with thrombosis of cavopulmonary connection. All of the deaths in this series were remote from tissue plasminogen activator administration, and none were directly attributable to or possibly related to tissue plasminogen activator infusion.
Discussion
Patients treated with tissue plasminogen activator in this case series were principally young infants who had recently undergone cardiac surgery. The majority of patients (77%) experienced a therapeutic benefit as manifested by complete or partial resolution of their venous thrombosis on ultrasound scanning. Although mortality was high in this patient group, as described, there were no deaths or haemorrhagic complications directly attributable to tissue plasminogen activator administration.Reference Manlhiot, Menjak and Brandao 1 On the basis of our experience, tissue plasminogen activator administration is both relatively safe and effective for resolution of venous thromboses in children after cardiac surgery; thus, it is reasonable to consider its use for patients with life-threatening thromboses.
Findings from this study are consistent with previous observations reported in the literature, in which tissue plasminogen activator has been used effectively for resolution of acute thrombosis with minimal bleeding when administered at low doses and for a short duration.Reference Bratincsak, Moore and El-Said 7 – Reference Canan Hasanoglu, Hezer and Karalezli 11 Important considerations noted in these studies include ensuring adequate fibrinogen levels through administration of cryoprecipitate, and concomitant administration of unfractionated heparin to achieve an anti-Xa level of 0.1–0.3 U/ml. Note that the activated partial thromboplastin time (aPTT) may be prolonged out of proportion to the anti-Xa level in patients receiving tissue plasminogen activator because fibrin degradation products can interfere with the aPTT reaction. Close monitoring of the platelet count and fibrinogen levels is also critical during systemic tissue plasminogen activator infusion. Existing safety and efficacy data on tissue plasminogen activator administration in patients who had undergone cardiac surgery are limited. One case report indicated that tissue plasminogen activator was effective for resolution of a pulmonary embolism in an adult following repair of abdominal aortic aneurysm.Reference Cable and Cherry 12 Another case report showed that urokinase plasminogen activator, another fibrinolytic agent, was effective in the treatment of acquired catheter-associated venous thrombosis in two children treated within 24 hours and 6 days of cardiac surgery, with no bleeding noted.Reference Pilloud, Rimensberger, Humbert, Berner and Beghetti 13
Given the serious sequelae that may occur, clinicians must remain vigilant to monitor for venous thrombosis during postoperative paediatric critical care. Obstruction and thrombosis of major systemic veins can occur postoperatively, especially in patients with indwelling central venous catheters.Reference Borasino, Diaz, El Masri, Dabal and Alten 14 , Reference Wright and Watts 15 If obstruction of the innominate vein, subclavian vein, or superior caval vein occurs, lymphatic drainage may be impaired because of obstruction of the thoracic duct. This can result in superior caval vein syndrome, chylopericardium, or chylothorax.Reference Mery, Moffett and Khan 16 – Reference Biewer, Zurn and Arnold 18 In one study of children after cardiac surgery, 51.8% of confirmed cases of chylothorax were related to venous thromboembolism; therefore, the authors concluded that persistent vessel occlusion may prevent patients from undergoing future treatments, diagnostic studies, or cardiac surgical interventions.Reference Bauman, Moher, Bruce, Kuhle, Kaur and Massicotte 19 Further, chylothorax has been shown to increase hospital length of stay, associated costs, and the risk for mortality because of serious metabolic, immunological, and nutritional complications.Reference Mery, Moffett and Khan 16 , Reference Soto-Martinez and Massie 20 , Reference Chan, Russell, Williams, Van Arsdell, Coles and McCrindle 21
Because of the risks associated with both thrombosis and thrombolysis, sensitive and specific diagnostic means are necessary to definitively determine whether there is a thrombosis. The D-dimer rapid blood test is a very sensitive – but not specific – test, but is of limited utility in patients dependent on instruments after surgery.Reference Carrier, Righini and Djurabi 22 – Reference Wells, Anderson and Rodger 24 In our patient population, presence of symptoms led to examination and diagnosis using ultrasound scanning, or venography if results were equivocal with high clinical suspicion, and thrombolytics were considered if the thrombus was felt to have haemodynamic consequences, to threaten future palliation, or if associated chylothorax was present and was not improving with a trial of anticoagulation treatment. Line-associated thrombi have been reported in up to 30% of children undergoing cardiac surgery when all patients were screened prospectively with echocardiography, venography, and venous ultrasound scanning.Reference Hanslik, Thom and Haumer 25 In this study, venography was most effective in detecting thrombi in the cavae and subclavian veins, but ultrasound scanning was more sensitive for detecting jugular thrombi. Current diagnostic strategies rely on the sequential use of these tests based on clinical probability of disease.Reference Le Gal and Righini 26
In the current study, we report our use of tissue plasminogen activator for venous thrombosis in a paediatric cohort within 3 months following cardiac surgery. In this complex and high-acuity population, there was improvement in the thrombus burden and decrease in thrombus-associated chylous drainage, with minimal morbidity attributable to tissue plasminogen activator observed. On the basis of these results, we have developed a consistent approach for patients with significant venous thrombosis that is associated with chylous drainage, with the impairment of venous return or cardiac output, or that has the potential to preclude future therapeutic or palliative intervention (Table 4). After diagnosis of venous thrombosis and before initiation of tissue plasminogen activator infusion, a thorough family history should be obtained to determine whether there is a family history of thrombophilia or other coagulation-related abnormalities. In addition, given that chylothorax is associated with a massive loss of clotting factors, a thrombotic evaluation at this time could be inaccurate; thus, we did not perform this testing acutely, but patients were followed up with haematological investigation during outpatient evaluation.
Approach to treatment of venous thrombosis in paediatric patients after cardiac surgery.

tPA=tissue plasminogen activator
This study was limited by our retrospective observational methodology and the small sample size. Evaluating a small number of patients may potentially contribute to type-II statistical error, in which we may have been unable to recognise increased complication rates within the small sample size. Further study is warranted with a larger sample size utilising a randomised study design or case-matching between patients who receive tissue plasminogen activator compared with those treated with heparin for venous thromboembolism.
Conclusions
On the basis of our experience with 13 patients, administration of tissue plasminogen activator for venous thrombi is efficacious and can be a reasonably safe intervention following cardiac surgery. On the basis of review of the literature and our series, the risk profile may be different than what is reported in adults. A thoughtful risk–benefit profile must dictate the intervention for any given patient.
Acknowledgements
None.
Conflicts of interest
The authors have no conflicts of interest.
Financial Support
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Ethical standard statement
The authors assert that all procedures contributing to this work comply with the ethical standards of relevant national guidelines and the study was approved by the Cincinnati Children’s Hospital Institutional Review Board.