INTRODUCTION
Language is a skill that most of us take for granted. We use it automatically and, for the most part, effortlessly, and can enjoy participating in conversations without having to think about the rapid computations that occur in our brains as we speak. It allows us to have our own unique form of social interaction and facilitates our ability to solve complex problems. It allows us to write our ideas down on paper and read what others have said, even over distant locations or periods of time. Language is, in fact, a significant part of what makes us human.
When language is taken away from us—as can happen after a brain injury—we are forced to realize how valuable it is and how much we depend on it in our everyday lives. We begin to understand how complicated language is, the many different ways in which it can be affected, and how difficult it is to regain once it is lost. Thus, the study of language disorders after an injury to the brain has helped us to understand more about the building blocks of human language, how these change after injury, and hopefully, how we can use this information to assist those who have been afflicted.
In discussing language disorders, it is important to distinguish them from disorders of “speech”. For this review, the term “language” will refer to a core system that enables the user to assign or decode a symbol (word, sign, or other form of linguistic label) to an object or concept they want to convey or comprehend, and also to apply the appropriate grammatical rules to arrange or decipher phrases and sentences. In this definition, language is thus the “engine” of communication, without which the elaborated sharing of verbal information cannot take place. When language is disrupted in this way as a result of injury to the brain, we refer to this as “aphasia”. On the other hand, “speech” is defined here as the mechanism by which language is orally expressed and constitutes how an utterance is ultimately articulated. Some individuals may have a motor speech deficit that makes it difficult to produce words (e.g., some form of dysarthria) or to coordinate complex movements for articulation (i.e., apraxia of speech).
HISTORICAL STUDIES OF LANGUAGE DISORDERS AND THE BRAIN
Many textbooks suggest that the study of brain and language disorders began in the 19th century, but, in fact, the field has a long and scholarly past. The oldest records go back to the ancient Egyptians around 3000 B.C. with a papyrus described by Edwin Smith. In hieroglyphics, a head-injured man is described who became “speechless” when pressure was applied to the area of his injury. The ancient Greeks also wrote accounts of speech loss after brain injury and further associated these with a paralysis on the right side of the body (Corpus Hippocraticum).
Despite numerous intervening reports over the centuries, Pierre Paul Broca gets credit for first associating language with a specific region of the brain (Paul Broca, Reference Broca1861b). While working as a surgeon at a long-term care institution outside of Paris, Broca encountered a patient who could only produce the utterance “tan, tan” each time he attempted to speak. At autopsy, Broca observed an area of softening in the inferior frontal gyrus. Several months later, Broca saw another patient with a similar disorder who also had damage to the inferior frontal gyrus. At that point, Broca concluded that “the integrity of the third frontal convolution (and perhaps of the second) seems indispensable to the exercise of the faculty of articulate language.” (Paul Broca, Reference Broca1861a).
With additional cases, Broca realized the injury was always on the left side, thus establishing the lateralization of the disorder (Broca, Reference Broca1865). This region later became known as Broca’s area, although for many years, numerous reports were published that contradicted Broca’s finding (see Dronkers, Plaisant, Iba-Zizen, & Cabanis, Reference Dronkers, Plaisant, Iba-Zizen and Cabanis2007). It was Broca’s impression that his patients understood everything that was said to them, which is why he objected to Trousseau coining the term “aphasia” (or loss of language; Broca, Reference Broca1864). Nevertheless, the term prevailed and the disorder Broca described was later referred to as “Broca’s aphasia”.Footnote 1
Thirteen years after Broca’s original publications, Carl Wernicke described two cases of a very different kind of aphasia that involved comprehension deficits and fluent speech without the production difficulties described by Broca (Wernicke, Reference Wernicke1874). Such cases had been described before, but based on the autopsy results of one of these patients, Wernicke attributed the comprehension deficits to the posterior portion of the left superior temporal gyrus, a region that later came to be known as Wernicke’s area. Wernicke incorporated Broca’s findings with his own cases and proposed a novel model of language processing that included the notion that language functions could also be disrupted after injury to the connecting pathways (e.g., the arcuate fasciculus) that transferred information from Wernicke’s to Broca’s areas. Wernicke’s model of language, later modified by Lichtheim (Reference Lichtheim1885) and renewed by Geschwind (Reference Geschwind1965), forms the basis of most models of language published in textbooks today.
This classic model was not always held in favor, however, as many additional models were proposed with the idea that aphasia was caused by a more generalized impairment (e.g., Freud, Reference Freud1891; Goldstein, Reference Goldstein1948; Head, Reference Head1926; Jackson, Reference Jackson1878, Reference Jackson1879; Lashley, Reference Lashley1950). The Russian neuropsychologist, Alexandre Luria, had the most detailed alternative account, describing different components or “factors” of cognitive functions that could be localized in the brain that, when damaged, led to constellations of different syndromes including aphasia. His work, compiled over many years of observations, included diagrams of the areas of the skull that were penetrated by gunshot wounds acquired during World War II (Luria, Reference Luria1947, Reference Luria1966). Luria’s many works form the model still used by neuropsychologists and speech pathologists throughout Russia today.
At the same time that Geschwind was modifying the Wernicke-Lichtheim model of aphasia in the mid-20th century, the fields of speech-language pathology, neuropsychology, and behavioral neurology were growing and changing the way that aphasia was described and treated. Several new language assessment tools were developed that enabled clinicians to assess the extent of the disorder so that diagnosis and treatment could be improved (Porch, Reference Porch1967; Schuell, Reference Schuell1965). The Boston Diagnostic Aphasia Examination (BDAE; Goodglass & Kaplan, Reference Goodglass and Kaplan1972) provided profiles for classifying the different types of aphasia, incorporating both clinical and linguistic features. The Western Aphasia Battery (WAB; Kertesz, Reference Kertesz1982) later added a numeric scoring system to facilitate patient classification. To assess more specific deficits, specialized tests were developed, such as the Boston Naming Test, designed to examine naming deficits across a range of difficulty, further teasing out the nature of the disorder by examining the quality of the responses given (Kaplan, Goodglass, & Weintraub, Reference Kaplan, Goodglass and Weintraub1983).
Linguistic analyses of language disorders also began to emerge around the middle of the 20th century, providing a new perspective on language organization. Zurif, Caramazza, and Meyerson (Reference Zurif, Caramazza and Meyerson1972) made the important observation that patients with Broca’s aphasia do not, in fact, understand everything, but rather have difficulty understanding sentences containing complex grammatical constructions. By association, Broca’s area came to be known as a “center” for syntactic processing. Similar attempts at localization were investigated in other linguistic domains, such as morphology, lexical-semantics, phonetics, and phonology.
Around this time, the emergence of new neuroimaging techniques became key in defining the brain areas that might be ascribed to such language disorders, whether they were clinical diagnoses or linguistic descriptions. The early computerized tomographic (CT) scans of the 1970s had relatively low spatial resolution but were instrumental in delineating the location of brain injuries in vivo, unlike the autopsy studies or skull penetration research that had been the cornerstone of localizationist theories. The Wernicke-Lichtheim model was now being called back into question as investigators were finding that brain–behavior relationships such as the association between Broca’s area and Broca’s aphasia were not as clear as once thought (e.g., Mohr, Reference Mohr1976), nor were the boundaries of these classic brain regions well delineated (e.g., Bogen & Bogen, Reference Bogen and Bogen1976).
Thus, by the early 1980s, improved descriptions of language were added to theoretical models of brain–behavior relationships, along with better assessment tools and new ways to view the brain after injury. The predominate theories were essentially serial processing models in which information passed from Wernicke’s area to Broca’s area by way of the fiber tract that connected them. The precise functions of these two areas was still under debate, a discussion that would continue well into the next decades.
LANGUAGE RESEARCH IN THE LATE 20TH CENTURY AND BEYOND
Neuroimaging
The biggest advance in understanding brain-language relationships and language disorders was triggered by remarkable advancements in computer technology and computer-based neuroimaging in the late 20th century, allowing researchers to visualize brain structures in three dimensions with high resolution and to monitor functional brain activity via blood flow and metabolism. These tools led to an eruption of innovative new ideas that expanded our understanding of the linguistic brain into a broader network with sub-networks and extensive interconnections. Below, we organize these discoveries in terms of the tools that were used with brain-injured individuals to investigate the brain basis of language.
Lesion-symptom mapping
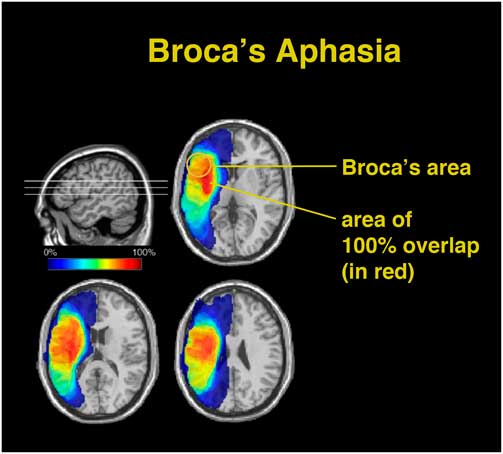
Using computerized reconstructions of patients’ lesions based on CT and MRI scans, we are now able to transform an individual patient’s imaging data into standard neuroimaging space, so that the lesions of large groups of patients can be directly compared. Reconstructed lesions of patients who share the same disorder or syndrome can be superimposed on each other to determine if a common area of overlap can be found. Generally, studies using these techniques have confirmed that aphasia syndromes do not localize to small, discrete regions of the brain such as Broca’s or Wernicke’s areas (e.g., Dronkers & Ludy, Reference Dronkers and Ludy1998; Kertesz, Harlock, & Coates, Reference Kertesz, Harlock and Coates1979; Naeser & Hayward, Reference Naeser and Hayward1978). For example, patients with a chronic Broca’s aphasia (> 6 months) have lesions in Broca’s area only approximately 75% of the time (Dronkers & Baldo, Reference Dronkers and Baldo2010; see Figure 1). In fact, small lesions that affect only Broca’s area lead to a transient mutism that resolves in 3 to 6 weeks (Dronkers, Redfern, & Knight, Reference Dronkers, Redfern and Knight2000; Penfield & Roberts, Reference Penfield and Roberts1959). This mutism certainly reflects a contribution of Broca’s area to speech production, but the rapid recovery indicates that Broca’s area is only one part of a more complicated system.
Overlapping of lesions in 36 individuals with Broca’s aphasia persisting longer than one year. The area of 100% overlap (shown in red) is large and encompasses structures beneath the pars opercularis and triangularis, the region collectively known as Broca’s area. Broca’s area is only lesioned in approximately 75% of these cases. (Adapted from Dronkers & Baldo, Reference Dronkers and Baldo2010.)

In fact, lesions producing long-lasting Broca’s aphasia are typically large and involve neighboring tissue of the inferior and middle frontal gyri, insula, basal ganglia, and surrounding white matter (see Figure 1). Injury to these structures each produce different symptoms that ultimately contribute to the overall disorder. For example, one symptom that co-exists with Broca’s aphasia is “apraxia of speech,” a problem in coordinating the different articulators necessary for speech production. Individuals diagnosed with apraxia of speech (regardless of aphasia type) have a common area of infarction in the superior pre-central gyrus of the insula (Dronkers, Reference Dronkers1996).
Importantly, individuals without apraxia of speech have lesions that completely spare the superior pre-central gyrus of the insula, despite encompassing much of the same left hemisphere territory. Apraxia of speech can occur in isolation, but is a common occurrence in cases of Broca’s aphasia. Thus, lesions associated with Broca’s aphasia are not restricted to any one area; rather, the different isolated symptoms and their associated brain regions combine together to produce a persisting syndrome such as Broca’s aphasia.
Regarding Wernicke’s area and Wernicke’s aphasia, individuals with lesions constrained to Wernicke’s area also exhibit only a transient Wernicke’s aphasia that resolves relatively quickly. Individuals with a persisting Wernicke’s aphasia may have some involvement of Wernicke’s area, but a large critical area of overlap is in the posterior middle temporal gyrus, and particularly, the underlying white matter (Dronkers & Baldo, Reference Dronkers and Baldo2010; Dronkers, Redfern, & Ludy, Reference Dronkers, Redfern and Ludy1995). The involvement of white matter is key to understanding the clinical presentation of Wernicke’s aphasia and will be addressed further below.
Voxel-based mapping methods
Recently, voxel-based morphometry (VBM; see Ashburner & Friston, Reference Ashburner and Friston2000) and voxel-based lesion symptom mapping (VLSM; Bates et al., Reference Bates, Wilson, Saygin, Dick, Sereno, Knight and Dronkers2003) were developed to statistically relate brain changes to clinical symptoms in progressive illnesses and in stroke, respectively. Unlike previous lesion analysis techniques, VBM and VLSM allow for the analysis of continuous data across a range of patient performance and aphasia severity, rather than simply comparing a subset of patients with and without a particular syndrome or diagnosis. In this way, these techniques are statistically very powerful as they make use of all available data and calculate statistics to test the relationship of language (or other cognitive) symptoms to discrete brain regions within each voxel (or three-dimensional (3D) pixel). VLSM and VBM techniques have further refined our understanding of the roles that specific brain regions play in supporting particular speech and language processes (see Baldo, Wilson, & Dronkers, Reference Baldo, Wilson and Dronkers2012; Mechelli, Price, Friston, & Ashburner, Reference Mechelli, Price, Friston and Ashburner2005, for reviews).
The use of VBM has been particularly useful in studying patients with language deficits associated with neurodegenerative disease. Recent work using VBM in primary progressive aphasia (PPA; Mesulam, Reference Mesulam2001), a neurodegenerative disorder that initially affects language, has revealed at least three variants of PPA (semantic, non-fluent, and logopenic), each involving different brain regions and different language profiles (Gorno-Tempini et al., Reference Gorno-Tempini, Dronkers, Rankin, Ogar, Phengrasamy, Rosen and Miller2004). Other VBM analyses (e.g., Mummery, Shallice, & Price, Reference Mummery, Shallice and Price1999) have corroborated earlier pioneering clinic-pathological studies implicating the anterior temporal pole in the semantic variant, also known as semantic dementia (Hodges, Patterson, Oxbury, & Funnell, Reference Hodges, Patterson, Oxbury and Funnell1992), specifically in the processing of semantic memory.
Other regions that have been highlighted through the use of VLSM in aphasic stroke patients include the left anterior temporal lobe for semantic production (Mirman et al., Reference Mirman, Chen, Zhang, Wang, Faseyitan, Coslett and Schwartz2015). This finding is consistent with the kind of naming errors observed in neurosurgical patients undergoing resection of the left anterior temporal lobe and in those with primary progressive aphasia with anterior lobe atrophy (see below). Another VLSM study conducted in neurosurgical patients sought to tease out the different contributions to naming within the temporal lobe (Wilson et al., Reference Wilson, Lam, Babiak, Perry, Shih, Hess and Chang2015). Those with pending anterior temporal lobe resections were found to have significant naming deficits pre-surgery, but resections in the left posterior middle temporal gyrus and posterior ventral temporal areas were most predictive of naming deficits post-surgery. Of course, these temporal areas are connected to each other via several major fiber pathways and the contribution of these pathways in supporting semantic processing is still being unraveled.
VLSM can also be used to reveal combinations of regions that support more complex language functions. For example, this technique was used to examine the left hemisphere regions necessary for the comprehension of different sentence types, ranging from simple declarative sentences (e.g., “The girl is sitting”) to more complex grammatical structures (e.g., “It’s the clown that the girl chases”; Dronkers, Wilkins, Van Valin, Redfern, & Jaeger, Reference Dronkers, Wilkins, Van Valin, Redfern and Jaeger2004). Patients listened to sentences and were asked to choose the picture that best depicted the stimulus they heard. The VLSM analyses revealed five different brain regions that were important for language comprehension, but each one was associated with a different type of deficit. Lesions to the left posterior middle temporal gyrus and underlying white matter caused the most severe comprehension problems, with difficulty in understanding even the simplest sentence forms (see Figure 2a).
(A) VLSM plot showing positive t-values (in red) in the posterior middle temporal gyrus (pMTG), obtained by comparing patients with and without lesions at each voxel on the CYCLE-R sentence comprehension measure. Aphasic individuals with lesions in the pMTG had difficulty understanding even the simplest sentence forms. (B) Composite of all regions found to be significant on the CYCLE-R sentence comprehension measures, shown in MNI space. As the sentences became more syntactically complex, these additional regions were implicated. (Adapted from Dronkers et al., Reference Dronkers, Wilkins, Van Valin, Redfern and Jaeger2004, and Turken & Dronkers, Reference Turken and Dronkers2011.)

As the sentences became more complex, numerous other processes and supporting brain regions were implicated (see Figure 2b). These results showed that many left hemisphere regions outside classical Wernicke’s area are involved in the comprehension of language, with each area becoming important depending on the complexity and demands of the comprehension task.
Recent papers have further refined these voxel-based mapping techniques by showing the importance of using non-parametric permutation-based statistics, incorporating potentially confounding covariates such as lesion volume and chronicity, accounting for limited coverage across the entire brain, using multivariate statistics, and reporting statistical maxima rather than center-of-mass results (e.g., Inoue, Madhyastha, Rudrauf, Mehta, & Grabowski, Reference Inoue, Madhyastha, Rudrauf, Mehta and Grabowski2014; Mah, Husain, Rees, & Nachev, Reference Mah, Husain, Rees and Nachev2014; Rorden & Karnath, Reference Rorden and Karnath2004; Wilson et al., Reference Wilson, Lam, Babiak, Perry, Shih, Hess and Chang2015).
Furthermore, these techniques can be combined with white matter analysis techniques to identify both critical grey and white matter correlates of language (e.g., Baldo, Katseff, & Dronkers, Reference Baldo, Katseff and Dronkers2012; Mirman et al., Reference Mirman, Chen, Zhang, Wang, Faseyitan, Coslett and Schwartz2015). While functional imaging techniques reveal broad territories involved in language (see below), lesion-symptom mapping techniques such as VLSM identify brain regions that are clearly necessary for normal language functioning, for without them, patients cannot successfully communicate.
Diffusion MRI
Another significant advancement has been the use of MR diffusion imaging (dMRI) to investigate white matter connections and their role in language as well as patterns of language recovery. dMRI calculates the magnitude and direction of water diffusion for each voxel and is based on the premise that water diffuses more rapidly along the axis of large fiber bundles as compared to grey matter and cerebrospinal fluid (Alexander, Lee, Lazar, & Field, Reference Alexander, Lee, Lazar and Field2007). In brain injury, this information can be used to quantify microstructural tissue properties that reflect damage to these pathways, which can then be correlated with behavioral deficits.
Tractography further uses diffusion data to reconstruct white matter pathways that can then be examined for size, length, or structural integrity (Catani, Howard, Pajevic, & Jones, Reference Catani, Howard, Pajevic and Jones2002). Reconstruction of fiber pathways based on newer acquisition strategies (e.g., high angular resolution diffusion-weighted imaging, HARDI) and more complex models (e.g., constrained spherical deconvolution, CSD) are better able to resolve such problems as fibers that cross within voxels (Tournier, Mori, & Leemans, Reference Tournier, Mori and Leemans2011) and can provide appropriate tract-specific measurements of tract integrity (Dell’Acqua, Simmons, Williams, & Catani, Reference Dell’Acqua, Simmons, Williams and Catani2013).
Overall, tractography based on these advanced models as well as those using the classic diffusion tensor method enables researchers to gain insights into pathways connecting cerebral language areas and their functional contributions (for reviews, see Bajada, Lambon Ralph, & Cloutman, Reference Bajada, Lambon Ralph and Cloutman2015 and Dick, Bernal, & Tremblay, Reference Dick, Bernal and Tremblay2014). This revived hodological framework offers an important methodological advancement, as now DTI can reveal, in vivo, how damage to specific fiber tracts are responsible for particular deficits (for a more in-depth discussion see Catani & Mesulam, Reference Catani and Mesulam2008).
Studies using DTI techniques and various types of tractography in patients with acquired brain damage have shown that tracts, such as the arcuate fasciculus (AF), contribute to distinct language production behaviors (Ivanova et al., Reference Ivanova, Isaev, Dragoy, Akinina, Petrushevskiy, Fedina and Dronkers2016), particularly mapping sounds with articulatory (motor) stereotypes (Breier, Hasan, Zhang, Men, & Papanicolaou, Reference Breier, Hasan, Zhang, Men and Papanicolaou2008; Kümmerer et al., Reference Kümmerer, Hartwigsen, Kellmeyer, Glauche, Mader, Klöppel and Saur2013), and the processing of complex syntax (Grossman et al., Reference Grossman, Powers, Ash, McMillan, Burkholder, Irwin and Trojanowski2013; Wilson et al., Reference Wilson, Galantucci, Tartaglia, Rising, Patterson, Henry and Gorno-Tempini2011). Temporal tracts, such as the inferior longitudinal fasciculus (ILF), inferior frontal-occipital fasciculus (IFOF), and potentially also the uncinate fasciculus (UF) and middle longitudinal fasciculus, have been shown to be mainly involved in language comprehension (Ivanova et al., Reference Ivanova, Isaev, Dragoy, Akinina, Petrushevskiy, Fedina and Dronkers2016; Kümmerer et al., Reference Kümmerer, Hartwigsen, Kellmeyer, Glauche, Mader, Klöppel and Saur2013).
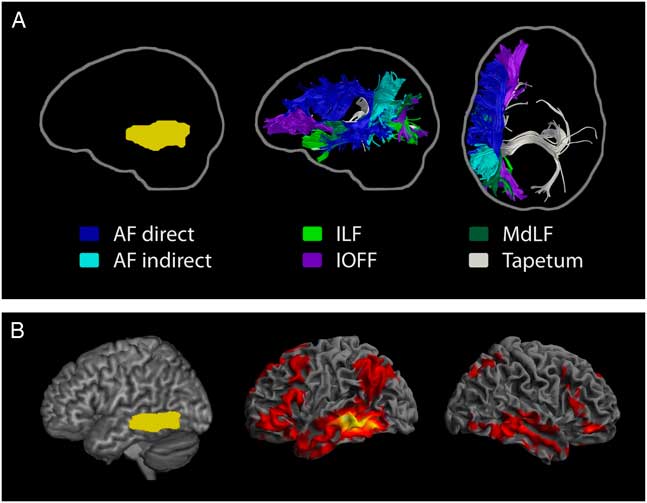
In particular, the white matter underlying the left posterior middle temporal gyrus contains branches of all the above-named tracts as well as the inter-temporal fibers of the corpus callosum (tapetum; Turken & Dronkers, Reference Turken and Dronkers2011; see Figure 3a). Lesions beneath the left posterior middle temporal gyrus disrupt extensive connections to other areas of the brain, possibly explaining why patients with injuries to these fiber tracts have such severe and persisting language comprehension disorders.
Such findings provide anatomical support for models of language processing that have suggested that a dorsal stream (i.e., above the Sylvian fissure) is critical for mapping speech sounds to articulation and a more ventral (i.e., temporal lobe) stream participates in mapping sound to meaning (see Bornkessel-Schlesewsky, Schlesewsky, Small, & Rauschecker, Reference Bornkessel-Schlesewsky, Schlesewsky, Small and Rauschecker2015; Hickok & Poeppel, Reference Hickok and Poeppel2007; Saur et al., Reference Saur, Kreher, Schnell, Ku, Vry, Umarova and Rijntjes2008). The dorsal stream in these models would be supported primarily by the AF, responsible for the serial processing of information involved in phonological and syntactic processing and the language output system. The ventral stream would be supported by temporal lobe tracts such as the IFOF, ILF, and UF, involved in parallel processing of linguistic input critical for the lexical-semantic system.
More recent analyses of diffusion imaging data from aphasic individuals examining the functional significance of tract segments (rather than whole tracts) revealed a more complex picture, with portions of the dorsal AF and ventral ILF and IFOF associated with deficits in both language production and comprehension (Ivanova et al., Reference Ivanova, Isaev, Dragoy, Akinina, Petrushevskiy, Fedina and Dronkers2016). As studies using diffusion imaging in brain-injured individuals evolve, the field will continue its examination of the role of fiber pathways in the processing of language.
Functional neuroimaging
While structural imaging techniques are used to evaluate the physical abnormalities of the injured brain, functional brain imaging emerged in the later 20th century as a way to study ongoing activity in both normal and atypical brains. Measurements of metabolic activity and blood flow began to contribute to the study of speech and language mechanisms, initially using tools such as positron emission tomography (PET) and single photon emission computerized tomography (SPECT). Here, a radioactive tracer is used to track glucose metabolism or blood flow, both of which are correlated with active brain tissue. In aphasia, changes have been found in both lesioned and non-lesioned brain regions, suggesting a broader dysfunctional network in aphasia (Metter et al., Reference Metter, Jackson, Kempler, Riege, Hanson, Mazziotta and Phelps1986), particularly for subcortical lesions (Démonet, Puel, Celsis, & Cardebat, Reference Démonet, Puel, Celsis and Cardebat1991).
After PET, functional neuroimaging, particularly functional MRI (fMRI), soon became the pervasive method of investigating brain-behavior relationships in the healthy human brain, by measuring the amount of blood flow to regions of the brain while the participant executes a particular task. Meta-analyses of the first generation of PET and fMRI studies revealed a broad network of language areas in the left hemisphere in the neurologically normal brain that are active during language processing, including the middle and inferior temporal gyri, fusiform and angular gyri, and left prefrontal areas (e.g., Binder et al., Reference Binder, Frost, Hammeke, Cox, Rao and Prieto1997; Price, Reference Price2000). Other, unexpected findings generated from functional imaging studies included the observation of activation in the cerebellum (see Mariën et al., Reference Mariën, Ackermann, Adamaszek, Barwood, Beaton, Desmond and Ziegler2014 for a review), and the right hemisphere during linguistic and verbal cognitive tasks (Vigneau et al., Reference Vigneau, Beaucousin, Hervé, Jobard, Petit, Crivello and Tzourio-Mazoyer2011).
In the study of language disorders, PET and fMRI have been applied more recently to identify areas of under- and over-activity following a brain injury and how those changes relate to language deficits and recovery (Perani et al., Reference Perani, Cappa, Tettamanti, Rosa, Scifo, Miozzo and Fazio2003; Saur et al., Reference Saur, Lange, Baumgaertner, Schraknepper, Willmes, Rijntjes and Weiller2006; Weiller et al., Reference Weiller, Isensee, Rijntjes, Huber, Müller, Bier and Diener1995). With respect to recovery, some studies demonstrate that right hemisphere compensation is responsible for improvement in language over time (e.g., Rosen et al., Reference Rosen, Petersen, Linenweber, Snyder, White, Chapman and Corbetta2000), while others show perilesional activity or involvement of other undamaged areas in the lesioned hemisphere (e.g., Fridriksson, Richardson, Fillmore, & Cai, Reference Fridriksson, Richardson, Fillmore and Cai2012). Most studies reveal a mixture of these patterns (for reviews, see Crinion & Leff, Reference Crinion and Leff2007; Thompson & den Ouden, Reference Thompson and den Ouden2008). Very likely, the degree of contralateral compensation and involvement of domain-general areas depends on the linguistic impact of the areas that have been injured (Geranmayeh, Brownsett, & Wise, Reference Geranmayeh, Brownsett and Wise2014; Heiss, Kessler, Thiel, Ghaemi, & Karbe, Reference Heiss, Kessler, Thiel, Ghaemi and Karbe1999).
In addition to measurements of blood flow, event-related potentials (ERPs), extracted from electroencephalograms (EEGs), were introduced as a way of measuring the time course of language processing, rather than just its location (Kutas & Hillyard, Reference Kutas and Hillyard1980). In patients, electrophysiological measurements are also used in electrocorticography (ECoG) where electrode grids are placed on the exposed surface of the brain during neurosurgery to record seizure activity and identify epileptic foci. These direct measurements have revealed novel findings such as the representation of distinct phonetic features within the superior temporal gyrus (Mesgarani, Cheung, Johnson, & Chang, Reference Mesgarani, Cheung, Johnson and Chang2014) and the temporal dynamics of speech production (Flinker et al., Reference Flinker, Korzeniewska, Shestyuk, Franaszczuk, Dronkers, Knight and Crone2015). Increasingly, depth electrodes are being used to record epileptic activity in areas not easily accessible to the neurosurgeon. In such cases, the hippocampus has been found to provide an ongoing semantic context for incoming words, adding the hippocampus to the list of regions actively involved in language processing (Piai et al., Reference Piai, Anderson, Lin, Dewar, Parvizi, Dronkers and Knight2016).
Resting state fMRI
While task-based fMRI studies dominated the literature in the latter part of the 20th century, several unforeseen observations emerged. One of these was the observation that even during so-called “baseline” or resting tasks, when no experimental input is provided and no explicit output is required, the brain still exhibited well-coordinated and organized activity (Raichle et al., Reference Raichle, MacLeod, Snyder, Powers, Gusnard and Shulman2001). Analysis of this “resting state” activity allowed for the extraction of different networks of areas that co-activate (i.e., areas demonstrating synchronous, spontaneous low-frequency blood flow fluctuations), providing insight into the functional connectivity of the brain (Cordes et al., Reference Cordes, Haughton, Arfanakis, Wendt, Turski, Moritz and Meyerand2000; Smith et al., Reference Smith, Vidaurre, Beckmann, Glasser, Jenkinson, Miller and Van Essen2013).
In the normal brain, the resting-state language network has been shown to encompass not only classical language processing regions, such as Broca’s and Wernicke’s areas, but also adjoining left prefrontal, temporal and parietal regions, including some subcortical structures, such as the caudate bilaterally and the left putamen/globus pallidus and subthalamic nuclei (Muller & Meyer, Reference Muller and Meyer2014; Smith et al., Reference Smith, Vidaurre, Beckmann, Glasser, Jenkinson, Miller and Van Essen2013; Tomasi & Volkow, Reference Tomasi and Volkow2012). Turken and Dronkers (Reference Turken and Dronkers2011) used resting state fMRI (rsfMRI) to identify a frontal-parietal-temporal language comprehension network that was based on left hemisphere brain regions known to be affected in individuals with aphasia. This network also included right hemisphere regions, supporting the importance of right hemisphere mechanisms in language comprehension, as well (see Figure 3b).
(A) Streamline tractography of the major pathways associated with the left posterior middle temporal gyrus (pMTG; shown left in yellow). Results are shown from a neurologically-normal participant in sagittal and axial views and reflect the extensive connectivity affected by a lesion to the left pMTG. The direct and indirect segments of the arcuate fasciculus, the inferior occipito-frontal fasciculus, the middle longitudinal fasciculus, the inferior longitudinal fasciculus, and transcallosal projections, consistent with the tapetum, are shown. (B) Resting state functional connectivity profile of the left pMTG (shown left), warped to MNI stereotaxic space. The red regions in the middle and right panels correlate highly with the left pMTG. (Adapted from Turken & Dronkers, Reference Turken and Dronkers2011.)

To date, there is only a handful of rsfMRI studies involving individuals with aphasia. Overall, they reveal abnormalities in multiple resting-state networks including the language network, demonstrating reduced functional connectivity in networks in the left hemisphere and between left hemisphere networks and right hemisphere regions (Nair et al., Reference Nair, Young, La, Reiter, Nadkarni, Song and Prabhakaran2015; van Hees et al., Reference van Hees, McMahon, Angwin, de Zubicaray, Read and Copland2014a). Also, there seems to be an association between a decrease in functional connectivity in language-cognition resting-state brain networks and residual language abilities (Nair et al., Reference Nair, Young, La, Reiter, Nadkarni, Song and Prabhakaran2015; Zhu et al., Reference Zhu, Chang, Freeman, Tan, Xiao, Gao and Kong2014, but see Yang et al., Reference Yang, Li, Li, Li, Pang, Yao and Chen2016). While these studies are clearly preliminary, they do provide another piece of evidence that language is processed by a non-modular, highly integrated and yet vastly plastic neural system, that encompasses regions well beyond the classical language areas.
As with any technique, neuroimaging analyses of brain-injured patients have their limitations. First and foremost is that injury to one area of the brain almost certainly affects other regions as well. Hypoperfusion, structural and functional disconnections to other areas, and changes within the attentional system are some of the indirect effects associated with brain injuries, even focal ones (e.g., Ivanova et al., Reference Ivanova, Isaev, Dragoy, Akinina, Petrushevskiy, Fedina and Dronkers2016; Jarso et al., Reference Jarso, Li, Faria, Davis, Leigh, Sebastian and Hillis2013; Nadeau & Crosson, Reference Nadeau and Crosson1997; Turken & Dronkers, Reference Turken and Dronkers2011). These factors are not typically seen on standard clinical images, and additional measures need to be performed to account for such effects.
Other Advances
Other Forms of Language Disorders
The exploration of language disorders in other languages has added to our knowledge of how language can be affected by brain injuries. Through cross-linguistic research, we have seen the effects of brain injury in numerous different languages and have learned that aphasia syndromes can present quite differently depending on the typology of the language. For example, Turkish-speaking individuals with Broca’s aphasia do not produce agrammatic speech because this richly inflected language contains words with numerous prefixes and suffixes that cannot be omitted without changing the meaning the word (Bates, Wulfeck, & MacWhinney, Reference Bates, Wulfeck and MacWhinney1991).
Nevertheless, certain “neurolinguistic universals” also exist, such as dissociations in action and object naming, even in languages that do not carry special grammatical markings (e.g., Chinese; Bates, Chen, Tzeng, Li, & Opie, Reference Bates, Chen, Tzeng, Li and Opie1991). Signed languages, like oral languages, is similarly affected by brain injury. Based on findings in deaf individuals with aphasia, the core components of signed languages show the same brain–language patterns seen in hearing individuals, even though the modality is different (Poizner, Klima, & Bellugi, Reference Poizner, Klima and Bellugi1990). Similarly, the study of aphasia in multilingual individuals has taught us that, while lexical items (or even writing systems) of a speaker’s different languages can be differentially affected, deficits in the core systems of language (e.g., morphosyntax, phonology) parallel those in monolinguals (Paradis, Reference Paradis2004).
As mentioned earlier, studies in individuals with primary progressive aphasia (PPA) add to our understanding of brain-language relationships. In particular, the semantic variant of PPA, which affects the ventral and lateral temporal lobes, causes a unique language profile affecting the naming and recognition of objects and persons (particularly low-frequency items), while the processing of grammatical information remains intact. Single word comprehension is also impaired, although the patient can repeat words and sentences without difficulty. This profile is not seen in vascular aphasia and is thought to reflect deficits in semantic memory, since the recognition deficit is consistent across all input modalities (Hodges et al., Reference Hodges, Patterson, Oxbury and Funnell1992; Snowden, Goulding, & Neary, Reference Snowden, Goulding and Neary1989; Warrington, Reference Warrington1975).
Data from neurosurgical patients have also contributed in numerous ways. By stimulating various brain regions and subcortical connections during awake surgery, neurosurgeons can record disruptions in language thus avoiding resecting critical structures (Penfield & Roberts, Reference Penfield and Roberts1959). Early work by Ojemann and colleagues demonstrated great individual variability in language localization, not only in classical language areas, but also in the anterior temporal and parietal lobes, thus questioning classical models.
Recently, the importance of subcortical connections was revealed with electrostimulation of the AF and IFOF, yielding speech arrest and naming difficulty with paraphasic errors (for reviews, see Chang, Raygor, & Berger, Reference Chang, Raygor and Berger2015; Duffau, Reference Duffau2014). Intraoperative mapping of neurosurgical patients has also revealed that patterns of recovery differ depending on the regions removed (Sanai, Mirzadeh, & Berger, Reference Sanai, Mirzadeh and Berger2008). (Ojemann, Ojemann, Lettich, & Berger, Reference Ojemann, Ojemann, Lettich and Berger1989). Surgical resections in temporal lobe epilepsy have also pointed to the importance of the temporal pole in supporting semantic functions (Lambon Ralph, Ehsan, Baker, & Rogers, Reference Lambon Ralph, Ehsan, Baker and Rogers2012).
Linguistic approaches
In linguistic approaches to studying language disorders, the focus has shifted from adhering to a strict aphasia classification approach, to providing a detailed account of observed speech and language deficits and determining the level of breakdown within existing models of language processing (e.g., Friederici & Singer, Reference Friederici and Singer2015; Hagoort & Indefrey, Reference Hagoort and Indefrey2014; Kay, Lesser, & Coltheart, Reference Kay, Lesser and Coltheart1996). For instance, some contemporary aphasia batteries have abandoned the aphasia classification scheme altogether (e.g., Kay, Coltheart, & Lesser, Reference Kay, Lesser and Coltheart1992; Howard, Swinburn, & Porter, Reference Howard, Swinburn and Porter2010) and rather focus on detecting specific language deficits (e.g., Bastiaanse, Edwards, Mass, & Rispens, Reference Bastiaanse, Edwards, Mass and Rispens2003; Cho-Reyes & Thompson, Reference Cho-Reyes and Thompson2012).
Similarly, most current treatment studies are less focused on aphasia type or fluent/non-fluent distinctions, but rather look to observed patterns of specific linguistic deficits. These are often accompanied by measurements of neurophysiological or structural changes that accompany language gains (van Hees et al., Reference van Hees, Mcmahon, Angwin, de Zubicaray, Read and Copland2014a; Reference Cho-Reyes and Thompson2014b). Some linguistic approaches complement clinical speech-language pathology practice in which the benefits of intense treatment, group therapy, and new techniques are being investigated, sometimes in conjunction with an analysis of accompanying neural changes (e.g., Schlaug, Marchina, & Norton, Reference Schlaug, Marchina and Norton2009). While most studies have evaluated group effects, the ultimate goal is to integrate research into clinical practice to devise treatments that benefit the individual patient and their particular communication problems.
Another important contribution to research on language after brain injury concerns whether different semantic categories are selectively affected in some patients. Examples of such category-specific deficits include difficulty with word classes such as nouns versus verbs (Caramazza & Hillis, Reference Caramazza and Hillis1991) and proper versus common names (Semenza, Reference Semenza2009). Other studies have reported category-specific deficits in domains such as living versus non-living things (Warrington & Shallice, Reference Warrington and Shallice1984) suggesting a more conceptual basis for these distinctions. Some authors have suggested that semantic dissociations could be related more to basic sensory-motor dimensions such as the motoric features of action names (as represented by verbs), sensory characteristics of objects (as with nouns), or the integration of visual and sensory information (as with living things) (Gainotti, Silveri, Daniel, & Giustolisi, Reference Gainotti, Silveri, Daniel and Giustolisi1995).
In fact, manipulability can account for patient deficits in naming both actions and objects, particularly when the lesion involves the motor hand cortex (Arévalo et al., Reference Arévalo, Perani, Cappa, Butler, Bates and Dronkers2007). This may follow for other sensorimotor domains, as well, accounting for such deficits as errors in the naming of musical instruments after lesions to left auditory cortices (Damasio, Tranel, Grabowski, Adolphs, & Damasio, Reference Damasio, Tranel, Grabowski, Adolphs and Damasio2004). These findings remind us that the brain regions involved in naming deficits span both the left and right hemispheres and well outside of the classical brain regions (Damasio et al., Reference Damasio, Tranel, Grabowski, Adolphs and Damasio2004).
Other studies in the linguistic domain include the exploration of the neural basis of such constructs as morphology, syntax, and phonology. While morphology is the system of how words are put together, syntax is the set of rules that governs how words are put together to make phrases or sentences. In recent work, aphasiologists have gone from thinking of Broca’s area as the sole location underlying syntactic processing to accepting that numerous brain regions contribute to the understanding of language, although these may each contribute in different ways, some linguistic, some non-linguistic (e.g., Dick et al., Reference Dick, Bates, Wulfeck, Utman, Dronkers and Gernsbacher2001; Dronkers, Wilkins, Van Valin, Redfern, & Jaeger, Reference Dronkers, Wilkins, Van Valin, Redfern and Jaeger2004; Hickok & Poeppel, Reference Hickok and Poeppel2007; Tyler et al., Reference Tyler, Marslen-Wilson, Randall, Wright, Devereux, Zhuang and Stamatakis2011).
A broader distribution of areas has also been found for phonology, the sound system of language. Phonological errors in naming have been related to pre-motor cortex, pre- and postcentral gyri, and the supramarginal gyrus (Schwartz, Faseyitan, Kim, & Coslett, Reference Schwartz, Faseyitan, Kim and Coslett2012), as well as the precentral gyrus of the insula and the arcuate and superior longitudinal fasciculi (Bates et al., Reference Bates, Wilson, Saygin, Dick, Sereno, Knight and Dronkers2003; Dronkers et al., Reference Dronkers, Plaisant, Iba-Zizen and Cabanis2007; Dronkers, Reference Dronkers1996), depending on the nature of the error made (Bates et al., Reference Bates, Wilson, Saygin, Dick, Sereno, Knight and Dronkers2003; Dronkers et al., Reference Dronkers, Plaisant, Iba-Zizen and Cabanis2007; Dronkers, Reference Dronkers1996; Schwartz et al., Reference Schwartz, Faseyitan, Kim and Coslett2012).
Finally, successful communication relies on both hemispheres of the brain, not just the left. The more pragmatic aspects of language, those that provide additional context such as stress, intonation, and facial expressions, also contribute greatly to the meaning of an utterance. These tend to be more affected after right hemisphere injury, leading to impairments in social cues that complement the morpho-syntactic, semantic, and phonological contributions of the left hemisphere. Other factors such as attention, emotion, insight, and the organization of information, can greatly affect how well a person interacts with their language partner.
Interaction between language and cognition
Although early aphasiologists sometimes spoke of aphasia as a loss of memory for words, the fields of language and memory diverged by the middle of the 20th century (but see Luria, Reference Luria1966). More recent findings, however, have renewed an interest in the close relationship between language and other aspects of cognition. Examples of this include the famous case of H.M., who was treated for epilepsy with a bilateral temporal lobectomy that left him severely amnesic. Early research on H.M. focused on the dissociations he exhibited between implicit versus explicit memory, but later testing revealed that his deficits were not confined to the realm of memory, but also included deficits in language (MacKay, Stewart, & Burke, Reference MacKay, Stewart and Burke1998).
Other studies emerged in the literature showing a strong relationship between language and cognition in aphasic individuals. Specifically, the degree of aphasia severity predicted impaired performance on supposedly non-verbal tasks such as problem-solving and executive functioning (Baldo, Paulraj, Curran, & Dronkers, Reference Baldo, Paulraj, Curran and Dronkers2015). Working memory was found to be related to language abilities, particularly comprehension, in aphasic individuals (Ivanova, Dragoy, Kuptsova, Ulicheva, & Laurinavichyute, Reference Ivanova, Dragoy, Kuptsova, Ulicheva and Laurinavichyute2015; Sung et al., Reference Sung, McNeil, Pratt, Dickey, Hula, Szuminsky and Doyle2009), and Riès and colleagues have shown the effects of cognitive control demands on word selection (Riès, Karzmark, Navarrete, Knight, & Dronkers, Reference Riès, Karzmark, Navarrete, Knight and Dronkers2015). Such new findings strongly suggest that language cannot be studied in isolation, as it has strong connections with other brain networks supporting higher-level cognition. However, such interdependence between language and cognition does not mean that people with aphasia cannot “think” or have lost their intelligence. Even those who are most severely affected by aphasia have thoughts and ideas, can carry on with daily activities, can draw and paint, solve fundamental problems, and are most certainly are aware of their condition. The problem in aphasia is not with thought; it lies more in the ability to verbally mediate and communicate their thoughts and ideas.
Finally, we have learned that the acquired skills of reading and writing are partially dependent on the language network but also involve a unique set of critical brain regions. In the case of reading, a “visual word form area” has been identified in left posterior ventral temporo-occipital cortex that appears to be critical for single-word reading (Dehaene, Reference Dehaene2009). Writing, on the other hand, has been alternately associated with left parietal cortex as well as left ventral temporal cortex (Lorch, Reference Lorch2013). Reading and writing impairments are often observed in individuals with aphasia but can also occur in isolation (alexia and agraphia, respectively). These “pure” forms of reading and writing impairment suggest a unique contribution of neural systems, distinct from the general language network.
Our own experience in studying the neural mechanisms of speech and language disorders has taught us that language is neither exclusively localized nor broadly distributed in the brain; it is a combination of both. While input or output mechanisms such as speech perception and articulation may show consistent patterns of localization, the more complex process of language involves numerous brain regions that work together to support language. Regions of the left temporal lobe (temporal pole, posterior middle temporal gyrus, and underlying white matter) contribute to the knowledge of things in our world as well as what we call them, although such information may be diffusely represented, depending on their relationships to other words, concepts, or motor and sensory functions.
For the processing of complex grammatical information, we see impairments after left frontal injury that include Brodmann’s area 47 and other regions that support executive functions, such as working memory, suggesting that these regions help with the manipulation of information that helps us to understand “who did what to whom” and to produce such constructions correctly. Thus, language also requires the contribution of areas that are more domain-general and support other functions besides just language, regions that become involved when language processing requires assistance from other cognitive systems. This includes functions such as attention, memory, perception, and pragmatics, some of which also rely on the right cerebral hemisphere.
Finally, we cannot forget the labyrinth of axonal connections that bind these structures together, providing the highways that allow the dynamics of language to happen. Thus, language does not just depend on two brain areas and one fiber tract, but is instead the result of a large network made up of constellations of neurons and neural events that contribute, as needed, to the task at hand.
FUTURE POSSIBILITIES
Predicting the future is an impossible challenge, but there are several promising approaches that will likely carry us into the next few decades. Viewing the brain as a “connectome” and language disorders as “disconnectomes” is one way of pursuing a network approach. This includes the recognition that there are both local networks and more broadly distributed ones that combine in different ways to support distinct language and cognitive functions. Thinking more about the remote effects of brain lesions as well as how grey and white matter structures mature across the lifespan will also help us to understand how these networks are developed and how they interact. Perhaps the classification of cortical areas according to their connections will become a more fruitful endeavor than thinking about the reverse relationship, as we currently do.
Megascience is certainly on the horizon with “big data” from large, multicenter studies enabling robust multivariate analyses that can be used to evaluate brain–behavior relationships on a large scale. The “Big Brain” project is already providing microscopic information on a 3D neuroanatomical reference brain, to assist with human brain mapping endeavors such as receptor mapping, fiber tracking, and gene expression (Amunts et al., Reference Amunts, Lepage, Borgeat, Mohlberg, Dickscheid, Rousseau and Evans2013). Artificial intelligence models will improve with additional data, and the modeling of virtual lesions may also help us understand the effects of brain injury without depending on unfortunate accidents of nature. Techniques that offer high temporal resolution (ECoG, ERPs, and magnetoencephalography) will help settle the question of whether language operates in a serial or distributed manner and which components of language come online at which points in time.
For those working with brain-injured individuals, our greatest hope is that we will see major advances in therapies to facilitate neural recovery in the coming years. This will require a better understanding of the mechanisms of recovery as well as the development of new therapies and neural prostheses. For instance, transcranial stimulation techniques, such as transcranial magnetic stimulation (TMS) and transcranial direct current stimulation (Hamilton, Chrysikou, & Coslett, Reference Hamilton, Chrysikou and Coslett2011) have been used enhance language functions in both healthy and brain-injured individuals (Marangolo et al., Reference Marangolo, Fiori, Calpagnano, Campana, Razzano, Caltagirone and Marini2013; Naeser et al., Reference Naeser, Martin, Nicholas, Baker, Seekins, Kobayashi and Pascual-Leone2005; Schlaug, Marchina, & Wan, Reference Schlaug, Marchina and Wan2011).
The integration of research from the cellular level to the cognitive level is critical for understanding the neurobiology of recovery, such as the role of astrocytes in learning and recovery, and the chemical interactions that may spark new innovations in pharmaceutical interventions. The genetic and environmental influences on brain changes, as well as other factors (e.g., gender, handedness, motivation, intensity of therapy), have been shown to have differential impacts on outcome, and ongoing work is being done to understand how these different factors interact to predict recovery in each individual (Code, Reference Code2001).
We anticipate that future studies will continue to provide further insights into the restoration of damaged fiber tracts, the formation of novel connections, and the recruitment of other pathways not previously involved in linguistic processing. Preliminary studies using stem cells in stroke patients have also produced encouraging results with respect to both safety and tolerability of the treatment, as well as some promising improvements in motor functioning (Kalladka et al., Reference Kalladka, Sinden, Pollock, Haig, McLean, Smith and Muir2016; Steinberg et al., Reference Steinberg, Kondziolka, Wechsler, Lunsford, Coburn, Billigen and Schwartz2016). Whether such improvements are related to the intervention or to spontaneous recovery still needs to be fully evaluated in larger, randomized clinical trials. Hopefully, stem cell studies will soon have an impact on the study of language recovery.
In the area of prosthetics, a few centers have begun to develop brain-machine interfaces to allow paralyzed individuals the ability to control mechanical devices by simply thinking. Aflalo et al. (Reference Aflalo, Kellis, Klaes, Lee, Shi, Pejsa and Andersen2015) implanted quadriplegic individuals with a small grid over the parietal cortex that allows them to volitionally move a prosthetic arm. Such advances may translate to the language domain and help the speech- or language-disordered person to communicate again.
As we ponder the future, it is tempting to imagine that we might soon see the fine details of network activity in real time, and watch the process of recovery as it unfolds. Continued advances in neuroimaging will certainly assist with this progress, as will newer techniques we have not yet imagined. Still, we must keep in mind that revisiting past works and past models also has its place in new research. Finally, while all the new technologies at our disposal are tempting us to go further into the uncharted territories of the brain, it is important to remember that nothing can replace careful clinical assessments, and that our ultimate goal is to improve the quality of life for those with language disabilities.
As we move from the past into the future, we have arrived at the understanding that language is an extremely complex system that requires an extensive and interactive network of brain regions and the fibers them connect them. The areas of the brain that support language are far more extensive than Broca or Wernicke could ever have imagined, and the many fiber pathways that connect cortical regions may play an even more important role in language than previously thought. It is our hope that further advances in understanding the “Brain–Language Connectome” will provide us with the tools for understanding how language is processed in the normal brain, and for assisting our patients in their recovery from brain injury.
ACKNOWLEDGMENTS
This work was supported in part by the U.S. Department of Veterans Affairs, Office of Research & Development CSR&D and R&D Programs and NIH/NIDCD grant 1 R01 DC016345. The contents reported within do not represent the views of the Department of Veterans Affairs or the United States Government. This article was also prepared within the framework of the Basic Research Program at the National Research University Higher School of Economics and supported within the framework of a subsidy by the Russian Academic Excellence Project “5-100”. We are grateful to the members of the Aphasia Center - And Turken, Carl Ludy, Krista Schendel, Brian Curran, Tim Herron, XJ Kang, Allison Zhong, Natalie Kacinek, Jet Vonk, and Janet Patterson - for their insightful comments and lively discussions on this topic. Special thanks go to our research participants who took the time to teach us all about language disorders. The authors state no conflicts of interest.