Migraine is a debilitating neurological condition experienced by approximately 6–8% of men and 15–25% of women in western countries (Ref. Reference Pietrobon and Striessnig1). This high prevalence has led the World Health Organization to rank migraine in the top 20 conditions leading to years lived with disability. This disability results not only from the painful headaches, but also from the host of associated symptoms that co-occur with migraine. The diagnostic criteria for migraine include episodic headache lasting from 4 to 72 h, with two of the following, throbbing, unilateral pain, aggravation on movement, or pain of at least moderate severity, and at least one of the following, nausea or vomiting, or photophobia and phonophobia (Ref. 2). For patients suffering from typical migraine, pain and accompanying symptoms have no obvious genetic, structural or molecular cause. This manuscript reviews the current understanding of migraine, focusing on the role of calcitonin-gene-related peptide (CGRP) in the context of neurogenic inflammation and photophobia.
CGRP is a multifunctional neuropeptide found in every organ system in the body (Refs Reference Wimalawansa3, Reference van Rossum, Hanisch and Quirion4, Reference Russo, Dickerson and Lajtha5, Reference Recober and Russo6). CGRP immunoreactivity is especially prevalent in the trigeminal nerve, where it is found in nearly 50% of the neurons (Refs Reference Tajti7, Reference Eftekhari8). Its expression in the trigeminal nerve is of particular interest given the role of the trigeminovascular system in migraine (Ref. Reference Messlinger9). The peripheral trigeminovascular system consists of sensory fibres of the trigeminal ganglion that project from meningeal blood vessels (both dural and pial) to brainstem trigeminal nuclei (Refs Reference Messlinger10, Reference Liu, Broman and Edvinsson11). The central trigeminovascular system refers to regions of the central nervous system (CNS) that further process this input: the spinal trigeminal nucleus and posterior thalamus. At the peripheral nerve endings, CGRP is recognised as the most potent vasodilatory peptide (Ref. Reference Brain and Grant12). CGRP receptors are located on cerebral vascular smooth muscle, where they cause vasodilation (Refs Reference Edvinsson13, Reference Moreno14, Reference Oliver15). In addition to vasodilation, peripheral release of CGRP also triggers mast cell degranulation, which contributes to neurogenic inflammation together with substance P (Refs Reference Brain and Grant12, Reference Ottosson and Edvinsson16, Reference Theoharides17). CGRP is often co-released with substance P (Refs Reference Skofitsch and Jacobowitz18, Reference Lundberg19, Reference Lee20). CGRP receptors have been identified on dural mast cells (Ref. Reference Lennerz21). At the central terminals of the trigeminal nerve, CGRP is a neuromodulator at second-order nociceptive neurons in the spinal trigeminal nucleus caudalis (TNc) (Refs Reference Messlinger9, Reference Fischer22). CGRP has a similar role in the dorsal horn of the spinal cord, where it can induce central sensitisation to tactile stimuli (Ref. Reference Marquez de Prado, Hammond and Russo23). CGRP receptors have been identified in the TNc, a subset of trigeminal ganglion neurons and satellite glia of the trigeminal ganglion (Refs Reference Eftekhari8, Reference Lennerz21, Reference Storer, Akerman and Goadsby24, Reference Fischer, Koulchitsky and Messlinger25, Reference Levy, Burstein and Strassman26). Hence, there are several sites of CGRP receptor action that might be relevant to migraine.
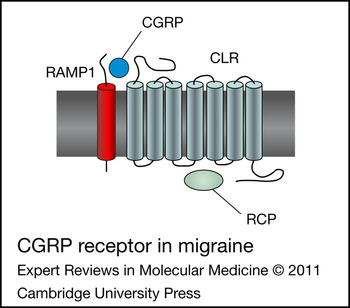
The CGRP receptor is a fairly unique multimer of a G-protein-coupled receptor called calcitonin-like receptor (CLR) and a small transmembrane protein called receptor activity-modifying protein 1 (RAMP1) (Fig. 1) (Refs Reference Archbold27, Reference Barwell28). A cytoplasmic protein, receptor component protein (RCP), enhances receptor coupling to the G-protein signalling machinery (Ref. Reference Evans29). CLR requires RAMP1 for both its trafficking to the cell surface and binding of CGRP (Ref. Reference McLatchie30). Our data indicate that RAMP1 is the functional rate-limiting subunit of the receptor in the nervous system and vascular smooth muscle (Refs Reference Zhang, Dickerson and Russo31, Reference Russo32, Reference Zhang33). The crystal structure of the N-terminal ectodomain of the CGRP receptor has recently confirmed that a heterodimer of CLR and RAMP1 forms a CGRP binding pocket and that the clinically effective CGRP receptor antagonists block this peptide-binding cleft (Ref. Reference ter Haar34). The observed 1:1 heterodimer is consistent with a crosslinking study of full-length receptors (Ref. Reference Hilairet35). By contrast, bimolecular fluorescence complementation indicated that the CGRP receptor contains two CLRs with only one RAMP1 (Ref. Reference Heroux36). The possibility that the CGRP receptor can also exist as a tetramer of two CLRs and two RAMP1 proteins with two ligand-binding sites is consistent with our data demonstrating that elevation of RAMP1 levels shifts the Hill coefficient of receptor activation from 0.9 to 2.6, which indicates RAMP1-induced positive cooperativity (Ref. Reference Zhang33).
CGRP receptor in migraine. Schematic of the CGRP receptor complex composed of CLR, RAMP1 and RCP. Redrawn from Ref. 186 with permission. Abbreviations: CGRP; calcitonin gene-related peptide; CLR, calcitonin-like receptor; RAMP1, receptor activity-modifying protein 1; RCP, receptor component protein.

In this review, we will first discuss the evidence supporting a role for CGRP in migraine, and then discuss two anatomically distinct mechanisms of CGRP action at peripheral and central sites that might contribute to migraine.
CGRP has a key role in migraine
Although a full understanding of the neural mechanism of migraine remains elusive, there has been a convergence of basic and clinical evidence demonstrating that CGRP is a key molecular player (Ref. Reference Villalon and Olesen37). Several clinical studies have identified a role for CGRP in migraine. Over 20 years ago, it was reported that plasma CGRP levels are increased during migraine (Refs Reference Goadsby, Edvinsson and Ekman38, Reference Juhasz39, Reference Gallai40, Reference Goadsby, Lipton and Ferrari41), although more recent studies have called this into question (Refs Reference Tvedskov42, Reference Tfelt-Hansen and Le43). Elevated CGRP has also been reported in the saliva of migraineurs (Refs Reference Bellamy, Cady and Durham44, Reference Cady45). Remarkably, injection of CGRP induced a delayed, migraine-like headache in 57–75% of migraineurs with and without aura (Refs Reference Hansen46, Reference Lassen47, Reference Asghar48). Because CGRP did not have this effect on healthy controls, it suggests that migraineurs have increased sensitivity to CGRP. CGRP infusion also causes aura in a portion of patients who suffer from migraine with aura (Ref. Reference Hansen46). However, as noted by the authors, the aura episodes might be due to stress from the CGRP infusion procedure and further investigation is warranted. In contrast to CGRP actions on common migraine patients, administration of CGRP elicited migraine-like headaches in only 9–22% of patients with familial hemiplegic migraine (FHM), which was statistically not different from controls (0–10%) (Refs Reference Hansen49, Reference Hansen50). Mutations that could lead to changes in brain excitability have been identified for several forms of FHM (Refs Reference Ophoff51, Reference De Fusco52, Reference Dichgans53) and will not be reviewed here. Whether the differences in CGRP susceptibility between common migraine and FHM patients indicate qualitative or quantitative differences in underlying pathways is open to debate and will probably require studies with larger populations. Certainly, for typical migraines, blocking CGRP release and receptor activity are useful therapeutic strategies. This was first shown by triptan drugs that restored CGRP levels to baseline coincident with pain relief (Ref. Reference Goadsby, Lipton and Ferrari41, Reference Juhasz54). The CGRP receptor antagonists olcegepant and telcagepant are clearly effective antimigraine drugs (Refs Reference Olesen55, Reference Connor56, Reference Ho57). Unfortunately, in spite of its promising efficacy in several Phase III trials for acute migraine treatment, clinical development of telcagepant has recently been discontinued, presumably because of signs of liver toxicity from a prophylaxis clinical trial (Refs 58, 59).
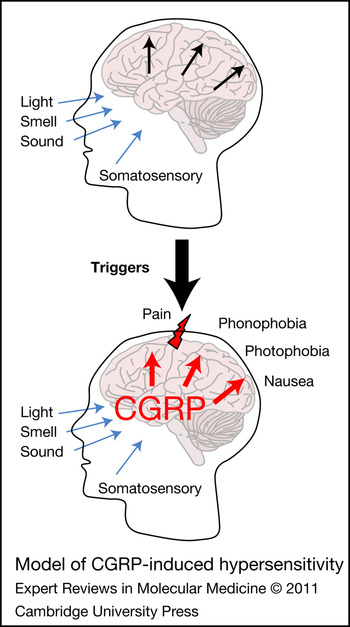
As a neuromodulator, CGRP could potentially increase synaptic transmission (for reviews, see Refs Reference Ho, Edvinsson and Goadsby60, Reference Seybold, Canning and Spina61). In the spinal cord dorsal horn, CGRP receptors colocalise with AMPA-type glutamate receptors on postsynaptic neurons. Pretreatment with CGRP increased the firing frequency of these neurons in response to AMPA, an effect that can be blocked by the peptide antagonist CGRP 8-37 (Refs Reference Ebersberger62, Reference Gu and Yu63). Consequently, when CGRP levels are elevated in a susceptible individual, we hypothesise that there could be an amplification of otherwise ordinary sensory input to beyond a pain threshold (Fig. 2).
Model of calcitonin gene-related peptide (CGRP)-induced hypersensitivity. Under normal conditions (top), CGRP levels are relatively low, leading to normal neurotransmission and proper filtering of sensory input. Migraine triggers initiate a transition to increased CGRP levels (bottom). The elevated CGRP levels increase synaptic transmission in the hypersensitive migraine brain. As a result, increased perception of sensory inputs is registered in the cortex as painful stimuli. Adapted from Ref. 60.

Although it is evident that CGRP has a role in nociceptive transmission, migraine is clearly a multifactorial disorder with a host of genes contributing to migraine susceptibility. For example, not all patients respond to CGRP receptor antagonists. This suggests the involvement of other contributing factors. Of course, this does not rule out CGRP involvement in the nonresponder population, just as one cannot conclude from triptan nonresponders that 5-HT1 receptors are not involved in migraine. Likewise, genetic mapping studies have failed to associate migraine with variations in the CGRP gene (Ref. Reference Menon64). Similarly, a genome-wide association study has not implicated CGRP or CGRP receptor genes (Ref. Reference Anttila65). Furthermore, infusion of other chemicals (glyceryl trinitrate, histamine, pituitary adenylate cyclase-activating peptide) can trigger delayed migraine-like headache in migraineurs, in a manner similar to CGRP (Refs Reference Iversen, Olesen and Tfelt-Hansen66, Reference Christiansen67, Reference Lassen, Thomsen and Olesen68, Reference Schytz69). Accordingly, CGRP should be considered as one factor (among possibly many) that contributes to migraine.
Within the context of migraine, it is a reasonable speculation that CGRP acts at several steps in a cascade from the trigeminal nerve to the CNS. CGRP is released from trigeminal ganglion neurons both peripherally at the dura and centrally in the spinal trigeminal nucleus (Ref. Reference O'Connor and van der Kooy70). Within the CNS, both CGRP and CGRP receptors are present in many areas implicated in the pathogenesis of migraine. In this review, we will discuss evidence that CGRP could contribute to migraine by both peripheral and central mechanisms.
Peripheral actions of CGRP: neurogenic inflammation
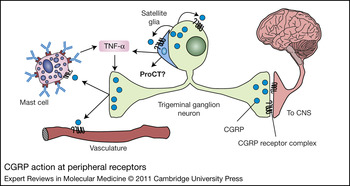
Perivascular release of CGRP from the trigeminal nerve induces vasodilation and dural mast cell degranulation, which both contribute to neurogenic inflammation. Neurogenic inflammation describes a sterile, inflammatory event that occurs as a result of sensory nerve activation and is characterised by vasodilation, plasma protein extravasation, and release of proinflammatory and inflammatory molecules from resident mast cells (Ref. Reference Markowitz, Saito and Moskowitz71). Vasodilation is due to CGRP action on vascular smooth muscle (Ref. Reference McCulloch72). Extravasation is caused by substance P, which is often co-released with CGRP. The inflammatory cascade can be triggered by CGRP actions on dura-resident mast cells and satellite glial cells of the trigeminal ganglion. CGRP actions at these peripheral sites are highlighted in Figure 3.
CGRP action at peripheral receptors. CGRP triggers an inflammatory cascade at the periphery. Inflammatory mediators released from mast cells sensitise sensory neurons and promote vascular permeability. Satellite glia influence the local microenvironment within the ganglia by releasing proinflammatory mediators such as tumour necrosis factor α (TNF-α), which can act on trigeminal neurons to increase CGRP synthesis and secretion, setting up a positive-feedback loop, which along with direct actions mediated by CGRP on a subset of trigeminal neurons might contribute to the extended duration of migraine. Satellite glia might also release proCT, which could also activate CGRP receptors.

Despite the fact that peripheral contributions to migraine have fallen from favour in recent years (for a review see Ref. Reference Ho, Edvinsson and Goadsby60), the story is far from complete. Indeed, the role of cerebrovascular dilation remains controversial (Refs Reference Asghar48, Reference Olesen73, Reference Chan74). The overall role of neurogenic inflammation has been discounted in large part owing to the failure of substance P receptor antagonists in migraine clinical trials (Refs Reference Ho, Edvinsson and Goadsby60, Reference Diener75). Furthermore, animal studies strongly supported a central, not peripheral, action of CGRP (Ref. Reference Levy, Burstein and Strassman26) and CGRP receptor antagonists (Ref. Reference Sixt, Messlinger and Fischer76). Although open to interpretation, these results could be confounded by mast cell degranulation during the experimental procedure. In addition, the studies do not rule out peripheral contributions. Finally, the relatively high level of CGRP receptor antagonists required for clinical efficacy compared with in vitro predictions has been used as an argument for a central site of action beyond the blood–brain barrier (Ref. Reference Edvinsson77). However, this comparison has recently been called into question (Ref. Reference Tfelt-Hansen and Olesen78) and the fact that peripheral administration of CGRP described above is able to induce migraine-like headaches has helped keep the debate open. In this context, a judicious re-evaluation of peripheral CGRP actions in neurogenic inflammation at mast cells and glia is warranted.
Mast cell degranulation
Mast cells are bone-marrow-derived cells (Refs Reference Lambracht-Hall, Dimitriadou and Theoharides79, Reference Wedemeyer, Tsai and Galli80) that are involved in normal immune responses and allergic reactions (Ref. Reference Hakim-Rad, Metz and Maurer81). Mast cells can be activated by direct injury (chemical or physical), crosslinking with immunoglobulin E, or activated complement proteins (Ref. Reference Prussin and Metcalfe82). Several diseases that involve mast cells are associated with increased incidence of migraines, including allergies, asthma, eczema, interstitial cystitis and irritable bowel syndrome (Refs Reference Low and Merikangas83, Reference Koziol84, Reference Warnock and Clayton85).
The involvement of mast cells in migraine has been speculated on for many years (Ref. Reference Theoharides86), and there are several lines of evidence that support their involvement. Sinus headache, which is not an officially recognised condition, co-occurs with sinusitis symptoms. Indeed, 90% of these headaches meet the diagnostic guidelines for migraine but are misdiagnosed (Ref. Reference Tepper87). Sinusitis is commonly a result of an allergic response, which is mediated by mast cells (Ref. Reference Theoharides and Kalogeromitros88). The population of mast cells most likely to contribute to the pathogenesis of migraine are dura-resident mast cells. A distinguishing feature of these cells is the ability of CGRP to degranulate them, which differs from other mast cells that require substance P (Refs Reference Messlinger9, Reference Ottosson and Edvinsson16). CGRP receptors are clearly present on mast cells in the dura mater (Ref. Reference Lennerz21). These mast cells lie adjacent to both sensory neurons and the vasculature (Ref. Reference Rozniecki89). Mast cell activation and degranulation lead to the release of several neuroactive and vasoactive substances. These include bradykinin, histamine, prostaglandins, tumour necrosis factor α (TNF-α), vascular endothelial growth factor and serotonin (Ref. Reference Theoharides17). The release of these inflammatory and proinflammatory agents can potentially generate a positive-feedback loop onto sensory neurons because they trigger CGRP release. An inflammatory soup (low pH, bradykinin, 5-HT, prostaglandin E2, histamine) (Ref. Reference Burstein, Collins and Jakubowski90) induces CGRP secretion from cultured trigeminal sensory neurons (Ref. Reference Durham and Russo91). This elevated secretion is predicted to be long lasting because cytokines also activate CGRP gene transcription (Ref. Reference Bowen92). Importantly, an inflammatory response triggered by chemical induction of mast cell degranulation sensitises primary sensory neurons that innervate the dura of the meninges (Ref Reference Levy93). Mechanosensitive neurons innervating the dura show increased activity shortly after degranulation and remain hyperactive for hours. It is believed that these excitable neurons have a key role in promoting intracranial migraine pain (Refs Reference Pietrobon and Striessnig1, Reference Strassman and Levy94, Reference Waeber and Moskowitz95). Increased activation of these primary afferent neurons also resulted in increased activity of neurons in the TNc, as measured by c-Fos immunoreactivity (Ref. Reference Levy93). Further evidence for mast cell actions being mediated by peripheral nociceptors is that sumatriptan, an antimigraine medication that inhibits CGRP release from these nociceptors, can block the effect of mast cell degranulation on the TNc (Ref. Reference Levy93).
At least one agent, histamine, released from mast cells has been directly implicated in migraine. Plasma histamine levels have been reported to be elevated in migraineurs, with a further increase during a migraine attack (Refs Reference Launay96, Reference Heatley97, Reference Sjaastad and Sjaastad98). Inhalation or injection of histamine causes migraine-like headaches in migraineurs, but only mild headaches in nonmigraineurs (Refs Reference Krabbe and Olesen99, Reference Lassen100). In a revealing experiment, Messlinger and colleagues identified a subpopulation of meningeal afferent fibres that were activated by low doses of histamine that were comparable with those predicted to occur on mast cell degranulation (Ref. Reference Schwenger101). However, although an H1 antagonist was able to block histamine-induced migraine, it was unable to block nitric-oxide-induced migraine (Ref. Reference Lassen102). Antihistamines are effective in a subset of migraine patients (Refs Reference Rossi, Fiermonte and Pierelli103, Reference Lewis104, Reference Togha, Ashrafian and Tajik105). Consequently, although the story is incomplete, cumulative contributions from histamine and other agents released on mast cell degranulation might contribute to the migraine state.
Rather than focusing on single agents, stabilising mast cells and blocking the effects of their proinflammatory contents might be beneficial. For example, nonsteroidal anti-inflammatory drugs are one of the most commonly used treatments for migraine (Refs Reference Diener106, Reference Silberstein and Goadsby107). In a clinical experiment using migraineurs with known food triggers, a mast-cell-stabilising drug was effective in preventing migraine symptoms after exposure to trigger foods (Ref. Reference Monro, Carini and Brostoff108). Montelukast is a leukotriene receptor antagonist with demonstrated efficacy in two small, open label trials for migraine prophylaxis (Refs Reference Sheftell109, Reference de Souza and Carvalho110). This drug was not successful in a larger, double-blind study (Ref. Reference Brandes111); however, it could be that only a subset of migraines involves an allergic process. Recent evidence shows that amitriptyline and prochlorperazine, which are successful for migraine prophylaxis, inhibit proinflammatory mediator release from mast cells in vitro (Ref. Reference Clemons112).
Satellite glial activation
In the trigeminal ganglion, satellite glia are intimately associated with neuronal cell bodies and are able to influence the local microenvironment similarly to glial functions in the CNS (Refs Reference Pannese113, Reference Hansson and Ronnback114). Recently, satellite glia have unexpectedly been shown to behave much like mast cells in response to CGRP. Neuronal cell bodies contain the necessary machinery for releasing neuropeptides, so a mechanism for release of CGRP within the ganglion exists. Trigeminal ganglion preparations have also been shown to release CGRP in response to a combination of nitric oxide donors and inflammatory stimuli (Ref. Reference Eberhardt115). CGRP treatment of satellite glia increases proinflammatory cytokine release and actions that can sensitise sensory neurons (Refs Reference Vause and Durham116, Reference Thalakoti117, Reference Capuano118, Reference De Corato119). This is a direct response because satellite glia contain functional CGRP receptors (Refs Reference Eftekhari8, Reference Lennerz21). In addition to cytokine release, CGRP triggers additional inflammatory gene expression changes in glia in vitro (Ref. Reference Vause and Durham116). These observations are consistent with evidence for neuron–glia interactions in inflammatory and pain conditions (Refs Reference Watkins, Milligan and Maier120, Reference Cao and Zhang121). As with the actions of CGRP on mast cells, it has been proposed that CGRP could have a role in activation or sensitisation of the sensory neurons by satellite glia (Refs Reference Thalakoti117, Reference Capuano118). The further synthesis and release of CGRP from the neurons would then generate a positive-feedback loop that would enhance and sustain the inflammatory state and neuronal sensitisation (Fig. 3). Indeed, we observed elevated CGRP levels in the cerebrospinal fluid of transgenic mice sensitised to CGRP actions in the nervous system (Ref. Reference Recober122). A similar elevation of CGRP mRNA levels was observed in some brain regions (Ref. Reference Russo123). These observations are consistent with a CGRP-mediated positive-feedback loop in cell cultures that stimulates further CGRP synthesis (Ref. Reference Zhang33).
Glial production of procalcitonin
The positive-feedback loop might include not only CGRP, but also an alternative splice product from CALCA, the gene from which CGRP is transcribed (Fig. 3). CALCA also encodes the hormone calcitonin (CT) (Ref. Reference Amara124). CT expression is normally restricted to parafollicular C-cells of the thyroid and regulates blood Ca2+ levels primarily by acting at its receptor on osteoclasts. CT is a cleavage product from a larger precursor peptide known as proCT (Ref. Reference Moya, Nieto and JL125). Normally, neither CGRP nor CT is expressed in satellite glia because of repressive epigenetic marks (Ref. Reference Park126). However, whole organ culture of the trigeminal ganglion results in ectopic CGRP expression in satellite glia, presumably as a result of inflammatory signals (Refs Reference Kristiansen and Edvinsson127, Reference Tajti128). Organ culture also increases immunoreactive proCT in satellite glia. ProCT levels are increased in many inflammatory conditions, as discussed below.
Circulating levels of proCT are generally quite low in healthy individuals. Serum proCT levels have been reported to increase several thousand times during sepsis, a severe inflammatory response that generally occurs in response to bacterial infection. Elevation of proCT in autoimmune diseases that have an inflammatory component, such as lupus and rheumatoid arthritis, has also been reported (Ref. Reference Buhaescu, Yood and Izzedine129). Although the exact mechanism of action of proCT under these conditions is not well understood, proCT might serve as a valuable biomarker for inflammation. Under some conditions, proCT might have a wider role. In animal models of sepsis, exogenous administration of proCT reduced survival whereas blocking endogenous proCT using a neutralising antibody increased survival (Ref. Reference Martinez130).
A recent study reported increased serum proCT in migraineurs during attacks when compared with baseline levels (Ref. Reference Turan131). Although the levels during migraine are much lower than those seen in sepsis, the idea that proCT and inflammation are linked under other conditions suggests that the meningeal sterile inflammation believed to occur in migraine could lead to local release of proCT. As mentioned previously, whole-organ tissue culture, which is associated with inflammation, allows proCT expression in satellite glia (Ref. Reference Tajti128). Expression of proCT will probably require epigenetic changes because promoter methylation normally represses the CALCA gene and DNA demethylation is sufficient to allow proCT expression in cultured trigeminal ganglia glia (Ref. Reference Park126). Increased proCT might have a functional consequence in migraine because it has been shown to act as a partial agonist at CGRP receptors (Ref. Reference Sexton132). Further study of the significance of proCT in migraine is merited.
Cortical spreading depression as a trigger of peripheral CGRP release
Cortical spreading depression (CSD) occurs when a focal stimulation of the cerebral cortex results in a slowly propagating wave (2–6 mm/min) of neuron and glial hyperactivity followed by a prolonged suppression in neuronal activity. Previous work has associated changes in cerebral blood flow with aura, a transient, mostly visual disturbance that precedes the headache in a subset of migraine patients (Refs Reference Olesen, Larsen and Lauritzen133, Reference Lauritzen134, Reference Hadjikhani135). Although other evidence argues against the connection between CSD and migraine (Refs Reference Ayata136, Reference Wolthausen137, Reference Hauge138), it seems reasonable that CSD might be at least one type of migraine trigger.
CSD appears to involve CGRP actions at two points. First, there is evidence that CGRP has a role in the initial hyperaemia during CSD because CGRP receptor antagonism blocks transient pial artery dilation in animal models of CSD (Refs Reference Colonna139, Reference Wahl140). This suggests that there must be local release of CGRP in the meninges, which could then serve to sensitise local sensory neurons. CGRP release in the meninges would then lead to mast cell degranulation and release of inflammatory mediators (Ref. Reference Ottosson and Edvinsson16). A recent report has shown that CGRP also has modest proinflammatory actions on cultured cortical astrocytes, analogous to actions on satellite glia (Ref. Reference De Corato119). Although experimental CSD in cats does not increase CGRP outflow in jugular blood (Ref. Reference Piper141), this does not rule out local increases in CGRP in the cortex.
Studies by Moskowitz and colleagues demonstrated that experimental CSD could activate trigeminal afferents in cortical meninges (Ref. Reference Bolay142). This activation is predicted to be mediated by excitatory agents released from neurons and glia. In a detailed study of meningeal nociceptor activity after experimentally induced CSD in rats, Burstein and colleagues recently demonstrated remarkably long-lasting activation of these neurons (Refs Reference Zhang143, Reference Zhang144). Interestingly, there was a marked delay before the activation. Identification of the reason for this delay should be informative. Other animal models have demonstrated CSD-dependent increases in c-Fos expression in the TNc (Refs Reference Moskowitz145, Reference Kunkler and Kraig146) and meningeal plasma extravasation (Refs Reference Bolay142, Reference Buzzi, Bonamini and Moskowitz147). Additional recent data show that experimental CSD in rats leads to delayed activation of peripheral meningeal nociceptors and second-order neurons of the trigeminovascular system (Refs Reference Zhang143, Reference Zhang144). These results are consistent with observations following systemic mast cell degranulation (Ref. Reference Levy93) and dural application of inflammatory soup or TNF-α (Refs Reference Jakubowski148, Reference Zhang149). An independent corticotrigeminal pathway has recently been shown to modulate activity initiated by the meningeal nociceptors in spinal trigeminal nucleus neurons (Ref. Reference Noseda150). In this regard, a recent study by Porreca's group has shown that dural inflammation can trigger CGRP-dependent allodynia that is modulated by descending facilitation from the rostral ventromedial medulla (Ref. Reference Edelmayer151). Whether there is a convergent regulation by these multiple pathways remains to be determined. In addition, if the reported induction of aura by peripheral injection of CGRP is confirmed (Ref. Reference Hansen46), this raises the possibility that CGRP may also have a role upstream of CSD.
Possible central actions of CGRP: modulation of light sensitivity
CGRP and its receptor are widely distributed across the CNS (Refs Reference van Rossum, Hanisch and Quirion4, Reference Dobolyi152, Reference Skofitsch and Jacobowitz153, Reference Yashpal154). As such, CGRP has been suggested in a number of centrally mediated activities that might be relevant to migraine, including anxiogenesis, stress responses, nociception and light aversion (Refs Reference Wimalawansa3, Reference van Rossum, Hanisch and Quirion4, Reference Russo, Dickerson and Lajtha5, Reference Recober and Russo6). We will focus on light aversion because recent studies have laid out an anatomical pathway for photophobia that is well positioned to be modulated by CGRP (Ref. Reference Noseda155).
Before discussing potential contributions from CGRP to photophobia, it is necessary to first define different forms of photophobia. Recently, three types of photophobia have been defined: ocular discomfort caused by exposure to light, exacerbation of headache by light and heightened perception of light (Ref. Reference Noseda and Burstein156). The first involves the trigeminal nerve. Light-induced ocular pain has been studied by exposing rats to very bright light, which resulted in activation of secondary neurons in the spinal trigeminal nucleus, presumably in response to vasodilation in the eye (Ref. Reference Okamoto157). A connection to migraine is intriguing, but remains to be established. Most pertinent to this review is the exacerbation of headache by light that is experienced by up to 80% of migraineurs (Refs Reference Selby and Lance158, Reference Drummond159).
Convergence of trigeminal and retinal signals in the thalamus
Photophobia in migraineurs who lack image-forming vision but retain the ability to detect light suggests that a nonvisual pathway is involved in the potentiation of migraine pain by light (Ref. Reference Noseda155). This observation implicates the intrinsically photosensitive retinal ganglion cells (ipRGCs), which contain the photopigment melanopsin and are involved in nonvisual responses to light, such as circadian entrainment (Ref. Reference Freedman160). These cells are intact in legally blind individuals that maintain the ability to detect light in the absence of functional rods and cones. Some ipRGCs terminate in posterior thalamic nuclei (Po) that also respond to dura stimulation (Ref. Reference Noseda155). These dura-sensitive neurons in the Po are modulated by light-driven activation of ipRGCs. This convergence of light and dural signals suggests an integrative role for the posterior thalamus in light-induced migraine pain. It is also consistent with neuroimaging studies in patients that have shown thalamic activation during migraine (Ref. Reference Afridi161). An intriguing observation was the variability in the stimulus-response time for light-induced activation in the Po. Whereas some units responded rapidly (within several milliseconds) to light stimulation, a significant delay lasting several hundred seconds was detected in other units (Ref. Reference Noseda155). This delay suggests that the thalamic pathway is part of a modulated network. We speculate that CGRP might be involved in this modulation.
Both CGRP and its receptor have been identified in the nociceptive pathway from the trigeminal nerve to the thalamus (Ref. Reference Wimalawansa3). As described previously, CGRP is in about 35–50% of the first-order trigeminal ganglia neurons, and the receptor is in a subset of these CGRP-containing neurons. In culture, most if not all trigeminal ganglia neurons express both CGRP and receptor proteins, suggesting that there is dynamic plasticity in their regulation, possibly because of upregulation on nerve injury (Ref. Reference Zhang33). CGRP receptors, but not CGRP, have also been identified in the satellite glia of the ganglia and possibly nonmyelinating Schwann cells (Ref. Reference Eftekhari8). Second-order nociceptive neurons in the TNc contain CGRP receptors (Ref. Reference Liu162). These neurons do not synthesise CGRP. Trigeminovascular input is then relayed to third-order neurons in the posterior thalamus (Ref. Reference Burstein163). The predominant CGRP-immunoreactive cell bodies in the thalamus are found in the subparafascicular nucleus, posterior thalamic nuclear group, peripeduncular nucleus and areas ventromedial to the posterior thalamic group (Ref. Reference Kresse, Jacobowitz and Skofitsch164). Although most light-sensitive neurons in the dura were found near the dorsal edge of the posterior thalamic nuclear group (Ref. Reference Noseda155), others were scattered in nearby posterior nuclei, including the ventroposteromedial thalamic nucleus that contains CGRP receptors.
CGRP actions in the ventroposteromedial thalamus have recently been brought to the forefront by identification of CGRP receptors on neurons responsive to nociceptive trigeminovascular input (Ref. Reference Summ165). CGRP receptor antagonists can block this nociceptive stimulation (Ref. Reference Summ165). Also within the thalamus, the presence of CGRP in neurons of the subparafascicular thalamus and other posterior intralaminar thalamic nuclei is especially intriguing. These CGRP-containing neurons, as well as neurons at the caudal extent of the thalamic posterior group (Ref. Reference Gauriau and Bernard166), relay and integrate somatosensory and nociceptive stimuli from ascending pathways (Ref. Reference de Lacalle and Saper167). CGRP fibres from this region that project to the amygdala have been suggested to have a role in autonomic and behavioural responses to acoustic and somatosensory stimuli (Ref. Reference Yasui, Saper and Cechetto168). Other studies have shown that neurons in these regions can activate the hypothalamic–pituitary–adrenal axis in response to auditory stress (Ref. Reference Campeau and Watson169). Further studies suggest that convergence of auditory and nociception inputs to the CGRP-positive lateral parvocellular subparafascicular thalamic nucleus is important for conditioned auditory and visual fear responses (Refs Reference Coolen170, Reference Coolen171). These anatomical data show that CGRP and its receptor are in the appropriate neighbourhood to modulate trigeminovascular and photic activation of thalamic neurons.
Potential nonthalamic contributions
While we have focused on CGRP actions in the thalamus, a more comprehensive and cautious analysis must include the possibility that CGRP could also modulate photophobia by actions in other brain regions. CGRP-immunoreactive cell bodies and fibres are prevalent in nuclei of the hypothalamus, ventral tegmental area, selected brainstem nuclei (Ref. Reference Kresse, Jacobowitz and Skofitsch164), periaqueductal grey (PAG) (Ref. Reference Ma172) and cerebellum (Refs Reference Dobolyi152, Reference Edvinsson173). Likewise, CGRP-binding sites have been mapped to many regions of the CNS, including the cortex, limbic system (amygdala, nucleus accumbens, hypothalamus) and brainstem (PAG, medulla, pons) (Refs Reference van Rossum, Hanisch and Quirion4, Reference Skofitsch and Jacobowitz153, Reference Yashpal154). Some of these regions also receive projections from the ipRGC. The function of most of the major ipRGC projections, such as the suprachiasmatic nucleus in circadian rhythms, has been well established. However, there are other relatively low abundance projections that have been less studied (Ref. Reference Hattar174). These include ipRGC fibres to the medial nucleus of the amygdala, bed nucleus stria terminalis (BSTN) and PAG, which are regions that contain CGRP and its receptor.
The ipRGC inputs to the extended amygdala (medial nucleus and BSTN) are of particular interest (Ref. Reference Hattar174). The amygdala is known to relay nociceptive information (Ref. Reference Calvino and Grilo175), and the medial amygdala is a convergence and integration site of photic and olfactory stimuli that modulate reproductive behaviour (Refs Reference Cooper176, Reference Elliott, Weiss and Nunez177, Reference Morin and Blanchard178). There are CGRP receptors in the centromedial nuclear area of the amygdala and extended regions, such as the BSTN. Injection of CGRP into the central nucleus and BSTN causes fear behaviour in rats (Ref. Reference Sink179), which demonstrates that CGRP can have an anxiogenic role in the extended amygdala. The CGRP in the amygdala is primarily from fibres projecting from the thalamus (Ref. Reference D'Hanis, Linke and Yilmazer-Hanke180). There is dense CGRP innervation from the posterior thalamus and parabrachial nuclei to the central and, to a lesser extent, the medial nucleus of the amygdala (Ref. Reference D'Hanis, Linke and Yilmazer-Hanke180). Specifically, CGRP-labelled neurons were traced from the subparafascicular, lateral subparafascicular and posterior intralaminar nuclei of the thalamus to the amygdala (Ref. Reference Yasui, Saper and Cechetto168). Of particular note, the subparafascicular and lateral subparafascicular nuclei primarily projected to the medial amygdala and the amygdalostriatal transition area, which are areas found to contain ipRGC projections. Interestingly, the authors concluded that these CGRP-containing fibres mediate conditioned autonomic and behavioural responses to acoustic stimuli or somatosensory stimuli (Ref. Reference Yasui, Saper and Cechetto168). Whether these fibres project from any of the dural-activated thalamic neurons identified by Burstein and colleagues remains to be tested.
Similarly, the presence of CGRP-containing fibres and receptors in the PAG, which contains ipRGC fibres, should also be considered as potential sites of CGRP action in photophobia behaviour. CGRP-immunoreactive cell bodies are found in the PAG (Ref. Reference Ma172), which is part of the descending pain inhibitory system (Ref. Reference Gebhart181) and cooperates with the amygdala in processing fear and anxiety (Ref. Reference Behbehani182).
Light-aversive behaviour of a CGRP-sensitised mouse model
Support for a role for central actions of CGRP in photophobia has been provided by light-aversion studies in genetically engineered mice. Although relatively unexplored, light aversion has been a useful parameter for objective light sensitivity in animal models. Differential light sensitivity between different strains of inbred mice has been shown, indicating a possible inherent sensitivity to light (Ref. Reference Thiels, Hoffman and Gorin183). Light aversion was correlated to photophobia in nestin/hRAMP1 transgenic mice, a model of CGRP sensitivity (Ref. Reference Recober184). The nestin/hRAMP1 mice are genetically sensitised to CGRP by nervous system overexpression of human RAMP1, a component of the CGRP receptor (described above) (Ref. Reference Zhang33). Compared with control littermates, nestin/hRAMP1 mice spend less time in the light after intracerebroventricular injection of CGRP, suggesting that light causes discomfort in these animals under these conditions (Refs Reference Recober122, Reference Recober185). However, the central administration results do not conclusively rule out a peripheral effect and the results must be interpreted with caution because it is very likely that some injected CGRP could leak at the site of injection through the meninges. Nonetheless, the ability to genetically restrict hRAMP1 expression to discrete neuronal regions in this mouse model provides a valuable tool for identifying sites of CGRP action (Ref. Reference Russo186). Whether CGRP actions in the thalamus amygdala, or other sites contribute to photophobia will be an interesting area of future study.
Research in progress
Basic and clinical researchers continue to offer complementary approaches that are improving our understanding of the role of CGRP in the complex pathogenesis of migraine. Even though the story is far from complete, we propose that activation of a peripheral inflammatory response by CGRP acting in concert with central modulation by CGRP contributes to migraine pain.
Several new CGRP-based therapies are currently under development for the treatment of migraine. New small-molecule CGRP receptor antagonists have completed Phase II clinical trials, both with positive results (Refs Reference Diener187, Reference Hewitt188). Monoclonal antibodies intended to prevent CGRP from engaging its receptor are being pursued as a path towards long-term prophylactic therapy (Refs Reference Shi189, Reference Zeller190). In preclinical studies, these antibodies were able to inhibit neurogenic inflammation without affecting cardiovascular parameters (Ref. Reference Zeller190). If effective in migraine therapy, systemic delivery of antibodies will highlight the importance of peripheral CGRP actions. Additional antimigraine therapies are also being developed targeting glutamate receptors, which as mentioned above could potentially be modulated by CGRP (Refs Reference Sang191, 192).
Future research will probably explore other molecules that might contribute to the pathogenesis of migraine, such as histamine and proCT. It seems likely that experiments will continue to examine the relationship between the nervous and immune systems, especially the interplay of CGRP with the immune system. The identification of sites of CGRP action in the CNS should lead to more insights and improved therapeutics for migraine. In this way, increased understanding of the impact of CGRP on the trigeminovascular system will continue to propel us closer to successful therapeutics for migraine.
Acknowledgements
We gratefully acknowledge Rami Burstein for very helpful guidance and suggestions, and our peer reviewers for insightful advice on the article. This work was supported by the National Institutes of Health (DE016511 and NS075599) and a Ruth L. Kirschstein NRSA fellowship (NS074728) (to A.C.R.).