Introduction
Bony defects of the anterior wall of the frontal sinus may occur due to frontal mucoceles, pyocoeles, malformations and tumours, and following trauma and infection. Many different techniques exist for closing such defects. Autologous tissue graft reconstruction using split calvaria is very much favoured in the literature, but fixation with osteosynthetic material is usually required.Reference Grundmann and Kehrl1–Reference Edwards and Ousterhout3 Sometimes, a bony transplant is resorbed over time, depending on its origin.Reference Baumeister, Peek, Friedman, Levin and Marcus4
Other, alloplastic graft materials can also be used, together with various types of cement. The use of such materials avoids the risk of donor site morbidity; however, such allografts may be susceptible to rejection and infection.Reference Sahoo, Roy, Desai and Gupta5
In the cases presented below, we were faced with the problem of preceding infection, and therefore needed to avoid using foreign material implants or osteosynthesis. In addition, it was essential to seal the nasal cavity with vascularised autografts, in order to avoid potential ascending bacterial contamination of the frontal implant.
As is known from cranioplasty, rib reconstruction constitutes an alternative approach for treating larger defects of the skull.Reference Beekmans, Don Griot and Mulder6, Reference Munro and Guyuron7 In this article, we describe the surgical procedure for rib reconstruction in the frontal sinus region; we also discuss the available literature on this topic.
Patients and methods
Patient one
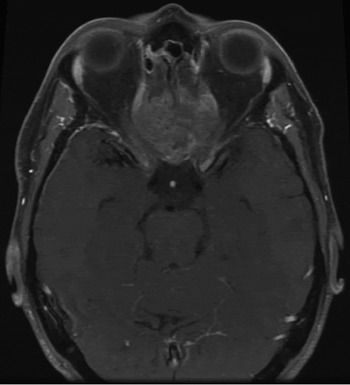
In 2007, a 47-year-old, Caucasian man was diagnosed with sinonasal undifferentiated carcinoma, by endonasal biopsy. The initial tumour-node-metastasis (TNM) stage was cT4 cN0 cM0, according to the Union for International Cancer Control (UICC) classification (Figure 1). The tumour was placing pressure on both optic nerves, causing the patient's vision to deteriorate.
Axial, T1-weighted, gadolinium-enhanced magnetic resonance imaging scan of patient one prior to surgery, showing a sinonasal undifferentiated carcinoma at the level of the optic nerves.

Therefore, we performed emergency tumour debulking via transnasal transcribriform resection, with optic nerve decompression. This was followed by transfrontal subcranial resection of the adjacent dura. The defect was reconstructed with a pericranial flap, and the anterior wall of the frontal sinus was restored using a split calvarium graft fixed with titanium mini-plates.
The peritumoural area received adjuvant chemoradiation, comprising cisplatin (total dose 65 mg) and a total radiation dose of 60 Gy (intensity modulated radiotherapy).
The patient's vision returned to almost normal values (uncorrected vision of 70 and 100 per cent), and his initial double vision resolved.
One and a half years after initial diagnosis, the patient developed intermittent eyelid swelling on both sides, with subsequent formation of a right upper lid abscess.
Postradiogenic osteitis of the frontal bone was found to be the underlying pathology, involving infection with multiple bacteria (Pseudomonas aeruginosa, Staphylococcus aureus, coagulase-negative staphylococcal species and group B streptococci), which required treatment with long term intravenous antibiotics.
The foreign osteosynthetic material was removed, all necrotic bone was debrided, and the frontal sinus was obliterated with abdominal fat.
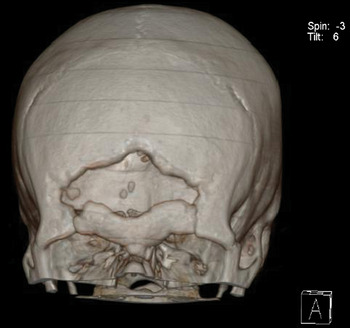
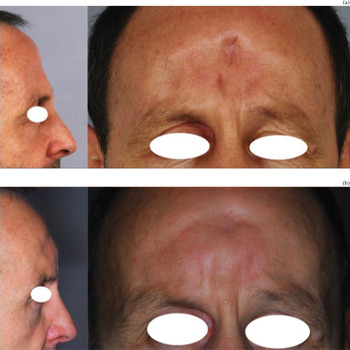
The infection resolved; however, a large hole was left in the anterior wall of the frontal sinus, together with a bony defect in the right orbit (Figures 2 and 3b). As a consequence, the patient's forehead had a large dent which was not cosmetically desirable (Figure 3b).
Three-dimensional computed tomography reconstruction of patient one, showing the pre-reconstruction defect in the frontal sinus. A = anterior

(a) Pre-reconstruction and (b) nine months post-reconstruction photographs of the first patient's forehead.

Patient two
A 43-year-old, Caucasian woman was treated by combined transnasal and transfrontal resection for a cT4 cN0 cM0, malignant solitary fibrous tumour of the frontal sinus and nasal cavity. The anterior wall of the frontal sinus was fixed by titanium mini-plating, a bony defect was restored with a Palacos (Heraeus Kulzer GmbH, Hanau, Germany) cement plasty, and the skull base was reconstructed using titanium mesh.
The operation was followed by intensity modulated radiotherapy with a cumulative dose of 64 Gy.
The patient subsequently developed greenish rhinorrhoea. This was discovered to be due to P aeruginosa infection, requiring antibiotic treatment with aminoglycosides and ceftazidim.
However, the infection advanced and frontal osteomyelitis developed. Repeated craniotomy was necessary. All foreign material was removed and the osteomyelitic bone debrided. The skull base was reconstructed using a pedicled periosteal flap, and the anterior frontal sinus wall was again restored using Palacos cement plasty.
Antibiotics were continued for one month post-operatively. However, this treatment was subsequently discontinued because of bilateral vestibular dysfunction, and substituted with piperacillin with tazobactam.
Unfortunately, the patient again developed infection, this time with a cutaneous fistula. The Palacos cement plasty was again removed and wide local debridement performed. A free radial forearm flap was used to cover the external defect.
This flap failed, and the procedure was repeated from the contralateral side.
Finally, the patient was treated with Rimactane® and ciprofloxacin, and the infection resolved.
Again, the patient was left with a large dent in her forehead due to the bony defect.
Materials and methods
The informed consent of both patients was obtained for publication of the contents of this article.
The same reconstructive surgical procedures were undertaken for both patients.
We used a two-team approach, working with our colleagues from the plastic and reconstructive surgery department.
The left side of the thorax was incised between the eight and ninth rib, and a thorough subperiosteal dissection performed. We then harvested either the bony parts of both ribs, in patient one, or only one rib, in patient two, without any injury to the pleura. The periosteum was incised only ventrally, and was closed after removal to promote rib regrowth. The skin was closed in two layers, and two suction drains inserted.
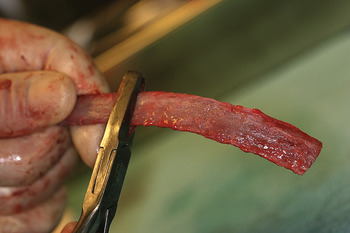
The approximately 15 cm long transplants were then split in half using a hand-driven chisel and thinned using flat-nosed pliers, in order to render them more flexible (Figure 4).
Intra-operative photograph showing flattening of the split-rib graft, using pliers, for patient one.

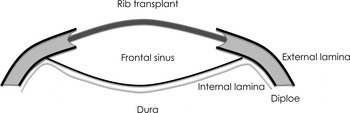
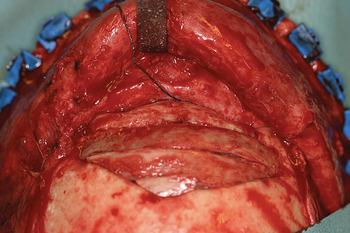
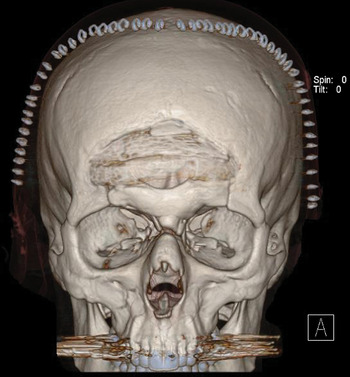
After coronal incision and preparation of the scalp down to the supraorbital rim, the supraorbital nerves were identified and spared. The edges of the bony defect were debrided, and a groove was drilled into the diploe, using a 2 mm drill, just between the external and internal tabulae (Figures 5 and 6). The rib transplants were tailored in length to fit the gap. The rib transplants were then placed into the laterally drilled groove, bent and under tension, to form the new contour of the forehead (Figures 7 and 8).
Diagram of the reconstructed site.

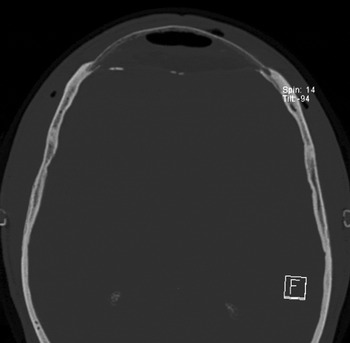
Early post-reconstruction, axial computed tomography scan of the reconstruction site in patient one. F = Foot

Intra-operative photograph showing reconstruction in patient one.

Early post-reconstruction, three-dimensional computed tomography reconstruction for patient one. A = anterior

In patient one, a small piece of calvarial bone was placed onto the orbital roof, in order to reconstruct a smaller defect in this area.
Finally, all edges were levelled using a sharp 5 mm drill, the scalp was put back in place, and the incision was closed using a bilayer technique, after placement of two non-suction drains.
We also conducted a literature review on split-rib reconstruction of the cranium. The PubMed database was searched using the following key words: ‘split rib’, ‘frontal sinus reconstruction’, ‘frontal sinus + rib’, ‘frontal sinus osteoplasty’, ‘bone grafting frontal sinus’, ‘frontal sinus osteomyelitis’, ‘sinus + rib grafts’, ‘cranial vault reconstruction’, ‘frontal cranioplasty’, ‘rib cranioplasty’ and ‘frontal rib grafts’. We assessed only material published between 1950 and 2010, concurrent with the modern antibiotic era. We considered articles if abstracts were available electronically, or if the article title indicated that its content may be relevant. Selection was limited to English language literature.
We included in the review only those publications describing the use of a split rib technique to close a cranial defect, preferably in the frontal sinus region.
All 18 publications selected were reviewed as full text articles, in order to record the total number of patients, defect site, reconstruction material used, aesthetic results, complications and graft osteointegration.
Results
Patients' post-operative course
In our two patients, post-operative X-rays of the thorax showed no signs of pneumothorax. The post-operative course was uneventful in both cases. Minimal pain in the left hemithorax was treated with non-steroidal anti-inflammatory drugs. Patient one was discharged from hospital after 10 days of prophylactic antibiotic treatment, as recommended by colleagues in the infectious diseases department. Patient two left hospital after six days and needed no further antibiotic treatment. Sutures and clips were removed on day 10.
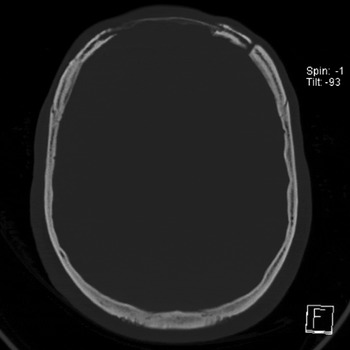
Follow up was performed on a monthly basis, using magnetic resonance imaging (MRI), computed tomography (CT) and positron emission tomography (PET) CT. The final follow-up CT scan of patient two, performed eight months after reconstruction, is shown in Figure 9, and clearly demonstrates signs of osteointegration of the rib graft.
Eight months post-reconstruction, axial computed tomography scan of patient two, showing signs of osteointegration. F = Foot

At the time of writing (40 and 36 months after initial diagnosis), there were no signs of tumour recurrence in either patient. Despite this, follow up was ongoing.
Literature review
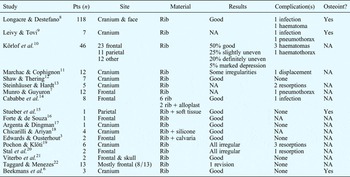
Almost 1000 articles were identified by our PubMed search, although overlapping results were encountered. Thirty-four publications were selected and retrieved as full text articles, of which only 18 met the inclusion criteria (see Table I).
Previous studies of split-rib cranial reconstruction*

* Identified by literature review. Pts = patients; osteoint = osteointegration; NA = not specified
Articles were excluded for the following reasons: non-human subjects (one paper), reconstruction in the wrong anatomical area (one paper), insufficient data (six papers), inappropriate initial selection (i.e. paper did not refer to split-rib reconstruction; six papers), and results overlapping with those of a previously identified study (two papers).
The accepted 18 publications described a total of 250 patients undergoing skull reconstruction. In 241 cases, split ribs were the only reconstructive material used (aside from fixation wires). In nine cases, other materials were used in combination with rib transplants (alloplastic graft material in six cases, soft tissue in one and calvarial bone in two). Fifty-nine cases involved frontal area reconstruction and 12 involved parietal area reconstruction; in 181 cases, the site of reconstruction was not clearly defined, but was stated to be in the skull area.
The overall results were reported to be very good. Six (2.5 per cent) cases of bony resorption were reported, and 10 (4 per cent) patients underwent revision surgery due to unsatisfactory results. One early displacement needed immediate revision, one haematoma required evacuation, and three local infections were controlled with systemic antibiotics. No transplant losses were encountered in patients with infections, and in only one case was local debridement needed to control infection.Reference Leivy and Tovi9 There were three cases of major complications, all of which involved haemato- or pneumothorax requiring drainage. In two studies, with a total of five patients, post-operative complications were not evaluated. Osteointegration was discussed and confirmed in only four studies, involving a total of 129 patients. Three studies (with a total of 24 patients) did not report aesthetic outcomes, and two studies (with a total of five patients) did not clearly assess complications.
Discussion
There is not much information in the otolaryngological literature on reconstructions of the anterior wall of the frontal sinus. In our literature search, only two of the finally reviewed articles were from otolaryngological journals, and these involved a total of only five patients. Most descriptions were in case reports or small series introducing new materials and techniques in this field. Because frontal sinus defects are often found in close proximity to other cranial defects, our neurosurgical colleagues and collaborating plastic and reconstructive surgeons seem to be more familiar with this problem, and have found several ways of coping with even larger defects of the cranium. However, reconstructions of bony defects in the frontal area are aesthetically more challenging than those located parietally or occipitally.
Current skull reconstruction techniques include the use of alloplastic and autologous materials.Reference Goiato, Anchieta, Pita and dos Santos23 However, certain situations require different approaches to achieve successful closure of cranial defects. Live bone seems to be more resistant to infection.Reference Hancock24 The advantages of autologous calvarial reconstruction, over the use of alloplastics, have been reported previously.Reference Sahoo, Roy, Desai and Gupta5 Baumeister and colleagues described an algorithm for the treatment of neurosurgical bone flap losses due to infection.Reference Baumeister, Peek, Friedman, Levin and Marcus4 After treatment of a potential soft tissue defect, they recommended alloplastic material as the first choice, followed by autologous grafts and allogenic bone. However, they emphasised the need to confirm that any previous infection is completely healed by the time of intervention, when alloplastic material is used. In complicated infectious situations, autologous bone is preferred.
Thus, expert opinion currently favours the use of split-calvarial bone grafts. However, in specific situations (e.g. when one needs to cover a large area in a repeatedly infected site), alternative approaches and techniques are often required. One such alternative, with proven good results, is split-rib cranioplasty.
Reconstruction of the skull in the area of the frontal sinus is prone to infection, due to ascending bacteria from the nasal cavity. We, and others, believe that closure of the frontal recess (including meticulous removal of sinus mucosa) is an important step in preventing such infection, as it isolates the frontal sinus from the nasal cavity.Reference Manson, Crawley and Hoopes25 In addition, perfused tissue (e.g. a pedicled pericranial flap) needs to be brought in to cover badly vascularised tissue, especially in irradiated areas.Reference Snyderman, Janecka, Sekhar, Sen and Eibling26
In cases of osteitis and osteomyelitis (anywhere in the body) in which antibiotic therapy has failed, thorough debridement of the affected bone is essential, and removal of any foreign material in proximity to the focus of infection is also required. Therefore, in cases of repeated infection, we avoid using alloplastic implants during subsequent reconstruction. (In unproblematic cases, we use split-calvarium grafting to cover frontal defects, but this reconstruction usually needs to be kept in place by mini-plate osteosynthesis or wires, especially if large areas are involved.)
In all the reviewed cases of split-rib reconstruction of the frontal sinus, there was not a single case of graft loss due to infection. With split-rib grafting, it is possible to close even large defects in the skull area, using a ‘living’ graft, where split-calvarium grafting could not provide sufficient material.Reference Weber, Kearns and Smith27 Split-rib grafts can be kept in place without any use of fixation, simply by drilling a rim into the diploe of the calvarium and placing the graft under slight tension to follow the natural curvature of the skull.Reference Marchac and Cophignon11 Thus, the use of split-rib grafting is favoured in previously infected regions, as foreign material is always more prone to bacterial colonisation. The tension on the transplant promotes healing by axial compression, as seen in other osteosynthetic procedures.Reference Bagby28 There is excellent integration of the split-rib grafts, as shown in an experimental study by Longacre and Destefano.Reference Longacre and Destefano29
Both our patients required regular radiological follow up, using MRI, CT and PET-CT imaging, to monitor outcomes following treatment of their malignant tumours. The use of bony grafts without osteosynthetic materials has the additional advantage of good radiolucency, producing no magnetic interference on MRI, as well as no artefacts on electroencephalography (in patients with seizures).Reference Shaw12
Another indisputable advantage of rib grafts is the ability of the rib to regrow, when the periosteum is closed over the site of the harvested rib. In their large series, Körlof et al. reported almost 100 per cent regrowth of the harvested rib.Reference Körlof, Nylén and Rietz10
One of the main disadvantages of the split-rib technique is donor site morbidity. Although post-operative pain is usually not severe, there is the potential risk of injury to the pleura and subsequent pneumo-haematothorax, requiring pleural drainage.Reference Tessier, Kawamoto, Matthews, Posnick, Raulo and Tulasne30 This complication has been reported in as many as 30 per cent of patients following rib removal.Reference Whitaker, Munro, Salyer, Jackson, Ortiz-Monasterio and Marchac31 However, other studies of facial and cranial reconstruction using rib grafts have reported an incidence of 1–2.4 per cent.Reference Tessier, Kawamoto, Matthews, Posnick, Raulo and Tulasne30, Reference James and Irvine32 In our study, we observed this complication in only three cases (approximately 1 per cent), of a total study group of 252 (i.e. our own two patients plus 250 literature review cases undergoing cranial reconstruction using split-rib grafting). Clinically, if a pleural tear is suspected intra-operatively, this can be tested by filling the surgical wound with water and applying positive pressure ventilation; any pleural tear should cause bubbles to rise. An X-ray of the thorax, taken during expiration, should confirm the findings.
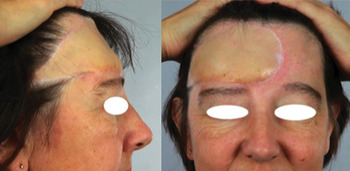
Another reported disadvantage of split-rib grafting is an inferior cosmetic result, in terms of an uneven surface. In our limited series, results were good for the large defects that needed to be covered (Figure 10). A minor degree of unevenness, such as seen in our first patient (Figure 3b) can be easily addressed by injection of autologous abdominal fat. Of the studies identified in our literature, the best aesthetic outcome was reported by Körlof et al.: 75 per cent of reconstructions achieved good or slightly uneven results, with only 5 per cent retaining an obvious depression of the reconstructed area.Reference Körlof, Nylén and Rietz10 Of those identified articles which reported their aesthetic outcomes, good results were reported for 182/214 reconstructions (85 per cent). However, in our opinion these descriptions were often not sufficiently detailed, so this rate may overestimate the incidence of a favourable cosmetic outcome.
• Multimodal treatment of sinonasal malignancies may result in osteomyelitis and cosmetic deformity
• In such cases, frontal sinus reconstruction can be a challenge
• In the two presented cases, split-rib reconstruction had good cosmetic results, adequate osteointegration and minimal donor site morbidity
• Split-rib reconstruction should be considered when avoidance of foreign materials is required
Clinical photographs of patient two, taken 15 months after reconstruction.

It was not the aim of this study to compare different reconstructive materials. The advantages and disadvantages of the various graft materials are discussed elsewhere, as are their indications in cranial reconstructive surgery.Reference Goiato, Anchieta, Pita and dos Santos23, Reference Gosain33–Reference Kuttenberger and Hardt36 The choice of reconstructive materials for the two patients presented is discussed above. In both patients, alloplastic materials were too prone to infection, and had already failed previously. For similar reasons, we chose not to use preformed or manufactured titanium implants for the final reconstruction.Reference Lethaus, Poort Ter Laak, Laeven, Beerens, Koper and Poukens37 Split calvarium had either already been used or would have failed to fill the large gap. Furthermore, split-calvarium grafting would have required wire or mini-plate fixation, leading to implantation of foreign material which could cause untreatable infection. (The same applies to iliac bone grafting, although other techniques have been described.)Reference Grocott38
The overall results of the split-rib method are good and morbidity is low; however, extensive experience in the frontal sinus region is lacking. Further research is needed into the outcomes of split-rib reconstruction in this region.
Conclusion
Split-rib osteoplasty of the frontal sinus is a valid method for closing even quite large defects. It has the advantage of not relying on foreign material or osteosynthesis, therefore minimising the risk of infection. Furthermore, it causes no distracting imaging artefacts, and functional and aesthetic morbidity at the graft donor site is minimal.
Acknowledgement
We thank Dr Walter Künzi, Department of Plastic and Reconstructive Surgery, for his support with manuscript preparation.