


Synthesis and structure of ultrananocrystalline diamond films
Diamond thin films are of great interest and are being investigated because of many current (e.g., diamond coated mechanical pump seals and bearings) and potential (e.g., microelectromechanical/nanoelectromechanical systems [MEMS/NEMS]) applications to enable a new generation of multifunctional devices.Reference Auciello and Sumant1 Several types of diamond thin films have been synthesized and systematically studied, exhibiting different microstructures, surface morphologies, and properties. Diamond films have been grown on the surfaces of insulators, semiconductors, and metals. Following surface pretreatment, or “seeding” (embedding micro- or nanodiamond particles on the substrate surface), diamond films are grown on the seeds mainly using microwave plasma-enhanced chemical vapor deposition (MPCVD) or hot filament chemical vapor deposition (HFCVD).Reference Auciello and Sumant1,Reference Butler and Sumant2 For the MPCVD method, a mixture of gases is inserted into an air evacuated chamber, and microwave power is coupled to the gas to produce a plasma involving ionized and neutral atoms and molecules containing C, H, and other components such as Ar. In the HFCVD process, an array of hot filaments heated up to 2200°C induces cracking of the CH4 molecules, producing radicals that induce the growth of diamond films.Reference Auciello and Sumant1,Reference Butler and Sumant2 The use of a hydrogen-rich chemistry (H2 [balance]/CH4 [0.1 to 4%])Reference Auciello and Sumant1,Reference Butler and Sumant2 results in microcrystalline diamond (MCD) (1–5 µm grains and columnar microstructure) (for ∼1% CH4) and nanocrystalline diamond (NCD) (10–100 nm grains) (for up to ∼4% CH4) films. MCD and NCD films grown on surfaces of insulators (oxides), semiconductors, and metals seeded with diamond micro-/nanoparticles without particle surface functionalization exhibit low initial nucleation densities (<1010/cm2) due to agglomeration of the particles on the substrate surface. MCD surfaces are rough (root mean square [rms] ∼10% of film thickness).Reference Auciello and Sumant1,Reference Butler and Sumant2 On the other hand, high diamond film nucleation densities are achieved (>1012/cm2) using a seeding process involving functionalized diamond particles to avoid agglomeration,Reference Rotter, Yoshikawa, Koga, Tzeng, Klages and Miyoshi3 which is also used to grow relatively smooth, high-quality NCD films at 600–800°C.Reference Auciello and Sumant1,Reference Butler and Sumant2
The H2/CH4 chemistry-based growth process is driven by CHx (x = 2–3) radicals interacting with the substrate surface. This involves the hydrogen abstraction process, ultimately resulting in carbon atoms bonding into positions corresponding to the diamond lattice. The atomic hydrogen in the plasma preferentially etches a graphitic phase that co-deposits with the diamond phase. However, atomic hydrogen also etches the diamond phase, although at a ∼50 times lower rate than for graphite, resulting in the formation of intergranular voids and columnar morphology with large grains (≥1 µm). The MCD films exhibit high residual compressive stress, poor intergranular adhesion, very rough surfaces, and high coefficient of friction (≥0.5).Reference Auciello and Sumant1,Reference Butler and Sumant2 Consequently, MCD films are not well suited for medical devices requiring very low coefficient of friction and low wear, such as orthopedic implants. The grain size can be reduced to 10–100 nm, characteristic of NCD films, by increasing the CH4/H2 ratio in the plasma. This results in relatively smooth NCD films,Reference Auciello and Sumant1,Reference Butler and Sumant2 but with increased non-diamond components at the grain boundaries.Reference Butler and Sumant2 NCD films grown with high sp Reference Rotter, Yoshikawa, Koga, Tzeng, Klages and Miyoshi3 content,Reference Butler and Sumant2 using a CH4 (0.3%)/H2 (99.7%) gas mixture, exhibit the NCD structure for thickness ≤ few hundred nm, but above that, grain coarsening dominates due to a lack of re-nucleation, and the film develops columns, increased grain size, and roughness.
In contrast to MCD and NCD film growth, ultrananocrystalline diamond (UNCD) films are produced by MPCVD using a novel (patentedReference Naguib, Birrell, Elam, Carlisle and Auciello4) argon-rich chemistry [Ar (99%)/CH4(1%)]1 with no hydrogen added.Reference Auciello and Sumant1,Reference Naguib, Birrell, Elam, Carlisle and Auciello4 This produces carbon dimers (C2) and CHx radicals in the plasma, from methane decomposition, via reactions (1) and (2) described below:
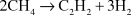 $$2{\rm{C}}{{\rm{H}}_{4}} \to {{\rm{C}}_{2}}{{\rm{H}}_{2}} + 3{{\rm{H}}_{2}}$$
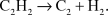 $${{\rm{C}}_{2}}{{\rm{H}}_{2}} \to {{\rm{C}}_{2}} + {{\rm{H}}_{2}}.$$
Initial work indicated that C2 dimers play a critical role in UNCD film nucleation and growth.Reference Auciello and Sumant1,Reference Sternberg, Zapol and Curtiss5 Calculations predicted that the C2 dimers have low activation energy (∼6 kcal/mol) for insertion into the substrate surface, thus establishing the nucleation characteristics of UNCD films. Recent modeling indicates that while the C2 population in the plasma is high, the population near the surface may be low, and other hydrocarbon radicals (e.g., CH3, C2H2) are also substantial or the main contributors to the UNCD film growth.Reference May, Allan, Ashfold, Richley and Mankelevich6 This model, however, could not fully explain the low temperature growth (≤400°C) of UNCD films. Clearly, more experimental and modeling studies are needed. Regardless of the mechanism, the distinctive characteristic of the UNCD film growth process is that the plasma contains very small quantities of hydrogen, arising mainly from thermal decomposition of methane to acetylene in the plasma.Reference Auciello and Sumant1
The uniqueness of UNCD films is that they exhibit a nanostructure with the smallest grain size obtainable today for diamond films (see Figure 1a). Important also is that insertion of nitrogen in the gas mixture (e.g., Ar [79 sccm]/CH4 [1 sccm]/N2 [20 sccm]) results in UNCD films, named N-UNCD, with ∼10 nm grain size and ∼2 nm wide grain boundaries (Figure 1b).Reference Xiao, Birrell, Gerbi, Auciello and Carlisle7 N-UNCD films are semi-metallic, with nitrogen incorporated into grain boundaries, thereby satisfying dangling C bonds and providing electrons for electrical conduction.
High-resolution transmission electron microscopy micrographs of (a) plain ultrananocrystalline diamond (UNCD) films (∼2–5 nm grain size and 0.5 nm grain boundary width) and (b) N-UNCD (with nitrogen atoms inserted in grain boundaries) films (∼10 nm grain size and ∼2 nm grain boundary width) produced by microwave plasma-enhanced chemical vapor deposition. Reprinted with permission from Reference 43. © 2001 American Institute of Physics. Note: GB, grain boundary.

A critical outcome of the UNCD nucleation and growth process is that these diamond films are produced at the lowest temperatures (350–400°C) possible today, as measured by thermocouples in contact with the substrate during growth and most importantly by the demonstrated growth of UNCD films to encapsulate complementary metal oxide semiconductor (CMOS) devices, which exhibit similar performance before and after growing UNCD films on them. The CMOS device would be destroyed if diamond films were grown on them at temperatures much higher than 400°C; thus, integrating UNCD coatings with CMOS devices is an alternative to the thermocouple method (described previously) in cross-checking the low-temperature growth of UNCD films.Reference Auciello and Sumant1 To the best of the authors’ knowledge, a similar demonstration of low-temperature NCD film integration with CMOS devices has not been published in the open literature yet. Low-temperature UNCD film growth on CMOS devices forms the basis for monolithically integrated UNCD-MEMS/NEMS/CMOS devicesReference Auciello and Sumant1,Reference Sumant, Auciello, Carpick, Srinivasan and Butler8 and for UNCD-coated CMOS microchips implantable inside the human body.Reference Auciello and Sumant1,Reference Xiao, Wang, Carlisle, Mech, Greenberg, Freda, Humayun, Weiland and Auciello9
Bias-enhanced nucleation and bias-enhanced growth (BEN/BEG) is the latest development in the synthesis of UNCD films. The process involves biasing the substrate with a negative voltage (∼ –150 to –300 V) to attract C+ and CHx+ ions from the plasma, sub-planting several Angstroms into the material (from the surface), and producing a carbide nucleation layer to grow UNCD films. BEN/BEG provides several advantages over conventional UNCD growth, namely, (1) comparable or better seeding efficiency, (2) stronger adhesion to substrates, and (3) an integrated fully dry nucleation/growth process only using plasmas. BEN/BEG processes, using H2/CH4 chemistry, produced NCD (30–100 nm grains) films exhibiting diamond cluster formation, relatively high surface roughness, high compressive stress, film delamination, and high non-diamond phase content.Reference Stoner, Ma, Wolter and Glass10 UNCD films were produced using BEN with H2/CH4 plasma chemistry for the BEN step, but growing the UNCD films without bias, did not yield optimum nanostructure and properties.Reference Lee, Lin, Chia, Cheng and Lin11 More recently, a low pressure BEN/BEG process was developed using Ar/CH4 chemistry, which yielded UNCD films with an identical nanostructure to that shown in Figure 1a: low stress (∼80–100 MPa), smooth surfaces (rms ∼4–6 nm), and higher growth rates (∼1 µm/hr)Reference Chen, Zhong, Konicek, Grierson, Tai, Lin, Kabius, Hiller, Sumant, Carpick and Auciello12 than for UNCD films grown without bias (∼0.2–0.3 µm/h).Reference Auciello and Sumant1 BEN/BEG UNCD films may be the most appropriate approach for coating of dental and other prostheses.
Properties of UNCD films
The properties of UNCD films most relevant to the development of medical implants and devices include (1) hardness (98 GPa) and Young’s modulus (980 GPa)Reference Auciello and Sumant1 close to corresponding values for single crystal diamond (100 GPa and 1200 GPa, respectively); (2) one of the lowest coefficients of friction (0.02–0.04)1 of any coating developed today; (3) high fracture strength (∼5.3 GPa);Reference Auciello and Sumant1 (4) relatively high electrical conductivity via incorporation of N atoms in the grain boundaries (N-UNCD)Reference Auciello and Sumant1 (Garret et al. recently demonstrated excellent performance of N-UNCD-coated metallic electrodes for neural stimulation.13) or B atoms substitution for C atoms in the diamond lattice (B-UNCD)Reference Auciello and Sumant1 to provide electrons into the conduction band, yielding electrical conductivity;Reference Zhanga, Zimmer, Howe and Maboudian14 (5) extreme resistance to chemical attack by body fluids, as demonstrated by an UNCD-coated Si microchip implanted inside rabbit eyes as the main component of an artificial retina with the aim to restore partial sight to people blinded by genetically induced degeneration of photoreceptors;Reference Xiao, Wang, Carlisle, Mech, Greenberg, Freda, Humayun, Weiland and Auciello9 and (6) the use of UNCD films as scaffolds for efficient stem cell growth and differentiation for tissue engineeringReference Shi, Jin, Chen and Auciello15 (this characteristic may enable enhanced grafting of UNCD-coated dental and other implants via bone cell growth onto the UNCD surface of the implant).
Applications of UNCD coatings in implants and medical devices
Coatings for encapsulation of silicon-based microchips
Research has been conducted over the last two decades to develop implantable prostheses and hybrid bionic systems to restore lost human motor and sensory functions. First-generation neural prostheses are being used to restore hearing and sight via cochlear implantsReference House16 and artificial vision devices, respectively.Reference Weiland, Liu and Humayun17
Human vision is produced by photons from the images penetrating the eye and exciting the retina photoreceptors. The photonic excitation is transformed into electrical pulses, which excite the bipolar cells connected to the photoreceptors. The bipolar cells amplify the electrical pulses and inject them into the ganglion cells (cells that send electrical pulses to the brain) (see Figure 3a), from where the pulses are transmitted through the axons (wire-like electrical pulse carriers connected to the ganglion cells), which bundle altogether to form the optical nerve that carries the electrical signals to the brain where the images are finally formed. Several approaches have been investigated to restore sight to people born with natural sight, who become blind by genetically induced degeneration of retina photoreceptors, which results in retinitis pigmentosa (Figure 2a) affecting young people (∼15–30 years old), and macular degeneration (Figure 2b) affecting older people (≥50 years old).
(a) Schematic of artificial retina concept (Argus II device in its final future rendition); (b) cross-sectional scanning electron microscopy (SEM) micrograph of an ultrananocrystalline diamond (UNCD)-coated Si chip showing the UNCD dense hermetic characteristic; (c) picture of UNCD-coated Si chip implanted in a rabbit eye for about one year; SEM micrograph of UNCD coating (d) before implantation and (e) after implantation, showing no degradation; and (f) x-ray photoelectron spectroscopy analysis of UNCD coating after implantation, showing no surface chemical modification after being exposed to the eye’s saline humour (O1s, N1s, and C1s correspond to the atomic levels of the elements with electron occupancy). Reprinted with permission from Reference 33. © 2013 Woodhead Publishing Limited. Note: RF, radio frequency.
(a) Tubular vision, characteristic of people with retinitis pigmentosa, until they become totally blind, upon losing the last photoreceptors. (b) Peripheral vision characteristic of people with macular degeneration. Reprinted with permission from Reference 33. © 2013 Woodhead Publishing Limited.
Vision restoration technologies
Vision restoration technologies being explored include (1) a flexible digital viewing device, including tools to manipulate information from images and to provide the means for the patient to navigate (move) following visual input;18 (2) microsystem-based visual prosthesis, involving a spiral electrode around the optic nerve, connected to an implanted stimulator, which receives images from an external camera and translates them into electrical signals that stimulate the optic nerve;18 (3) a miniature telescope implanted in the eye’s posterior chamber, which works by increasing (∼3 times) the size of the image projected onto the retina to overcome a central blind spot;Reference Lane and Kuppermann19 (4) a microchip located behind the retina connected to the MPDA (the Tübingen micro-photodiode array [MPDA] project), collecting incident light and transforming it into electrical current stimulating the retina ganglion cells;Reference Zrenner, Bartz-Schmidt, Benav, Besch, Bruckmann, Gabel, Gekeler, Greppmaier, Harscher, Kibbel, Koch, Kusnyerik, Peters, Stingl, Sachs, Stett, Szurman, Wilhelm and Wilke20 (5) an artificial silicon retina, involving a microchip containing photodiodes that detect light and convert it into electrical pulses stimulating ganglion cells (project was discontinued); (6) a photovoltaic retinal prosthesis, with a subretinal photodiode array and an infrared image projection system mounted on video goggles that transmits information from a video camera, processes it in a mobile computer, and displays it on pulsed near-infrared (850–915 nm) video goggles, thus projecting images onto the retina via eye optics to activate photodiodes in the subretinal implant to convert light into pulsed bi-phasic electric current in each pixel;Reference Loudin, Simanovskii, Vijayraghavan, Sramek, Butterwick, Huie, McLean and Palanker21 (7) the Dobelle eye, involving a camera mounted on glasses that transmits images to a stimulator chip implanted in the brain’s primary visual cortex and injects electrical pulses directly to the brain cells;Reference Ings22 (8) an intracortical visual prosthesis with intra-cortical electrode arrays, similar to the Dobelle system, but with increased spatial resolution based on more electrodes per unit area;Reference Rush and Troyk23 (9) a microchip with 98 stimulating electrodes projected for implantation in the supra-choroidal space (a device with 1024 electrodes is under development), being developed by Bionic Vision Australia (national consortium of researchers from the Bionics Institute, the Centre for Eye Research Australia, and several universities);24 (10) the Harvard/MIT retinal implant, involving a subretinal stimulator chip with an electrode array beneath the retina that receives images beamed from a camera mounted on glasses, decodes them, and stimulates ganglion cells with electrical pulses;Reference Doyle, Troyk, Kelly, Shire, Wyatt and Rizzo25 and (11) the Argus II retinal prosthesis, involving a chip that in the final rendition would be implanted inside the eye on the ganglion cell layer, located in the retina (Figure 3a), receive an image from a charge-coupled device camera on a pair of glasses, and inject processed electrical pulses, with image inscription, to the ganglion cells through a large electrode array, such that pulses are finally transmitted to the brain, via the ganglion cell axon bundle (optical nerve), for image formation on the brain cortical region.Reference Humayun, Dorn, da Cruz, Dagnelie, Sahel, Stanga, Cideciyan, Dancan, Eliott, Filley, Ho, Santos, Safran, Arditi, Del Priore and Greenberg26
The Argus II device was developed by a team of researchers from universities, national laboratories, and Second Sight (a company currently commercializing the device) during a 10-year US Department of Energy-funded project. The Argus II device (named one of the top 25 inventions for 2013 by TIME magazine)is currently among the most advanced artificial retina devicesReference Humayun, Dorn, da Cruz, Dagnelie, Sahel, Stanga, Cideciyan, Dancan, Eliott, Filley, Ho, Santos, Safran, Arditi, Del Priore and Greenberg26 and is the only one currently available commercially in the United States and Europe to restore partial sight to people blind by retinitis pigmentosa.
Coatings technologies for encapsulation of implantable microchips
Artificial vision prostheses involving silicon (Si)-based microchips, in the ultimate rendition, implanted inside the eye, should be encapsulated with a hermetic/biocompatible coating to inhibit a chemical destructive attack of Si by the eye’s saline humour (fluid). Hermetic coatings for encapsulation of medical implants should have a double functionality of protecting the implantable device as well as the surrounding tissues to enable long service times free of electronic failure. Two types of packaging technologies are being developed: (1) hard shell (used in the current commercial Argus II device), and (2) encapsulating coatings. For implantable microchips, encapsulating coatings provide a better platform for miniaturization to enable implantation inside the eye, since the hard shell is too big for insertion into the eye. The coatings should be hermetic and biocompatible, because the Si CMOS device performance can be affected by the eye’s saline solution, resulting in the microchip destruction.Reference Hammerle, Kobuch, Kohler, Nisch, Sachs and Stelzle27
Coating materials currently being evaluated for encapsulating implantable Si microchips include SiO2,Reference Meyer28 SiC,Reference Stuart, Edell, Guzelian, Liu and Edell29 polytetrafluoroethylene and polyimide,Reference Seo, Kim, Chung, Kim, Yu and Yu30 and parylene.Reference Seo, Kim, Chung, Kim, Yu and Yu30 SiO2 coatings exhibited dissolution and decay when implanted in animals up to six months.Reference Hammerle, Kobuch, Kohler, Nisch, Sachs and Stelzle27 Polyimide and other polymers are inexpensive and flexible, but absorb significant quantities of water, resulting in electrical leakage, and are not hermetic, enabling chemical attack and eventual destruction of the encapsulated chip.
In contrast, UNCD coatings exhibit a unique combination of properties previously described; and for the encapsulation of an artificial retina Si microchip, UNCD coatings are the only diamond-based coatings that can be grown at ∼400°C (maximum sustainable temperature) on CMOS devices without destructionReference Auciello and Sumant1 and with excellent performance when implanted in animals’ eyes for long periods of time.Reference Xiao, Wang, Carlisle, Mech, Greenberg, Freda, Humayun, Weiland and Auciello9 Extensive in vivo animal studies involving implantation of UNCD-coated Si chips in rabbit eyes (Figure 3b–c), followed by scanning electron microscopy studies (Figure d–e) and x-ray photoelectron spectroscopy (Figure 3f) measurements for surface chemical analysis, showed that the UNCD coating provides encapsulation that may enable long-term (measured in years) implantation of a Si chip inside the eye without any degradation.Reference Xiao, Wang, Carlisle, Mech, Greenberg, Freda, Humayun, Weiland and Auciello9
Details of the development of UNCD films as biocompatible coatings for encapsulation of the artificial retina microchip can be found in Reference 9, while details on the Argus II device development are found in References 26 and 31.
UNCD coatings for treatment of glaucoma
Glaucoma is a medical condition characterized by increased intraocular pressure (IOP) either through increased production or decreased outflow of the eye’s saline humour in the eye’s anterior chamber (Figure 4a). Normally, the aqueous humour flows out of the eye through a mesh-like channel called the trabecular mesh. If the channels become blocked, fluid builds up in the inner part of the eye, resulting in glaucoma.
(a) Schematic of a human eye showing key components; (b) schematic of a glaucoma condition showing optic nerve damage; and (c) schematic showing humour eye drainage flow. Reprinted with permission from Reference 33. © 2013 Woodhead Publishing Limited.
Less common causes of glaucoma include a blunt or chemical injury to the eye, severe eye infection, blockage of blood vessels or eye inflammation, and eye surgery to correct another condition. Glaucoma usually occurs in both eyes, although each eye is differently affected. The increased IOP may result in optic nerve damage (Figure 4b), thus causing damaged vision or blindness.
There may be open- or closed-angle glaucoma. Closed-angle glaucoma can appear suddenly and painfully, with rapid visual loss. Open-angle, chronic glaucoma progression is slower, and lost vision is not noticed until the disease has progressed significantly. Once lost, the damaged visual field cannot be recovered. Glaucoma is the second leading cause of blindness after cataracts. Glaucoma affects one in 40 adults over 40 years of age. It is estimated that by 2020, 80 million people worldwide will suffer from glaucoma.Reference Paolo and Matteo32 Early detection of glaucoma served to arrest or slow the progression via pharmacological, surgical means, or, as a last resort, glaucoma drainage devices. Further details about glaucoma can be found in Reference 32.
UNCD coatings for long-life glaucoma drainage devices
When pharmacotherapies and surgery have failed, glaucoma drainage devices represent an option (Figure 5a). An important unsolved problem with current glaucoma drainage devices is the host reaction against the polymer surface of the implant, occurring immediately after implantation (seconds to minutes and extending for several hours after implantationReference Kenneth Ward34). This occurs via protein layer adhesion to the hydrophilic (water absorbent) polymer-based surface of the device, resulting in an inflammatory response developing within the first eight hours. Macrophages are recruited, by chemical signals, to the implant site where they secrete growth factors that stimulate fibroblast cells responsible for collagen production, producing a fibrous capsule around the implant. After a few weeks, a complete fibrotic reaction occurs, isolating the implant from the rest of the body. This fibrous capsule produces deleterious effects on glaucoma drainage devices, leading to filtration failure.Reference Lim, Allan, Loyd, Muirm and Khaw35
(a) Schematic of a human eye showing implantation of a glaucoma drainage device. Note the need for two incisions: one for inserting the large (∼17 × 12 mm) body of the valve, and one for insertion of the drain tube; (b) optical image of an uncoated glaucoma valve 24 hours after implantation into a rabbit’s eye, showing fibrosis over the implant surface; (c) ultrananocrystalline diamond-coated glaucoma valve about four months after implantation in the second eye of the same rabbit for which the uncoated valve was implanted (showing no fibrosis).Reference Auciello, Gurman, Berra, Zaravia, Zysler and Narayan33
The rest of this subsection focuses on describing the work done in joint collaboration between researchers at The University of Texas-Dallas, the University of Buenos Aires, and the Hospital Austral in Buenos Aires, Argentina, aimed to demonstrate the effectiveness of a UNCD coating in avoiding fibrotic capsule development around a glaucoma silicone-based drainage device that impairs the drainage of the eye’s saline humour. All experiments were conducted following the US National Institutes of Health (NIH) and the Administración Nacional de Medicamentos, Alimentos y Tecnología Médica (ANMAT) guidelines (Argentina’s FDA equivalent) for animal care. The experiments involved two rabbits, each receiving one uncoated drainage device (Figure 5b) in one eye, and one coated with a low temperature (∼400°C) UNCD film (Figure 5c) in the other eye. The experimental approach was conducted in order to reduce the number of animals involved and avoid inter-individual variability from using different animals in one experiment. In the 24 hours after implantation, the uncoated device was covered with fibrosis due to protein adhesion in the eye, while the UNCD-coated device remained clear even after several months of implantation.Reference Auciello, Gurman, Berra, Zaravia, Zysler and Narayan33 This was a demonstration of the effectiveness of UNCD films as bio-inert/biocompatible encapsulating coatings to improve, by orders of magnitude, the lifetime of the implanted devices.
The lack of protein adhesion on the surface of the UNCD-coated drainage device is attributed to the fact that the surface of UNCD films is extremely hydrophobic due to the hydrogen termination of the surface of the as-deposited UNCD films.Reference Auciello and Sumant1
UNCD-coated grid as new glaucoma treatment implant
As mentioned earlier, current glaucoma drainage devices are relatively large and require two surgical incisions, as indicated in Figure 5a. The USA-Argentina collaboration group is developing an alternative approach, involving implanting a small grid (∼3 mm in diameter), featuring hundreds to thousands of small holes formed by the boundaries of a grid of thin wires in the clogged trabecular meshwork region (Figure 6a).Reference Auciello, Gurman, Berra, Zaravia, Zysler and Narayan33
(a) Schematic of a new smaller glaucoma drain device based on an ultrananocrystalline diamond (UNCD)-coated grid with hundreds to thousands of holes, implanted in the trabecular meshwork. Optical pictures of grids implanted in the trabecular meshwork region of separate rabbit’s eyes in the same animal: (b) Uncoated Cu grid showing rejection in about 24 hours, and (c) UNCD-coated Cu grid after several months implantation, showing no rejection. Reprinted with permission from Reference 33. © 2013 Woodhead Publishing Limited.
Preclinical trials were conducted in an animal facility at the University of Buenos Aires, Argentina, following protocols approved by NIH and ANMAT for animal care. It was expected that the large number of holes in the grid would provide very efficient drainage of the eye’s humour. The grid was coated with a UNCD film. Initial experiments were performed using copper (Cu) grids to demonstrate the power of the UNCD film as a bioinert/biocompatible coating. It is well known that Cu elicits unacceptable toxicity in the eye, and if the UNCD coating were not hermetic, the eye humour would permeate though it, and the eye would recognize the presence of Cu underneath the UNCD film and eject the grid. Figure 6b shows a Cu grid, implanted in the trabecular region of one rabbit eye, being biologically rejected and expulsed outside the eye in about 24 hours after implantation.Reference Auciello, Gurman, Berra, Zaravia, Zysler and Narayan33 In contrast, a UNCD-coated grid implanted in the other eye (Figure 6c), remained totally inert inside the eye for several months.Reference Auciello, Gurman, Berra, Zaravia, Zysler and Narayan33
This initial work shows a promising drainage device technology and much less invasive surgical procedure for treating glaucoma, due both to the much smaller device and simpler surgical procedure. Titanium (Ti) will be used as a grid material in future work, since UNCD films grow very well on Ti1 and will protect Ti from chemical attack by the eye’s saline humour.
UNCD coatings for new dental implants
Pure Ti and Ti alloys are widely used in dental and orthopedic implants. The use of Ti-based prostheses was motivated by past work showing that Ti-based implants exhibit appropriate mechanical properties and biocompatibility.Reference Abdel-Hady Gepreel and Niinomi36 However, recent literature on the performance of Ti implants in patients indicates that they exhibit failures, specifically due to loss of osseointegration (a direct structural and functional connection between ordered living bone and the surface of a load-carrying implant) and corrosion.Reference Omar, Omar, Esposito, Lausmaa and Thomsen37
Current Ti-based dental implants, used to replace missing teeth, fail due to body fluids-induced Ti corrosion,Reference Gittens, Olivares-Navarrete, Tannenbaum, Boyan and Schwartz38 which releases metallic particles from the Ti surface into local tissue from where it could reach the systemic circulation,Reference Olmedo, Cabrini, Duffó and Guglielmotti39 with a potential increase in metal levels in the plasma. These elevated levels could result in systemic toxicity, as observed for other metallic implants.Reference Allen, Ambardekar, Devaraj, Maleszewski and Wolfel40 On exposure to air or liquid, titanium develops a passivating titanium dioxide (TiO2) layer that makes it nonreactive. It is well known that the TiO2 layer prevents corrosion. However, when it is in contact with body tissue and fluids, electrochemical processes take place, rendering it prone to breakage, which releases ions/particles into the milieu. Once the passivating oxide layer is eliminated, the Ti implant acts as an in vivo electrode that produces electrochemical reactions in the tissue.
UNCD-coated metallic implants exhibit extreme resistance to chemical attack by body fluids.Reference Auciello and Sumant1,Reference Xiao, Wang, Carlisle, Mech, Greenberg, Freda, Humayun, Weiland and Auciello9 In addition, roughening of the Ti implant surface by micromachining followed by coating with UNCD films produces a chemically resistant micro-roughened surface that can enhance osseointegration, as demonstrated previously for roughened Ti implant surfaces.Reference Hacking, Boyraz, Powers, Sen-Gupta and Kucharski41 In addition, recent work demonstrated that NCD coatings exhibit increased resistance to bacterial adhesion as compared to stainless steel and Ti.Reference Amaral, Gomes, Lopes, Santos and Silva42
In one study, Ti laminar implants were used as samples for in vivo tests. The samples used were (1) uncoated Ti, (2) UNCD-coated Ti (Figure 7a), and (3) UNCD/W-coated Ti, wherein a W layer was grown on the surface of the Ti implant using magnetron sputter-deposition to enhance the density of UNCD coatings, which was demonstrated by the formation of a dense tungsten carbide (WC) template interface on the surface of the W layer.Reference Auciello and Sumant1 The UNCD coatings were grown on all samples using the MPCVD method.Reference Auciello and Sumant1 Male Wistar rats were used to study the interaction of uncoated Ti and UNCD-coated Ti implants with bone. NIH guidelines as well as the Ethics Principles of the Faculty of Dentistry, University of Buenos Aires, for surgical procedures and care of laboratory animals, were followed.
(a) Cross-sectional scanning electron microscopy micrograph of an ultrananocrystalline diamond (UNCD) film grown on a Ti implant, showing high density and smoothness of the UNCD film surface. (b) Micrograph of the implant-tissue interface (UNCD-coated Ti). Lamellar bone tissue (B) in close contact with the surface of the implant (in black), showing good osseointegration. BM (bone marrow), Mag. x400. Note: t, thickness.Reference Auciello, Gurman, Berra, Zaravia, Zysler and Narayan33
The histological analysis of the samples from the control and experimental groups revealed areas of lamellar bone in close contact with the surface (osseointegration) (Figure 7b) and areas of bone marrow in contact with the implant surface (myelointegration). These studies showed that UNCD has good biocompatibility as a coating material for dental implants. Among other factors, the clinical success of implants depends on osseointegration of the implant and, if coated, on the coating/substrate reliability. Histological studies indicated that the UNCD-coated Ti implants in this study achieved excellent osseointegration, without exhibiting any inflammatory reactions (Figure 7b).
The unique mechanical, tribological, chemical, and biological properties of UNCD films demonstrated in the work reviewed in this article indicate that UNCD coatings may enable the manufacturing of a new generation of dental implants with anticorrosion properties, which can provide more superior performance than current uncoated metal-based implants.
Summary
The discussion of the fundamental and applied materials science as well as implant and device development and testing for representative key medical implants and devices based on UNCD coatings shows that this material provides a unique combination of mechanical, tribological, chemical, and biological properties, which will help develop new medical implants and devices with superior performance compared to those currently based on other materials. In this respect, UNCD coatings will enable a new generation of chemically robust (resistant to chemical attack by body fluids) UNCD-coated prostheses (e.g., artificial hips knees, elbows, dental implants), UNCD-coated catheters, and electrically conductive N-UNCD-coated electrodes for neural stimulation. In addition, it has been demonstrated that UNCD surfaces can provide new scaffolds for stem cell growthReference Shi, Jin, Chen and Auciello15 and differentiation, opening new opportunities in the field of tissue engineering.
Acknowledgments
Work performed at the University of Texas-Dallas was supported by the Endowed Chair funds of O.A. (#37139010). O.A. acknowledges support by the DOE-Artificial Retina Project (US Department of Energy, Biomedical Engineering Research under contract W-31-109-ENG-38) and collaborators, especially M. Humayun (project director). Work performed in M.G.’s laboratory (University of Buenos Aires-Argentina) was funded by grants: UBACyT 20020100100812 (UBA); PIP 11220090100117 (CONICET); and PDTS PO 01 2013 (UBA)-Ministry of Science, Technology, and Productive Innovation, Argentina. M.G. acknowledges contributions by Dr. Cabrini and Eng. Almagro (CNEA Argentina) for the experimental model for laminar implants.
Orlando Auciello holds an endowed chair in the Materials Science and Engineering and Bioengineering Department at The University of Texas at Dallas. He received his MS (1973) and PhD (1976) degrees in physics at the University of Cuyo, Argentina. His research interests include multifunctional oxide thin films for memory, high frequency, and micro/nanolectronic devices, nanocarbon films for MEMS, and biomedical devices. He has published 450 articles, 19 books, and two book series and holds 17 patents. Among his awards are seven R&D 100 Awards, the National Laboratories Award for commercialization of UNCD technology, Fellow of AAAS and MRS, and MRS President in 2013. Auciello is also co-founder of Advanced Diamond Technologies and Original Biomedical Implants, Commercializing the UNCD technology. Auciello can be reached at The University of Texas at Dallas, Richardson, TX, USA; tel. 972-883-4731; and email oha120030@utdallas.edu.
Pablo Gurman is a research scientist at The University of Texas at Dallas and a visiting scientist at the Institute for Soldier Nanotechnologies of the Massachusetts Institute of Technology. He received his MD degree at Facultad de Medicina, Universidad de Buenos Aires, Argentina, in 2002. His research interests include nanocarbon films for bioMEMS, nanomedicine, and drug delivery. He has published six papers, two encyclopedia chapters, and four book chapters, and he is an author of three books. Gurman has two patents pending. He can be reached at The University of Texas at Dallas, Richardson, TX, USA; tel. 972-883-4881; and email pablo.gurman@utdallas.edu.
María B. Guglielmotti is head professor in the Oral Pathology Department, School of Dentistry, University of Buenos Aires (UBA) (2002–present). She is also a researcher of the Scientific and Technological Research Council of Argentina (1985–present). She received her PhD degree in 1983 at the University of Buenos Aires and her Oral Pathology Specialist degree in 1983 at UBA. Her research interests include bone biology and biocompatibility of implant biomaterials (metallic/bone substitutes). She has published 64 articles, seven book chapters, and 80 abstracts. She was president of the Argentine Division of the International Association for Dental Research in 1995; director of nine PhD theses; and director of 13 Research Fellows. She received the Houssay Award in 1987. Guglielmotti can be reached at the School of Dentistry, UBA, Buenos Aires, Argentina; tel. 5411-49641273; and email bguglielmotti@gmail.com.
Daniel G. Olmedo is a professor in the Oral Pathology Department, School of Dentistry, University of Buenos Aires (UBA). He is also a researcher of the Scientific and Technological Research Council of Argentina. He received his DDS (1992) and PhD (2001) degrees from the University of Córdoba and his Specialist in Oral Pathology degree (2009) from UBA. His research interests include implant materials biocompatibility and metallic implant corrosion. He has published 22 peer-reviewed articles, two book chapters, and 52 conference abstracts. He received the Argentina Division Hatton Award in 2000 and 2004. He is vice president (2013–2014) and president (2015–2016) of the Argentine Division of the International Association for Dental Research. Olmedo can be reached at the School of Dentistry, UBA, Buenos Aires, Argentina; tel. 5411–49641273; and email dolmedo@argentina.com.
Alejandro Berra is head of laboratory practices and adjunct professor of cellular and molecular medicine at the University of Buenos Aires. His research interests include investigative ophthalmology and visual science, experimental eye research, clinical and experimental ophthalmology, visual neurosciences, and cell biology. He has published 35 papers and four book chapters. He has one international and four national awards. Berra can be reached at the Facultad de Medicina, Universidad Nacional de Buenos Aires, Paraguay, and Ciudad Autónoma de Buenos Aires, Argentina; tel. +54 11 4508 3608; and email alejo.berra@gmail.com.
Mario J. Saravia is chairperson of the Department of Ophthalmology, Hospital Universitario Austral (2006–present). His interests include ophthalmic surgery, retinal diseases, and clinical research. He is also director of the Latino American postgraduate course of ophthalmology. He has published 18 papers and seven books as co-author and holds one patent. Saravia can be reached at Tigre, Buenos Aires, Argentina; tel. +54 911 5229 9000; and email msaravia@cas.austral.edu.ar.md.



