Clostridioides (formerly Clostridium) difficile, a gram-positive, spore-forming, anaerobic bacteria, is the most common cause of healthcare-associated infection in the United States.Reference Lessa, Mu and Bamberg 1 The spores of C. difficile are highly resistant to a wide range of disinfectants and can persist for long periods in many different environments. Previously, our group showed that C. difficile can be isolated from areas within and outside of the hospital regardless of proximity to a CDI patient.Reference Alam, Walk and Endres 2 Thus, prevention and control of outbreaks or hyperendemic CDI likely requires an in-depth knowledge of the molecular epidemiology of the strains throughout the continuum of care. Thus, careful monitoring of patients outside of the acute-care hospital presents an important challenge for infection control.Reference Chopra and Goldstein 3 , Reference Curry, Muto and Schlackman 4 Outbreaks of CDI are recognized in hospitals and, to a lesser extent, in extended healthcare centers such as long-term care (LTC) facilities.Reference Ziakas, Joyce and Zacharioudakis 5 , Reference Wust, Sullivan, Hardegger and Wilkins 6 The purposes of this study were (1) to describe a CDI outbreak in a LTC facility that used molecular typing techniques and whole-genome sequencing to identify the dissemination of the clonal strain in the environment and (2) to describe the effects of terminal cleaning.
Methods
Clinical setting and case definition
The outbreak occurred at a 146-bed LTC facility in Texas that provides nursing care and rehabilitation services to patients with chronic medical conditions. The facility had not previously had any outbreaks or recent cases of CDI.
During the outbreak investigation, a CDI case was defined as a resident with new onset of diarrhea as well as a positive diagnostic test for C. difficile toxins using a commercially available C. difficile toxin a/b EIA test.
Environmental decontamination and sampling
We hypothesized that environmental contamination outside the patient’s room contributed to the outbreak of cases throughout the facility. To test the hypothesis that C. difficile spores were likely disseminated throughout the facility, 50 surface samples of 930 cm2 (~1 square foot) were swabbed with presterilized cotton gauze moistened with sterile water. Samples were placed into a 50-mL presterilized tube and transported to the laboratory within 12 hours of collection. For each batch of 10 swabs, a negative control (ie, an unused swab) was included to ensure no cross contamination of swabs. To assess environmental contamination in patients’ rooms compared to communal areas in the facility, all patient rooms were swabbed (n=30 swabs), with an additional 20 swabs taken from elsewhere in the facility. If the results of the initial environmental sampling confirmed the hypothesis of widespread spore dissemination in the environment, the entire facility was scheduled to undergo a terminal clean with a 10% bleach solution. The terminal clean was performed by trained facility staff with the guidance of the state health department. Environmental sampling of the facility was repeated 6 months later in the same patient rooms and communal areas to test for continued presence of C. difficile.
Microbiologic procedures
Stool and environmental samples were enriched in brain heart infusion (BHI) broth with 0.05% sodium taurocholate (Sigma Chemicals, St Louis, MO) and incubated anaerobically at 37°C for up to 3 days as previously described.Reference Alam, Walk and Endres 2 From each sample, 10 mL broth culture was centrifuged to concentrate the cells with the resulting pellet suspended in 100 µL of normal saline (0.85% NaCl), plated onto cycloserine cefoxitin fructose agar (CCFA, Anaerobic Systems, Morgan Hill, CA), and incubated anaerobically at 37°C for 40–48 hours (Forma Anaerobic System, Mode 1025/1029). Suspected colonies were tested using latex agglutination reagent (Oxoid, Hampshire, UK). Each batch of samples was processed with a positive and a negative control. The presence of toxin genes was assessed using multiplex polymerase chain reaction (PCR) to detect the presence of toxin A (tcdA), toxin B (tcdB), and tpi genes.Reference Lemee, Dhalluin and Testelin 7
Clostridioides difficile ribotyping
Fluorescent ribotyping was performed as previously described.Reference Martinson, Broadaway and Lohman 8 , Reference Alam, Anu, Walk and Garey 9 Briefly, PCR ribotyping primersReference Bidet, Barbut, Lalande, Burghoffer and Petit 10 were synthesized with a fluorescent label (Life Technologies, Carlsbad, CA) and adjusted to 10 pmol/μL. A 25 μL PCR was performed using AmpliTaq Gold DNA polymerase (Applied Biosystems, Foster City, CA) and the following conditions: 95°C (10 minutes); 35 cycles of 95°C (30 seconds), 55°C (30 seconds), and 72°C (1 minute 30 seconds); and a final extension of 72°C (10 minutes) (Eppendorf vapo-protect thermal cycler, Thermo Scientific, Waltham, MA). Amplicons were analyzed using an ABI3730xl DNA Analyzer and MapMaker 1000 ROX DNA sizing standard (BioVentures, Murfreesboro, TN). This technique does not distinguish between ribotypes 053 and 163, ribotypes 014 and 020, and ribotypes 078 and 126; therefore, these are reported as combined ribotypes (ie, 053-163, 014-020, and 078-126).
Clostridioides difficile multilocus variance analysis
The multilocus variance analysis (MLVA) typing of C. difficile isolates ribotype 027 was performed using a previously published fluorescent MLVA markers methodReference van den Berg, Kuijper, van Coppenraet and Claas 11 described by Broukhanski et al.Reference Broukhanski, Low and Pillai 12 , Reference Broukhanski, Simor and Pillai 13 Briefly, amplicons are diluted in formamide, mixed with LIZ600 DNA ladder and run on an ABI 3130xl genetic analyzer (Applied Biosystems) for fragment analysis. Processing of capillary electrophoresis was done using BioNumerics version 7.6 software (Applied Maths, Austin, TX). Peak files from the genetic analyzer were normalized to the LIZ600 DNA ladder to determine amplicon size and to calculate the summed tandem-repeat difference (STRD). The copy number for each variable number of tandem repeats (VNTR) locus based on amplicon size was determined using previously published guidelines.Reference Broukhanski, Low and Pillai 12 Complexes containing >2 isolates whose MLVA genotypes generated an STRD <2 were defined as highly related isolates.Reference Curry, Muto and Schlackman 4
Whole-genome sequencing
For whole-genome single-nucleotide polymorphism (SNP) analysis, cleaned sequence reads were mapped to the R20291 reference genome (GenBank accession no. FN545816) using the RedDog pipeline (https://github. com/katholt/RedDog) according to the developer’s previous guidelines. Briefly, Bowtie2 version 2.2.3 softwareReference Langmead and Salzberg 14 was used for mapping, and SAMtools version 0.1.19 softwareReference Li, Handsaker and Wysoker 15 was used for calling SNPs. Only high-quality SNPs were used for phylogenetic analyses. Phylogenetic trees were created in FigTree and edited using iTOL (https://itol.embl.de/). Transmission analyses were carried out as described previously.Reference Kumar, Miyajima and He 16 The ARG-ANNOT database was used to identify antimicrobial resistance genes.Reference Gupta, Padmanabhan and Diene 17
Results
Description of outbreak
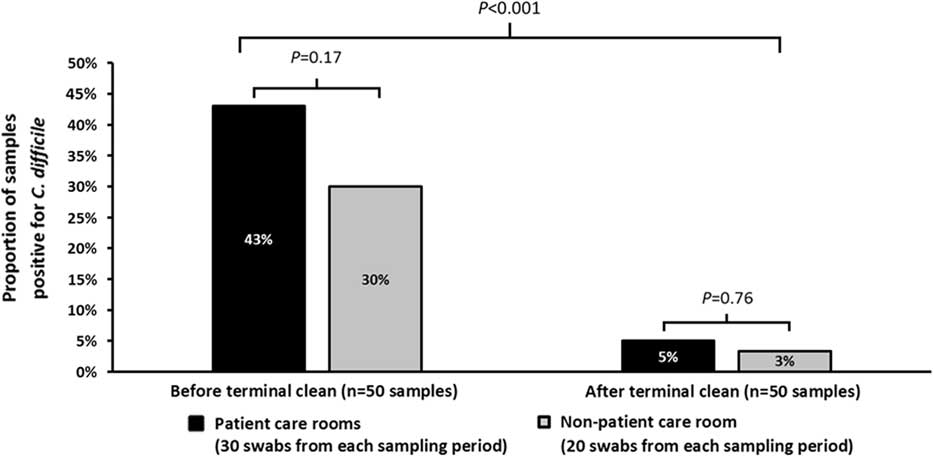
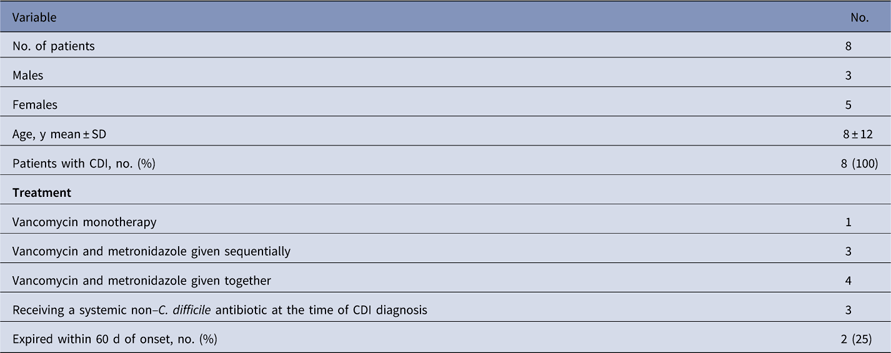
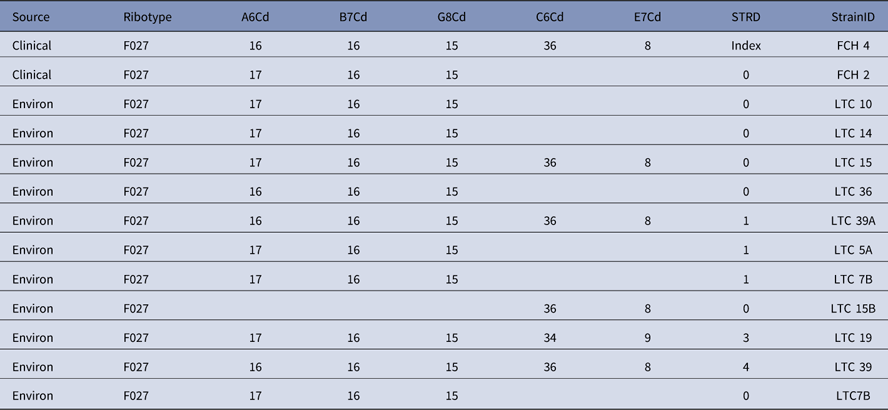
In September 2016, a 90-year-old male recently discharged from an acute-care facility was diagnosed with CDI after a new onset of diarrhea with abdominal pain. Despite terminal cleaning with a 10% bleach sporicidal solution in rooms with active cases, a total of 7 additional residents became symptomatic and tested positive for C. difficile toxins over the next 2 months. A description of the 8 patients who acquired CDI during the period at the facility is provided in Table 1. Stool specimens were available from 5 patients for C. difficile growth and typing. Of the 5 stool specimens, 4 grew toxigenic C. difficile: all 4 were ribotype 027. Also, 50 environmental swab samples were collected prior to the facility-wide terminal cleaning; 14 of these grew toxigenic C. difficile (28%). Of these 14 isolates, 11 (79%) were ribotype 027. Toxigenic C. difficile spores were disseminated throughout the facility; they were present in the patient care environment (43%) and in non–patient care areas (30%; P=0.17). Environmental contamination was disseminated widely throughout the institution, including bed handrails, television remote control, doorway entrances, shower seat surface, wheelchair arms, toilet hand rails, bedside table, sink surfaces, physical therapy grip handrail, dining room table top, and communal shower chairs. These results prompted a facility-wide terminal cleaning, which was effective at decreasing contamination by C. difficile spores and eradicating the ribotype 027 strain from the environment (Fig. 1). After the terminal cleaning, the environmental swabbing of the facility was repeated. Of 50 environmental swab samples, 2 grew toxigenic C. difficile (1 swab each from a patient-care area and a non–patient care area). Neither of the 2 C. difficile isolates were ribotype 027. The MLST was not able to differentiate the isolates (all were ST-1); therefore, MLVA was conducted to provide more discrimination. The MLVA typing was successful in 11 environmental ribotype 027 isolates and 2 of the 4 ribotype 027 clinical isolates. Both clinical strains were highly related to each other, and 9 of the 11 environmental isolates were considered highly related to the clinical isolates (Table 2).
Proportion of positive environmental samples before and after facility-wide terminal clean with 10% bleach solution. Plotted on the x-axis is the time point before and after terminal clean and the y-axis shows the percentage of samples that were positive for C. difficile. There was a significant difference in percentage of specimens positive for C. difficile between patient care rooms (black bars) and non–patient care areas at both time points. Terminal cleaning significantly reduced the C. difficile burden overall.

Description of Clostridioides difficile Infection (CDI) Cases

Note. SD, standard deviation.
MLVA Typing of Ribotype 027 Clinical and Environmental Clostridioides difficile Isolates

Note. Environ, environmental isolate.
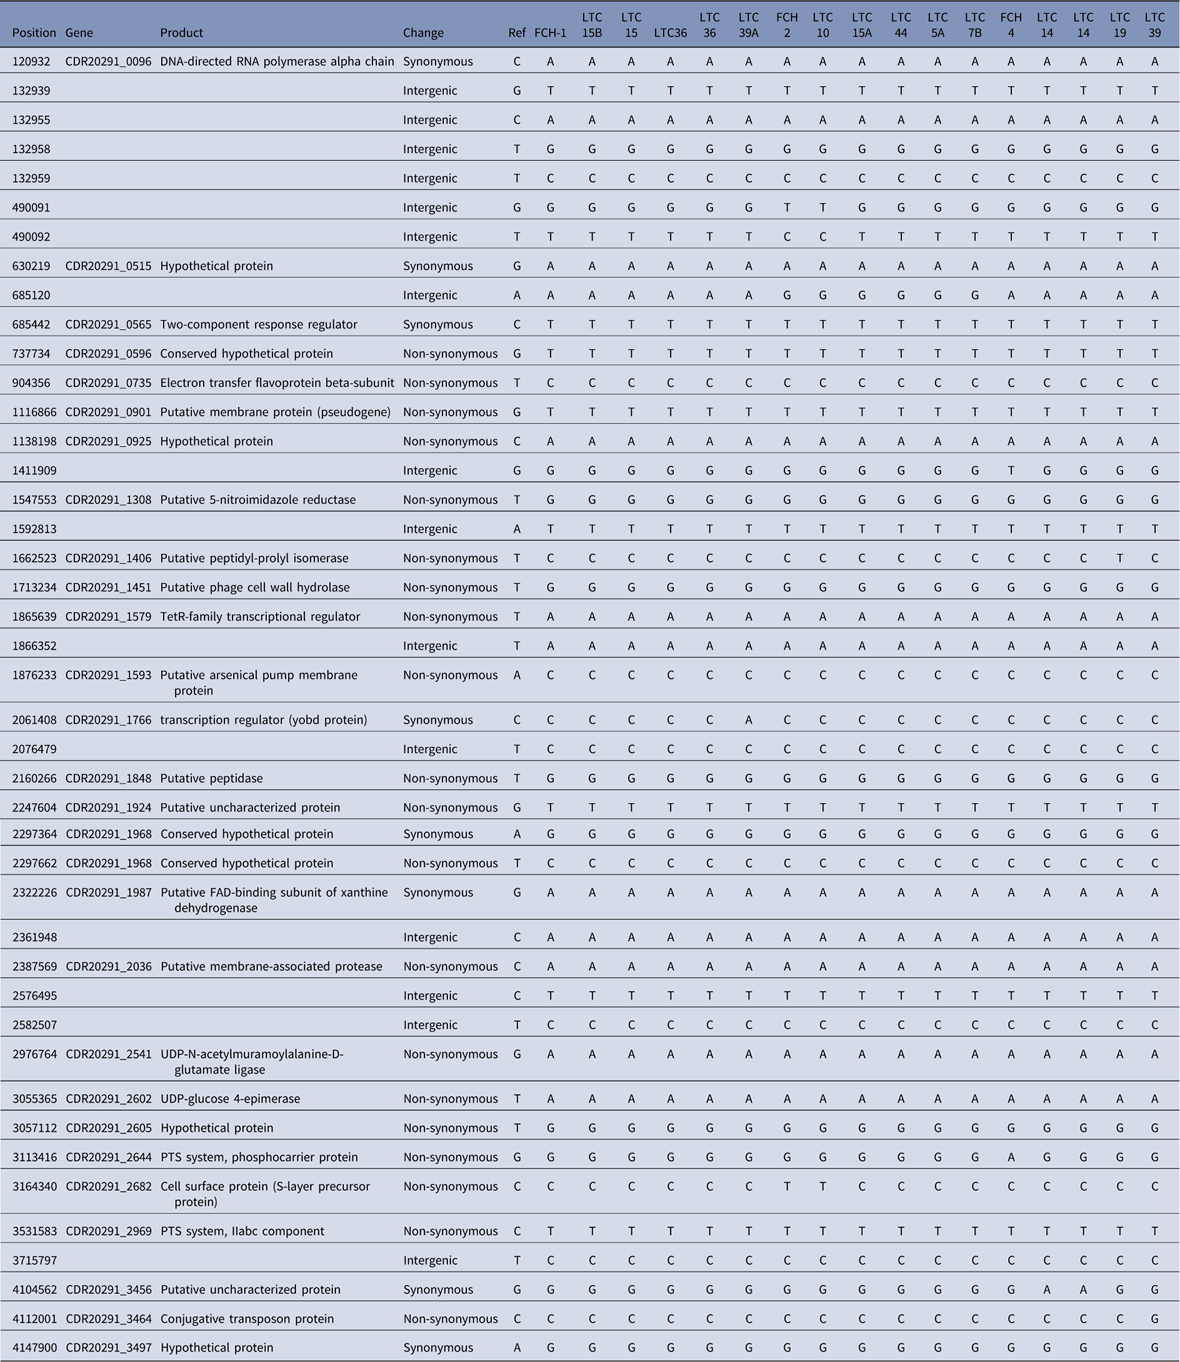
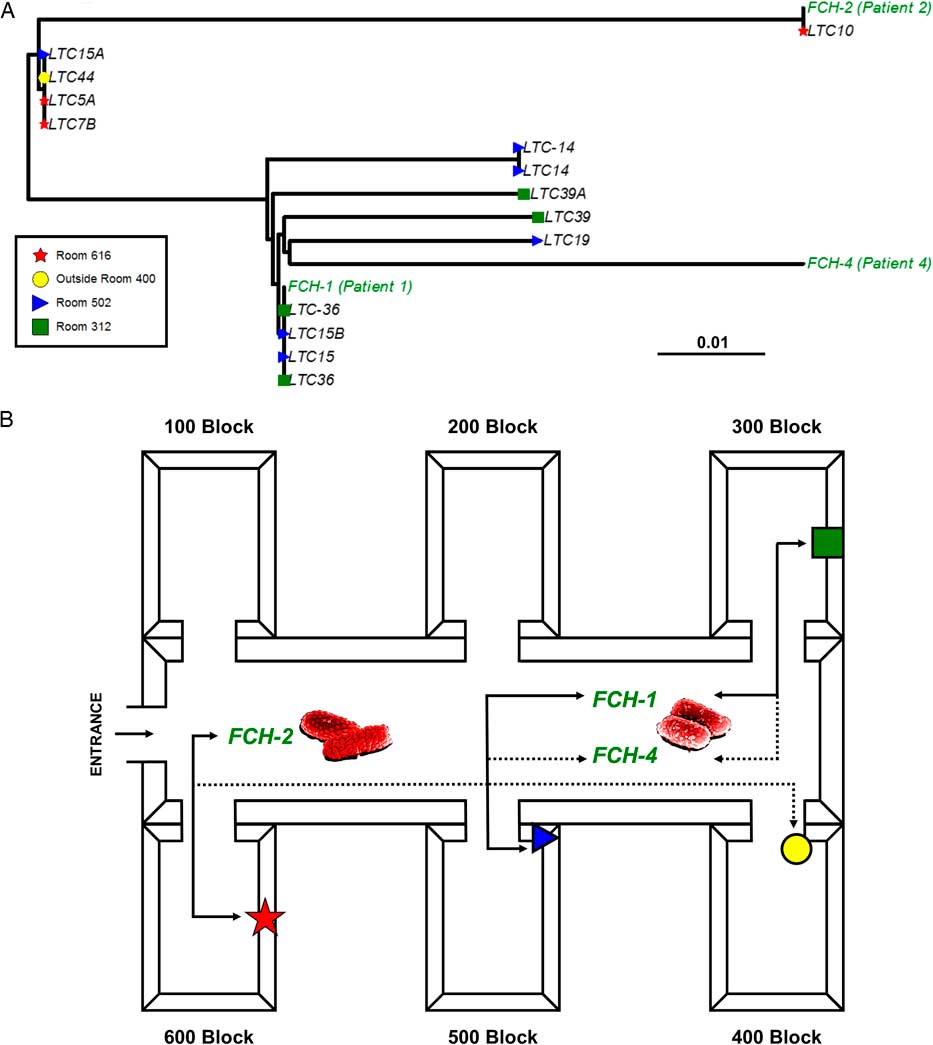
To determine the extent to which the isolates were highly related, whole-genome sequencing was carried out. In total, 17 isolates were sequenced, including 3 clinical and 14 environmental isolates. Sequencing produced >10 million high-quality sequencing reads per isolate, which corresponded to >20 times the depth of coverage. Reads were mapped to the R20291 reference core genome, and SNPs were identified. All isolates were >99.999% genetically similar and only differed at 9 SNP sites, which included 4 intergenic mutations, 1 synonymous substitution, and 2 nonsynonymous substitutions. The 3 clinical strains varied at a total of 4 SNP sites; the clinical strain FCH-1 was different from another clinical strain FCH-2 by 2 SNPs and was different from clinical strain FCH-4 by 4 SNPs (Table 3). All of the strains were of the fluoroquinolone resistant 2 (FQR2) lineage.Reference He, Miyajima and Roberts 18 In addition to fluoroquinolone resistance, 2 strains (clinical strain FCH-4 and environmental strain LTC-7B) contained bla TEM-1D encoding a β-lactamase.
Whole-Genome Sequencing SNPs and Annotation

To demonstrate the overall genetic relatedness, a maximum likelihood phylogenetic tree was made from 44 SNP sites (Fig. 2A). As a proof of concept, 2 colonies each were isolated from 2 different isolates (LTC-36 and LTC-14), were sequenced in duplicate, and were identical. Certain environmental isolates were 100% genetically identical to the clinical isolates (Fig. 2A). Using epidemiological data with the sequencing results, transmission analyses were performed on all the isolates. Because chronology between clinical cases and environmental contamination was unclear, a conjectural transmission diagram was created from the isolation location and the SNP analysis (Fig. 2B). Because there was only a 2 SNP difference between FCH-1 and FCH-4, these strains were likely derived from a common source, either the 300 block or the 500 block of rooms. These data provide strong evidence that there was transmission between the patient and the LTC facility environment.
Maximum likelihood phylogeny and CDI transmission map. (A) The phylogenetic tree was made from 44 SNP sites and is midpoint rooted. Patient isolates are colored in green font and environmental samples in other colors based on location. The bar at the bottom of Fig. 2a (0.01) refers to degree of relatedness of isolates. (B) Using the epidemiological data with the phylogeny, a suspected transmission map was made of the long-term care facility. A solid line indicates an isolate shared a direct contact and was genetically identical to another isolate, whereas the dotted line indicates a suspected connection to another isolate. Red spore indicates a patient isolate. For example, clinical isolate FCH-2 was genetically identical to an environmental isolate from the 600 block of the LTC that was highly similar but not identical to an environmental isolate from the 400 block.

Discussion
Residents of LTC facilities have been recognized to be at risk for CDI due to a variety of factors including advanced age, administration of systemic antibiotics, and high rates of comorbid conditions.Reference Chopra and Goldstein 3 Hospitalized patients developing CDI are more likely to be discharged to LTC facilities than are other hospitalized patient populations.Reference Dubberke, Butler and Reske 19 Two previous outbreaks of CDI due to ribotype 027 has been reported in residents of LTC facilities.Reference Guerrero, Nerandzic, Jury, Chang, Jump and Donskey 20 , Reference Archbald-Pannone, Boone, Carman, Lyerly and Guerrant 21 However, whole-genome sequencing and subsequent molecular epidemiology of the outbreak were not conducted in these previous studies. In the current study, we used molecular typing techniques to identify a highly related, clonal outbreak of C. difficile ribotype 027. The clone was widely disseminated throughout the facility; it was present in patient rooms as well as other areas of the facility. The facility, guided by the results of an environmental contamination investigation, was able to eradicate the ribotype 027 from the environment and to reduce the contamination of C. difficile spores in the environment. The molecular typing was accomplished using high-throughput, cost-effective techniques to start (ribotyping) followed by more discriminatory typing techniques (MVLA and WGS) to confirm the relatedness of the strains. Using these tools, we were able to demonstrate clonal dissemination of ribotype 027 throughout the facility as well as successful eradication of the clone from the facility. Finally, using whole-genome sequencing, a potential route of transmission of isolates throughout the facility was generated and provided insight into the transmission of C. difficile between patients and the environment.
Although uncommon, use of environmental sampling to guide decontamination efforts has been reported.Reference Yui, Ali, Muzslay, Jeanes and Wilson 22 A tertiary-care referral center in England sampled 16 different sites within the hospital to guide terminal cleaning with either a sporicidal agent or aerial hydrogen peroxide. Although persistence in the environment was observed, a decrease in the number of positive C. difficile isolates was observed. A typing method was not used in this study. We have previously demonstrated that toxigenic C. difficile spores are present in the healthcare and non–healthcare environments, including shoe bottoms.Reference Alam, Walk and Endres 2 It is possible that sites that underwent terminal cleaning became recontaminated from another source. This example demonstrates the value of typing in addition to culture to demonstrate removal of the original clone. For example, in our study, 2 positive C. difficile cultures were identified after terminal cleaning. Using ribotyping, we were able to demonstrate that these cultures were not from the original ribotype 027 clone present in the LTC facility.
This study has several limitations. Although we were able to demonstrate the effectiveness of our terminal clean to remove the ribotype 027 clone from the environment, we cannot infer the causality that this intervention interrupted the ongoing outbreak. However, because the isolates were identical between the environmental and clinical strains, it is possible. We were not able to perform MLVA analysis on 2 of the ribotype 027 clinical isolates, and we did not get deep enough sequence reads for a single ribotype 027 isolate for whole-genome sequencing analysis. Movement of patients throughout the facility made more detailed epidemiologic studies to correlate patient movement with spore dissemination difficult. This CDI outbreak was the first ever at this institution. Whether this guided decontamination technique would work at other healthcare settings with prior cases of CDI or higher rates of C. difficile contamination with more diverse ribotypes will require further study.
In conclusion, using a variety of molecular typing techniques, we were able to demonstrate reduced environmental contamination of toxigenic C. difficile spores and eradication of a ribotype 027 clone. Applying this technique to other healthcare centers may help to decrease the burden of CDI in the healthcare system.
Acknowledgments
We would like to thank the University of Houston Seq-N-Edit core for help with sequencing. We would like to thank the University of Houston Center for Advanced Computing and Data Science, specifically Peggy Lindner, for assistance and support with the bioinformatics analyses.
Financial support
This work was supported by research grants from the Texas Department of State Health Services and the National Institutes of Health/National Institute of Allergy and Infectious Diseases (NIH NIAID grant no. 1UO1 AI-24290-01).
Conflicts of interest
All authors report no conflicts of interest.