Prophylactic implantation of temporary epicardial pacing wires after surgery for congenital heart disease is a common practice for the diagnosis and therapy of post-operative arrhythmias.Reference Batra and Balaji 1 Although today mainly bipolar temporary pacing wires are implanted because of their better performance characteristics compared with unipolar wires,Reference Batra and Balaji 1 – Reference Yiu, Tansley and Pepper 3 the functional lifetime of temporary pacing wires is very restricted, and early dysfunction is a common problem.Reference Elmi, Tullo and Khalighi 4 Recently, we experienced early failure – ventricular exit block – of bipolar temporary pacing wires in two patients after congenital cardiac repair. In both cases, atrioventricular synchronous pacemaker therapy could be re-established using the failing bipolar lead with a unipolar stimulation mode. Thus, in our 5-month-old patient who underwent a ventricular septal defect repair and had a post-surgical complete atrioventricular block, ventricular pacing could be re-established on the second post-operative day for 42 hours. In our other patient, a 10-month-old patient who underwent the Ross–Konno procedure and had a second-degree atrioventricular block, unipolar stimulation was applied from post-operative day 2 to 4. In both patients, the atrioventricular conduction impairment resolved spontaneously. The unipolar pacing thresholds were stable during their application, and the pacing mode was well tolerated, not requiring changes in sedation. The aim of the present study was to systematically investigate the feasibility of the suggested unipolar conversion for standard bipolar temporary pacing wires and to evaluate its electrical characteristics in comparison with the bipolar “gold standard”. The results are discussed with regard to the possible clinical implications.
Methods
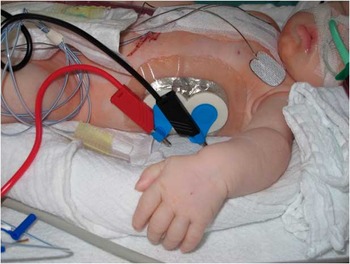
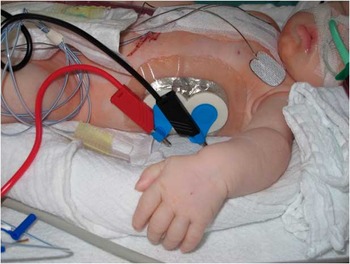
Our current practice consists of prophylactic placement of quadripolar temporary myocardial leads (Heartwire, TME4-68T, Osypka, Rheinfelden, Germany) in all patients with congenital heart disease undergoing a cardiopulmonary bypass. Wires are attached to the right atrium – the right atrial appendage or the body of the right atrium – and to the anterior or diaphragmatic surface of the right ventricle, keeping a distance of 1.0–2.0 cm between the two wires of the bipolar electrodes. For the present study, 18 consecutive post-operative patients with a body weight below 20 kg were tested for bipolar and unipolar functioning of the atrial and ventricular leads after arrival at the intensive care unit. Before testing, a 12-channel ECG was recorded to exclude major arrhythmias. For the testing procedure, we used an external pacemaker (Pace 300, Osypka GmbH, Germany) with one atrial and two independent ventricular channels. This device allows a very accurate trimming of sensitivity (atrial 0.2–20 mV, steps of 0.1 mV, ventricular 1–20 mV, steps of 0.1 mV) and stimulation parameters (amplitude 0.1–18 V, steps of 0.1 mV; Fig 1). The bipolar pacing parameters served as reference values by connecting the two atrial cables to the atrial channel and the two ventricular cables to the right ventricular channel. We determined the pacing thresholds at a fixed pulse duration (0.5 ms) and sensitivity for the atrium in the AAI mode and for the ventricle in the VVI mode. For the unipolar measurements, only one of the two cables of the bipolar electrodes was connected with the external pacemaker, serving as the cathode (Fig 1). As an anodal conductor, we placed a paediatric adhesive cutaneous defibrillation patch (DP-702 M Nikman™, Unomedical, Stonehouse, Great Britain) on the left thorax and connected this using two attached ECG electrodes (Ambu® Blue Sensor SP, Bad Nauheim, Germany) and a self-fabricated cable to the corresponding channel of the external pacemaker (Fig 2). The testing procedure was similar to that used for the bipolar mode. After switching the cables within the same channel, the second unipolar configuration was tested; this resulted in two unipolar values – a “worse” and a “better” value – and one corresponding bipolar value for each measurement. We also tested for inadvertent phrenic stimulation by increasing the output to the maximum levels. For statistical analysis, we used the Wilcoxon signed-rank test. Numeric data are expressed as mean values with standard deviations and ranges.
An external pacer (Pace 300, Osypka GmbH) with an atrial unipolar and ventricular bipolar configuration (example). Thus, for the atrium, only one pole of the bipolar electrode (white plug) is connected to the atrial channels as a cathode. A self-fabricated cable that is connected to a cutaneous patch electrode (see also Fig 2) serves as an anodal conductor. The ventricular lead is connected in a bipolar manner (both plugs in the ventricular channel).

For the unipolar configuration of the temporary pacing wires, a cutaneous defibrillation patch (DP-702 M Nikman™, Unomedical), placed on the left lateral thorax, serves as an anodal conductor. The patch is connected with two attached ECG electrodes (Ambu® Blue Sensor SP) and a self-fabricated cable to the corresponding channel of the external pacemaker.
Results
The patient diagnoses (n = 18) were as follows: 5 × ventricular septal defects, 1 × atrioventricular septal defect, 3 × d-transposition of the great arteries, 2 ×atrial ostium secundum defects, 1 × left ventricular outflow tract obstruction, 1 × partial anomalous venous drainage, 1 × total anomalous venous drainage, 1 × truncus arteriosus communis, 1 × pulmonary atresia with an intact ventricular septum, 1 × pulmonary atresia with a ventricular septal defect, and 1 × double outlet right ventricle. Of the patients, 16 underwent corrective and two patients underwent palliative surgery. The average cardiopulmonary bypass time was 70 ± 29 (32–123) minutes. The mean patient age was 9.2 ± 13.9 (1.7–51) months and weight was 6.3 ± 3.8 (3–17.3) kg. Among the patients, eight (44%) were on mild inotropic support (epinephrine maximum 0.05 mcg/kg/minute), 6 (33%) received norepinephrine (maximum dose 0.05 mcg/kg/minute), and 13 (72%) received a medication with milrinone (0.35 mcg/kg/minute).
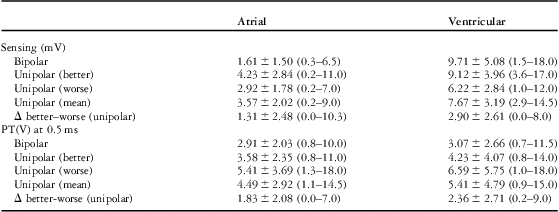
The testing was performed 4.5 ± 2.5 hours after the end of cardiopulmonary bypass. At the time of testing, all patients had a normal sinus rhythm with intact atrioventricular conduction (AV time 100 ± 15 ms). For comparison, the “better” and the “worse” of the two unipolar values and the arithmetic mean from both parameters were matched with the reference value for the bipolar configuration in each patient. The results are summarised in Table 1.
Testing values of the bipolar and unipolar modes in comparison, expressed as mean values with standard deviation and range.

The mean unipolar configuration is a virtual number, generated as the arithmetic mean between the better and the worse values. The difference (Δ) between the better and the worse unipolar configurations illustrates the variation of the unipolar values in the individual patient
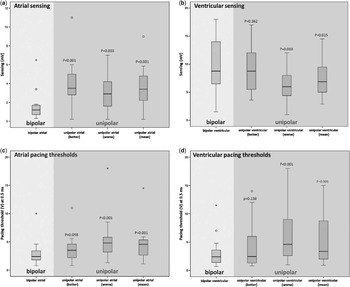
Figure 3a–d summarises the comparison of bipolar versus unipolar configurations using the Wilcoxon signed-rank test. The atrial sensing turned out to be significantly better in both unipolar configurations compared with the bipolar mode (p < 0.001 and p < 0.003; Fig 3a). The ventricular unipolar sensing did not differ significantly in the “better” of both possible configurations compared with the bipolar values (p = 0.362, Fig 3b). The unipolar pacing thresholds for the atrium (Fig 3c) and the ventricle (Fig 3d) tended to be slightly worse, although, again, the “better” unipolar configuration did not differ significantly from the bipolar measurements (atrial: p = 0.058, Fig 3c; ventricular: p = 0.138, Fig 3d). The pacing thresholds in the “worse” unipolar configuration were significantly higher than those in the bipolar configuration but were still within an acceptable range for effective pacing (Table 1 and Fig 3c and d). Therefore, we did not observe any exit block or undersensing, either in the unipolar or in the bipolar configurations. In three patients, phrenic nerve stimulation was present with high unipolar output values; however, pacing was still possible, as this occurred with ∼2.2-fold higher values than the effective pacing threshold. Skeletal muscle stimulation of the chest wall was not observed in any case, even with the highest testing output (18 V at 0.5 ms impulse width).
( a–d ) Comparison of bipolar and unipolar testing values using the Wilcoxon signed-rank test (boxplots with median and 25th/75th percentiles).

Discussion
Placement of temporary epicardial pacing wires is a common and accepted routine practice in surgery for congenital heart disease.Reference Batra and Balaji 1 At present, most institutions prefer bipolar electrodes – usually two wires implanted with a distance of 1–2 cm in between – as they have proved to be more reliable and have lower pacing thresholds and higher longevity compared with unipolar ones.Reference Batra and Balaji 1 – Reference Yiu, Tansley and Pepper 3 Deterioration of the wire function within 2–4 days is a common problem; early failure due to wire fracture or dislocation has also been described.Reference Elmi, Tullo and Khalighi 4 Owing to our institutional experience with failing temporary pacing wires in pacemaker-dependent patients with congenital heart disease, we sought for a rescue procedure suitable for this rare occasion. According to our clinical experience with permanent bipolar epicardial electrodes, for example, Model 4968 (Minneapolis, Minnesota, United States of America), Medtronic which, similar to bipolar temporary pacing wires, have a separated anodal and cathodal conductor on the epicardial surface, there is often a “better” and a “worse” electrode limb. In case a of fracture of the conductor of the bipolar epicardial leads, restoration of lead function using the second intact conductor has been described.Reference Rusanov and Spotnitz 5
Therefore, we report an easy and reliable method to apply unipolar pacing using one of the two conductors of a pair of bipolar pacing wires as an anode and a cutaneous patch electrode customised from the standard intensive care unit equipment as a cathode. The feasibility of the suggested unipolar setting was successfully tested in a series of patients undergoing surgery for congenital heart disease. We limited the maximum patient weight to 20 kg, as in this group, alternative methods for temporary pacing in case of epicardial pacing failure are extremely problematic. Temporary transvenous pacing may not be applicable because of the patient's size or lack of venous access, especially in univentricular palliation. Although transoesophageal pacing may be possible, even in neonates,Reference Paul, Luhmer, Wilken and Kallfelz 6 , Reference Hessling, Brockmeier and Ulmer 7 it only offers an atrial pacing option, requires a relatively high pacing output,Reference Hessling, Brockmeier and Ulmer 7 and has an increased risk for oesophageal trauma in the long term.Reference Kohler, Zink, Scharf and Koch 8 Transcutaneous pacing, despite its immediate availability in the intensive care unit, can only be used to initiate asynchronous ventricular pacing for a relatively short period of time. As the patients feel extremely uncomfortable and high capture energies are required, transcutaneous pacing is generally not recommended for periods of over 24 hours.Reference Knilians 9 The use of external pacemakers with a high voltage output and variable impulse width, for example, oesophageal stimulators such as the Pace 50E, Osypka, Rheinfelden, Germany, could be helpful but might be associated with similar patient discomfort and do not allow sequential pacing. Newer techniques such as a transcutaneous ultrasound to stimulate the heart are under investigationReference Lee, Lau and Tse 10 but have not yet been introduced clinically. Considering all this, epicardial temporary pacing wires remain the gold standard in post-operative pacing after congenital heart disease repair.Reference Batra and Balaji 1
The clinical relevance behind this is the relatively high incidence of post-operative arrhythmia after congenital heart disease surgery. Patients with sinus node dysfunction, junctional ectopic tachycardia, supraventricular tachycardia – AV nodal re-entry, atrioventricular re-entry, flutter, and sinus node re-entry tachycardia – and atrioventricular block may all benefit from therapy with temporary pacing wires.Reference Batra and Balaji 1 , Reference Valsangiacomo, Schmid and Schupbach 11 , Reference Rekawek, Kansy and Miszczak-Knecht 12 Our testing results suggest that this therapeutic option can be maintained with comparable outcomes using unipolar configured bipolar temporary pacing wires. Although the worse unipolar pacing thresholds were significantly higher than their bipolar reference values, the difference was clinically not relevant, as the absolute values (5.4 V for the atrium and 6.6 V for the ventricle with a pulse duration of 0.5 ms) were still within an acceptable range for the modern temporary pacemaker output (maximum up to 25 V at 0.5 ms). Only one unipolar configured electrode showed a near-exit block with the “worse” unipolar cable (pacing threshold 18 V at 0.5 ms), but even in this case, the “better” unipolar’ conductor did not differ as much from the bipolar value (11 V at 0.5 ms versus 8 V at 0.5 ms). Therefore, our findings might be very helpful in pacemaker-dependent patients: as soon as the function of the bipolar temporary pacing wires worsens or even starts to fail in the early post-operative setting, unipolar conversion should be considered. Supposing that only one of the two bipolar cables is affected, for example, by mechanical alteration during sternal closure, the option to use the alternative, assumingly intact, cable in the unipolar manner still remains. We observed a low incidence of inadvertent phrenic nerve stimulation with unipolar atrial stimulation, as a result of the different electrical circuit; as this occurred at a threshold over twice as high as the effective pacing threshold, it should not be of clinical relevance. An approach to circumvent this problem would be to change the position of the anodal patch electrode. Subcutaneous placement of a “surgical” pacemaker wire could also serve as an alternative for our relatively large self-customised indifferent electrode; however, because of its invasiveness, this setting was not tested.
Interestingly, the unipolar atrial sensing was even better than its bipolar counterpart. Sensing signals of temporary pacing wires are known to deteriorate significantly earlier than capture thresholds, usually on the second day.Reference Elmi, Tullo and Khalighi 4 Therefore, in case of low or borderline intrinsic atrial signals, unipolar sensing may be considered to maintain an AV synchronous demand pacing mode and thus avoid a fixed pacing rate stimulation. This is of clinical importance as a disturbance of the normal atrioventricular synchrony and a dyssynchronous ventricular contraction may be deleterious in patients with congenital heart disease.Reference Rekawek, Kansy and Miszczak-Knecht 12 – Reference Ceresnak, Pass and Starc 14 Thus, individually optimised temporary dual-chamber pacing in patients after surgery for congenital heart disease can significantly improve the haemodynamics, as measured by a higher systolic arterial blood pressure and lower atrial pressure as a result of synchronous ventricular contraction.Reference Rekawek, Kansy and Miszczak-Knecht 12 – Reference Ceresnak, Pass and Starc 14
Study limitations
This work is subject to important limitations. We did not evaluate the proposed unipolar rescue procedure in the real situation of failure of bipolar temporary pacing wires. Therefore, it remains speculative whether the recommended bailout procedure will always deliver positive results. If both wires become dysfunctional because of mechanical dislocation or generalised myocardial dysfunction, unipolar pacing may also not be successful. Another constraint concerns the fact that the testing was solely performed on the operative day in each individual patient. Therefore, we cannot predict the behaviour of the suggested unipolar mode during a typical post-operative course. We suppose that there is a high likelihood that the functional deterioration in the unipolar mode is similar to that of the bipolar mode.Reference Elmi, Tullo and Khalighi 4 To address this issue, testing of the unipolar in comparison with the bipolar mode immediately before wire removal should be considered in future investigations. As we only tested neonates and infants, we cannot predict whether the method is equally applicable in older and bigger congenital heart disease patients. It might well be that unipolar testing parameters are worse in this group, as unipolar capture and sensing may be impaired because of higher transcutaneous and transthoracic impedance.
Conclusion
The study results confirm that a customised unipolar stimulation mode using standard bipolar temporary pacing wires is highly effective in neonates and infants after cardiac surgery for congenital heart disease. In the case of failure of the bipolar mode, unipolar conversion should always be considered, especially in patients in whom pacing or diagnostic evaluation using temporary electrodes is mandatory.
Acknowledgements
The authors would like to thank Julia Stein for calculating the statistics and Anne Gale (ELS, Editor in the Lifesciences) for editorial assistance.