Pulmonary arterial hypertension (PAH), one of the malignant pulmonary vascular diseases, is featured by pulmonary arterial vascular remodelling. The progressively increased resistance of pulmonary vessels will result in death and failure of the right heart. Reference Humbert, Morrell and Archer1 PAH in children can be diagnosed at any age stage. Reference Rosenzweig, Abman and Adatia2 In neonates, infants, and older children, PAH can manifest as heritable (HPAH) and idiopathic (IPAH); alternatively, it is associated with other conditions (APAH), including connective tissue disease or congenital heart disease. Reference Humbert and Trembath3 Although the clinical manifestations vary depending on different aetiologies, the histopathological changes are similar in children and adults. Reference D’Alonzo, Barst and Ayres4 Based on the identified mechanisms, three target therapy classes, namely, phosphodiesterase type-5 inhibitors (tadalafil and sildenafil), endothelin receptor antagonist (ambrisentan and bosentan), and prostanoids (treprostinil, epoprostenol, beraprost and iloprost) are utilised to treat paediatric PAH. Specifically, the phosphodiesterase type-5 (PDE5) inhibitors can improve the pulmonary circulation through enhancing the NO/cyclic guanosine phosphate (cGMP) signaling pathway, relaxing the pulmonary arterial smooth muscles, dilating the pulmonary arteries, reducing the pulmonary arterial pressure, enhancing the right ventricular myocardial contractility, improving the pulmonary vascular remodelling, and suppressing the proliferation of pulmonary vascular smooth muscle cells. PDE5 inhibitors, such as sildenafil, have long been considered as safe and effective. A few studies show that sildenafil treatment at a high dose can increase the risk of mortality, whereas a low-dose treatment appeared to be ineffective. Reference Barst, Ivy and Gaitan5 Additionally, according to the US Food and Drug Administration (FDA), sildenafil should not be prescribed for PAH children. However, the European Medicines Agency has approved the use of sildenafil to treat PAH children at the age of 1–17 years. Reference Hansmann, Apitz and Abdul-Khaliq6 Besides, in the American Thoracic Society and American Heart Association guidelines, sidenafil is still recommended to treat paediatric PAH. Reference Abman, Hansmann and Archer7
Given these uncertainties, the current meta-analysis and systematic review was carried out, aiming to address the safety and effect of sildenafil on treating paediatric PAH.
Methods
Information sources as well as the search strategy
The following data sources were retrieved, namely, the Cochran Library database (Cochran Central Register of Controlled Trials), Medline, and EMBASE, using related medical subject headings and text words, including “pulmonary hypertension”, “child”, “children”, “paediatric”, “sildenafil citrate”, “sildenafil”, “revatio”, “viagra”, “phosphodiesterase 5 inhibitors”, “controlled clinical trial”, and “randomized controlled trial”. A final search was performed in the first week of May, 2019. To ensure a comprehensive literature search, the bibliography of the articles included was also checked.
Study selection and outcome estimation
The randomised controlled trials (RCTs) inclusion criteria were as follows: (i) studies in which pulmonary artery pressure (PAP) or mortality rate during follow-up was measured as the major effect of ≥ 1 trial intervention; and (ii) studies that recruited patients aged <18 years old. Eligible studies were enrolled regardless of the aetiology. Trials would be eliminated if they did not provide results from the outcomes selected.
The primary outcomes were the mortality rate during follow-up, together with the alternation of mean PAP (mPAP). The secondary outcomes included the mechanical ventilation time, length of hospital stay, length of ICU stay, the need for inotropic support, as well as pulmonary hypertensive crisis. Typically, the haemodynamic, clinical, and survival outcomes were all involved.
Data collection and risk of bias
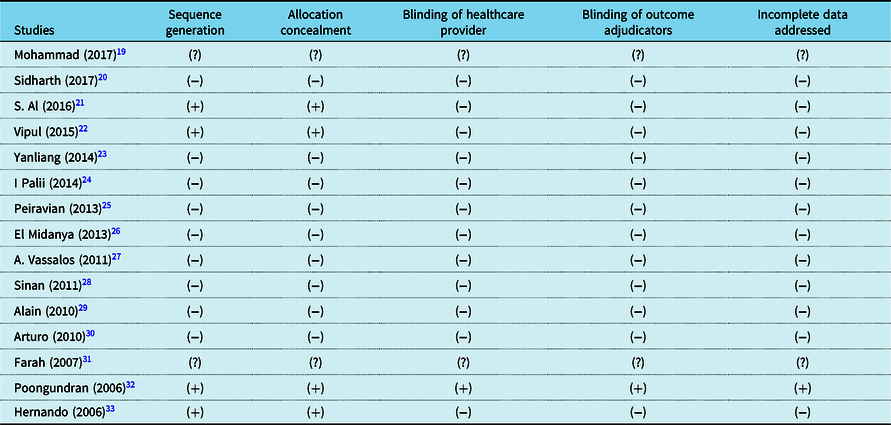
The retrieval results had been completed using the reference-managing software (EndNote). The STATA was adopted for statistical analysis. The analysis decision was determined beforehand. Abstracts/titles, as well as the full texts had been selected and data were extracted using the standard spreadsheet. The extracted data included study characteristics (namely, allocation concealment, sequence production, blinding of outcome adjudicators and healthcare provider, as well as insufficient information addressed); baseline patient characteristics (age, weight, mPAP, patients included and drug dose), and outcome events. Any disagreement between the reviewers was resolved by discussion. Full texts of the selected studies were searched by one reviewer at least at the time of abstract and title screening. Moreover, we contacted the corresponding and/or the first author for the initial publication to ask for the missing information. We assessed all potential sources of bias and defined the low, high, as well as ambiguous bias risk in all five areas (Table 2). Differences were settled down by reaching a consensus or negotiation with the third reviewer.
Result synthesis as well as additional analyses
One of our primary outcome measures was the relative risk (RR) together with the corresponding 95% confidence intervals (CIs) regarding the mortality. A standard mean difference (SMD) together with the related 95% CI would be computed to examine the change in PAP. Additionally, the Mantel–Haenszel random-effects model was used to carry out a meta-analysis, so as to acquire the pooled results. The I2 statistics and Cochran’s Q were utilised to estimate the heterogeneity statistically. The fixed-effects model would be utilised to compute the RR together with 95% CI in the presence of significant heterogeneity. Reference Higgins, Thompson and Deeks8 The priori hypotheses to explain heterogeneity were the different dosages of sildenafil, and study quality (namely, the bias risk). Subgroup analysis was carried out on the basis of those hypotheses in the presence of moderate heterogeneity (I2 > 30%). In order to evaluate the bias of publication, the funnel plot analysis and Egger’s linear regression test for each outcome were performed.
Results
Retrieval results as well as study features
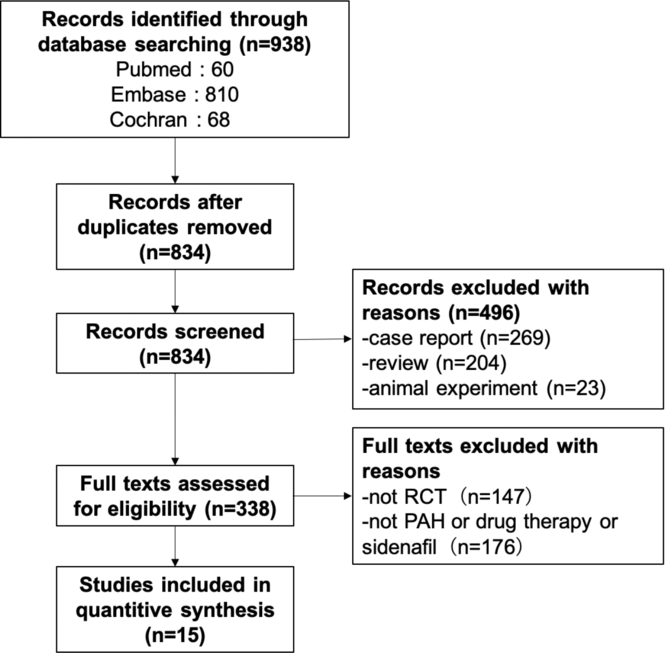
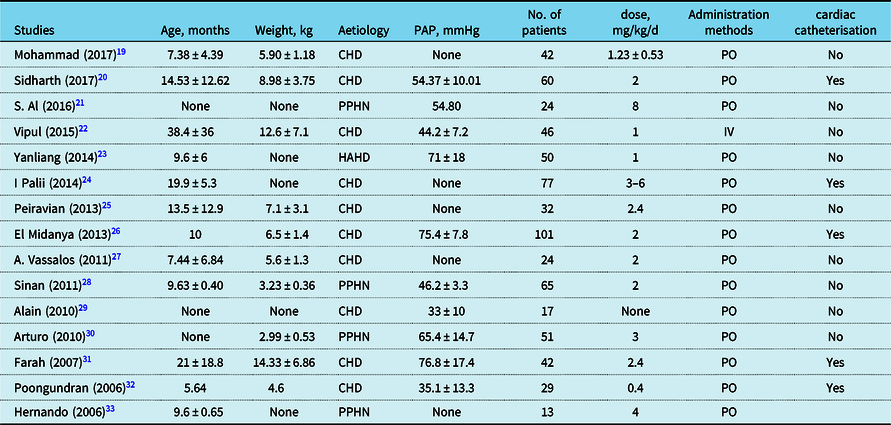
Nine-hundred and thirty-eight articles had been found based on the initial retrieval (Fig 1). No additional abstract or study was screened based on other sources. Three-hundred and thirty-eight of the 938 articles were enrolled to screen the full texts. At last, 15 studies involving 651 cases satisfied the inclusion criteria. Most of the articles were excluded due to the unavailability of the required data (Fig 1 and Table 1). Patients included in the study were those who had systolic PAP > 35 mmHg or mean PAP > 25 mmHg with high pulmonary vascular resistance. All studies have at least one area of elevated or unclear bias risk (Table 2). There were few data on the bias risk outside the published studies, irrespective of contacting the original authors.
Flowsheet of studies included and excluded.

Characteristics of studies included

“Age” refers to the average age of the experimental group; “Weight” refers to the average weight of the experimental group; “CHD” refers to the abbreviation for congenital heart disease; “PPHN” refers to the abbreviation for persistent pulmonary hypertension of the newborn; “HAHD” refers to the abbreviation for high altitude heart disease; “PAP” refers to the average pulmonary artery pressure of the experimental group; “No. of patients” refers to the number of patients met all conditions for inclusion; “Dose” refers to the dose of sildenafil.
Risk of bias of individual studies

“−” High risk of bias; “?” Unclear/not reported; “+” Low risk of bias.
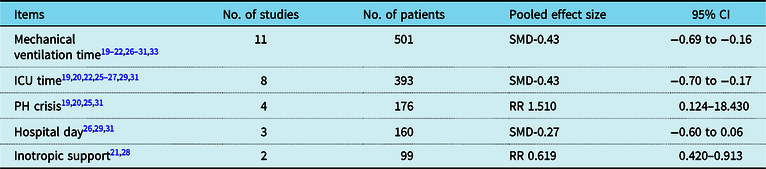
Summary of findings table

“No. of studies” refers to the number of studies met all conditions for inclusion; “No. of patients” refers to the number of patients met all conditions for inclusion; “CI” is a medical abbreviation for confidence interval; “SMD” is a medical abbreviation for standard mean difference; “Mechanical ventilation time” refers to the duration of mechanical ventilation; “ICU time” refers to length of stay in ICU; “PH crisis” refers to the incidence of pulmonary hypertensive crisis; “ Hospital day” refers to the length of hospitalisation; “Inotropic support” refers to the ratio requiring vasoactive drug support.
Primary outcomes
Effect on mortality of PAH children
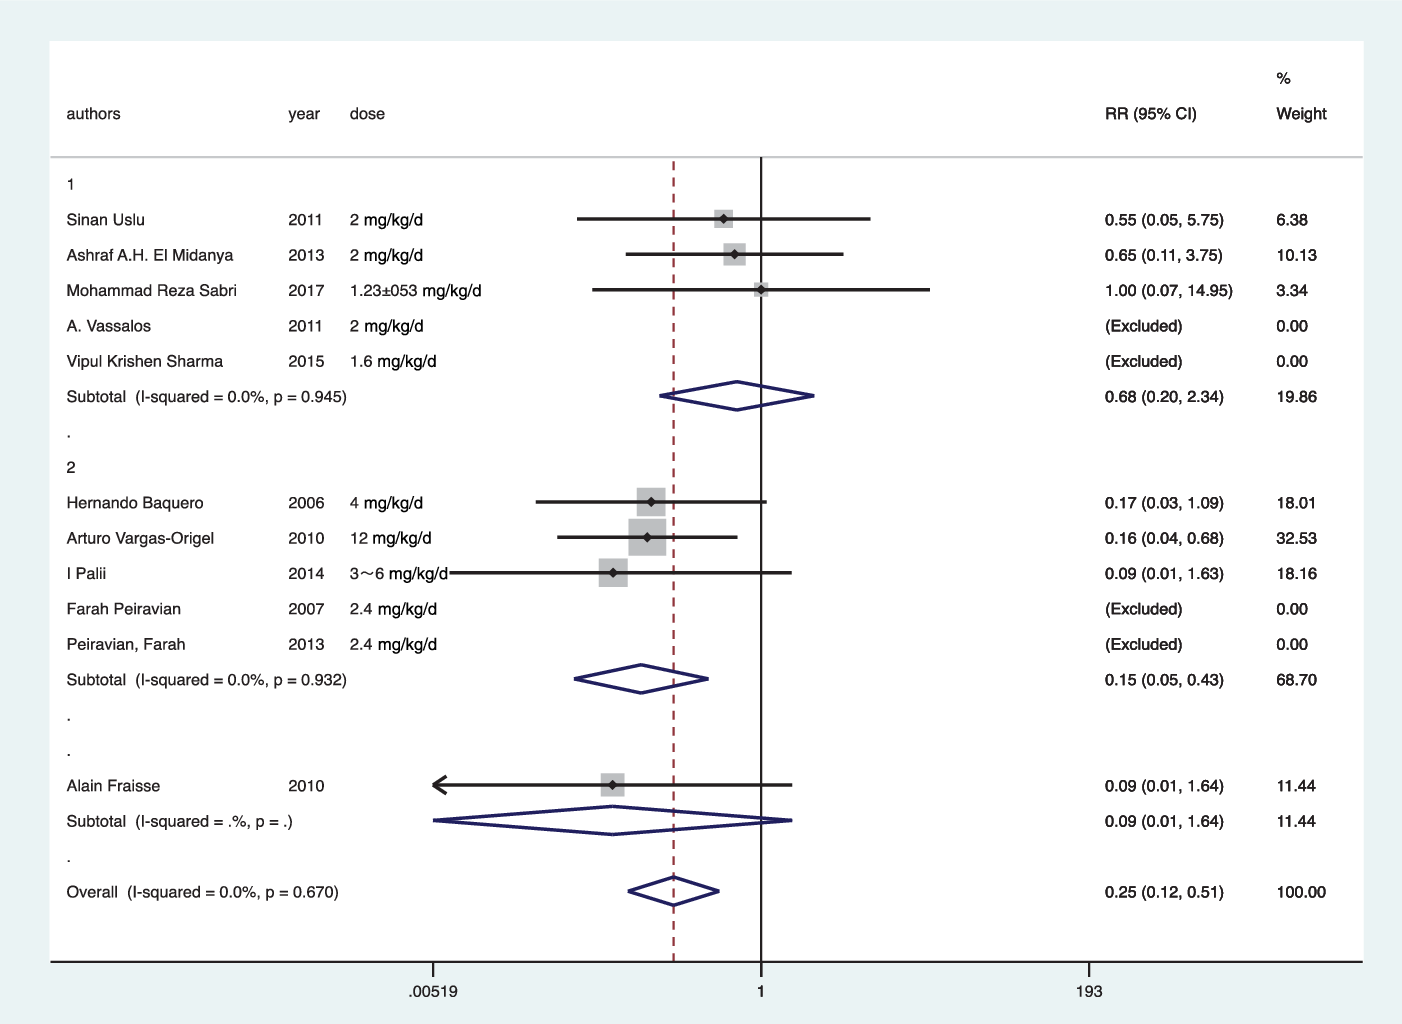
Information regarding the sildenafil treatment efficacy in the death events could be obtained from 11 publications, which included 510 patients and 33 events. Compared with control groups, the sildenafil group had significantly reduced deaths (RR = 0.25, 95% CI: 0.12–0.51; p < 0·0001, Fig 2). Besides, the overall risk estimate was in the range of 95% CI of every single study, with no evident heterogeneity evidence except for the occasionally expected variability (p = 0.670 upon Cochran’s Q test, I2 = 0%). Difference in the mortality of low-dose sildenafil group was not significant compared with the high-dose group (p = 0.152).
Mortality and relative risk in individual trials and pooled relative risk under a fixed-effect model. Notes: “Dose” refers to the dose of sildenafil; “CI” is a medical abbreviation for confidence interval; “RR” is a medical abbreviation for relative risk.

Secondary outcomes
Effect on duration of mechanical ventilation time
Mechanical ventilation time was reported by 11 studies that recruited 501 patients. The pooled estimate favoured that sildenafil reduced the duration of mechanical ventilation time (p < 0.0001, 95% CI: −0.69–0.16, SMD = −0.43, Table 3).
Effect on length of ICU stay
The length of ICU stay was assessed by 9 studies recruiting 393 patients. The pooled estimate favoured that sildenafil reduced the length of ICU stay (p < 0·0001, 95% CI −0.70–0.17, SMD = −0.43, Table 3).
Effect on pulmonary hypertensive crisis
The incidence of pulmonary hypertensive crisis was reported in 4 studies recruiting 176 patients. Difference in pulmonary hypertensive crisis incidence was of no statistical significance in sildenafil group compared with control group (p = 0.071, 95% CI: 0.124–18.43, RR 1.51, Table 3).
Effect on length of hospital day
The length of hospital stay was reported in 3 studies that involved 160 patients. Difference of length of hospital stay in sildenafil group was of no statistical significance compared with that in control group (p = 0.756, 95% CI: −0.60–0.06, SMD = −0.27, Table 3).
Effect on the need of inotropic support
The need of inotropic support was assessed by two studies. The pooled estimate favoured that sildenafil reduced the need of inotropic support (p = 0.016, 95% CI: 0.420–0.913, RR = 0.619, Table 3).
Discussion
Results of this meta-analysis suggested that sildenafil reduced the mortality of PAH patients. The risk of mortality showed no obvious difference between the low-dose and high-dose sildenafil subgroups. However, relative to control group, differences in mPAP, the incidence of pulmonary hypertensive crisis and length of hospital stay of PAH children were of no statistical significance in sildenafil group However, the pooled estimate favoured that sildenafil reduced the duration of mechanical ventilation time, length of ICU stay, and the need for inotropic support.
The pooled estimate regarding the mortality in PAH cases was significantly reduced in sildenafil group. Some studies have reported no deaths because of relatively short follow-up period. Our study showed that sildenafil reduced the deaths amongst PAH cases. But in Robyn J’s study, Reference Barst, Beghetti and Pulido9 treatments with high-dose sildenafil would increase the mortality risk relative to that of lower-dose sildenafil, which was not consistent with our results. Therefore, we further conducted subgroup analyses stratified based on different doses of sildenafil. The 10 studies were sequenced according to the sildenafil doses in the trial, which were then divided into high-dose and low-dose groups at the threshold dose of 2.4 mg/kg/d. We found that the risk of mortality did not differ between the low-dose and high-dose sildenafil groups. Consequently, we suggested that sildenafil reduced the mortality of PAH cases regardless of drug dose.
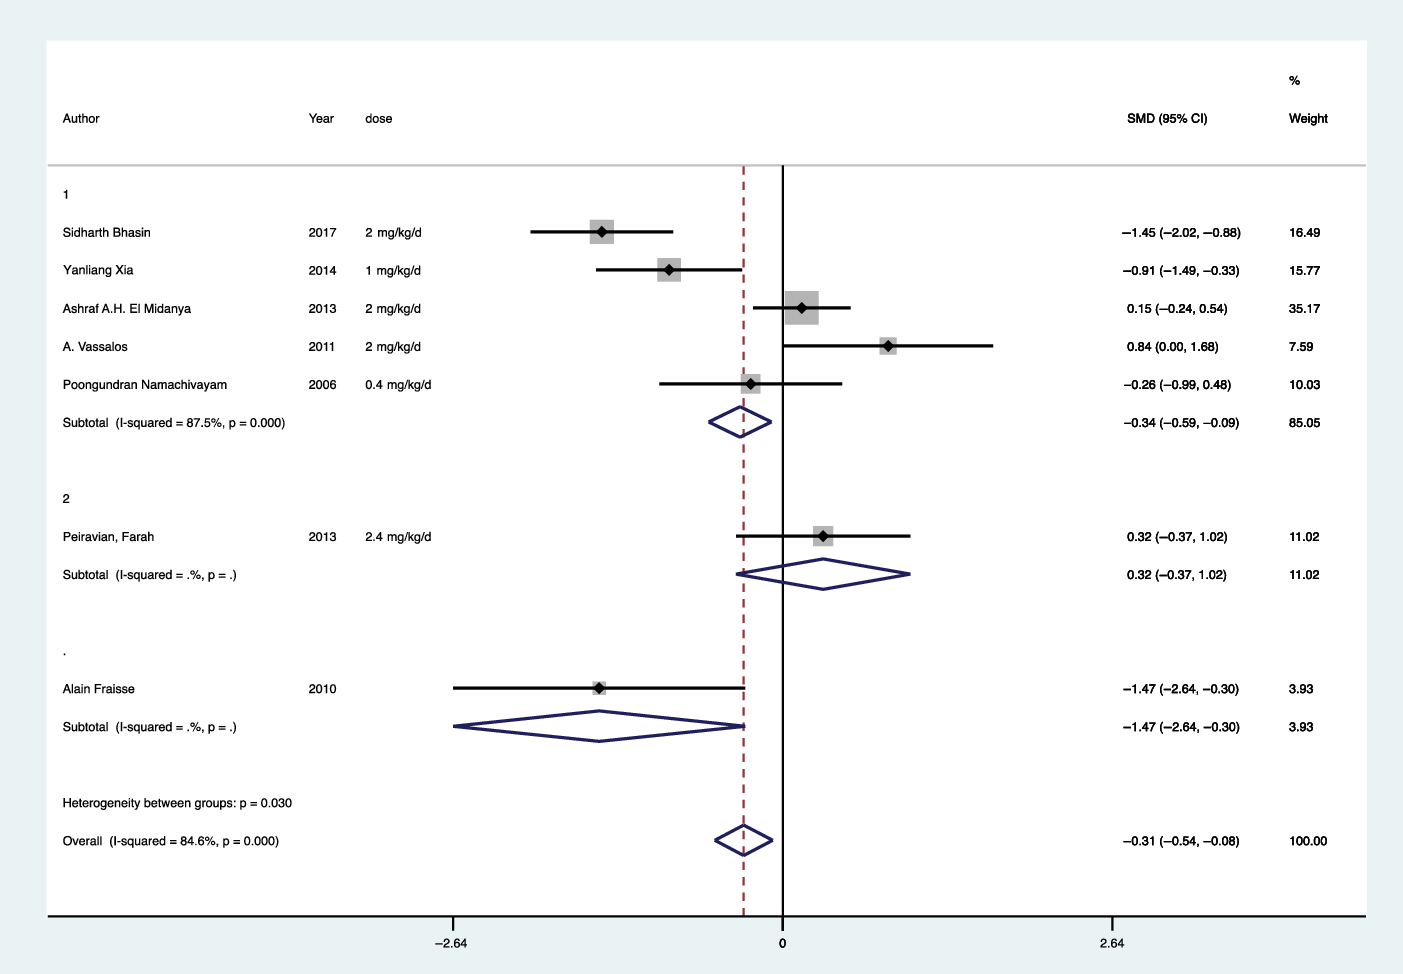
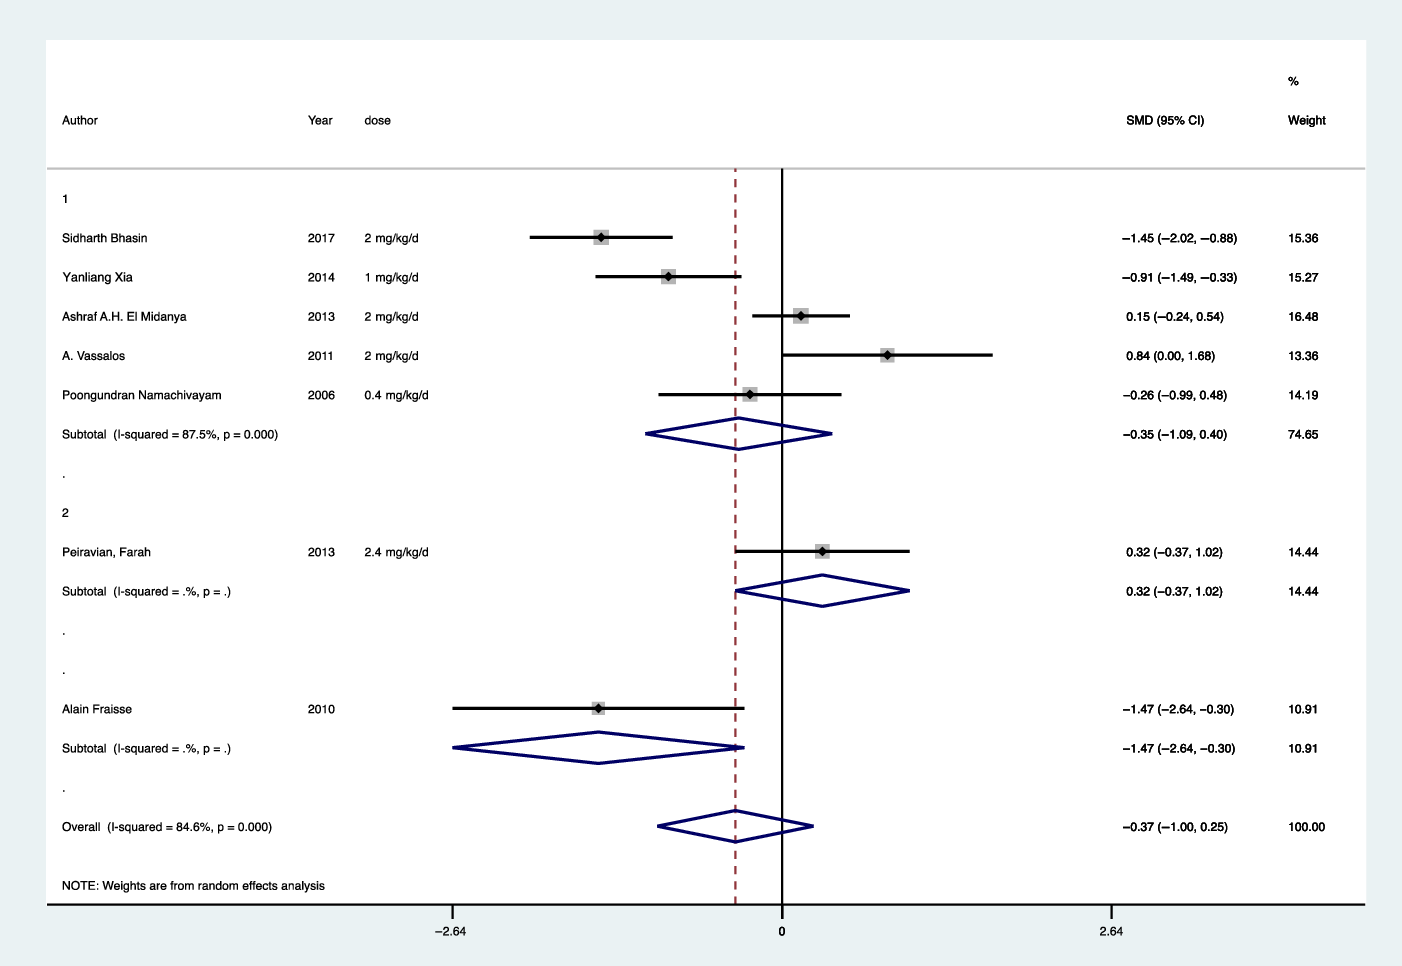
Sildenafil is ineffective in decreasing mPAP and the incidence rate of pulmonary hypertensive crisis. In this study, a fixed-effects model was used to obtain the SMD and 95% CI (Fig 3). According to our results, sildenafil reduced the incidence of PAH, but there was great heterogeneity. So we change it to a random-effects model (Fig 4). To search for the causes of the large heterogeneity, subgroup analyses were carried out on low- as well as high-dose group. According to the subgroup analysis results, different doses could not explain the heterogeneity. Sildenafil had been shown to reduce the incidence of PAH in all the included studies, and we believed that there was an excessive heterogeneity, which would not lead to negative results. Sildenafil, one of the selective PDE-5 inhibitors can potentially suppress NO effects in the downstream. NO can induce vasodilation as well as relaxation of the smooth muscle, which is achieved by the influence on the cyclic guanosine monophosphate (c-GMP) pathway. Reference Galiè, Ghofrani and Torbicki10 In Robyn J’s study, Reference Barst, Ivy and Gaitan11 the functional capacity, peak oxygen consumption, PVR, and mPAP levels were enhanced in high- and medium-dose groups relative to the placebo group, while a low dose would be ineffective. Nonetheless, in Carmine Dario Vizza’s study, Reference Vizza, Sastry and Safdar12 sildenafil at the dose of 5 mg for 3 times daily appeared to have similar clinical and haemodynamic effects as those at 20 mg for 3 times daily. As a result, the effects of different drug doses on the PAP remain uncertain, which should be further studied.
mPAP and standard mean difference in individual trials and pooled weighted mean difference under a fixed-effects model. Notes: “Dose” refers to the dose of sildenafil; “CI” is a medical abbreviation for confidence interval; “SMD” is a medical abbreviation for standard mean difference.

mPAP and standard mean difference in individual trials and pooled weighted mean difference under a random-effect model. Notes: “Dose” refers to the dose of sildenafil; “CI” is a medical abbreviation for confidence interval; “SMD” is a medical abbreviation for standard mean difference.

Basic treatment combined with sildenafil can shorten the mechanical ventilation time and reduce the incidences of ventilator-related diseases, such as ventilator-related pneumonia, barometric injury, difficulty in removing the ventilation machine, and bronchopulmonary dysplasia. In our meta-analysis, there was no difference in the length of hospital stay amongst studies reporting the related outcomes. Pulmonary hypertension is often associated with heart failure, respiratory failure, and other serious diseases. Reference Hansmann13 We considered that the simple treatment of PAH cannot effectively shorten the length of hospital stay. In Bai Y’s study, Reference Bai, Sun and Hu14 the combined therapy mitigated clinical worsening, increased the 6-minute-walk distance, decreased the mPAP, resistance of pulmonary vessel, and right atrial pressure. As a result, comprehensive treatment may be a better choice for PAH patients. Thus, a comprehensive treatment involving inhaled iloprost, sildenafil, and bosentan can potentially enhance patient survival while decreasing the necessity of lung transplantation amongst severe PAH adult patients. Reference Hoeper, Markevych and Spiekerkoetter15 When treating PAH, high systemic circulation pressure is often required to ensure the blood supply of all organs. Sildenafil is utilised to lower the pulmonary circulatory pressure and thus to decrease the need for vasoactive drug support. Although the efficacy of sildenafil in reducing pulmonary artery pressure in our study is uncertain, we believe that greater heterogeneity was one of the reasons for this result.
The favourable tolerance of sildenafil in treating PAH has been reported in different studies, and less severe adverse reactions are reported. However, some studies have reported that the common adverse reactions include gastrointestinal reactions like nausea, abdominal discomfort, dyspepsia, nervous system reactions (including headache, dizziness, and insomnia). Reference Roldan, Deiros and Romero16 Consequently, future studies should pay more attention to monitor the long-term safety due to the relatively short follow-up period.
Some limitations should be noted in this meta-analysis. First, our meta-analysis adopted relatively broad inclusion criteria, which inevitably gave rise to the heterogeneity problems. In spite of the insufficient statistical heterogeneity detectable in the risk of mortality, these studies focused on different aetiologies, delivery patterns, and patient populations. Differences in aetiologies results in different outcomes. We selected articles according to inclusion and exclusion criteria. A total of 15 studies were included. In gathering basic information from these studies, we found that almost all aetiologies were associated with congenital heart disease and persistent pulmonary hypertension in newborns. We attempted a subgroup analysis of different aetiologies. But unfortunately, congenital heart disease was the cause of pulmonary hypertension in all 11 articles reporting mortality and in 7 of the 8 articles examining the effect of sildenafil on pulmonary hypertension. Thus, from a clinical point of view, these trials might be considered as heterogeneous. Second, the follow-up periods ranged from 36 h to 12 months. We regretted the short follow-up time of some studies, which often analysed neonates with persistent pulmonary hypertension. Due to the disease-specific nature of persistent pulmonary hypertension in newborns, these studies were followed for shorter periods of time than for other causes of pulmonary hypertension. In studies with short follow-up period, not all results were detected clinically upon the completion of follow-up, which might lead to certain bias. Significant heterogeneity was detected in this meta-analysis, which was related to the potential effect of follow-up period on the results. We could draw the conclusion from Ploegstra’s study Reference Ploegstra and Berger17 and Galiè N’s study Reference Galiè, Humbert and Vachiery18 that WHO FC, NT-proBNP/BNP, mRAP, PVRI, cardiac index, and acute vasodilator response are effective prognostic factors to evaluate long-term outcomes. Limited by lack of the original data, we can’t have a comprehensive analysis. At the same time, we find that sidenafil was administered intravenously in one mentioned paper, Reference Sharma, Joshi and Joshi22 while in other papers, oral administration was used. Further research is needed to explore the therapeutic efficacy of different kinds of administration of sildenafil.
In conclusion, sildenafil has certain advantages in lowering the mortality rate of PAH patients and the effect is independent of the drug dose. Haemodynamic outcomes and other clinical outcomes of paediatric PAH treated with sidenafil are still controversial. Rigorous and large RCTs are warranted.
Acknowledgement
None.
Financial support
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Conflicts of interest
None.
Ethical standards
The ethics committee of Peking University First Hospital granted an exemption from requiring ethics approval.