Introduction
It is not uncommon to encounter stridor soon after extubation of a patient who has been intubated with an endotracheal tube for mechanically assisted ventilation, most commonly due to inflammation or ischaemia of the laryngotracheal mucosa.Reference Zias, Chroneou, Tabba, Gonzalez, Gray and Lamb1–Reference Beebe3 Occasionally, ulceration occurs, especially in the subglottis and most commonly in the region of the cervicotracheaReference Zias, Chroneou, Tabba, Gonzalez, Gray and Lamb1, Reference Cardillo, Carbone, Carleo, Batzella, Jacono and Lucantoni2 (due to traumatic intubation or endotracheal cuff pressure necrosis, now rare due to the advent of the high-volume, low-pressure cuff). The resultant granulation tissue and scar formation can also cause stridor if the tracheal lumen is sufficiently compromised. These patients may be quite well in the immediate post-extubation period but may gradually develop stridor due to progressive thickening of the scar tissue.
Tracheal stenosis is generally due to circumferential (intraluminal) granulation tissue thickening and scarring, with the onset of stridor and respiratory embarrassment when sufficient narrowing of the lumen has occurred. Stridor due to true tracheal stenosis does not vary much in its severity or audibility with changes in position (i.e. whether the patient is supine, prone or upright), because it is due to a ring of tissue formed within the tracheal lumen.
However, if the stridor is due to a tracheal flap on the posterior wall, supine positioning will cause the flap to fall back, partially relieving the patient's respiratory distress, while prone positioning will cause the flap to fall forward, worsening respiratory distress. In the upright posture, however, the process of respiration (especially when forceful) will cause the flap to act as a one-way valve, allowing expired air to pass up and out easily but trapping inspired air and thus narrowing the tracheal lumen during inspiration.
Herewith, we present a patient with progressive stridor which developed over a period of several days and which manifested as an airway emergency necessitating emergency tracheostomy. This was due to an earlier undiagnosed and unsuspected tracheal mucosal tear which developed into a mucosal flap, which acted as a one-way valve preventing inspired air from reaching the lower airway and lungs.
In this rare case, the tracheal mucosal tear was caused by multiple intubation attempts during an unremitting episode of status epilepticus in our hospital's accident and emergency centre. The patient was subsequently admitted to the intensive care unit for respiratory support while her epileptic seizures were brought under control.
Case report
A 15-year-old girl was admitted to the accident and emergency centre in acute respiratory distress, which had initially developed gradually (as mild stridor) following endotracheal tube extubation a little over a fortnight earlier.
During this earlier presentation, the patient had been intubated to prevent complications of uncontrolled status epilepticus; after which she had been placed on ventilator support in the intensive care unit while waiting for the seizures to abate. She had been ‘ventilated’ for five days. When her condition had been deemed stable and the fitting episodes were under control, the patient had been gradually taken off the ventilator, with the assistance of intravenous dexamethasone given pre- and post-extubation.
The patient had been discharged home soon afterwards, and had appeared well with no signs of stridor. However, three days later at home, her mother had detected a slight wheeze coming from the patient's throat whenever she took a deep breath. The patient had also developed shortness of breath on the slightest exertion. The wheeze had soon become more audible, and the patient's breathing effort had become more pronounced.
In the ensuing few days, the patient's breathing efforts had become more and more distressing. Consequently, she presented to the ENT clinic approximately a week later, due to intolerable respiratory strain. At this time, her stridor was very loud, she was unable to speak more than three short, quick syllables before gasping for breath, and her use of her accessory respiratory muscles to breathe was apparent to all; furthermore, her wide-eyed, anxious gaze, flaring nostrils, prominent sternocleidomastoid muscles, and heaving chest and shoulder movements were all indicative of severe respiratory distress and probable imminent respiratory failure.
A quick flexible endoscopic examination was conducted, which revealed an apparently stenosed trachea below the vocal folds (at this stage, she was classified as having Cotton's grade two tracheal stenosis); however, the extent and exact site of involvement could not yet be determined.
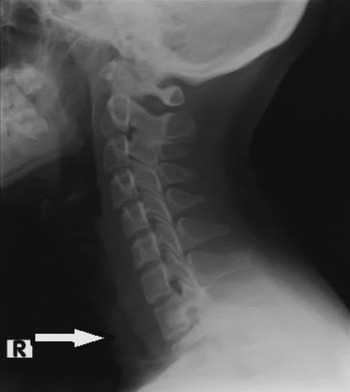
Lateral neck radiographs appeared to indicate the presence of a narrowed trachea from the level of the seventh cervical vertebra downwards (Figure 1), while the lower extent could not be visualised. The chest X-ray was unremarkable.
Lateral neck X-ray showing the site of the tracheal narrowing (arrow). A soft tissue shadow is seen within the lumen of the airway. R = right

In view of the patient's obvious distress, she and her parents (as she was under-aged) were counselled and advised that she should undergo urgent tracheostomy to relieve her effortful breathing and to prevent the imminent onset of respiratory failure. However, despite fully explaining the risks and complications which may arise if such treatment were delayed or deferred for too long, the patient and her parents were adamant in refusing any immediate intervention, as they wanted time to consider other options and to seek other opinions.
The very same night, the patient returned in acute distress, with an oxygen saturation level of less than 50 per cent, visibly struggling to breathe. She was immediately taken to the operating theatre, where an emergency tracheostomy was performed under local anaesthesia. Subsequently, she was placed under general anaesthesia for endoscope-assisted direct laryngoscopic examination.
While being wheeled to the operating theatre, lying supine, the patient's stridor became less audible and her oxygen saturation stabilised to 98 per cent, albeit with the aid of a ventilation mask delivering 100 per cent oxygen. This was unusual as generally the opposite would be true, i.e. a patient in respiratory distress would prefer to sit upright, because lying supine would somewhat negate the action of the accessory respiratory muscles and thus leave the patient even more tachypnoeic and in worsening respiratory distress.
Intra-operatively, when the tracheotomy was performed no noticeable stenosis was seen, and the tracheostomy tube was passed into the trachea with ease. (A 7.0 mm Portex® cuffed tracheostomy tube was used, for fear of causing trauma to the stenosed segment and thus worsening any potential scar formation.) This easy intubation caused much surprise to the surgeon, as difficulty or resistance was anticipated, bearing in mind that an apparently stenosed segment was noted to extend down from the seventh cervical vertebra on the lateral neck X-ray.
Direct laryngoscopy, conducted when the patient was under general anaesthesia, was essentially normal, with no discernable stenosis.
In the event, due to the patient's struggles and restlessness during the procedure, as well as the anticipated difficulty of ventilation through an apparently narrowed airway, enthusiastic ‘bagging’ by the anaesthetist resulted in a pneumothorax. Chest drainage tubes were inserted, which were left in situ until the patient's lungs were fully re-expanded. She was then transferred to the intensive care unit for close monitoring.
Once the chest drains were removed, a flexible endoscopic examination was performed in the intensive care unit, both via the nose and threading through the tracheostomy tube. This did not show any stenosis. Due to the discrepancy between, on the one hand, the patient's respiratory distress and initial lateral neck X-ray appearance and, on the other, her negative rigid and flexible endoscopic findings, we were left to wonder if her respiratory distress was due to previously undetected lung pathology.
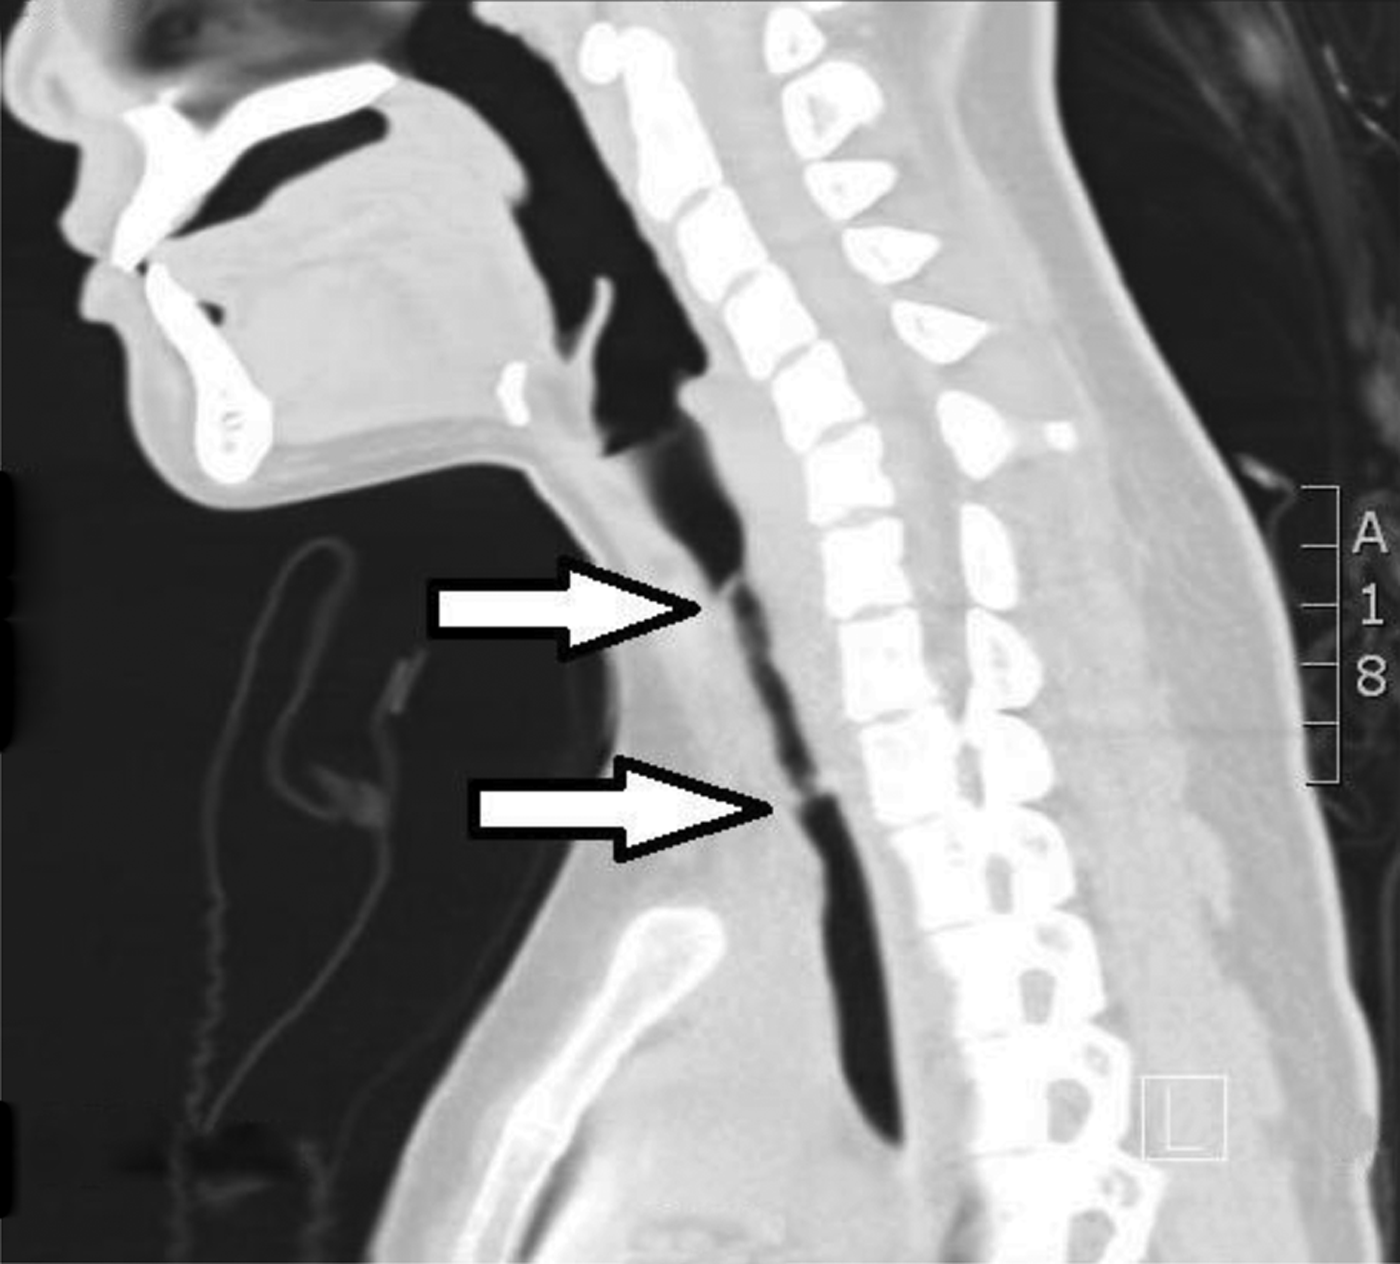
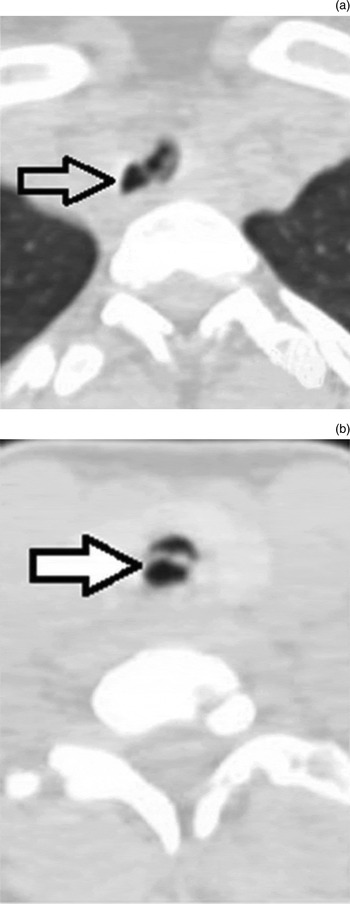
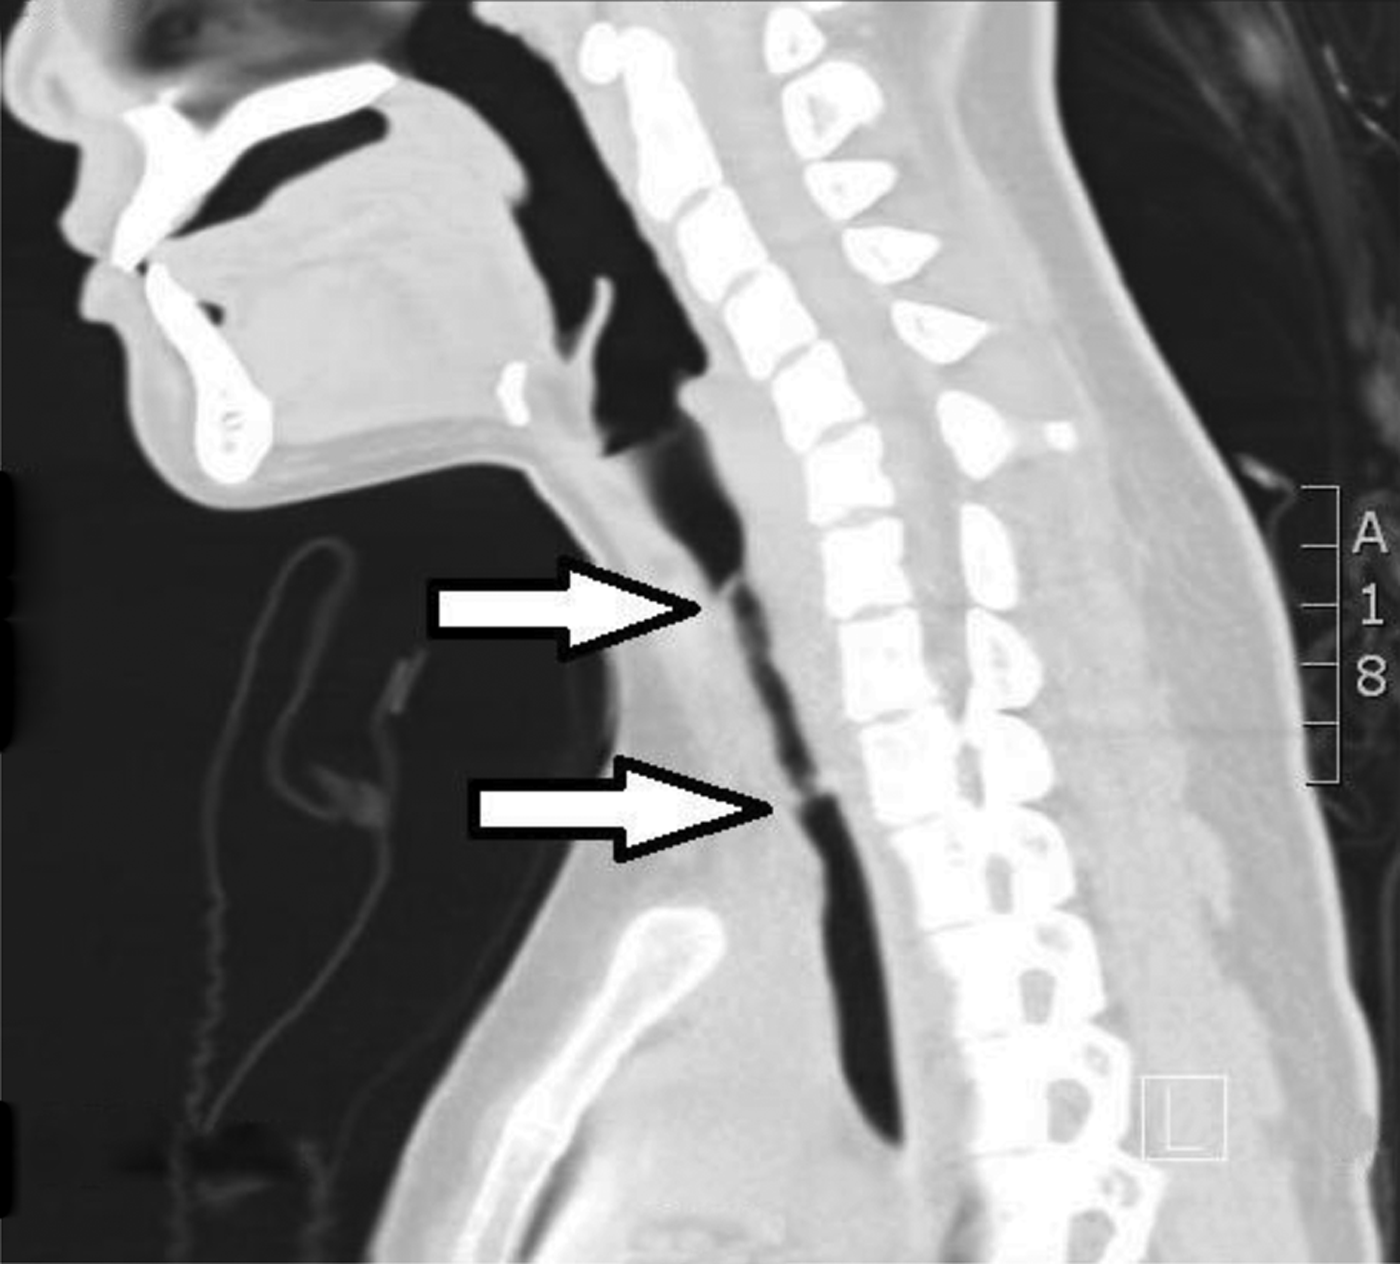
Once the patient was discharged from the intensive care unit, a computed tomography (CT) scan of the neck and thorax was performed. This revealed several interesting findings, but only when viewed with the ‘lung’ setting. It indicated tracheal narrowing of approximately 50 per cent, extending from the level of the seventh cervical to the second thoracic vertebrae (Figure 2). In the coronal reconstructed view, there were circumferential cuffs of tissue noted above and below the stenosed segment. Significantly, at the level of the seventh cervical vertebra, a ‘double lumen’ was seen in the axial view (Figure 3).
Sagittal computed tomography scan of the patient post-extubation. A narrowed segment (arrows) is seen from the level of the seventh cervical vertebra to the second thoracic vertebra, with a ‘double lumen’ seen at the proximal and distal ends. L = left
Axial computed tomography scan showing ‘double lumen’ (arrows) seen within the trachea at the level of (a) the seventh cervical vertebra and (b) the second thoracic vertebra, forming a flap and causing inspiratory stridor when the patient breathed.

There was no evidence of subcutaneous emphysema. The double lumen evident on the CT scan was the proximal end of the lacerated tracheal mucosa, which had been dissected (much like a dissecting aneurysm in an artery) along its submucosal plane and had formed a tissue flap which acted as a one-way valve. The patient's stridor had apparently been caused when the inspired air stream caused turbulence within the trachea when it was ‘reflected’ back up from the blind end of the dissection ‘pocket’: instead of passing down to the lower airway, the air travelled up towards the glottis. Hence, inspired air was redirected in the opposite direction, interrupting the usual lamellar flow and resulting in insufficient air passing into the respiratory system.
With the tracheostomy in place, bypassing the normal route of respiration, the tracheal flap fell back in place, allowing healing to begin.
The patient was subsequently weaned off her tracheostomy, after it was determined that the tracheal tear had adequately healed.
Discussion
Intubation injuries are not uncommon, even when the intubation is performed by a trained anaesthetist, especially in a disturbed patient. The resulting injuries can range from the minor, such as small lacerations on the lips, to the very serious and life-threatening, as illustrated in the presented case, even when all precautions are in place.Reference Beebe3
In the presented case, the patient had originally suffered from an attack of status epilepticus, which had continued unabated despite administration of the maximum safe dose of intravenous diazepam. At this stage the patient had been fitting violently, thus making intubation both essential, to prevent potentially fatal complications, and difficult and hazardous to patient and doctor.
Protection of the airway during a seizure attack remains the main concern of all medical personnel, and endotracheal tube intubation is the mainstay of airway management in unremitting status epilepticus. When attempting to intubate in such circumstances, trauma is almost always unavoidable. However, as illustrated in this case, traumatic intubation can become potentially life-threatening when a tracheal mucosa tear dissects along its submucosal plane during inspiration. This type of injury is uncommon, and to our knowledge has not previously been reported in any literature.
The most common, serious and potentially fatal outcome of traumatic intubation is a ruptured trachea, causing pneumomediastinum and subcutaneous emphysema. Reported risk factors include: female sex, over 50 years of age, emergency setting and gross over-inflation of the endotracheal cuff. Other probable risk factors are prolonged corticosteroid use, tracheomalacia, malpositioning of the endotracheal tube, use of the stylet to guide the endotracheal tube between the vocal folds, and excessive coughing.Reference Zias, Chroneou, Tabba, Gonzalez, Gray and Lamb1–Reference Chang, Chien, Hsu and Lai7
However, in our patient, although several of the risk factors mentioned above were present (e.g. emergency setting and stylet guidance of intubation), we are of the opinion that the tracheal mucosal flap was the result of an initial small tear in the wall of the trachea, which was progressively dissected along its submucosal plane during inspiration. This dissection was further facilitated by the increasing force and effort required for the patient to breathe.
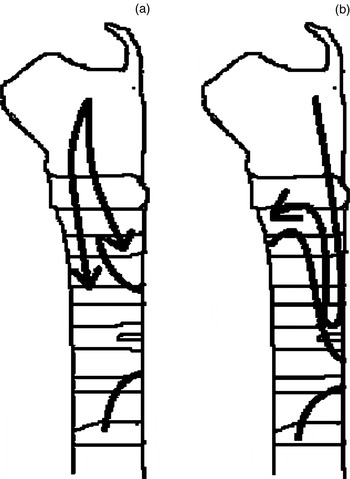
We postulate that the tear near the level of the seventh cervical vertebra was initially no more than a small section of tissue hanging down from the tracheal wall. This was why the patient had appeared well after she had been taken off respiratory support and extubated. However, with successive breaths this small section of tissue gradually grew into a flap as it was forced open further in a dissecting manner (Figure 4), akin to that of blood flow causing a dissecting aneurysm in a blood vessel. This also explains why the patient became progressively more stridulous over several days.
• The reported case had an iatrogenic tracheal mucosal tear causing post-extubation stridor
• Air flow dissected the mucosal tear, worsening the stridor and respiratory effort
• Emergency tracheostomy stented the airway and repositioned the flap, enabling healing
• Iatrogenic mucosal tear should be suspected where no evidence of tracheal stenosis is found
Schematic diagram showing the initial tracheal mucosal injury (a) caused by the tip of the endotracheal tube. Air flow dissected into the mucosal tear, which progressed to become a flap causing respiratory obstruction (b).

As the flap became larger, correspondingly the patient's tracheal lumen became progressively narrower, until the air passing down into the lower airway was no longer sufficient and the patient needed to increase her breathing effort. A vicious cycle thus developed: with each deep, forceful breath, the flap became larger and the tracheal lumen narrower, thus requiring even greater effort to draw air into the lungs.
An earlier CT scan may have been useful in this case, before the tracheostomy was performed. Because of the patient's effortful inspiration, the flap may have been much more clearly demonstrated as not only a double lumen but also, perhaps, a flailing piece of tissue moving in time with respiration.
The tracheostomy tube, with its initially inflated cuff, acted as a form of stent and helped to restore the mucosal flap back to its rightful position, aiding the healing process. The cuff was left inflated for several days, even after the patient was transferred from the intensive care unit to a general ward, in order to keep the mucosal flap in place until it had fully healed. This could have been confirmed by the passage of a flexible endoscope through the tracheostomy tube while the tube (with deflated cuff) was slowly and carefully withdrawn.
Conclusion
Iatrogenic laryngotracheal injuries are common and often unavoidable, especially when endotracheal tube insertion is done under unfavourable emergency conditions. Tracheal mucosal tears are rare and almost always undiagnosed, unless the tear is sufficiently large to lead to tracheal rupture, with dire consequences. However, a tracheal mucosal flap may be suspected when changes in patient position alter the nature and severity of the resultant stridor and/or respiratory distress.
In such cases, a tracheostomy tube with inflated cuff should be kept in place for an adequate period, in order to act as a stent and to help hold the flap in place while healing occurs.