





Introduction
Early identification of myocardial dysfunction in paediatric shock can significantly alter resuscitation strategies, yet timely access to comprehensive echocardiography can be limited or delayed.Reference Topjian, Raymond and Atkins1,Reference Weiss, Peters and Alhazzani2 Cardiac point-of-care ultrasound has emerged as a bedside tool to address this gap in shock, though paediatric data on clinical impact and bedside accuracy, particularly across the spectrum of systolic dysfunction, remain sparse.Reference Miller, Arichai and Gravel3–Reference Wilson, Maher, Sachdeva and Mills9
In association with severe acute respiratory syndrome coronavirus-2, children with multisystem inflammatory syndrome presented with broad variability of ventricular systolic function.10 The condition was frequently associated with rapidly progressive haemodynamic instability and cardiogenic shock.Reference Matsubara, Kauffman and Wang11,Reference Sanil, Misra and Safa12 In this high-prevalence model of paediatric shock, we aimed to assess the diagnostic accuracy and inter-rater reliability of cardiac point-of-care ultrasound performed by credentialed paediatric emergency medicine physicians.
Methods
We conducted a retrospective observational cohort study at a large university-based children’s hospital system from July 2020 to November 2021. In the credentialing pathway at our institution, paediatric emergency medicine fellows and faculty complete pre-requisite education composed of more than 30 hours of didactics and 150 quality-assured point-of-care ultrasound scans. Following completion of pre-requisite training, credentialing for cardiac point-of-care ultrasound includes completion of at least 25 cardiac point-of-care ultrasound studies with adequate quality images, accurate interpretation, and completed documentation. Credentialed paediatric emergency medicine physicians included attending physicians, paediatric emergency medicine fellows and point-of-care ultrasound fellows. All were trained to perform cardiac point-of-care ultrasound for the qualitative evaluation of global ventricular systolic function, right and left ventricular size and pericardial effusion. All point-of-care ultrasound images obtained at our institution underwent routine quality assurance review on a weekly basis.
Patients with multisystem inflammatory syndrome who underwent cardiac point-of-care ultrasound during initial emergency department evaluation were included. Credentialed paediatric emergency medicine physicians performed bedside qualitative assessments of left ventricular systolic function (normal versus depressed) as part of comprehensive clinical evaluations. Interpretations were compared with (1) ongoing departmental quality assurance review (non-blinded) and (2) blinded paediatric cardiologist interpretation of stored point-of-care ultrasound images.
Subgroup analysis was performed for patients with “somewhat” depressed left ventricular systolic function identified by paediatric cardiology review to include borderline dysfunction into the spectrum of qualitative assessment for left ventricular systolic dysfunction. Diagnostic performance metrics and Cohen’s kappa were calculated.
Results
During the study period, a total of 1,388 children underwent cardiac point-of-care ultrasound examinations, and 79 examinations were performed for patients with multisystem inflammatory syndrome in children as part of their routine care in the emergency department. These 79 examinations were completed by 24 credentialed paediatric emergency medicine physicians, including 20 attendings, 3 paediatric emergency medicine fellows, and 1 point-of-care ultrasound fellow. Patients’ median age was 9 years [IQR 4–11] (Table 1). Depressed left ventricular systolic function was identified in 42% by credentialed paediatric emergency medicine physicians and 31% by cardiology.
Bedside interpretation and MIS-C cohort descriptive analysis

Table 1. Long description
A table comparing characteristics of children with normal and depressed left ventricular systolic function. The table has 4 rows and 5 columns. Column headers are Normal LVSF, Depressed LVSF, Total, and Age (years, IQR). Row labels include Age (years, IQR), Sex (Male), and Race/ethnicity with subcategories White, Black/AA, Hispanic, and Other. Row 1: Age (years, IQR), Normal LVSF: 8 (4-11), Depressed LVSF: 10 (7-13), Total: 9 (4-13). Row 2: Sex (Male), Normal LVSF: 24 (52.2), Depressed LVSF: 20 (58.8), Total: 44 (55.6). Row 3: Race/ethnicity, White, Normal LVSF: 5 (10.9), Depressed LVSF: 8 (24.2), Total: 13 (16.5). Row 4: Race/ethnicity, Black/AA, Normal LVSF: 10 (21.7), Depressed LVSF: 14 (42.4), Total: 24 (30.4). Row 5: Race/ethnicity, Hispanic, Normal LVSF: 25 (54.3), Depressed LVSF: 10 (30.3), Total: 35 (44.3). Row 6: Race/ethnicity, Other, Normal LVSF: 6 (13.0), Depressed LVSF: 1 (3.0), Total: 7 (8.9).
MIS-C = multisystem inflammatory syndrome in children; LVSF = left ventricular systolic function; AA = African American.
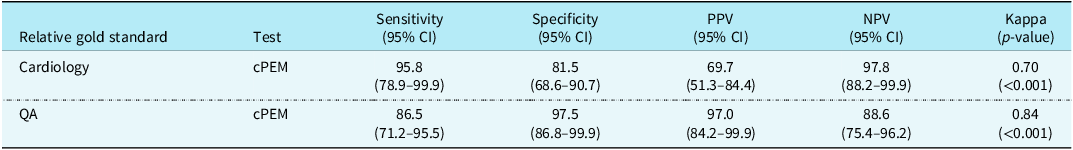
Compared with the quality assurance review, credentialed paediatric emergency medicine physician interpretation demonstrated a sensitivity of 87% and specificity of 98% (κ = 0.84, p < 0.001). Compared with cardiology, sensitivity was 96% and specificity 82% (κ = 0.70, p < 0.001) (Table 2). In the subgroup with “somewhat” depressed left ventricular systolic function (n = 21), bedside emergency medicine physician interpretation sensitivity was 95% compared with cardiology (Table 3).
Diagnostic accuracy of bedside cPEM for LVSF in MIS-C (N = 79)

Table 2. Long description
A table comparing diagnostic accuracy metrics for cPEM in cardiology and QA. The table has 2 rows and 6 columns. Column headers are Relative gold standard, Test, Sensitivity (95% CI), Specificity (95% CI), PPV (95% CI), NPV (95% CI), and Kappa (p-value). Row 1: Cardiology, cPEM, 95.8 (78.9-99.9), 81.5 (68.6-90.7), 69.7 (51.3-84.4), 97.8 (88.2-99.9), 0.70 (<0.001). Row 2: QA, cPEM, 86.5 (71.2-95.5), 97.5 (86.8-99.9), 97.0 (84.2-99.9), 88.6 (75.4-96.2), 0.84 (<0.001).
cPEM = credentialed paediatric emergency medicine physicians; LVSF = left ventricular systolic function; MIS-C = multisystem inflammatory syndrome in children; QA = quality assurance review.
Diagnostic accuracy of POCUS for “somewhat” depressed LVSF group (N = 21)

Table 3. Long description
A table comparing the diagnostic accuracy of POCUS for a somewhat depressed LVSF group against QA/cardiology. The table has four rows and five columns. Column headers are Gold standard, Test, Sensitivity (95% CI), Specificity (95% CI), PPV (95% CI), and Kappa (p-value). Row 1: QA/cardiology, cPEM, 95 (75.1–99.9), 100 (2.5–100), 100 (82.4–100), 0.64 (0.002).
cPEM = credentialed paediatric emergency medicine physicians; QA = quality assurance review.
Discussion
In this cohort, cardiac point-of-care ultrasound performed by credentialed paediatric emergency physicians demonstrated high sensitivity and strong inter-rater reliability for detecting ventricular dysfunction, including for borderline or “somewhat” depressed left ventricular systolic function. These findings are consistent with prior paediatric point-of-care ultrasound literature but are now demonstrated in a single paediatric disease process with a high prevalence and broad spectrum of pathology.Reference Miller, Arichai and Gravel3–Reference Scott, Alade, Leung, Vaughan and Riley5 Multisystem inflammatory syndrome in children as well as other forms of inflammatory or infectious myocarditis in children can be associated with rapid clinical deterioration, and borderline systolic dysfunction is often one of the few warning signs.Reference Matsubara, Kauffman and Wang11–Reference Teele, Allan, Laussen, Newburger, Gauvreau and Thiagarajan14 Therefore, it seems prudent that paediatric cardiac point-of-care ultrasound should emphasise the importance of borderline systolic dysfunction in children, as well as the difficulty making the diagnosis at the bedside and even via advanced echocardiographic tools.
In our cohort, it is important to note that credentialed paediatric emergency medicine physicians and quality assurance review diagnosed depressed systolic function at higher rates than paediatric cardiology. These discrepancies are likely multi-factorial, requiring additional investigations to elucidate the aetiologies. However, high sensitivity and reasonable positive predictive value are the goals of a successful screening test. From a clinical perspective, the high sensitivity observed supports the role of cardiac point-of-care ultrasound as a screening tool in undifferentiated paediatric shock. In this context, prioritising sensitivity may be appropriate to guide early escalation of care, even at some expense of specificity, as long as there is supportive advanced imaging or paediatric cardiology consultative collaboration.
Limitations
This single-centre study may limit generalisability, particularly given the well-established training pathway and quality assurance review at our large university-based children’s hospital. All assessments were qualitative, reflecting current point-of-care ultrasound practice. The observed differences between interpretations highlight ongoing challenges in qualitative assessment of systolic function, particularly at the borderline range. Additionally, discrepancies may reflect differences in blinding, timing of imaging, and the inherent limitations of qualitative evaluation reviewing offline stored clips. Comprehensive echocardiograms were not used for comparison since they were typically done meaningfully later in the clinical course, often following either stabilisation via medical therapies or after a clinical decompensation.
Conclusion
These findings demonstrate that cardiac point-of-care ultrasound performed by credentialed paediatric emergency physicians is highly sensitive and reliable for detecting ventricular dysfunction, even at the borderline range. Derived from a single disease cohort, the implications extend to the broader population of children presenting with undifferentiated shock, where early bedside identification of myocardial dysfunction is critical to guiding resuscitation and escalation of care. As paediatric point-of-care ultrasound adoption continues to expand, its clinical impact as a frontline provider tool for goal-directed medical therapy warrants further investigation across diverse shock states.
Acknowledgements
None.
Financial support
This research received no specific grant from any funding agency, commercial or not-for-profit sector.
Competing interests
The author(s) declare none.
Ethical standard
Not applicable.



 Open access

