Cesarean delivery infections occur in up to 7% of the 1.3 million cesarean deliveries performed annually in the United States. 1 , Reference Yokoe, Christiansen and Johnson 2 These infections can present as superficial and deep wound infections, intra-abdominal abscesses, and endometritis. The bacterial flora of these infections is polymicrobial.Reference Smaill and Grivell 3 There are no specific guidelines for the prevention of cesarean delivery infections, but multiple recommendations have been made for general prevention of surgical site infections. Cesarean deliveries are unique in many aspects and general surgical guidelines may not be applicable to this specific population. Timing of antibiotics to prevent infections and protect newborns from unnecessary antibiotic exposure has been a controversial area until recently,Reference Sun, Ding and Liu 4 – Reference Mackeen, Packard, Ota, Berghella and Baxter 6 and appropriate weight-based dosing for pregnant women without validated body mass index measurements is not entirely clear.Reference Stitely, Sweet and Slain 7 There are few data on the best antibiotic for surgical prophylaxis.Reference Gyte, Dou and Vazquez 8 A recent review suggests that only 29% of 77 interventions evaluated for prevention of cesarean delivery infections have strong evidence to support their use.Reference McKibben, Pitts, Suarez-Cuervo, Perl and Bass 9 We sought to assess cesarean delivery infection prevention practices in academic medical centers across the continental United States.
A literature review for best evidence-based practices for the prevention of cesarean delivery infections was performed and a short survey was developed, focusing on antibiotic prophylaxis and antisepsis practices (Online Appendix A). All US residency programs for obstetrics and gynecology were identified through the Association of Professors in Obstetrics and Gynecology website (https://www.apgo.org/component/residencydirectory). Programs outside the continental United States were excluded and multiple residency programs within the same main hospital were consolidated. The charge nurse, clinical specialist, nurse educator, or nurse manager of each labor and delivery unit for the primary hospital in each residency program agreed to participate and was interviewed by telephone between August and December 2014. Data were collected on an electronic spreadsheet (Excel; Microsoft) and analyzed. This survey project was approved by Johns Hopkins University Institutional Review Board.
Two hundred nineteen residency programs were identified and 198 hospitals met the inclusion criteria; of these, 197 participated in the telephone interview.
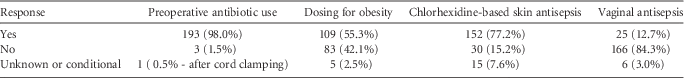
Of the 197 hospitals, 193 (98.0%) used antibiotics prior to skin incision for cesarean deliveries. One hospital dosed antibiotics after cord clamping and 3 hospitals did not universally use antibiotic prophylaxis. One hundred seventy-nine hospitals (90.9%) used first-generation cephalosporins, and 5 hospitals used combination therapy with azithromycin (4 hospitals) or metronidazole (1 hospital). Five hospitals prophylactically administered second-generation cephalosporins, 2 hospitals used ampicillin, and 2 used clindamycin. Only 109 hospitals (55.3%) consistently used higher doses of antibiotics for obese patients. Three interviewees did not know if dosing was modified for obesity and 2 hospitals sometimes adjusted the dose for obese patients.
One hundred fifty-two hospitals (77.2%) used some form of chlorhexidine-based preoperative skin antisepsis prior to Caesarean delivery. Twelve hospitals used either chlorhexidine skin antisepsis or a povidone-iodine–based skin preparation, depending on physician preference, and 3 interviewees were not sure of the type of skin antisepsis used.
Twenty-five hospitals (12.7%) consistently used vaginal preoperative antisepsis prior to cesarean delivery surgery and 6 additional hospitals sometimes used vaginal preoperative antisepsis, depending on physician preference (Table 1). Although not specifically asked, all hospitals that used vaginal antisepsis used povidone-iodine.
Infection Prevention Practices for Cesarean Delivery Surgeries in 197 Hospitals

NOTE. Data are no. (%) of hospitals.
Cesarean delivery infections cause significant morbidity to mothers with new babies. There are no consolidated guidelines specifically for the prevention of surgical site infections in women undergoing cesarean delivery. The 2013 guidelines for surgical prophylaxisReference Bratzler, Dellinger and Olsen 10 and the 2011 American College of Obstetrics and Gynecology Practice Bulletin 5 recommend cefazolin before skin incision for cesarean delivery surgery and weight-based dosing for obesity, acknowledging that there is limited evidence for these recommendations.
Our study found that some interventions are widely accepted and consistently used and others are inconsistently implemented or not used. We found the most consistency in the use of preoperative antibiotics prior to skin incision, with some variability in the type of antibiotic used and significant variability in dosing for obesity.
Several other adjunctive interventions have been investigated to reduce the incidence of post–cesarean delivery infections. Washing with chlorhexidine prior to surgery has been shown to reduce infections in orthopedic patients and in coronary artery bypass surgery patients but not in general surgery.Reference Webster and Osborne 11 There is some evidence that chlorhexidine-alcohol antisepsis, compared with povidone-iodine with alcohol, reduced surgical site infections in clean surgery and that alcohol-based antiseptics are more effective than aqueous antiseptics.Reference Dumville, McFarlane and Edwards 12 There are not enough data to recommend the use of chlorhexidine antisepsis in preventing infection outcomes specifically in cesarean delivery patients.Reference Hadiati, Hakimi, Nurdiati and Ota 13 Most of the hospitals we surveyed used some form of chlorhexidine-based skin antisepsis prior to surgery.
Multiple studies have shown that vaginal antisepsis with povidone-iodine in women undergoing cesarean delivery, particularly in women with ruptured membranes prior to surgery, reduced by 50% the incidence of postoperative endometritis.Reference Haas, Morgan and Contreras 14 We found that very few academic centers are using povidone-iodine vaginal antisepsis despite the strong evidence favoring this intervention.
One limitation of our study is that the nurses we interviewed may not be familiar with all practices in their units. In order to mitigate this concern, we interviewed only charge nurses, clinical specialists, nurse educators, and nurse managers to select for the more experienced nurses in each unit.
Another limitation is that our study assessed recommended standards of care in labor and delivery units and not actual practice. It has been shown that only 57% of women actually receive preoperative prophylactic antibiotics in practice.Reference Brubaker, Friedman and Cleary 15 This may be partly related to the emergent nature of some cesarean deliveries.
We found significant variability in the practices to prevent cesarean delivery infections in academic centers across the United States. Additional clinical trials and specific guidelines are needed to better define best practices in this patient population.
ACKNOWLEDGMENTS
Financial support. None reported.
Potential conflicts of interest. All authors report no conflicts of interest relevant to this article.
SUPPLEMENTARY MATERIALS
To view Supplementary Materials for this article, please visit http://dx.doi.org/10.1017/ice.2015.161