


Dear Editors,
We are so glad to hear of the interest in our work titled ‘Comparative study of the efficacy of topical steroid and antibiotic combination therapy versus oral antibiotic alone when treating acute rhinosinusitis’. I would like to reply to the comments made in the above-mentioned letter.
First, we shall address the comment ‘sample size of just 40 patients does not seem to be appropriate to derive a conclusion…’. Before we start any study, we determine the sample size based on a previously calculated standard international equation, and we respect the number obtained from the equation. In our study, optimal sample size was calculated according to the following equation:Reference Lwanga and Lemeshow1
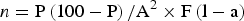 $$n = {\rm P}{\rm} \left( {100{\rm} - {\rm} {\rm P}} \right){\rm} /{\rm} {\rm A}^2 \times {\rm} {\rm F}{\rm} \left( {{\rm l}{\rm} - {\rm} {\rm a}} \right)$$
Where n = sample size, A = 0.1 when F (1 − a) = 0.10, and P = prevalence of acute bacterial rhinosinusitis. Hence, when calculated with the desired confidence level of 95 per cent and standard error of 5 per cent, with prevalence of acute bacterial rhinosinusitis (‘P’) at 2 per cent,Reference Gwaltney, Wiesinger and Patrie2 where A = 0.1 and F (1 − a) = 0.10, the optimal sample size was 20 patients for each group. We could not change the results by increasing the sample size as we have to respect the methodology rules.
With regard to the second comment ‘The authors have compared oral amoxicillin to topical ofloxacin and steroid combination. This creates a treatment bias…’, our aim was to clinically evaluate the effects of a topical antibiotic and steroid combination therapy administered intranasally, versus an oral antibiotic used alone, when treating acute rhinosinusitis. The investigation of an intervention requires that a control group is compared to the study group, and the logical control group is the standard, widely used and internationally accepted reference. For this intervention, the logical control was amoxicillin, as used in our study. Amoxicillin is a first-line therapy in patients suspected of having acute bacterial sinusitis because of its general effectiveness, safety, tolerability, low cost and narrow spectrum.Reference Desrosiers, Frenkiel, Hamid, Low, Small and Carr3 Hence, there was no bias here, as we compared the efficacy of the variable of interest (topical antibiotic and steroid) with the standard, widely used and internationally recommended (by most guideline agencies) treatment for acute rhinosinusitis, which acted as the baseline or control.
In addition, randomised clinical trials have to compare between two variables (with other factors fixed) in order to test one variable against a standard control. The results obtained, either positive or negative, will be almost true to the fact, as researchers in this type of study use the natural control as a baseline. We followed the methodological rules here and so there is no bias.
The third comment made is: ‘the “amoxicillin group” may not be sensitive’. The Canadian guidelines for the treatment of acute bacterial rhinosinusitis in adults recommend amoxicillin as a first-line antibiotic therapy for sinusitis symptoms lasting longer than 7 days.Reference Desrosiers, Evans, Keith, Wright, Kaplan and Bouchard4 The recommended duration of therapy for this initial treatment is 10 days.Reference Wright and Frenkiel5 In addition, amoxicillin is capable of achieving a high concentration in the sinus fluid when recommended doses are used with eradication of Haemophilus influenzae, Moraxella catarrhalis, Streptococcus pneumoniae, Staphylococcus aureus and Streptococcus pyogenes, which are usually associated with acute bacterial rhinosinusitis.Reference Manning, Cummings, Flint and Haughey6
The fourth comment reads: ‘there are no reports of the efficacy of “topical” ofloxacin in acute sinusitis’. The advantages of topical nasal antimicrobials include easy administration, high local drug concentration and minimal systemic adverse effects.Reference Harvey, Psaltis, Schlosser and Witterick7 Many previous studies have illustrated the advantages of using topical ofloxacin, which is bactericidal against staphylococcus and streptococci species including methicillin-resistant S aureus.Reference de Lange de Klerk, Blommers, Kuik, Bezemer and Feenstra8 Intranasal topical antimicrobials have been used in cases of: recurrent staphylococcal nasal colonisation, atrophic rhinitis, rhinoscleroma and chronic rhinosinusitis.Reference Goh and Goode9 In addition, prophylactic intranasal application of amphotericin B has been used to prevent invasive aspergillosis in neutropenic patients, and prophylactic intranasal application of interferon α2 has been used to prevent rhinovirus infection.
The fifth comment made is: ‘It is not clear how the dose of 5 drops every 8 hours has been calculated and seems to be arbitrary’. The calculated dose of combined ofloxacin (0.26 per cent) and dexamethasone (0.053 per cent) for 10 days, administered nasally (5 drops in each nostril every 8 hours), is compatible with the minimum inhibitory concentrations of ofloxacin for typical bacterial pathogens of acute otitis media, as the minimum inhibitory concentration for penicillin-resistant S pneumoniae is about 2 µg/ml.Reference Dohar, Garner, Nielsen, Biel and Seidlin10, Reference Bluestone11 Furthermore, this dose was found to be therapeutically equivalent to oral amoxicillin-clavulanate in acute otitis media patients with a tympanostomy tube.12 In addition, the treatment is approved by the Food and Drug Administration for chronic suppurative otitis media in children older than 12 years. It is also indicated for the treatment of acute otitis media in children older than one year old with a tympanostomy tube.Reference Gates11
Although antibiotics have been the mainstay of therapy, recent evidence has suggested that intranasal corticosteroids can provide additional benefit when used as an adjunct.Reference Nayak, Settipane, Pedinoff, Charous, Meltzer and Busse13
Finally, we would like to thank the author for the valuable recommendation made. We will consider this for our next project. We would also like to thank them for their interest in our work. We hope our reply, which focuses on the methodological steps made, clearly addresses the points raised.


